

When a system is ‘violently opposed’ to low-cost, effective healing, it tells you exactly who they are protecting and it’s not the patients. Real science shouldn’t be afraid of repurposed tools. It’s time to choose people over profits. - Susan
Introduction
From time to time, I share patient stories provided either by the treating physician or by the patients themselves. These are not abstract clinical summaries or statistical constructs; they are accounts of real people confronting serious illness and trying to reclaim their lives. Behind every laboratory value, scan, or pathology report is a human being navigating fear, hope, uncertainty, and resilience. These stories deserve to be told.
Within modern evidence-based medicine, such accounts are often dismissed as “anecdotal” and therefore regarded as scientifically weak. In oncology in particular, the prevailing view is that only large, randomized trials can establish the validity of a treatment. While rigorous trials are essential for determining efficacy and safety (of a single drug), the history of medicine reminds us that discovery rarely begins with a randomized study. It begins with observation. Physicians notice something unexpected in a patient. Treatment produces a response that defies conventional expectations. A pattern begins to emerge.
It is important to recognize that large randomized controlled trials are impractical for metabolic treatment strategies that rely on a combinations of repurposed drugs and nutraceuticals designed to exert multi-axis metabolic pressure on tumor biology. These interventions typically involve multiple inexpensive agents used in adaptive combinations, making them difficult to study within the traditional pharmaceutical trial framework. For this reason, careful clinical observation and well-documented case reports and case series may provide important early signals that deserve further investigation (this concept of multi-axis metabolic pressure will be discussed in greater detail in an upcoming post).
Over the last few years, I have become aware of hundreds of such cases—patients whose outcomes appear inconsistent with the predictions of standard oncologic thinking. Any single case must be interpreted with caution, and anecdotes alone cannot establish proof. Yet when similar observations occur repeatedly across many independent patients, they begin to represent something more than coincidence. They become clinical signals—observations that deserve careful documentation and scientific investigation rather than reflexive dismissal. It is worth remembering that some of the most important advances in medicine began exactly this way: with clinicians paying attention to what their patients were telling them. The purpose of presenting these cases is not to claim definitive answers, but to invite curiosity, humility, and further study. Progress in medicine has always depended on our willingness to observe carefully, question prevailing assumptions, and remain open to the possibility that biology sometimes behaves in ways we do not yet fully understand.
Case Report – Mr. D.
I thank Dr. F who provided the following report on his patient.
When I first met him, he did not look like a man living with stage IV cancer.
He walked slowly into the room, careful with his steps, the quiet fatigue of illness visible in his posture but not in his spirit. His vision had been damaged by prior strokes, leaving him with hemianopsia, and his body carried the scars of years of disease and treatment. Yet what struck me most was not the burden he carried—it was the calm determination in his voice.
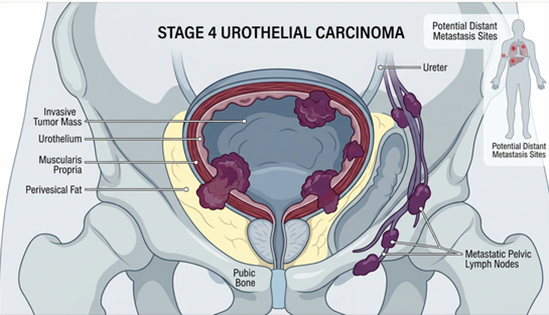
He had already been through more than most patients endure. Diagnosed with poorly differentiated stage IVB urothelial cancer, he had undergone the standard treatments offered by modern oncology: intravesical BCG, Padcev, and immunotherapy with Keytruda. The treatments were aggressive, and the complications were real—autoimmune hepatitis, hypothyroidism, chronic kidney disease, anemia, thrombocytopenia, and bilateral strokes that permanently altered his vision.
For many patients, this is the point where hope begins to quietly fade.
But that was not the case for him.
He spoke not about statistics or survival curves, but about living. He wanted more time with his family. More mornings waking up in his own home. More ordinary days that most of us take for granted.
Medicine often presents itself as a field of certainty—protocols, guidelines, randomized trials. But the reality physicians face every day is far more human and far less predictable. Patients arrive not as clinical problems but as stories still being written.
By the time he came to our clinic in August 2024, conventional therapy had taken its toll. His body had paid a high price for treatment, and the options remaining were limited. Rather than escalating toxicity, we began something far simpler: a metabolic approach using repurposed medications with long safety records, including ivermectin and fenbendazole, later transitioned to mebendazole. We spoke about limiting carbohydrates and a whole food ketogenic diet which he embraced enthusiastically.
At the time, there was no certainty that it would help.
There rarely is in medicine.
But medicine is also a field built on observation, humility, and the quiet recognition that biology sometimes behaves in ways we do not yet fully understand.
Over the months that followed, something remarkable began to appear—not in dramatic headlines or breakthrough announcements, but in the quiet language of radiology reports. CT scans. Follow-up imaging. And eventually a PET scan.
Each one telling the same story.
No active disease.
The patient had gone into remission or NED -No evidence of disease
This case report is not written to challenge oncology or dismiss the advances that modern cancer therapy has achieved. Instead, it is written for a much simpler reason.
Because sometimes a patient’s story reminds us that medicine still has room for humility—and that hope can occasionally arrive from the most unexpected places.
And sometimes, the patient teaches us more than the textbooks ever could.
Most oncologists and traditionally trained physicians have not yet embraced the metabolic approach to cancer and continue to rely primarily on the long‑standing Somatic Mutation model that has guided oncology for decades. This difference in perspective can make it harder for them to fully recognize and integrate emerging evidence that views cancer, at least in part, as a metabolic disease. At the same time, it is important to remember that genuine healing is most likely when there is a respectful partnership between an informed, engaged patient and a compassionate, open‑minded clinician who is willing to explore a full range of safe, evidence‑informed options together. - PAUL
PS: I have received many questions regarding the patients’ repurposed medication.
He was only taking Ivermectin and Mebendazole, no other medications or nutraceuticals. The dose of ivermectin was 0.4 mg/kg and the dose of mebendazole was 100 mg twice a day.

yes, the 2 pts i’ve seen respond the best to IVM and MBZ are bladder ca pt’s, one w/ a 12 cm tumor only T1 at surg and a young healthy man w/ presumed met to liver (no bx’s done) both shriking on IVM and MBZ, thanks for sharing!
Have been following you and the other good docs since covid mess. Thank you. Have your book.