

INTRODUCTION
Colorectal cancer (cancer of the colon or rectum) affects nearly 2 million people worldwide every year and is one of the leading causes of cancer death. But it’s also one of the cancers scientists understand best, because it doesn’t appear suddenly. Instead, it develops slowly and predictably, usually starting as a small, harmless growth called a polyp that can sit quietly in the colon for years before - occasionally - turning into cancer.
That slow, step-by-step process starts with damage to a single gene called APC (short for “adenomatous polyposis coli”). Almost every case of colon cancer, whether inherited or not, begins with this same broken gene. Understanding APC helps explain not just how colon cancer starts, but why it takes so long to develop, and why screening and removing polyps is one of the most effective ways to prevent cancer altogether.
Think of APC as a gatekeeper standing at the entrance to a dangerous path. When the gatekeeper is at his post, the gate stays shut and everything runs smoothly. When he’s removed, the gate swings open - but that alone doesn’t mean disaster follows. It just means trouble can now get in. Something else still has to walk through.
HOW COMMON IS COLON CANCER, AND WHY
Colon cancer is the third most commonly diagnosed cancer and the second deadliest, worldwide. On average, about 1 in 23 men and 1 in 25 women will develop it in their lifetime. Rates are highest in North America, Australia, and Western Europe. Interestingly, when people move from a low-risk country to a high-risk one, their own risk rises to match their new home within a generation or two - a strong clue that diet and lifestyle, not just genes, play a huge role.
Diets heavy in processed meat, refined carbs, and saturated fat appear to raise risk, while fiber, vegetables, and whole grains seem protective. Obesity, inactivity, heavy drinking, and smoking add to the risk as well. Scientists are also increasingly focused on the trillions of bacteria that live in our gut (the “microbiome”), which can influence inflammation and cancer risk in the colon.
One worrying trend: colon cancer is becoming more common in adults under 50, for reasons that aren’t fully understood yet, but likely involve some combination of diet, weight, and changes in gut bacteria.
Most cases (about 70%) happen with no strong family history at all. Only about 5-10% are caused by a clearly inherited condition. One of those inherited conditions is what led scientists to discover APC in the first place.
HOW SCIENTISTS DISCOVERED APC
Doctors have known since the 1800s that some families develop colon cancer at an alarming rate. Certain patients would develop hundreds or even thousands of polyps in their colon starting as teenagers, and nearly all of them eventually developed colon cancer if the colon wasn’t removed. This condition came to be called familial adenomatous polyposis, or FAP.
By the mid-1900s, doctors realized FAP was inherited in a simple, predictable pattern: each child of an affected parent had a 50/50 chance of inheriting it. That pattern pointed to a single gene being at fault. In the 1980s, using DNA analysis of large families with FAP, researchers tracked the culprit down to a specific spot on chromosome 5, and the gene was eventually identified and named APC.
This discovery mattered enormously - and not just for the rare families with FAP. Scientists soon discovered that the very same gene, APC, was also damaged in the vast majority of “ordinary” colon cancers that had nothing to do with inherited family risk. In other words, FAP families and everyday colon cancer patients were experiencing the same underlying process - one was just a much faster, more extreme version of the other.
This is also where the “gatekeeper gene” idea was born. A gatekeeper gene is one whose entire job is to prevent a tissue from growing out of control. When it fails, the tissue doesn’t necessarily become cancerous right away - but the door is now open for cancer to eventually develop.
WHAT APC ACTUALLY DOES
The APC gene contains the instructions for building a very large protein - one of the biggest proteins tumor-suppressor genes make in the whole body. Rather than doing one specific chemical job, this protein acts more like a scaffold or a central hub, physically connecting with dozens of other proteins involved in cell growth, cell shape, and cell division.
Most harmful mutations in APC cause the cell to build only a truncated, unfinished version of this protein - like a tool missing its working end. That broken protein can no longer do several of its most important jobs at once, which is part of why losing APC causes so much disruption throughout the cell.
To understand what those jobs are, it helps to understand how the lining of the colon normally works.
THE COLON’S SELF-RENEWING LINING
The inside lining of the colon is one of the fastest-renewing tissues in the entire body - it completely replaces itself every four to seven days. This constant renewal happens inside millions of tiny pits called crypts. At the base of each crypt sit stem cells, which divide to create new cells. Those new cells then move upward, maturing along the way, until they reach the surface, do their job for a short while, and are shed off entirely.
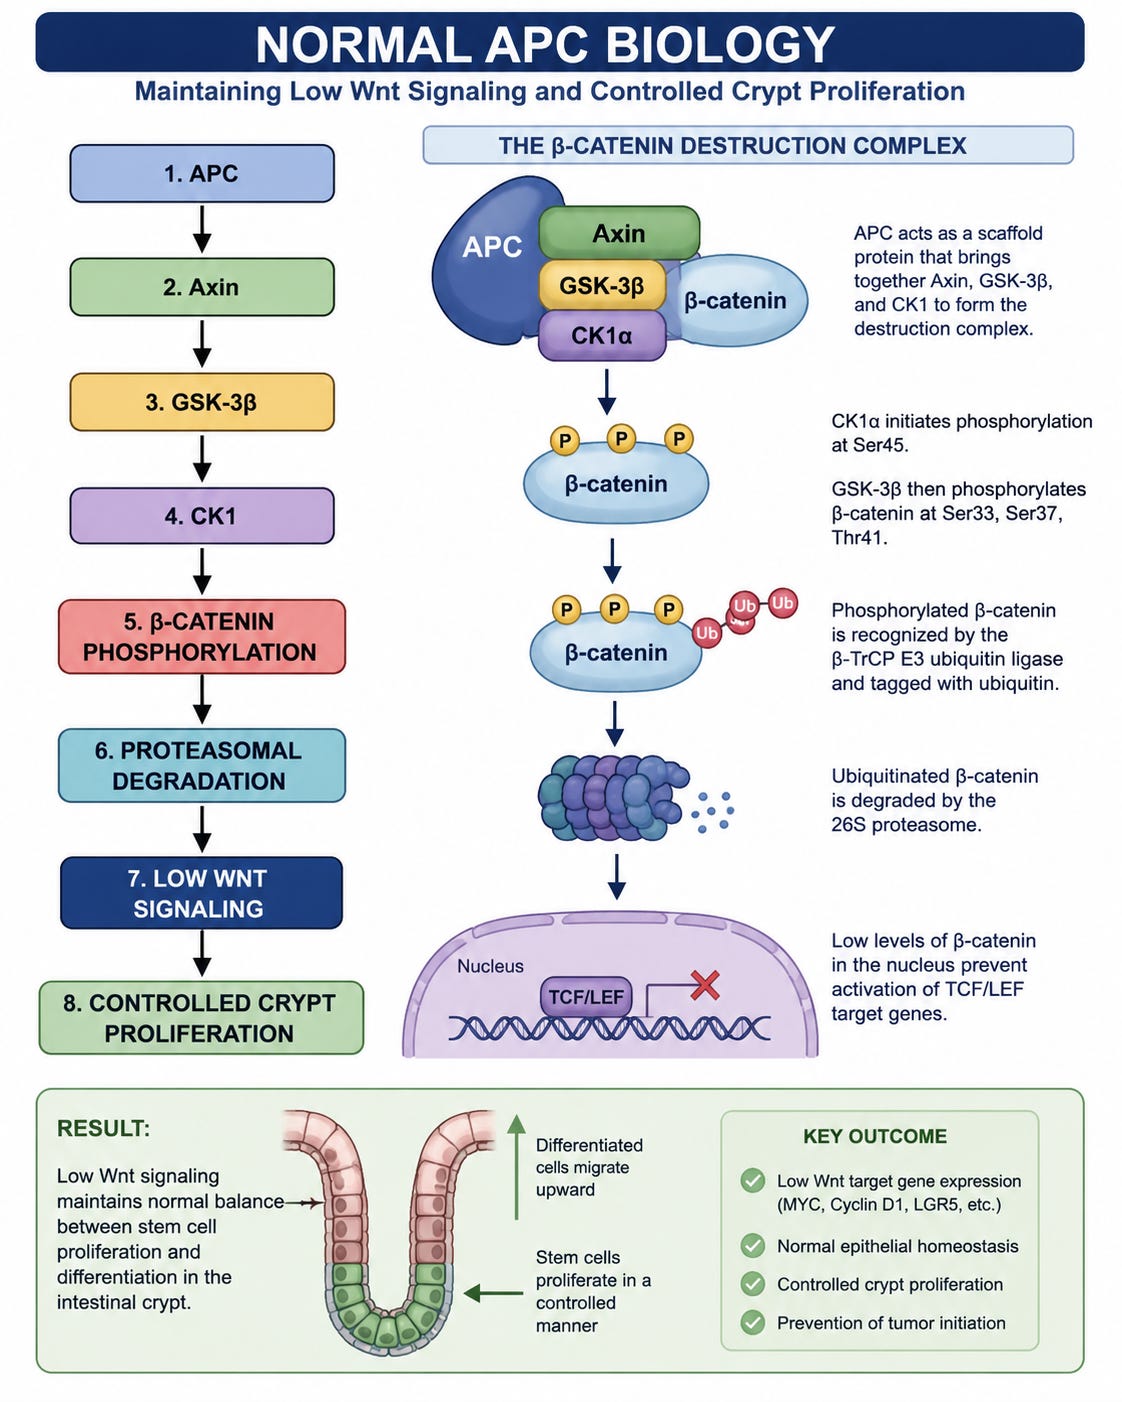
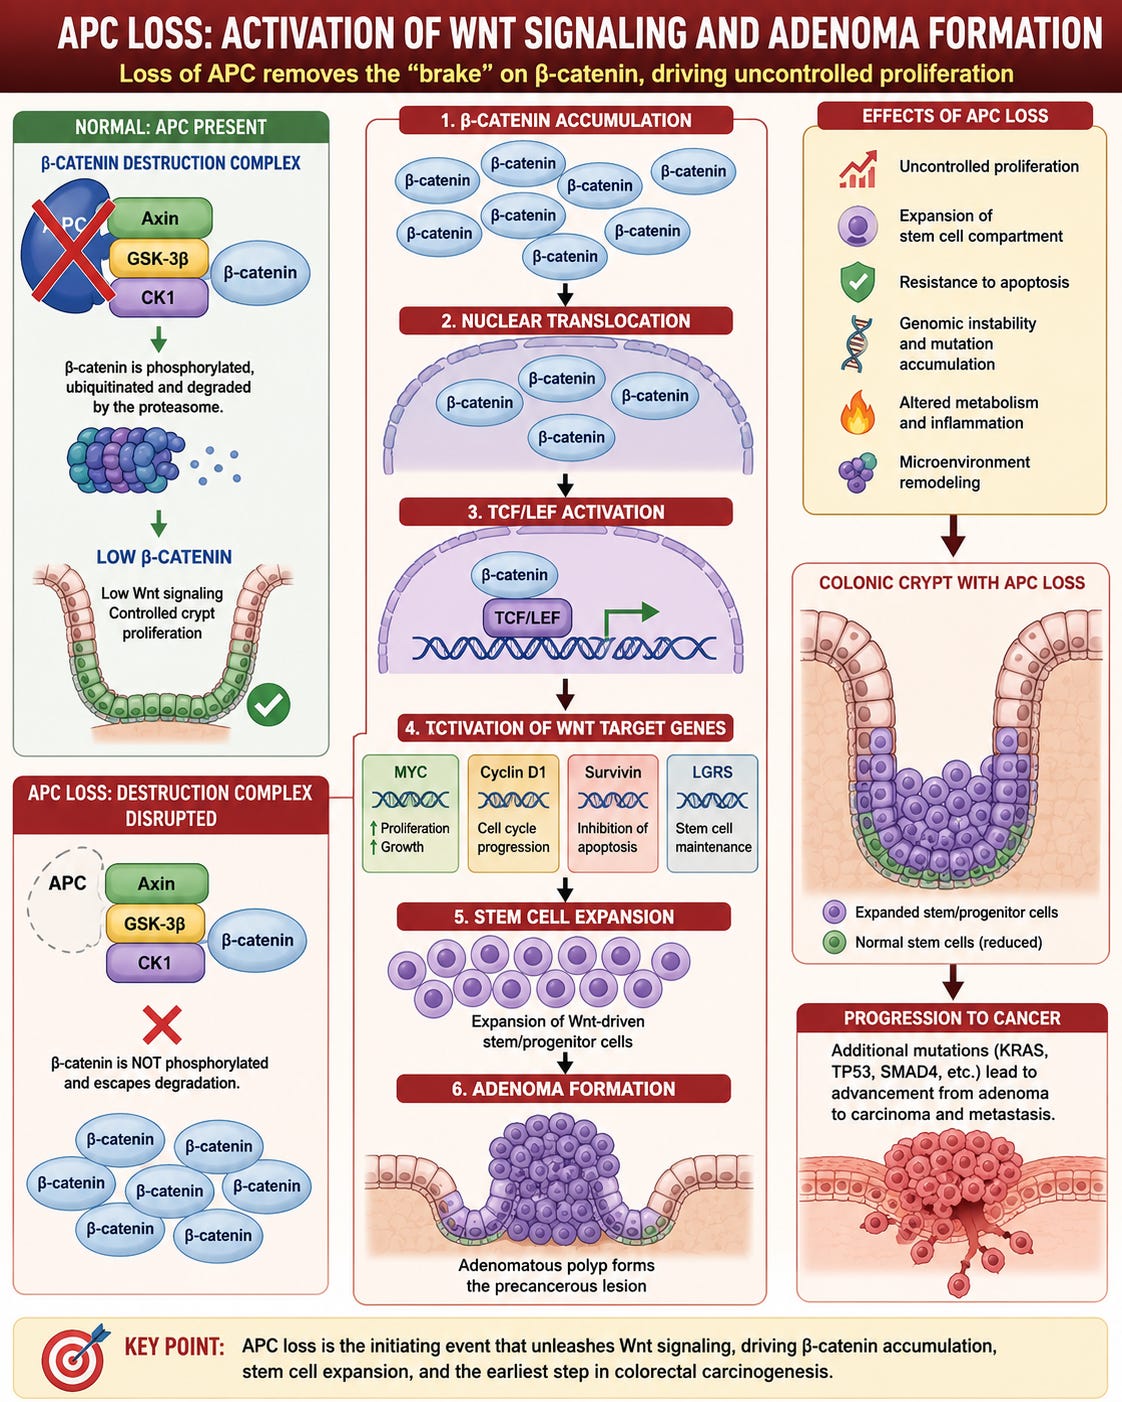
For this system to work properly, cells need to know exactly where they are in the crypt and what they should be doing at that stage - dividing, maturing, or dying. A major signal that tells cells this is called Wnt signaling (pronounced “wint”). Wnt signals are strong at the very base of the crypt, telling cells there to keep dividing like stem cells. As cells move upward and away from the base, Wnt signals fade, telling those cells it’s time to stop dividing and mature instead.
APC’s main job is to help enforce this fade-out. It does this by controlling a protein called β-catenin (beta-catenin). Think of β-catenin as a proliferation switch: when it builds up inside a cell, that cell turns on genes for growth and division. Normally, APC works together with a few partner proteins to continuously find and destroy β-catenin, keeping it in check everywhere except right at the crypt base where Wnt signaling is meant to be strong. This constant destruction is like a thermostat, keeping proliferation switched off except exactly where and when it’s needed.
WHAT HAPPENS WHEN APC IS LOST
Without a working APC protein, this destruction system breaks down. β-catenin can no longer be cleared out efficiently, so it builds up inside the cell - even when there’s no legitimate Wnt signal telling it to. In effect, the cell gets stuck believing it’s still at the base of the crypt, receiving a “keep dividing” message all the time, everywhere, regardless of where it actually is.
The consequences ripple outward from there:
● Cells keep dividing instead of maturing and moving on.
● Cells resist the normal self-destruct signal (apoptosis) that would otherwise clear out damaged or unnecessary cells.
● Cell division becomes sloppier, increasing the odds of copying errors and chromosome mistakes.
● The overall architecture of the crypt - which cells go where, and when - starts to break down.
None of this instantly creates a tumor. But it does convert an orderly, self-limiting renewal process into a chronic, unrestrained one - fertile ground where further problems can accumulate over time. That’s the essence of being a “gatekeeper”: APC’s loss doesn’t cause cancer directly, but it opens the gate that makes cancer possible.
FROM A SINGLE CELL TO A VISIBLE POLYP
When one stem cell loses APC, it out-competes its normal neighbors and its descendants gradually take over the entire crypt - a process called monoclonal conversion. Eventually, that abnormal crypt can split into two (”crypt fission”), and this spreading process repeats until millions of abnormal cells form a visible polyp.
Interestingly, these polyps typically grow very slowly, often just a few millimeters over many years. That’s because losing APC alone doesn’t remove every safety mechanism in the body. The immune system still patrols for abnormal cells, programmed cell death still clears many of them out, the protective lining (”basement membrane”) around the polyp is still intact, blood vessel growth into the polyp is limited, and - crucially - the other genetic changes needed for a full-blown cancer haven’t happened yet.
This slow-growing, precancerous phase is a huge opportunity: it’s exactly why colonoscopies, which detect and remove polyps before they become dangerous, are such an effective way to prevent colon cancer altogether.
THE STEP-BY-STEP PATH TO CANCER
In the 1980s and 90s, researcher Bert Vogelstein and colleagues showed that colon cancer typically develops through a reliable sequence of genetic hits, not a single random event. It usually starts with APC damage, followed later by damage to a gene called KRAS, and then to other genes such as TP53 and SMAD4, along with a general increase in genetic instability.
This discovery reshaped how scientists think about cancer altogether: instead of one catastrophic mutation causing disaster overnight, cancer behaves more like evolution happening inside a person’s own body over years or decades. Each new genetic change gives a small survival or growth advantage to the cells that carry it. Those cells slowly out-compete their neighbors, and the process repeats, adding complexity and danger with each round - not unlike natural selection playing out among microscopic populations of cells.
GENETIC CHAOS: CHROMOSOME AND CELL-STRUCTURE PROBLEMS
APC does more than manage β-catenin. It also helps cells divide their chromosomes correctly and helps maintain the internal skeleton that gives cells their shape and lets them move properly. When APC is lost, cell division becomes error-prone, sometimes leaving cells with too many or too few chromosomes - a state called chromosomal instability. Because a single faulty division like this can disrupt hundreds or thousands of genes at once, it dramatically speeds up the chaotic genetic experimentation that eventually produces more dangerous cancer cells. APC loss also disorganizes the normal structure of the crypt itself, which matters because healthy tissue architecture is itself a natural barrier against cancer.
WHY SOME CELLS BECOME “IMMORTAL” STEM-LIKE CELLS
Losing APC also causes ordinary cells to take on stem-cell-like properties they shouldn’t have - continuing to act like the “renewal” cells at the crypt base, even once they’ve moved away from it. Unfortunately, these stem-like cells also tend to resist chemotherapy, radiation, and immune attack, making them a likely source of future cancer cells.
Fortunately, the body has a backup defense: many APC-damaged cells enter a permanent, non-dividing state called senescence - essentially forced retirement for a cell. Only once additional mutations manage to also disable this backup defense can real progression toward cancer continue.
APC loss and the switch toward Warburg metabolism
Normal, healthy colon cells get most of their energy the efficient way — burning fuel through oxidative phosphorylation in the mitochondria. But when the APC gene is inactivated, one of the earliest and most consistent changes inside the affected cells is a shift toward aerobic glycolysis — burning glucose the fast, “wasteful” way, without fully oxidizing it, even though plenty of oxygen is available. This is the Warburg effect, first described by Otto Warburg nearly a century ago as a strange quirk of cancer cells. For decades it was viewed as a byproduct of malignancy rather than a cause. We now know it starts remarkably early, often in polyps that haven’t come close to becoming invasive cancer yet — and APC loss is one of the first triggers.
The mechanism runs through the same pathway APC normally keeps in check. Without functional APC, β-catenin builds up and enters the nucleus, where it turns on genes for glucose transport (notably GLUT1) and the enzymes of glycolysis. It also drives strong, sustained expression of MYC, a transcription factor that acts almost like a master metabolic amplifier — ramping up glucose uptake, glutamine use, ribosome production, and nucleotide synthesis all at once. In effect, the very same signal that tells the cell “keep dividing” also tells it “start eating differently,” rewiring metabolism to match the biosynthetic demands of constant proliferation.
The reason this matters is that dividing cells don’t just need ATP — they need raw materials: lipids for new membranes, nucleotides for new DNA, and amino acids for new proteins. Glycolysis, even though it’s a less efficient way to generate energy per glucose molecule than mitochondrial respiration, produces an abundance of intermediate molecules that can be diverted into these biosynthetic pathways. So the Warburg shift isn’t really about energy shortage — it’s about retooling the cell’s chemistry for building bulk instead of just staying alive. This is why it’s often described as an “anabolic” metabolism: its purpose is growth, not just survival.
Alongside this glycolytic shift, APC-deficient cells often show altered mitochondrial behavior — more fragmentation, less fusion, and a mild drop in oxidative efficiency, accompanied by higher levels of reactive oxygen species (ROS). This looks like a downside at first glance, but moderate ROS and reduced mitochondrial oxidation may actually help the tumor evolve, by increasing the mutation rate and pushing cells to rely even more heavily on glycolysis. Importantly, this metabolic reprogramming isn’t an all-or-nothing switch that happens the moment APC is lost — it’s gradual. Early adenomas show a modest increase in glycolysis while still retaining substantial mitochondrial function; the full Warburg phenotype seen in advanced colorectal cancer builds up over time, reinforced by later mutations in genes like KRAS and TP53, chronic inflammation, and hypoxia as the tumor grows. APC mutation, in other words, opens the door to this metabolic transition — it doesn’t complete it on its own.
CANCER DOESN’T GROW ALONE: THE SURROUNDING ENVIRONMENT MATTERS
A growing polyp doesn’t exist in a vacuum - it constantly interacts with surrounding blood vessels, immune cells, and the trillions of bacteria living in the gut.
APC and Inflammation
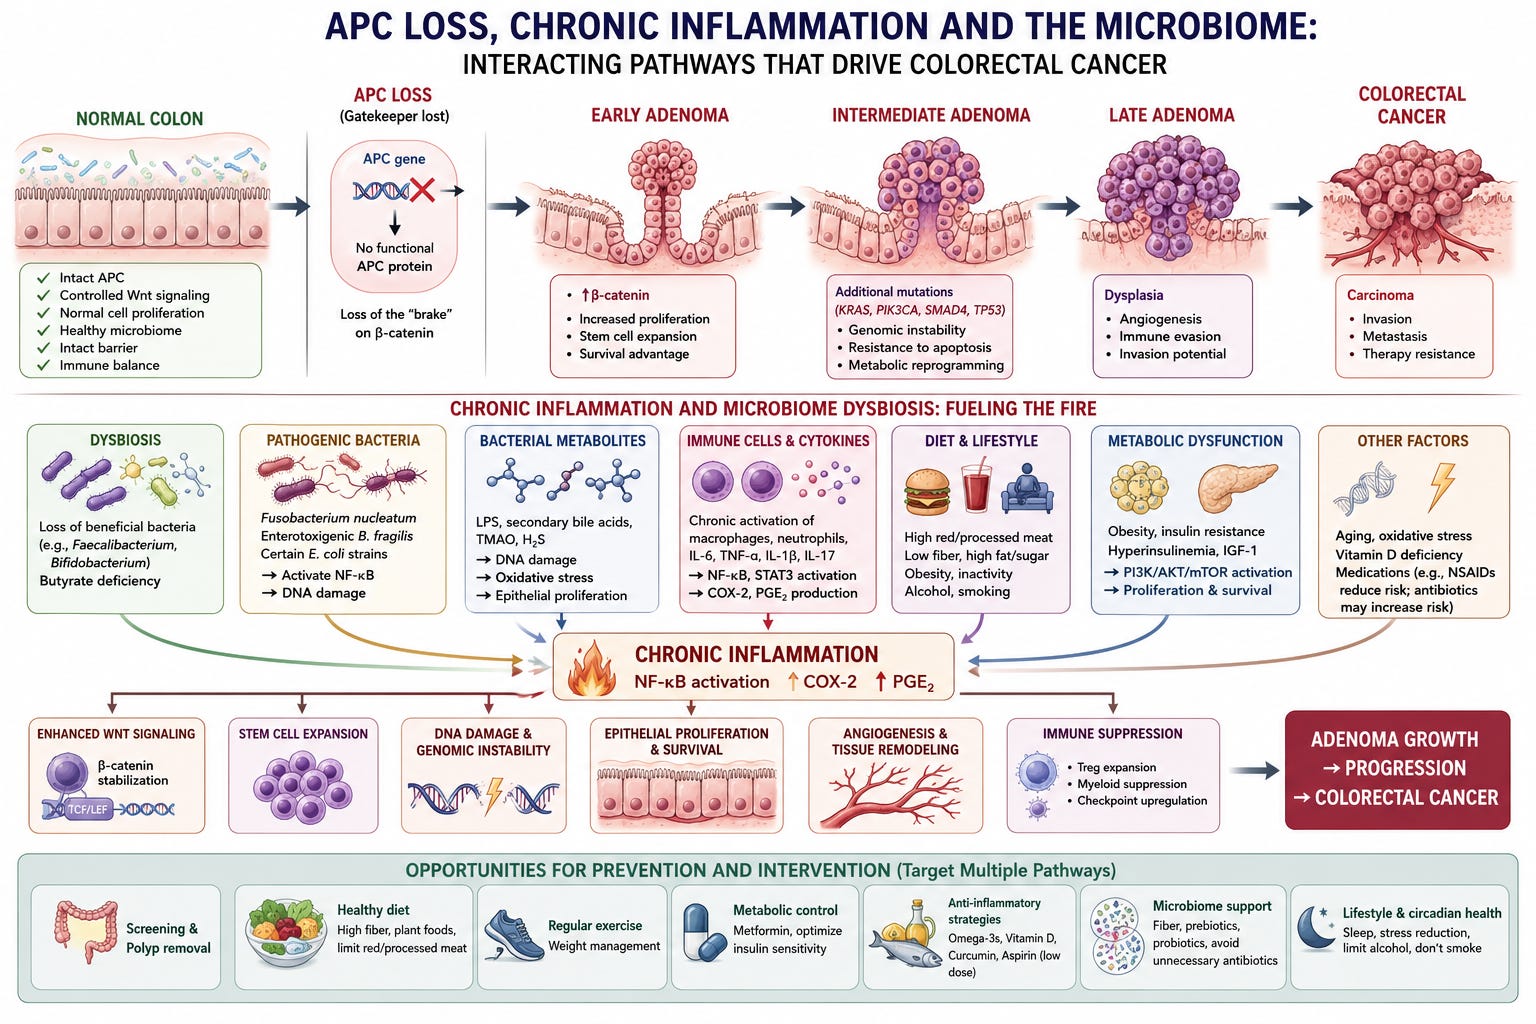
Inflammation is now recognized as a major driver of colorectal carcinogenesis, and loss of APC contributes to the development of a chronic pro-inflammatory tumor microenvironment. Beyond its well-established role in regulating Wnt/β-catenin signaling, APC loss activates inflammatory pathways that promote epithelial proliferation, inhibit apoptosis, and support tumor progression. Central to this process is NF-κB, a master regulator of inflammation that interacts closely with β-catenin signaling. This crosstalk creates a self-perpetuating cycle in which inflammatory cytokines reinforce Wnt activation, while downstream mediators such as cyclooxygenase-2 (COX-2) and prostaglandin E₂ (PGE₂) stimulate proliferation, angiogenesis, invasion, immune suppression, and resistance to cell death. Additional cytokines, particularly IL-6 and TNF-α, further amplify these effects through activation of the JAK/STAT3 and NF-κB pathways, facilitating progression from adenoma to carcinoma.
The inflammatory milieu is further shaped by environmental and metabolic factors. Intestinal dysbiosis, characterized by enrichment of organisms such as Fusobacterium nucleatum, enterotoxigenic Bacteroides fragilis, and certain strains of Escherichia coli, promotes chronic inflammation, DNA damage, and epithelial proliferation while depletion of butyrate-producing bacteria removes important anti-inflammatory and barrier-protective effects. A Western diet may exacerbate this process by increasing production of pro-inflammatory secondary bile acids, whereas obesity and insulin resistance contribute through chronic low-grade inflammation and activation of insulin/IGF-1 signaling pathways. Collectively, these interacting processes illustrate that APC loss initiates far more than a genetic defect—it establishes an inflammatory ecosystem that cooperates with metabolic reprogramming and Wnt signaling to drive colorectal cancer. This broader understanding helps explain why APC mutation alone is insufficient for malignant transformation and highlights inflammation as an important therapeutic target.
The immune system also plays a constant, active role, patrolling for and eliminating abnormal cells - a process scientists call immune surveillance. The abnormal cells that do survive are typically the ones that have found some way to hide or blend in, a process called immunoediting. Unfortunately, losing APC itself seems to help tumors dampen the immune response against them, partly explaining why some immune-based cancer treatments don’t work as well in these tumors.
Finally, as a polyp grows beyond the point where it can get enough oxygen and nutrients by simple diffusion, it triggers the growth of new blood vessels (angiogenesis) to feed itself further - another milestone on the road toward a more dangerous tumor.
WHY LOSING APC USUALLY ISN’T ENOUGH TO CAUSE CANCER
If APC damage alone were enough to cause cancer, then every single polyp - and every person with hundreds or thousands of polyps from FAP - would inevitably develop cancer. But that’s not what happens. Most polyps stay harmless for a lifetime.
That’s because multiple backup safety systems still have to fail before cancer can take hold: programmed cell death, forced cellular retirement (senescence), an intact protective lining around the polyp, limited blood vessel growth, an active immune system, and - above all - the absence (so far) of additional damaging mutations in other important genes. APC opens a door. Whether anything actually walks through it depends on everything else that happens next, often over the course of many years.
TREATMENT CHALLENGES AND WHAT COMES NEXT
Despite being the very first domino to fall in most colon cancers, APC itself has proven to be a frustratingly difficult drug target. That’s because APC is a “tumor suppressor” - something that’s missing or broken - and it’s generally much easier to design a drug that blocks an overactive protein than one that restores a broken one.
As a result, most current research instead targets the downstream effects of losing APC - for example, drugs aimed at blocking the same Wnt/β-catenin pathway further down the line. Unfortunately, this pathway is also essential for healthy gut lining renewal, so blocking it too strongly risks serious side effects, and no such drug has yet found major clinical success.
This has pushed researchers toward complementary strategies instead - targeting inflammation, tumor metabolism, or the surrounding tumor environment rather than APC or β-catenin directly. Newer tools like single-cell gene sequencing and lab-grown “mini-guts” (organoids) are also revealing just how varied and adaptable colon tumors really are, reinforcing the idea that future treatments will likely need to combine multiple approaches at once.
Given how slowly this process unfolds, prevention remains our single best tool. Removing polyps during a colonoscopy - before they ever have the chance to accumulate additional dangerous mutations - remains one of the most effective cancer-prevention measures in all of medicine. Healthy diet, regular exercise, maintaining a healthy weight, and (for some people) preventive aspirin use may all help keep the environment around any early APC-damaged cells less favorable to further progression.
THE BIG PICTURE
The discovery of APC fundamentally changed how scientists understand cancer - showing that it develops gradually, through a long chain of events, rather than appearing overnight. As the “gatekeeper” of the colon’s lining, APC’s job is to hold a careful, ongoing balance between cell renewal, maturation, and cell death. When that gatekeeper fails, the door opens to trouble - but trouble still has to walk through, one step at a time, often over decades.
We now understand that APC’s influence stretches far beyond simple growth signals - touching chromosome division, cell metabolism, the immune system, inflammation, and even the bacteria living in our gut. Its loss destabilizes this entire network, not just one pathway. But because it takes so many additional hits and changes to actually produce a dangerous cancer, this slow-moving process gives us a rare and valuable opportunity: to catch and remove the problem years before it ever becomes truly dangerous.
The Five-Axis Metabolic Pressure Model and the Prevention of Colorectal Cancer
The adenoma–carcinoma sequence provides a unique opportunity for cancer prevention because APC mutation typically precedes invasive colorectal cancer by 10–20 years. During this prolonged period, genetically altered epithelial cells remain highly dependent on favorable metabolic and inflammatory conditions for continued progression. The Five-Axis Metabolic Pressure Model proposes that colorectal carcinogenesis can be slowed—or potentially interrupted—by simultaneously targeting the major biological processes that support tumor evolution rather than focusing on a single molecular pathway. This systems-based strategy recognizes that APC mutation initiates cancer, but inflammation, metabolic dysfunction, mitochondrial adaptation, and immune evasion determine whether adenomas ultimately progress to invasive disease.
The first axis aims to reduce metabolic pressure by lowering glucose availability and insulin/IGF-1 signaling through weight management, regular exercise, a Mediterranean or low-carbohydrate diet, intermittent fasting, and agents such as metformin or berberine, thereby reducing activation of the PI3K/AKT/mTOR pathway. The second axis targets mitochondrial function and stem-cell biology, recognizing that early adenomas undergo progressive metabolic reprogramming and expansion of stem-like cells. Lifestyle interventions together with selected repurposed drugs and nutraceuticals—including doxycycline, curcumin, EGCG, sulforaphane, and resveratrol—have been proposed to increase metabolic stress on these emerging neoplastic cells, although robust clinical evidence for cancer prevention with these agents remains limited. The third axis focuses on maintaining genomic and structural integrity by reducing oxidative stress and supporting normal cellular homeostasis.
The fourth axis targets the tumor microenvironment, seeking to suppress chronic inflammation through optimization of vitamin D status, increased intake of omega-3 fatty acids, diets rich in fiber, and, in appropriately selected individuals, low-dose aspirin, which inhibits COX-2-derived prostaglandin signaling. These measures also help preserve a healthy intestinal microbiome, encouraging butyrate-producing bacteria while limiting dysbiosis associated with colorectal carcinogenesis. Finally, the fifth axis seeks to restore immune surveillance and circadian health through adequate sleep, stress reduction, regular physical activity, correction of nutritional deficiencies, and maintenance of a diverse, fiber-rich diet. Together, these five complementary axes aim to create a tissue environment that is unfavorable for adenoma progression. While colonoscopic screening and removal of premalignant polyps remain the cornerstone of colorectal cancer prevention, a comprehensive systems-based approach that addresses metabolism, inflammation, mitochondrial biology, and host immunity may provide an important additional strategy for reducing colorectal cancer risk.

Medical Disclaimer: The discussion of repurposed medications and nutraceuticals in this article is intended to review the scientific literature and does not constitute a recommendation for self-treatment. Decisions regarding the use of off-label therapies should be made in consultation with a qualified healthcare professional familiar with the patient’s medical history and current treatment plan. Please see the full Medical Disclaimer on the introductory page to Marik’s Cancer & Metabolic Healing Playbook.
Thanks for your very kind comments. Greatly appreciated. Paul
My respect for your research is significant. I value it to the degree that in the end if not merely prolonging my life it may save it. I feel I have a broader understanding than I believe I could have ever had independently save my exposure to your articles.
That being said if I had to make a dietary choice and only one chance at it I would not pick the vegetarian diet but the carnivore diet, which I have done. I include broccoli, Brussels sprouts and other things for fiber but otherwise consume copious amount of red meat, chicken and other high protein meals. I won’t take the time now but I’m also taking an ICI (keytruda) even though my numbers decreased just on repurposed drugs. On this largely saturated fat and red meat my ctDNA numbers are “0” 3 tests in a row (over time) and the tumors are shrinking with no metastasis all on a carnivore diet. I’m gluten and lactose intolerant also making certain grains difficult. I lost a ton of weight but am gaining it back slowly with a lot of healthy fats (including saturated)