


Note: This guide outlines our complementary approach to the use of repurposed drugs and nutraceuticals in cancer treatment. It is not intended as a comprehensive reference. Furthermore, this guide does not constitute a recommendation for self-treatment. Decisions regarding the use of off-label therapies should be made in consultation with a qualified healthcare professional familiar with the patient’s medical history and current treatment plan.

Please read the post entitled “The Metabolic Trap-The Application of Multiple-Axis Metabolic Pressure in Cancer Therapy Using Repurposed Drugs and Nutraceuticals” which complements this post.

Introduction
Cancer treatment must always be individualized. Factors such as tumor type and stage, tumor biology, patient comorbidities, functional status, and personal preferences all play a role in determining the most appropriate plan of care. Repurposed drugs and metabolic therapy can be used in several ways: as adjuncts to conventional oncology treatments or, in select cases, as primary therapy.
There is no ideal regimen; however, this guide centers on the primary use of four agents with consistent evidence and broad activity: ivermectin, mebendazole, doxycycline, and curcumin. These form the foundation of treatment, with other drugs and nutraceuticals layered in as needed. Blocking multiple cancer stem cell (CSC) pathways is critical, as CSCs drive resistance, relapse, and disease progression. Limiting glucose intake and/or a ketogenic diet is a fundamental component of the metabolic approach to cancer care, i.e. starving cancer.
Patients may respond differently to therapy. For example, while many respond to standard ivermectin dosing, a subset requires higher doses to achieve clinical benefit. For this reason, treatment intensity must be adjusted on a case-by-case basis. In addition, some patients may show a dramatic response to a single agent but as a rule multiple agents are required for their synergistic anticancer effect.
Two broad therapeutic strategies can be considered, each with a spectrum of options in between:
Limited therapy. Start with a smaller number of core agents at lower doses. Escalate gradually in patients who fail to respond. This strategy is particularly suited to those with early-stage or less aggressive cancers, or those already receiving multiple conventional therapies (e.g., many breast cancer patients).
Aggressive therapy. Begin with higher doses and a wider combination of agents, scaling back as tolerated in patients who respond, or escalating further in those with inadequate response. This approach is preferred in patients with metastatic disease or highly aggressive tumors. This approach is preferred in patients receiving metronomic chemotherapy.
Regardless of approach, treatment should be supervised by a qualified integrative clinician. Self-treatment is strongly discouraged. The spectrum of agents used should be modified dynamically according to the response to treatment (see monitoring the progression to cancer).
Limited Therapy
Diet: Low-carbohydrate, low-glycemic diet. Intermittent fasting/OMAD (one-meal-a-day. Add matcha tea, brewed green tea and/or 4 cups coffee/day.
Ivermectin: 0.2–0.4 mg/kg/day (commonly 0.3 mg/kg/day)
Vitamin D + K2: Vitamin D 10,000 IU daily and vitamin K2 100 mcg, with monitoring of 25-OH vitamin D and parathyroid hormone (PTH) levels
Curcumin: 1000 - 2000 mg/day (500 -1000 mg twice daily). Use highly bioavailable preparation e.g. Phytosome Curcumin, nano-curcumin or CurcuWIN.
Melatonin: 20 mg at night, titrated upward from 5 mg
Propranolol: 10–40 mg twice daily as tolerated
Green tea extract (EGCG): Twice daily, less than 800 mg/day
Berberine 500 mg twice daily (hold during multi-day fast)
Resveratrol: 500 mg twice daily (high bioavailability)
Aggressive Therapy
Diet: Low-glycemic ketogenic diet, OMAD, periodic 48 and 72 hour fasting.
Ivermectin: 0.4–0.8 mg/kg/day (commonly 0.6 mg/kg/day), with titration up to 1 mg/kg/day if response is poor and drug is well tolerated. Take with food. Reduce dose if experience headaches, dizziness and other neurological signs.
Mebendazole: 200 mg daily(100mg twice daily)
Curcumin 1000 - 2000 mg/day (500 -1000 mg twice daily). Use highly bioavailable preparation e.g. Phytosome Curcumin, nano-curcumin or CurcuWIN
Vitamin D + K2: Vitamin D 10,000 IU daily and vitamin K2 100 mcg; with monitoring of 25-OH vitamin D, Calcium and PTH: titrate to achieve a low-normal PTH level (Coimbra protocol)
Green tea extract (EGCG): Twice daily, less than 800 mg/day
Berberine 500 mg twice daily (monitor glucose if taking metformin)
Resveratrol: 500 mg twice daily (high bioavailability)
Sulforaphane: Free stabilized sulforaphane from broccoli seed extract (dosage varies)
Metformin: 500–1,000 mg twice daily (hold during multi-day fast)
Propranolol: 10–40 mg twice daily as tolerated
Melatonin: 20 mg at night, titrated upward from 5 mg
Doxycycline 100 mg twice daily for 12 weeks or 100 mg daily alternate months (indefinitely)
Modified citrus pectin (PectaSol): 14.4 g daily; six capsules, three times a day
Luteolin 100-200 mg daily
Genistein 50-100 mg/day has broad anticancer effects by inhibiting androgen receptor, IGF-1, PI3K–AKT–mTOR, NF-κB, and STAT3 signaling
Aged garlic extract 1000 mg daily
Omega-3 fatty acids: 2–4 g daily
Statins: Atorvastatin 40–80 mg daily or simvastatin 40 mg daily; avoid long-term use or precipitous LDL reduction, which may increase dementia risk
Quercetin: 500–1,000 mg twice daily (stagger dose with Ivermectin)
Alpha lipoic acid 300-600 mg daily
Dandelion extract 250-1000 mg twice day
Artesunate 200 mg daily
Low dose naltrexone 2 -4.5 mg daily
Epigenin (apigenin) a plant derived flavonoid, 50–400 mg/day
Pomegranate extracts 250 mg daily
Monk fruit sweetener (as required)
Consider high dose IV vitamin C (75 -100 g 2-3 times weekly) together with standard chemotherapy in patients with cancers that express low levels of catalase activity (melanoma, breast, pancreatic, esophageal and lung cancer). Screen for G6PD deficiency and kidney insufficiency.
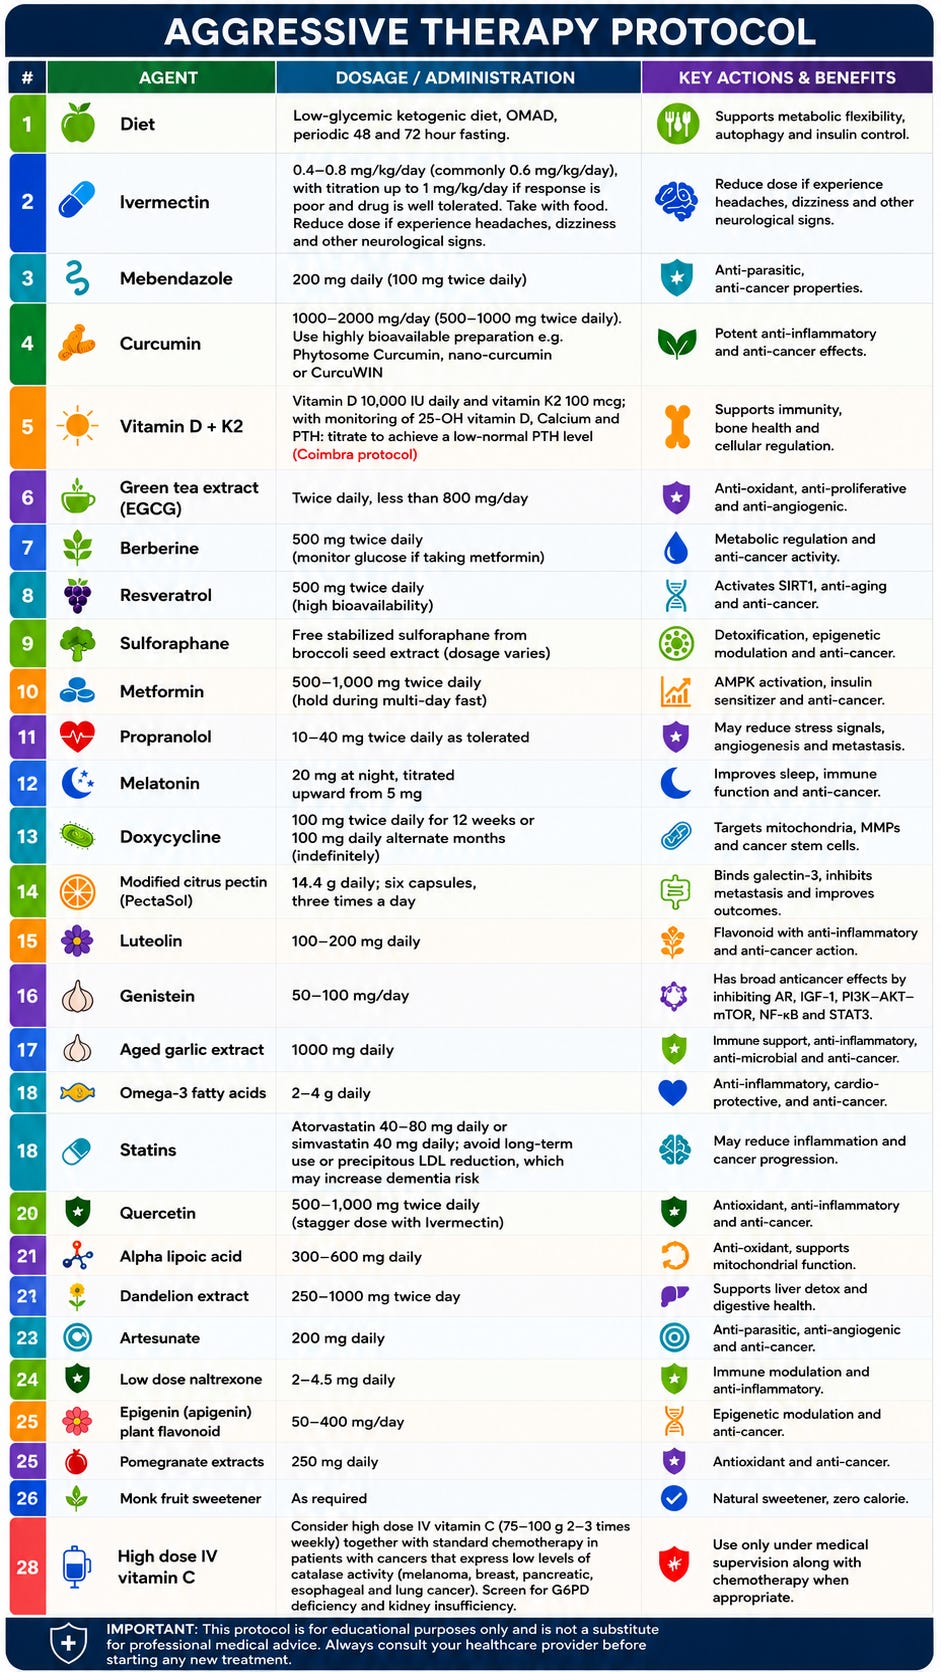
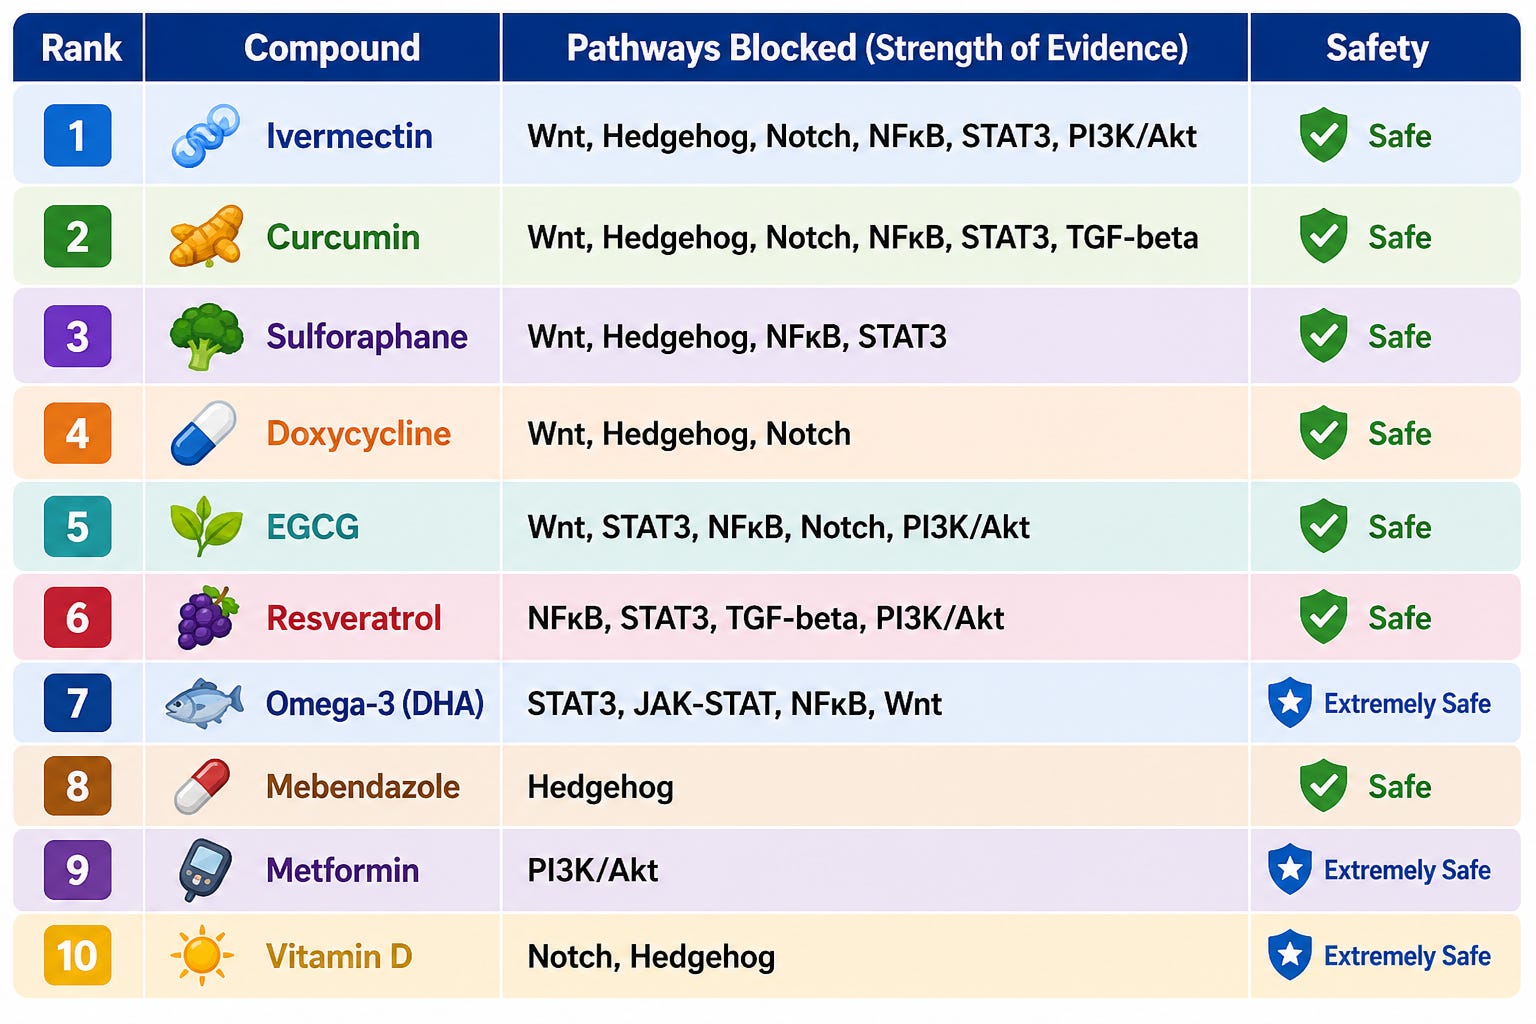
Tables 1 and 2 were generated using artificial intelligence (AI) engines and rank repurposed agents according to anti-cancer activity, cancer stem cell (CSC) pathways affected, and safety profile.
Table 1. Ranking of repurposed agents by anti-cancer activity, CSC pathway activity, and safety.
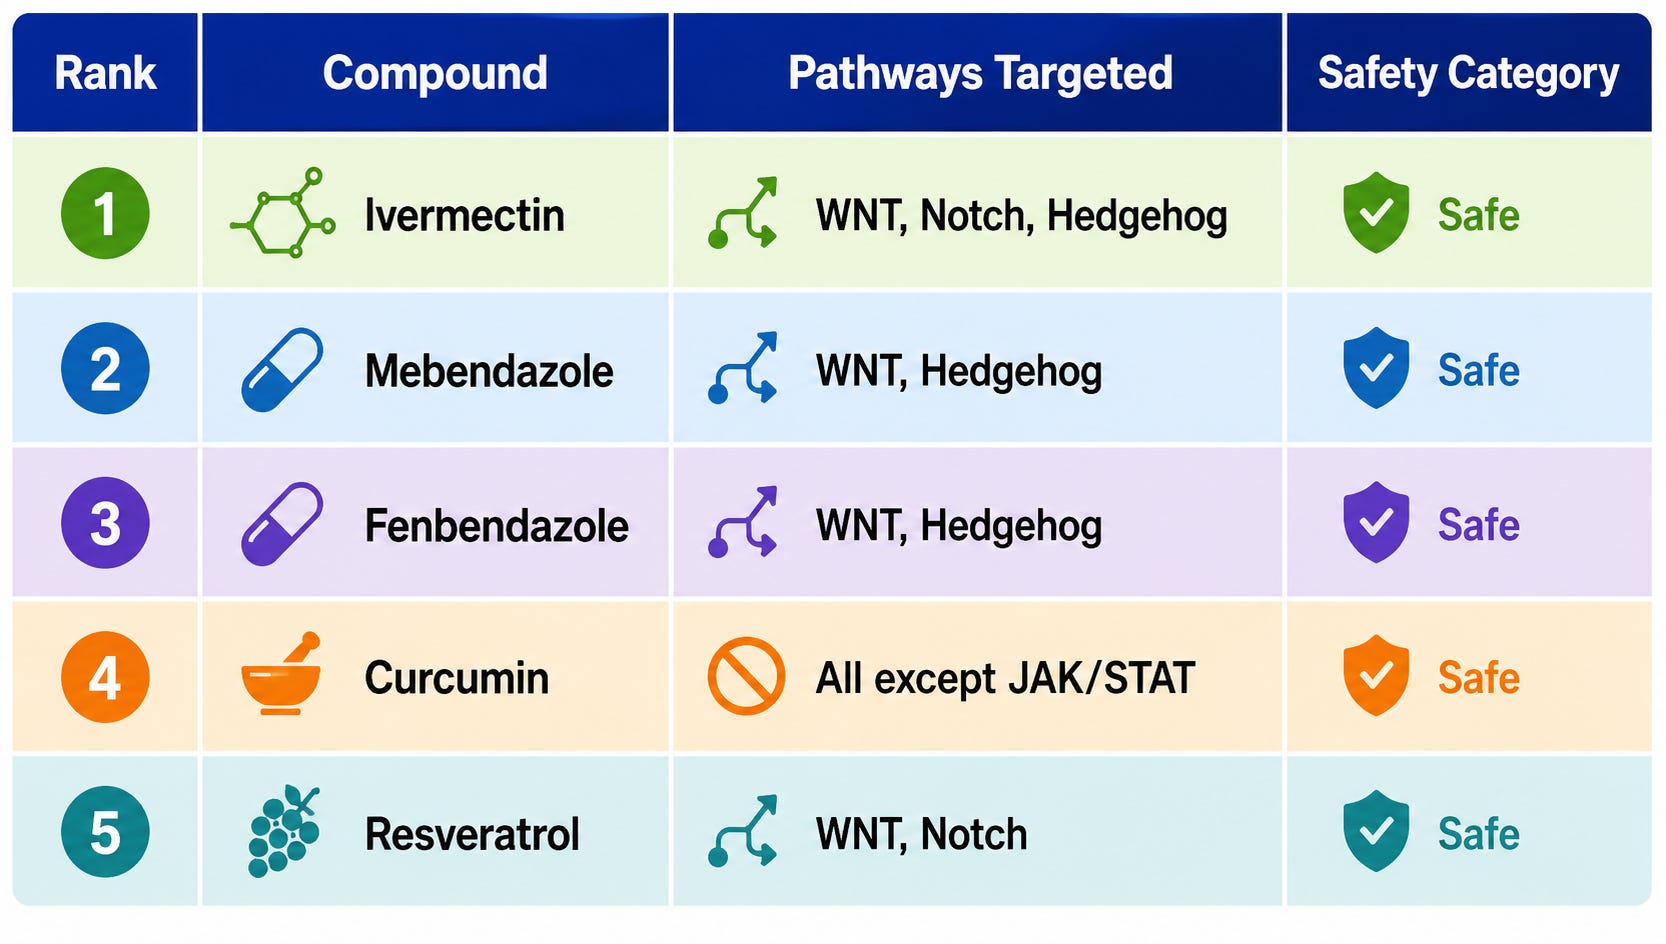
Table 2. Top 10 repurposed agents ranked by CSC pathway blockade, with pathway inhibition summarized and safety evaluated based on therapeutic index and commonly used doses.
The limited and aggressive therapeutic approaches described above apply broadly to patients with “generic cancers.” Based on limited clinical data and supported by AI, we outline below the agents we believe should be incorporated into treatment of the most common types of cancer in the “typical cancer” patient. These protocols are informed by exploratory AI analyses and limited data; head-to-head studies have not been performed, and the algorithms used by AI are not fully transparent. Accordingly, this information should be viewed as guidance in formulating patient-specific treatment. Furthermore, we believe that these repurposed agent combinations may help prevent stage 1 or stage 2 cancers from progressing to deadly stage 4 disease, with the goal of inducing remission.
Prostate Cancer
The Most Important Repurposed Drugs and Nutraceuticals for Prostate Cancer
I would rank them:
🥇 Tier 1
Metformin
Ivermectin
Berberine
Melatonin
EGCG
Sulforaphane
Curcumin
Vitamin D3
🥈 Tier 2
Mebendazole
Doxycycline
Omega-3 Fatty Acids
Propranolol
Luteolin
Quercetin
Resveratrol
🥉 Tier 3
Atorvastatin
Thymosin-α1
Mistletoe
Modified Citrus Pectin
Honokiol
Lycopene
Aged Garlic Extract
One notable change from lists I would have made a year ago is that luteolin has moved up substantially because of its impressive preclinical activity against androgen receptor signaling, PI3K-AKT-mTOR, STAT3, EMT, metastasis, and cancer stem cells—pathways that are central to prostate cancer progression.
Avoid Ashwagandha, Fenugreek and Galactomannan as they may increase free testosterone
Breast Cancer
The Most Important Repurposed Drugs and Nutraceuticals for Breast Cancer
🥇 Tier 1
Metformin
Melatonin
Ivermectin
Curcumin
Sulforaphane
EGCG
Vitamin D3
Berberine
🥈 Tier 2
Doxycycline
Mebendazole
Luteolin
Quercetin
Omega-3 Fatty Acids
Propranolol
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Mistletoe
Modified Citrus Pectin
Apigenin
Genistein
Boswellia
Aged Garlic Extract
Overall, I would place metformin, melatonin, ivermectin, curcumin, sulforaphane, and EGCG at the core of a metabolic strategy for breast cancer because together they target many of the key biological drivers across breast cancer subtypes, including insulin signaling, PI3K–AKT–mTOR, inflammation, EMT, cancer stem cells, and immune modulation.
Triple-Negative Breast Cancer (TNBC)
Because TNBC is highly enriched for CSCs and EMT, I would modify the ranking slightly.
Highest priorities
Metformin
Ivermectin
Sulforaphane
Doxycycline
Curcumin
Mebendazole
EGCG
Melatonin
Luteolin
Berberine
Hormone Receptor-Positive (ER+/HER2−) Breast Cancer
For hormone-sensitive disease, melatonin moves higher because of its anti-estrogen properties.
Highest priorities
Metformin
Melatonin
Curcumin
EGCG
Ivermectin
Sulforaphane
Vitamin D3
Berberine
Doxycycline
Luteolin
HER2-Positive Breast Cancer
Agents with the highest priorities
Metformin
EGCG
Curcumin
Melatonin
Sulforaphane
Ivermectin
Berberine
Doxycycline
Vitamin D3
Luteolin
Colorectal Cancer
For colorectal cancer the metabolic biology differs from both prostate and breast cancer. The dominant drivers include:
Wnt/β-catenin signaling (APC mutations in ~80%)
KRAS/MAPK signaling
PI3K–AKT–mTOR
Cancer stem cells (CSCs)
Inflammation (NF-κB, COX-2, IL-6/STAT3)
Warburg metabolism
Gut microbiome and tumor microenvironment
Accordingly, I would rank repurposed drugs and nutraceuticals as follows.
The Most Important Repurposed Drugs and Nutraceuticals for Colorectal Cancer
🥇 Tier 1
Metformin
Ivermectin
Berberine
Curcumin
Sulforaphane
EGCG
Vitamin D3
Melatonin
🥈 Tier 2
Mebendazole
Doxycycline
Omega-3 Fatty Acids
Propranolol
Luteolin
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin
Thymosin-α1
Modified Citrus Pectin
Honokiol
Mistletoe
Boswellia
Aged Garlic Extract
Apigenin
Genistein
KRAS-Mutant Colorectal Cancer
For tumors with KRAS mutations, I would modify the ranking because KRAS drives glycolysis, glutamine metabolism, and CSC biology.
Highest priorities
Metformin
Berberine
Ivermectin
Curcumin
Sulforaphane
EGCG
Mebendazole
Doxycycline
Melatonin
Vitamin D3
Metastatic Colorectal Cancer
For patients with metastatic disease, greater emphasis should be placed on CSCs and metastasis.
Highest priorities
Metformin
Ivermectin
Curcumin
Berberine
Sulforaphane
Mebendazole
Doxycycline
Omega-3 Fatty Acids
Propranolol
EGCG
Overall Perspective
Among all solid tumors, colorectal cancer has one of the strongest mechanistic rationales for a multi-target metabolic strategy because of its dependence on Wnt/β-catenin signaling, altered glucose metabolism, chronic inflammation, and cancer stem cells. A core combination of metformin, ivermectin, berberine, curcumin, sulforaphane, EGCG, vitamin D3, melatonin, mebendazole, and doxycycline provides broad coverage of these pathways. While many of these agents have extensive preclinical support and favorable safety profiles, high-quality clinical trials evaluating these combinations are still lacking, so this ranking should be viewed as a hypothesis-driven framework rather than an evidence-based treatment standard.
Lung Cancer
The Most Important Repurposed Drugs and Nutraceuticals for Lung Cancer
🥇 Tier 1
Metformin
Ivermectin
Melatonin
Curcumin
EGCG
Sulforaphane
Vitamin D3
Berberine
🥈 Tier 2
Doxycycline
Mebendazole
Propranolol
Omega-3 Fatty Acids
Luteolin
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Mistletoe
Boswellia
Modified Citrus Pectin
Apigenin
Genistein
Aged Garlic Extract
KRAS-Mutant NSCLC
KRAS-mutant tumors are particularly dependent on glycolysis, PI3K signaling, and metabolic plasticity.
Highest priorities
Metformin
Berberine
Ivermectin
Curcumin
Sulforaphane
EGCG
Doxycycline
Mebendazole
Melatonin
Vitamin D3
EGFR-Mutant NSCLC
For EGFR-driven tumors, agents that modulate EGFR signaling and potentially enhance sensitivity to EGFR inhibitors become especially attractive.
Highest priorities
Metformin
EGCG
Curcumin
Ivermectin
Melatonin
Sulforaphane
Berberine
Doxycycline
Vitamin D3
Luteolin
Small Cell Lung Cancer (SCLC)
Because SCLC is highly proliferative and rich in CSCs, greater emphasis should be placed on mitochondrial and CSC-targeting strategies.
Highest priorities
Metformin
Ivermectin
Doxycycline
Mebendazole
Curcumin
Melatonin
Sulforaphane
EGCG
Vitamin D3
Berberine
Overall Perspective
Among solid tumors, lung cancer—particularly NSCLC—has a strong mechanistic rationale for a multi-target metabolic strategy because of its reliance on EGFR/KRAS signaling, PI3K–AKT–mTOR, altered glucose metabolism, EMT, and cancer stem cells. A core combination of metformin, ivermectin, melatonin, curcumin, EGCG, sulforaphane, vitamin D3, berberine, doxycycline, and mebendazole provides broad coverage of these pathways. While there is encouraging preclinical evidence and some supportive clinical data for individual agents such as metformin and melatonin, well-designed clinical trials evaluating multi-agent metabolic regimens are still needed, so these rankings should be viewed as biologically informed
Melanoma
For melanoma, the biology differs substantially from epithelial cancers. The major drivers include:
MAPK signaling (BRAF/NRAS mutations)
PI3K–AKT–mTOR
YAP/TAZ signaling
Cancer stem cells (CSCs)
Immune evasion
Oxidative stress adaptation
Metabolic plasticity (glycolysis ↔ OXPHOS switching)
Mitochondrial metabolism, particularly in treatment-resistant disease
These rankings are based on mechanistic rationale, preclinical evidence, safety, and limited clinical data, and should be viewed as hypothesis-driven rather than evidence-based treatment recommendations.
The Most Important Repurposed Drugs and Nutraceuticals for Melanoma
🥇 Tier 1
Metformin
Ivermectin
Melatonin
Curcumin
Sulforaphane
Vitamin D3
EGCG
Berberine
🥈 Tier 2
Doxycycline
Mebendazole
Omega-3 Fatty Acids
Propranolol
Luteolin
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin
Thymosin-α1
Honokiol
Mistletoe
Boswellia
Modified Citrus Pectin
Apigenin
Genistein
Lycopene
Aged Garlic Extract
BRAF-Mutant Melanoma
Treatment resistance to BRAF inhibitors is often associated with a metabolic shift toward mitochondrial respiration and increased CSC activity.
Highest priorities
Metformin
Doxycycline
Ivermectin
Melatonin
Sulforaphane
Curcumin
EGCG
Berberine
Mebendazole
Vitamin D3
Immunotherapy-Treated Melanoma
For patients receiving immune checkpoint inhibitors, agents that support immune function while reducing chronic inflammation may be particularly attractive.
Highest priorities
Vitamin D3
Melatonin
Metformin
Ivermectin
Curcumin
Sulforaphane
EGCG
Omega-3 Fatty Acids
Berberine
Thymosin-α1
Overall Perspective
Melanoma is particularly well suited to a multi-target metabolic strategy because treatment resistance is often accompanied by metabolic plasticity, increased dependence on mitochondrial oxidative phosphorylation, and enrichment of cancer stem cell populations. A core regimen of metformin, ivermectin, melatonin, curcumin, sulforaphane, vitamin D3, EGCG, berberine, doxycycline, and mebendazole provides broad mechanistic coverage of these pathways. Although many of these agents have compelling preclinical evidence and favorable safety profiles, there is currently insufficient clinical evidence to conclude that these combinations improve melanoma-specific outcomes, so they should be considered investigational adjuncts rather than established therapies.
Ovarian Cancer
For ovarian cancer, particularly high-grade serous ovarian carcinoma (HGSOC), the biology differs from prostate, breast, and colorectal cancer. Key drivers include:
PI3K–AKT–mTOR
Homologous recombination deficiency (BRCA1/2)
Cancer stem cells (CSCs)
Epithelial–mesenchymal transition (EMT)
Angiogenesis (VEGF)
Inflammation (NF-κB, IL-6/STAT3)
Metabolic plasticity with increasing OXPHOS dependence
Peritoneal dissemination
Chemoresistance, often driven by CSCs and mitochondrial metabolism
Because recurrent ovarian cancer frequently develops OXPHOS dependence, I would rank mitochondrial-targeting agents slightly higher than for several other solid tumors.
As before, these rankings are hypothesis-driven, based largely on preclinical evidence and biological rationale rather than randomized clinical trials.
The Most Important Repurposed Drugs and Nutraceuticals for Ovarian Cancer
🥇 Tier 1
Metformin
Ivermectin
Doxycycline
Melatonin
Curcumin
Sulforaphane
EGCG
Vitamin D3
🥈 Tier 2
Berberine
Mebendazole
Luteolin
Propranolol
Omega-3 Fatty Acids
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin
Thymosin-α1
Honokiol
Mistletoe
Modified Citrus Pectin
Boswellia
Apigenin
Genistein
Aged Garlic Extract
BRCA-Mutated Ovarian Cancer
These tumors often respond well to PARP inhibitors initially, but resistant disease frequently becomes metabolically flexible.
Highest priorities
Metformin
Doxycycline
Ivermectin
Melatonin
Sulforaphane
Curcumin
EGCG
Berberine
Vitamin D3
Mebendazole
Platinum-Resistant Ovarian Cancer
This setting is characterized by CSC enrichment and increased mitochondrial metabolism.
Highest priorities
Doxycycline
Metformin
Ivermectin
Sulforaphane
Curcumin
Melatonin
Mebendazole
EGCG
Berberine
Propranolol
Overall Perspective
Among solid tumors, ovarian cancer has one of the strongest biological rationales for targeting mitochondrial metabolism and cancer stem cells, particularly in recurrent and platinum-resistant disease. A core combination of metformin, ivermectin, doxycycline, melatonin, curcumin, sulforaphane, EGCG, vitamin D3, berberine, and mebendazole provides broad mechanistic coverage of the pathways most closely associated with ovarian cancer progression and treatment resistance.
One notable difference from other tumor types is the higher ranking of doxycycline, reflecting increasing evidence that recurrent ovarian cancer becomes highly dependent on mitochondrial oxidative phosphorylation and that ovarian cancer stem cells rely heavily on mitochondrial function. While these mechanistic data are compelling, robust clinical trials evaluating these multi-agent metabolic combinations are still lacking, so this prioritization should be viewed as a biologically informed framework for future investigation rather than a clinically validated treatment algorithm.
Endometrial Cancer (Uterine Cancer)
For endometrial cancer, especially endometrioid uterine cancer, the dominant biology includes insulin resistance, obesity, estrogen signaling, PI3K–AKT–mTOR activation, inflammation, and cancer stem cells. Therefore, the ranking is slightly different from ovarian cancer.
The Most Important Repurposed Drugs and Nutraceuticals for Endometrial Cancer
🥇 Tier 1
Metformin
Berberine
Melatonin
Vitamin D3
Curcumin
Ivermectin
Sulforaphane
EGCG
🥈 Tier 2
Doxycycline
Mebendazole
Propranolol
Omega-3 fatty acids — anti-inflammatory, ferroptosis, metabolic support
Luteolin
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Mistletoe
Modified Citrus Pectin
Boswellia
Apigenin
Genistein
Aged Garlic Extract
Lycopene
Overall perspective: Endometrial cancer is one of the strongest candidates for a metabolic approach because many cases are linked to hyperinsulinemia, obesity, estrogen excess, and PI3K–AKT–mTOR activation. Metformin and berberine move to the top of the list because they target the metabolic terrain driving this disease.
Liver Cancer
For hepatocellular carcinoma (HCC), the biology is unique among solid tumors because it develops in a chronically inflamed, metabolically abnormal liver. The dominant drivers include:
PI3K–AKT–mTOR
Wnt/β-catenin (CTNNB1)
MYC activation
Chronic inflammation (IL-6, STAT3, NF-κB)
Oxidative stress
Angiogenesis (VEGF)
Cancer stem cells (EpCAM+, CD133+)
Warburg metabolism and glutamine dependence
Liver fibrosis and cirrhosis
Unlike many other cancers, metabolic syndrome, MASLD/NASH, obesity, insulin resistance, hepatitis B/C, and cirrhosis are major contributors to tumor development.
Accordingly, therapies that improve systemic metabolism, reduce hepatic inflammation, and suppress CSC biology move higher in priority.
The Most Important Repurposed Drugs and Nutraceuticals for Liver Cancer
🥇 Tier 1
Metformin
Berberine
Curcumin
Vitamin D3
Melatonin
Ivermectin
Sulforaphane
EGCG
🥈 Tier 2
Omega-3 Fatty Acids
Doxycycline
Mebendazole
Luteolin
Propranolol
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin
Thymosin-α1
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
Overall Perspective
Among solid tumors, hepatocellular carcinoma is perhaps the most metabolically driven, making it particularly well suited to a multi-target metabolic strategy. A core combination of metformin, berberine, curcumin, vitamin D3, melatonin, ivermectin, sulforaphane, EGCG, omega-3 fatty acids, and doxycycline provides broad mechanistic coverage of insulin signaling, PI3K–AKT–mTOR, Wnt/β-catenin, inflammation, fibrosis, angiogenesis, and cancer stem cell biology.
One notable difference from several other cancers is the higher ranking of berberine and omega-3 fatty acids, reflecting their favorable effects on metabolic dysfunction-associated steatotic liver disease (MASLD/NASH), insulin resistance, hepatic inflammation, and fibrosis, all of which contribute to liver carcinogenesis. As with the other rankings, these recommendations are hypothesis-driven and based largely on preclinical evidence, with limited clinical trial data evaluating multi-agent metabolic approaches in HCC.
Bladder Cancer
The treatment of bladder cancer depends on the histologic subtype, stage, and whether the disease is non-muscle-invasive (NMIBC) or muscle-invasive (MIBC). Approximately 90–95% of bladder cancers are urothelial (transitional cell) carcinomas.
Bladder cancer is particularly well suited to a metabolic approach because it exhibits many of the hallmark metabolic abnormalities targeted by the Metabolic Trap framework. Urothelial carcinomas commonly demonstrate increased glucose uptake, activation of the PI3K–AKT–mTOR pathway, enhanced glutamine metabolism, mitochondrial plasticity, angiogenesis, chronic inflammation, immune evasion, and a population of therapy-resistant cancer stem cells (CSCs). These biological characteristics suggest that applying simultaneous pressure across multiple metabolic and survival pathways may complement standard treatment and potentially reduce recurrence. However, it is important to emphasize that this strategy remains investigational and should be viewed as an adjunct to—not a replacement for—established therapies.
The Most Important Repurposed Drugs and Nutraceuticals for bladder cancer
🥇 Tier 1
Metformin
Ivermectin
Curcumin
Sulforaphane
Melatonin
Vitamin D3
EGCG
Berberine
🥈 Tier 2
Doxycycline
Mebendazole
Propranolol
Omega-3 fatty acids
Resveratrol/Pterostilbene
Genistein
Modified citrus pectin
🥉 Tier 3
PSK
Thymosin-α1
Honokiol
Mistletoe
Atorvastatin
Quercetin
Apigenin
Aged garlic extract
Integration with Standard Therapy
Non-muscle-invasive bladder cancer
Transurethral resection of bladder tumor (TURBT)
Intravesical Bacillus Calmette–Guérin (BCG) or intravesical chemotherapy
Muscle-invasive bladder cancer
Neoadjuvant cisplatin-based chemotherapy followed by radical cystectomy with pelvic lymph-node dissection.
Head and Neck Squamous Cancer
For head and neck squamous cell carcinoma (HNSCC), the dominant biology includes EGFR signaling, PI3K–AKT–mTOR, STAT3/NF-κB inflammation, EMT, angiogenesis, cancer stem cells, immune evasion, and mitochondrial plasticity. HPV-positive disease has distinct biology and generally a better prognosis, but many metabolic and CSC pathways overlap.
The Most Important Repurposed Drugs and Nutraceuticals for HNSCC
🥇 Tier 1
Metformin
Ivermectin
Curcumin
EGCG
Sulforaphane
Melatonin
Vitamin D3
Berberine
🥈 Tier 2
Doxycycline
Mebendazole
Propranolol
Luteolin
Omega-3 fatty acids
Quercetin —
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Mistletoe
Modified Citrus Pectin
Boswellia
Apigenin
Genistein
Aged Garlic Extract
Lycopene
Esophageal Squamous Cell Carcinoma
For esophageal squamous cell carcinoma (ESCC), the dominant biology includes EGFR signaling, PI3K–AKT–mTOR, STAT3/NF-κB inflammation, EMT, angiogenesis, cancer stem cells, mitochondrial plasticity, and field cancerization from chronic epithelial injury.
The Most Important Repurposed Drugs and Nutraceuticals for ESCC
🥇 Tier 1
Metformin
Curcumin
Ivermectin
EGCG
Sulforaphane
Berberine
Melatonin
Vitamin D3
🥈 Tier 2
Doxycycline
Mebendazole
Luteolin
Propranolol
Omega-3 fatty acids
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Mistletoe
Modified Citrus Pectin
Boswellia
Apigenin
Genistein
Aged Garlic Extract
Lycopene
Pancreatic Cancer
For pancreatic ductal adenocarcinoma (PDAC), the biological rationale for a metabolic approach is arguably stronger than for any other solid tumor. PDAC is characterized by:
KRAS mutations (~90–95%)
Extreme Warburg metabolism
Glutamine dependence
Cancer stem cells (CSCs)
Marked mitochondrial plasticity
Autophagy and macropinocytosis
Dense desmoplastic stroma
Profound immune suppression
Hypoxia and angiogenic signaling
Consequently, I would place greater emphasis on agents targeting mitochondrial metabolism, CSCs, KRAS-associated pathways, inflammation, and the tumor microenvironment.
These rankings are hypothesis-driven, based on mechanistic rationale, preclinical evidence, safety, and limited clinical data rather than randomized clinical trials.
The Most Important Repurposed Drugs and Nutraceuticals for Pancreatic Cancer
🥇 Tier 1
Metformin
Ivermectin
Doxycycline
Berberine
Curcumin
Sulforaphane
Melatonin
Vitamin D3
🥈 Tier 2
Mebendazole
EGCG
Propranolol
Omega-3 Fatty Acids
Luteolin
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin
Thymosin-α1
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
KRAS-Mutant Pancreatic Cancer
Since nearly all PDACs harbor KRAS mutations, therapies targeting metabolic consequences of KRAS become particularly attractive.
Highest priorities
Metformin
Berberine
Ivermectin
Doxycycline
Curcumin
Sulforaphane
EGCG
Melatonin
Mebendazole
Vitamin D3
Metastatic or Chemotherapy-Resistant PDAC
Treatment-resistant disease becomes increasingly dependent on mitochondrial metabolism and CSCs.
Highest priorities
Doxycycline
Metformin
Ivermectin
Sulforaphane
Curcumin
Berberine
Melatonin
Mebendazole
EGCG
Propranolol
Overall Perspective
Among all common solid tumors, pancreatic ductal adenocarcinoma may have the strongest biological rationale for a comprehensive metabolic strategy because it is driven by KRAS-mediated metabolic reprogramming, profound dependence on glycolysis and glutamine metabolism, dense stromal remodeling, and marked enrichment of cancer stem cells. A core regimen of metformin, ivermectin, doxycycline, berberine, curcumin, sulforaphane, melatonin, vitamin D3, mebendazole, and EGCG provides broad mechanistic coverage of these vulnerabilities.
One notable distinction from most other cancers is the higher priority assigned to doxycycline, reflecting substantial preclinical evidence that treatment-resistant pancreatic cancer relies heavily on mitochondrial oxidative phosphorylation and CSC biology. Likewise, berberine is ranked highly because of its effects on AMPK activation, glucose metabolism, and metabolic signaling, which align closely with the metabolic phenotype of PDAC. Although these mechanistic data are compelling, prospective clinical trials evaluating multi-agent metabolic protocols in pancreatic cancer are still lacking, so these rankings should be viewed as a biologically informed framework for future investigation rather than a clinically validated treatment algorithm.
Gastric Cancer
For gastric adenocarcinoma, the biological rationale for a metabolic approach is strong because tumor progression is driven by:
Chronic inflammation (particularly Helicobacter pylori)
PI3K–AKT–mTOR activation
Wnt/β-catenin signaling
STAT3 and NF-κB
HER2 signaling (in a subset of tumors)
Cancer stem cells (CSCs)
Epithelial–mesenchymal transition (EMT)
Angiogenesis
Metabolic reprogramming (Warburg effect and OXPHOS plasticity)
The ranking below is based on mechanistic rationale, preclinical evidence, safety, and the limited available clinical data. It should be viewed as hypothesis-generating, not as a validated treatment protocol.
The Most Important Repurposed Drugs and Nutraceuticals for Gastric Cancer
🥇 Tier 1
Metformin
Curcumin
Berberine
Ivermectin
Sulforaphane
EGCG
Melatonin
Vitamin D3
🥈 Tier 2
Doxycycline
Mebendazole
Luteolin
Omega-3 Fatty Acids
Propranolol
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin
Thymosin-α1
Honokiol
Mistletoe
Modified Citrus Pectin
Boswellia
Apigenin
Genistein
Aged Garlic Extract
Lycopene
HER2-Positive Gastric Cancer
For HER2-positive disease, agents that suppress HER2 and PI3K signaling become more attractive.
Highest priorities
Metformin
EGCG
Curcumin
Berberine
Ivermectin
Sulforaphane
Melatonin
Vitamin D3
Doxycycline
Luteolin
Diffuse-Type Gastric Cancer
Diffuse gastric cancers often show greater EMT, invasion, and CSC activity.
Highest priorities
Metformin
Ivermectin
Curcumin
Sulforaphane
Doxycycline
Berberine
Melatonin
Mebendazole
EGCG
Vitamin D3
Overall Perspective
Among gastrointestinal malignancies, gastric cancer has a strong biological rationale for a multi-target metabolic strategy because of its dependence on chronic inflammation, PI3K–AKT–mTOR signaling, Wnt/β-catenin activation, EMT, angiogenesis, and cancer stem cells. A core combination of metformin, curcumin, berberine, ivermectin, sulforaphane, EGCG, melatonin, vitamin D3, doxycycline, and mebendazole provides broad mechanistic coverage of these pathways.
A distinguishing feature of gastric cancer is the prominent role of chronic inflammation and, in many patients, antecedent Helicobacter pylori infection, making curcumin and berberine particularly attractive because of their combined anti-inflammatory, metabolic, and Wnt-modulating effects. In HER2-positive gastric cancer, EGCG and luteolin may have additional mechanistic relevance because of their preclinical effects on HER-family signaling. As with the other cancer-specific rankings, this prioritization is based primarily on mechanistic and preclinical evidence, and prospective clinical trials are needed to determine whether multi-agent metabolic strategies improve patient outcomes.
Glioblastoma
For glioblastoma, the dominant biology includes extreme metabolic plasticity, mitochondrial dependence in therapy-resistant cells, cancer stem cells, hypoxia, angiogenesis, invasion, PI3K–AKT–mTOR activation, STAT3/NF-κB inflammation, and blood–brain barrier penetration.
The Most Important Repurposed Drugs and Nutraceuticals for Glioblastoma
🥇 Tier 1
Metformin
Doxycycline
Melatonin
Ivermectin *
Curcumin
Sulforaphane
Berberine
Vitamin D3
🥈 Tier 2
Mebendazole
EGCG
Propranolol
Luteolin
Quercetin
Omega-3 fatty acids
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Boswellia
Mistletoe
Modified Citrus Pectin
Apigenin
Aged Garlic Extract
Lycopene
* Despite its limited penetration of the blood-brain barrier (BBB), several factors suggest ivermectin may still exert immune activity against GBM. These include the inherent disruption of the BBB in GBM tumors, ivermectin’s systemic immunomodulatory effects, and its potential for enhanced delivery through combination approaches. Most importantly, ivermectin has demonstrated the ability to transform “cold” tumors (with little immune infiltration) into “hot” tumors (with significant immune infiltration). This ability is particularly relevant because GBM is profoundly immunosuppressive and is often considered a “cold” tumor resistant to immunotherapy.
Triple Combination Synergy Assessment
In vitro evidence indicates that the triple combination of modified citrus pectin, PD-1 inhibitors, and ivermectin may provide substantial synergistic anti-cancer activity in GBM. While each agent has shown individual activity or paired synergy, the combined approach targets multiple complementary pathways that could help overcome the complex immunosuppressive mechanisms in GBM. It should be noted, however, that no clinical data currently support this combination.
Bottom line: Glioblastoma has a strong rationale for mitochondrial and CSC targeting. Doxycycline and mebendazole move higher because therapy-resistant glioma stem cells often rely on mitochondrial metabolism and cytoskeletal/invasive programs.
Kidney Cancer – Renal Cell Carcinoma
For most adults with kidney cancer (usually renal cell carcinoma), surgery to remove part of the kidney (partial nephrectomy) or the whole kidney (radical nephrectomy) is the standard treatment when the tumor is limited to the kidney. Sometimes active surveillance (close monitoring without immediate treatment) is used for very small tumors in older or frail patients. In patients with stage 4 disease (metastatic disease) targeted therapies (such as VEGF or mTOR inhibitors) and immunotherapies (such as PD‑1/PD‑L1 or CTLA‑4 inhibitors) can be given before or after surgery.
For renal cell carcinoma (RCC), especially clear-cell RCC, the dominant biology includes VHL loss, HIF-1α/HIF-2α activation, VEGF-driven angiogenesis, PI3K–AKT–mTOR, immune evasion, metabolic reprogramming, mitochondrial dysfunction, lipid accumulation, and hypoxia adaptation.
The Most Important Repurposed Drugs and Nutraceuticals for Kidney Cancer / RCC
🥇 Tier 1
Metformin
Ivermectin
Berberine
Curcumin
Sulforaphane
Melatonin
EGCG
Vitamin D3
🥈 Tier 2
Doxycycline
Mebendazole
Propranolol s
Omega-3 fatty acids
Luteolin
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Mistletoe
Modified Citrus Pectin
Boswellia
Apigenin
Genistein
Aged Garlic Extract
Lycopene
Basal Cell Carcinoma
For basal cell carcinoma (BCC), the biology differs somewhat from squamous cell carcinoma. BCC is characterized by a near-universal dependence on aberrant Hedgehog signaling (most commonly through mutations in PTCH1 or SMO), with additional contributions from PI3K–AKT–mTOR, Wnt/β-catenin, EGFR, inflammation, and metabolic reprogramming. Compared with SCC, BCC is generally less glycolytic, grows more slowly, and rarely metastasizes, but it remains metabolically adaptable.
Because most BCCs are cured with surgery or local therapies, the following tiered approach should be viewed as a hypothesis-driven adjunctive strategy based primarily on mechanistic rationale and preclinical evidence. It is not a substitute for guideline-based management.
Standard surgical excision with appropriate margins is the mainstay of treatment and offers high cure rates for most primary basal cell carcinoma (BCC). External beam can be definitive treatment for BCC when surgery is not possible or would be disfiguring. Repurposed drugs and nutraceutical play a secondary role particularly for prevention. It should be noted that the evidence supporting these second line therapies for primary treatment is weak.
Practical Multi-Axis Strategy for BCC
🥇 Tier 1 (foundation)
Metformin
Ivermectin
Curcumin
EGCG
Sulforaphane
Melatonin
Vitamin D3
🥈 Tier 2 (Add if appropriate)
Berberine
Doxycycline
Mebendazole
Genistein
Omega-3 fatty acids
Propranolol
Resveratrol / Pterostilbene
🥉 Tier 3 (Selected patients)
Atorvastatin
Honokiol
Apigenin
Quercetin
Modified Citrus Pectin
Thymosin-α1
High-dose IV Vitamin C
Mistletoe
Important clinical note
For localized basal cell carcinoma, standard treatments—including surgical excision, Mohs micrographic surgery, curettage and electrodesiccation, cryotherapy, topical therapies for selected superficial lesions, and radiotherapy when appropriate—provide excellent cure rates. The tiered metabolic approach outlined above is best considered an investigational adjunct supported primarily by laboratory and mechanistic evidence rather than randomized clinical trials in BCC. It should complement, not replace, established evidence-based treatment.
Topical Ivermectin
The rationale for topical ivermectin is somewhat stronger for basal cell carcinoma (BCC) than for squamous cell carcinoma because BCC is typically slow growing, locally invasive, and often confined to the epidermis and superficial dermis, making it more amenable to topical drug delivery. Nevertheless, there are currently no clinical trials demonstrating efficacy of topical ivermectin, with or without DMSO, for BCC, and its use remains investigational.
Squamous Cell Carcinoma of the Skin
Cutaneous squamous cell carcinoma (cSCC) is the second most common skin cancer, accounting for approximately 20% of non-melanoma skin cancers. Most tumors are cured with surgery, but a small proportion become locally advanced or metastatic, where prognosis is substantially worse. Standard treatment remains surgical excision (including Mohs micrographic surgery in appropriate cases), with radiotherapy and systemic therapies reserved for selected high-risk or advanced disease.
From the perspective of the Metabolic Trap, cSCC is an attractive candidate for metabolic intervention because it demonstrates activation of many of the same interconnected signaling pathways targeted by the multi-axis approach, including glycolysis, mitochondrial plasticity, cancer stem cell (CSC) biology, inflammatory signaling, angiogenesis, and immune evasion. However, it is important to note that the metabolic approach remains investigational and should be viewed as a complementary strategy rather than a replacement for standard treatment. Most evidence indicates that cSCC exhibits a moderate to strong Warburg phenotype.
Practical Multi-Axis Strategy for cSCC
🥇 Tier 1 (foundation)
· Metformin
Ivermectin
Curcumin
EGCG
Sulforaphane
Melatonin
Vitamin D3
🥈 Tier 2 (Add if appropriate)
Berberine
Doxycycline
Mebendazole
Genistein
Omega-3 fatty acids
Propranolol
Resveratrol / Pterostilbene
🥉 Tier 3 (Selected patients)
Atorvastatin
Honokiol
Apigenin
Quercetin
Modified Citrus Pectin
Thymosin-α1
High-dose IV Vitamin C
Mistletoe
Important clinical note
For localized cutaneous SCC, complete surgical excision (often with Mohs micrographic surgery for appropriate lesions) remains the standard treatment with the highest cure rates. The tiered approach above should be viewed as a research-based adjunctive framework intended to complement, not replace, evidence-based surgical and oncologic management. For advanced or metastatic cSCC, systemic therapies such as PD-1 inhibitors remain the standard of care, and the role of these repurposed drugs and nutraceuticals has not been established in clinical trials.
Topical Ivermectin
At present, there is no clinical evidence supporting the use of topical ivermectin as a treatment for cutaneous squamous cell carcinoma (cSCC), and there is no published evidence that mixing ivermectin with DMSO improves response. Most of the available data on ivermectin in cancer come from cell culture and animal studies using systemic exposure, not topical application.
Bottom line
Topical ivermectin is not an established treatment for cutaneous squamous cell carcinoma.
There is strong laboratory rationale but no clinical evidence demonstrating efficacy.
DMSO would likely increase skin penetration, but there are no published studies showing that ivermectin–DMSO combinations improve outcomes in cSCC.
For superficial premalignant lesions or carcinoma in situ, topical metabolic therapies are an interesting research direction, but for invasive cSCC, surgery remains the standard of care, with metabolic approaches considered investigational adjuncts rather than replacements.
Stage 4 Metastatic Disease
For Stage IV metastatic cancer, regardless of the primary tumor, the biology becomes increasingly convergent. Metastatic cancers typically acquire common hallmarks that include:
Cancer stem cell (CSC) enrichment
Metabolic plasticity (glycolysis ↔ OXPHOS switching)
Mitochondrial oxidative phosphorylation (especially in therapy-resistant disease)
EMT and invasion
Immune suppression
Angiogenesis
PI3K–AKT–mTOR activation
NF-κB and STAT3 activation
Systemic inflammation
Therapeutic resistance
Consequently, a broad multi-target metabolic strategy becomes biologically more attractive than focusing on a single pathway.
The ranking below is hypothesis-driven, based on mechanistic rationale, preclinical evidence, safety, and limited clinical data. It is not a substitute for established systemic therapies such as chemotherapy, immunotherapy, targeted therapy, endocrine therapy, or radiotherapy when these are indicated.
The Most Important Repurposed Drugs and Nutraceuticals for Stage IV Metastatic Cancer
🥇 Tier 1
Metformin
Ivermectin
Doxycycline
Curcumin
Melatonin
Sulforaphane
Berberine
Vitamin D3
🥈 Tier 2
Mebendazole
EGCG
Propranolol
Omega-3 Fatty Acids
Luteolin
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Modified Citrus Pectin
Boswellia
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
Pomegranate Extract
Patients Receiving Immunotherapy
For patients receiving immune checkpoint inhibitors, greater emphasis should be placed on agents that support antitumor immunity.
Highest priorities
Vitamin D3
Melatonin
Metformin
Ivermectin
Curcumin
Sulforaphane
EGCG
Omega-3 Fatty Acids
Berberine
Thymosin-α1
OXPHOS-Dependent Metastatic Disease
Examples include pancreatic cancer, recurrent ovarian cancer, glioblastoma, CLL, AML, melanoma, and some sarcomas.
Highest priorities
Doxycycline
Metformin
Berberine
Ivermectin
Melatonin
Sulforaphane
Curcumin
Mebendazole
EGCG
Vitamin D3
Overall Perspective
From a biological perspective, Stage IV metastatic disease is where the rationale for a multi-axis metabolic strategy is strongest, because metastatic tumors frequently converge on a common set of vulnerabilities, including cancer stem cells, mitochondrial oxidative phosphorylation, metabolic plasticity, immune evasion, angiogenesis, and chronic inflammation. Rather than targeting a single mutation, a rational strategy aims to apply simultaneous pressure to multiple pathways that support metastatic survival and therapeutic resistance.
Among the repurposed agents, metformin, ivermectin, doxycycline, curcumin, melatonin, sulforaphane, berberine, vitamin D3, mebendazole, and EGCG provide the broadest mechanistic coverage across these shared vulnerabilities. Nevertheless, there is currently no high-quality clinical evidence demonstrating that this combination improves survival in Stage IV cancer, and it should therefore be regarded as an investigational adjunct to, rather than a replacement for, evidence-based oncologic therapy. Prospective clinical trials are needed to determine the safety, optimal dosing, and clinical efficacy of such multi-agent metabolic strategies.
Stage 0: Carcinoma in Situ
For Stage 0 cancer (Carcinoma in Situ, CIS), the biological goals are fundamentally different from those in invasive cancer. There is no invasion, metastasis, or established cancer stem cell niche. The emphasis is on:
Preventing progression to invasive cancer
Reversing metabolic dysfunction
Reducing chronic inflammation
Restoring immune surveillance
Suppressing early clonal expansion
Maintaining epithelial differentiation
Preventing angiogenic switching
Targeting early cancer stem-like cells (where present)
Because of these goals, the emphasis shifts toward metabolic optimization and chemoprevention, rather than aggressive mitochondrial inhibition.
The ranking below is hypothesis-driven and reflects mechanistic rationale, safety, and available observational or preclinical evidence. It should not replace definitive local therapy (e.g., surgery or ablation), which remains the standard of care for most carcinomas in situ.
The Most Important Repurposed Drugs and Nutraceuticals for Stage 0 Carcinoma in Situ
🥇 Tier 1
Vitamin D3
Metformin
Curcumin
Sulforaphane
Melatonin
Berberine
EGCG
Omega-3 Fatty Acids
🥈 Tier 2
Luteolin
Quercetin
Resveratrol/Pterostilbene
Apigenin
Aged Garlic Extract
Modified Citrus Pectin
Propranolol (selected patients)
🥉 Tier 3
Doxycycline
Mebendazole
Ivermectin
Atorvastatin (when otherwise indicated)
Thymosin-α1
Honokiol
Boswellia
Mistletoe
Low-Risk Carcinoma in Situ
Examples include:
Low-grade ductal carcinoma in situ (DCIS)
Low-grade cervical intraepithelial neoplasia after treatment
Successfully treated carcinoma in situ with no residual disease
Highest priorities
Vitamin D3
Metformin (particularly in insulin resistance or diabetes)
Curcumin
Sulforaphane
Melatonin
Berberine
Omega-3 Fatty Acids
EGCG
Luteolin
Quercetin
High-Risk Carcinoma in Situ
Examples include:
Extensive high-grade DCIS
Multifocal CIS
Positive margins awaiting definitive treatment
Patients with strong inherited cancer predisposition (e.g., BRCA mutation)
Highest priorities
Metformin
Vitamin D3
Curcumin
Sulforaphane
Melatonin
Berberine
EGCG
Luteolin
Quercetin
Ivermectin (investigational, if used at all)
Overall Perspective
For Stage 0 disease, the therapeutic objective is prevention of progression, not treatment of established invasive cancer. Consequently, agents that improve metabolic health, reduce chronic inflammation, support immune surveillance, and favor normal cellular differentiation deserve the highest priority. In contrast, drugs primarily aimed at disrupting mitochondrial metabolism or rapidly proliferating cancer stem cells (such as doxycycline or mebendazole) have a weaker biological rationale in this setting.
The strongest evidence supporting prevention of progression still lies with definitive local treatment and appropriate surveillance. Repurposed drugs and nutraceuticals should therefore be viewed as investigational adjuncts to optimize the metabolic and inflammatory environment, rather than as substitutes for established management of carcinoma in situ.
Non-Hodgin Lymphoma (Adjunctive Treatment)
For non-Hodgkin lymphoma (NHL), the biology varies considerably by subtype (e.g., diffuse large B-cell lymphoma [DLBCL], follicular lymphoma, mantle cell lymphoma, marginal zone lymphoma, and T-cell lymphomas). Nevertheless, most B-cell NHLs share several important biological features:
B-cell receptor (BCR) signaling
PI3K–AKT–mTOR
NF-κB activation
JAK/STAT signaling
BCL-2-mediated apoptosis resistance
Cancer stem-like populations (particularly in aggressive and relapsed disease)
Mitochondrial oxidative phosphorylation (OXPHOS), especially in subsets of DLBCL and indolent lymphomas
Immune dysregulation
Tumor microenvironment dependence
Unlike many solid tumors, many lymphomas—particularly indolent NHLs—are more OXPHOS-dependent than glycolytic, making mitochondrial-targeting agents somewhat more attractive.
The ranking below is hypothesis-driven, based on mechanistic rationale, preclinical evidence, safety, and limited clinical data. It is not a validated treatment protocol.
The Most Important Repurposed Drugs and Nutraceuticals for Non-Hodgkin Lymphoma
🥇 Tier 1
Metformin
Curcumin
Doxycycline
Melatonin
Vitamin D3
Ivermectin
Berberine
EGCG
🥈 Tier 2
Sulforaphane
Thymosin-α1
Omega-3 Fatty Acids
Luteolin
Quercetin
Resveratrol/Pterostilbene
Propranolol
🥉 Tier 3
Mebendazole
Atorvastatin/Simvastatin
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
Lycopene
Indolent NHL (Follicular, Marginal Zone)
Because these lymphomas tend to rely more on mitochondrial metabolism and immune interactions, I would prioritize:
Metformin
Doxycycline
Melatonin
Curcumin
Vitamin D3
Ivermectin
Berberine
Thymosin-α1
EGCG
Sulforaphane
Aggressive NHL (DLBCL)
For aggressive disease, stronger emphasis is placed on apoptosis, PI3K signaling, and CSC-like populations.
Highest priorities
Metformin
Curcumin
Doxycycline
Ivermectin
Melatonin
EGCG
Berberine
Sulforaphane
Vitamin D3
Mebendazole
Overall Perspective
Many B-cell non-Hodgkin lymphomas exhibit a greater dependence on mitochondrial oxidative phosphorylation, B-cell receptor signaling, PI3K–AKT–mTOR activation, and NF-κB than do many solid tumors. Consequently, mitochondrial-targeting agents (such as doxycycline), AMPK activators (metformin and berberine), and immune-modulating compounds (melatonin, vitamin D3, and thymosin-α1) are ranked relatively highly. Curcumin also stands out because of its broad effects on NF-κB, STAT3, and BCL-2-mediated survival pathways. Although these mechanistic considerations provide a strong rationale for further study, clinical evidence supporting multi-agent metabolic protocols in NHL remains limited, and these rankings should be viewed as a biologically informed framework for future investigation rather than an established standard of care.
Hodgkins Lyphoma (Adjunctive treatment)
For classical Hodgkin lymphoma (cHL), the biology differs substantially from most solid tumors. The malignant Reed–Sternberg cells comprise only a small fraction of the tumor mass, with the remainder consisting of an immunologically active tumor microenvironment. Major biological drivers include:
NF-κB activation (nearly universal)
JAK/STAT signaling (especially STAT3 and STAT6)
PD-1/PD-L1 immune evasion
PI3K–AKT–mTOR
CD30 signaling
Cancer stem-like populations (less prominent than in epithelial cancers)
Inflammatory cytokines (IL-6, IL-13, TNF-α)
EBV-associated pathways (in a subset of patients)
Metabolic reprogramming and mitochondrial adaptation
Because immune dysregulation is central to Hodgkin lymphoma, agents with immune-modulating and anti-inflammatory properties rank somewhat higher than in many solid tumors.
The ranking below is hypothesis-driven, based primarily on mechanistic rationale, preclinical evidence, safety, and limited clinical data. It should not be interpreted as a validated treatment protocol.
The Most Important Repurposed Drugs and Nutraceuticals for Hodgkin Lymphoma
🥇 Tier 1
Metformin
Curcumin
Melatonin
Vitamin D3
Ivermectin
EGCG
Berberine
Sulforaphane
🥈 Tier 2
Thymosin-α1
Doxycycline
Omega-3 Fatty Acids
Luteolin
Quercetin
Resveratrol/Pterostilbene
Propranolol
🥉 Tier 3
Mebendazole
Atorvastatin/Simvastatin
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
Lycopene
EBV-Positive Hodgkin Lymphoma
In EBV-associated disease, immune modulation becomes even more important.
Highest priorities
Metformin
Melatonin
Vitamin D3
Curcumin
Thymosin-α1
Ivermectin
EGCG
Sulforaphane
Berberine
Doxycycline
Relapsed or Refractory Hodgkin Lymphoma
Following relapse, metabolic adaptation and immune escape become increasingly important.
Highest priorities
Metformin
Curcumin
Thymosin-α1
Melatonin
Ivermectin
Vitamin D3
Doxycycline
Berberine
EGCG
Sulforaphane
Overall Perspective
Unlike most solid tumors, Hodgkin lymphoma is characterized by profound immune dysregulation, with relatively few malignant cells embedded in a highly inflammatory tumor microenvironment. Consequently, the highest-priority adjunctive agents are those that combine immune modulation, inhibition of NF-κB and JAK/STAT signaling, metabolic reprogramming, and mitochondrial support. A core combination of metformin, curcumin, melatonin, vitamin D3, ivermectin, EGCG, berberine, sulforaphane, thymosin-α1, and doxycycline provides broad mechanistic coverage of these pathways. While the biological rationale is compelling, there is very limited clinical evidence supporting multi-agent metabolic protocols in Hodgkin lymphoma, and these rankings should be regarded as a framework for future investigation rather than established clinical recommendations.
Multiple Myeloma (Adjunctive Treatment)
For multiple myeloma, the dominant biology includes plasma-cell survival signaling, NF-κB activation, IL-6/JAK/STAT3, PI3K–AKT–mTOR, proteasome stress, mitochondrial metabolism, bone marrow microenvironment dependence, osteoclast activation, angiogenesis, and immune dysfunction.
The Most Important Repurposed Drugs and Nutraceuticals for Multiple Myeloma
🥇 Tier 1
Curcumin
Metformin
Melatonin
Vitamin D3
Berberine
Ivermectin
EGCG
Sulforaphane
🥈 Tier 2
Doxycycline
Omega-3 fatty acids
Thymosin-α1
Luteolin
Quercetin
Resveratrol/Pterostilbene
Propranolol
🥉 Tier 3
Mebendazole
Atorvastatin/Simvastatin
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
Lycopene
Bottom line: Multiple myeloma is especially driven by NF-κB, IL-6/STAT3, PI3K/mTOR, immune dysfunction, bone marrow stromal support, and mitochondrial adaptation. Curcumin ranks unusually high because of its strong overlap with NF-κB/STAT3/IL-6 signaling central to myeloma biology.
Myelodysplastic Syndrome
MDS is a complex and heterogeneous disease varying from a slow progressive disease to a highly aggressive form that transitions into acute myeloid leukemia. MDS is best followed by an oncologist with expertise in this area; repurposed drugs however have an important adjunctive role. The primary treatments for MDS are tailored to disease risk, patient age, and overall health. The only curative therapy is stem cell (bone marrow) transplant, but most patients receive supportive care, medications, or emerging targeted therapies to control symptoms and slow progression.
Standard treatment
Lenalidomide is recommended for lower-risk patients with the del(5q) cytogenetic abnormality and anemia
Chemotherapy regimens similar to those used in acute myeloid leukemia may be given to high-risk patients
Luspatercept and imetelstat are newer agents for lower-risk MDS and refractory anemia, showing promising results in clinical trials
Olutasidenib, a targeted drug for MDS patients with IDH1 mutations, has demonstrated strong outcomes in recent studies and is influencing current management
Repurposed drugs and Nutraceuticals
For myelodysplastic syndrome (MDS), the biology is different from solid tumors because the central problem is abnormal hematopoietic stem/progenitor cells, ineffective blood-cell production, chronic marrow inflammation, immune dysregulation, mitochondrial dysfunction, oxidative stress, and risk of progression to AML.
The Warburg effect is present in MDS providing a target for therapeutic approaches. Some evidence suggests that curcumin, resveratrol, vitamin D, and EGCG may have potential roles in the treatment or modulation of MDS.
The Most Important Repurposed Drugs and Nutraceuticals for MDS
🥇 Tier 1
Vitamin D3
Melatonin
Curcumin
Metformin
Sulforaphane
Berberine
EGCG
Omega-3 fatty acids
🥈 Tier 2
Thymosin-α1
Luteolin
Quercetin
Resveratrol/Pterostilbene
Doxycycline
Ivermectin
Aged garlic extract
🥉 Tier 3
Mebendazole
Atorvastatin/Simvastatin
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Lycopene
High-dose IV vitamin C
Acute Myeloid Leukemia (AML) – Pediatric (no radiation, standard chemotherapy)
For pediatric acute myeloid leukemia (AML), the therapeutic priorities differ from adult AML because:
Cure rates are substantially higher with intensive pediatric chemotherapy.
Children have greater susceptibility to long-term toxicities.
Preserving normal hematopoietic stem cell function, growth, neurodevelopment, fertility, and immune function is critical.
Any adjunctive therapy must have an excellent safety profile and must not interfere with standard chemotherapy.
From a metabolic perspective, pediatric AML shares many features with adult AML:
Leukemic stem cells (LSCs) are highly dependent on mitochondrial oxidative phosphorylation (OXPHOS).
BCL-2 signaling
PI3K–AKT–mTOR
NF-κB
STAT3
Bone marrow microenvironment
Reactive oxygen species (ROS) regulation
Fatty acid oxidation
However, because of the limited clinical evidence in children, I would rank agents much more conservatively than in adults.
The Most Important Repurposed Drugs and Nutraceuticals for Pediatric Acute Myeloid Leukemia
🥇 Tier 1
Vitamin D3
Melatonin
Omega-3 Fatty Acids
Curcumin
Sulforaphane
Metformin* (selected settings)
Berberine
EGCG
🥈 Tier 2
Doxycycline
Ivermectin
Luteolin
Quercetin
Resveratrol/Pterostilbene
Thymosin-α1
Apigenin
🥉 Tier 3
Mebendazole
Atorvastatin
Propranolol
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Genistein
Aged Garlic Extract
Lycopene
Overall Perspective
Pediatric AML has one of the strongest biological rationales for targeting leukemic stem cells and mitochondrial oxidative phosphorylation, but it is also a disease in which modern pediatric chemotherapy achieves high cure rates, and preserving long-term health is paramount. For that reason, adjunctive therapies should be selected with particular caution. Among the agents listed, vitamin D3, melatonin, and omega-3 fatty acids have the most favorable safety profiles, while doxycycline, metformin, ivermectin, and other metabolic agents remain investigational in this setting.
Any adjunctive therapy for a child with AML should be considered only in close collaboration with the treating pediatric oncology team, as there is currently no high-quality clinical evidence demonstrating that these repurposed drugs or nutraceuticals improve outcomes in pediatric AML. They should therefore be viewed as promising areas for future research rather than established components of standard care.
Adult AML
For adult acute myeloid leukemia (AML), the biology differs markedly from solid tumors. The major drivers include:
Leukemic stem cells (LSCs)—the principal source of relapse
Mitochondrial oxidative phosphorylation (OXPHOS) (particularly in LSCs)
BCL-2-mediated survival
PI3K–AKT–mTOR
FLT3, IDH1/2, and TP53 mutations (subset-dependent)
NF-κB and STAT3
Bone marrow microenvironment
Reactive oxygen species (ROS) homeostasis
Metabolic flexibility, with increasing fatty acid oxidation (FAO) and amino acid metabolism
Unlike many solid tumors, AML leukemic stem cells are highly dependent on mitochondrial oxidative phosphorylation, making mitochondrial-targeting strategies particularly attractive from a biological standpoint.
The ranking below is hypothesis-driven, based on mechanistic rationale, preclinical evidence, safety, and limited clinical data. It should not be interpreted as a validated treatment protocol.
The Most Important Repurposed Drugs and Nutraceuticals for Adult Acute Myeloid Leukemia
🥇 Tier 1
Doxycycline
Metformin
Melatonin
Curcumin
Vitamin D3
Berberine
Sulforaphane
EGCG
🥈 Tier 2
Ivermectin
Thymosin-α1
Omega-3 Fatty Acids
Luteolin
Quercetin
Resveratrol/Pterostilbene
Propranolol
🥉 Tier 3
Mebendazole
Atorvastatin
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
Lycopene
FLT3-Mutated AML
FLT3-mutated AML has high metabolic activity and aggressive biology.
Highest priorities
Doxycycline
Metformin
Curcumin
Melatonin
Sulforaphane
Berberine
EGCG
Vitamin D3
Ivermectin
Thymosin-α1
Relapsed/Refractory AML
Relapsed AML is enriched for OXPHOS-dependent leukemic stem cells.
Highest priorities
Doxycycline
Metformin
Melatonin
Curcumin
Sulforaphane
Berberine
EGCG
Ivermectin
Vitamin D3
Omega-3 Fatty Acids
Overall Perspective
Among hematologic malignancies, adult AML has one of the strongest biological rationales for targeting mitochondrial metabolism, particularly because leukemic stem cells are highly dependent on oxidative phosphorylation. This makes doxycycline uniquely attractive mechanistically compared with many solid tumors. Likewise, metformin, melatonin, curcumin, berberine, sulforaphane, and EGCG target complementary pathways involved in leukemic stem cell survival, inflammation, and metabolic adaptation.
One important caveat is that AML is an aggressive, rapidly progressive disease in which established therapies—including intensive chemotherapy, targeted agents (e.g., FLT3 and IDH inhibitors), hypomethylating agents, venetoclax-based regimens, and stem cell transplantation when appropriate—remain the standard of care. The agents ranked above should therefore be viewed, at present, as investigational adjuncts supported primarily by preclinical and mechanistic evidence, rather than proven alternatives or replacements for conventional AML treatment.
Chronic Lymphatic Leukemia
Recent years have seen a shift from traditional chemotherapy towards targeted drug therapies. Bruton tyrosine kinase (BTK) inhibitors such as ibrutinib, zanubrutinib, acalabrutinib, and pirtobrutinib disrupt cancer cell signaling and are commonly used, alone or with immunotherapy.
For chronic lymphocytic leukemia (CLL), the biology differs from both acute leukemias and solid tumors. CLL cells are slowly proliferating but highly metabolically active, relying heavily on mitochondrial oxidative phosphorylation (OXPHOS), fatty acid oxidation (FAO), and B-cell receptor (BCR) signaling rather than a classic Warburg phenotype. Other major biological drivers include:
B-cell receptor (BCR) signaling
PI3K–AKT–mTOR
NF-κB
BCL-2-mediated apoptosis resistance
Mitochondrial oxidative phosphorylation (OXPHOS)
Fatty acid oxidation (FAO)
Bone marrow and lymph node microenvironment
Immune dysfunction
Oxidative stress
Because of this biology, mitochondrial-targeting agents rank considerably higher in CLL than in most solid tumors.
The rankings below are hypothesis-driven, based on mechanistic rationale, preclinical evidence, safety, and limited clinical data. They are not substitutes for established therapies such as BTK inhibitors, BCL-2 inhibitors, anti-CD20 antibodies, or chemoimmunotherapy when indicated.
The Most Important Repurposed Drugs and Nutraceuticals for Chronic Lymphocytic Leukemia
🥇 Tier 1
Doxycycline
Metformin
Melatonin
Curcumin
Vitamin D3
Berberine
EGCG
Ivermectin
🥈 Tier 2
Sulforaphane
Omega-3 Fatty Acids
Thymosin-α1
Luteolin
Quercetin
Resveratrol/Pterostilbene
Propranolol
🥉 Tier 3
Mebendazole
Atorvastatin
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
Lycopene
Early-Stage (Rai 0–II) CLL
For patients under observation (”watch and wait”), emphasis should be placed on maintaining metabolic health and reducing chronic inflammation.
Highest priorities
Vitamin D3
Metformin
Melatonin
Curcumin
EGCG
Berberine
Omega-3 Fatty Acids
Sulforaphane
Doxycycline
Luteolin
Progressive or Relapsed CLL
Progressive disease is characterized by greater dependence on mitochondrial metabolism and resistance pathways.
Highest priorities
Doxycycline
Metformin
EGCG
Melatonin
Curcumin
Berberine
Ivermectin
Sulforaphane
Vitamin D3
Thymosin-α1
Overall Perspective
Among indolent hematologic malignancies, CLL has one of the strongest biological rationales for targeting mitochondrial metabolism because leukemic cells exhibit high mitochondrial mass, increased oxidative phosphorylation, and dependence on fatty acid oxidation, while remaining less glycolytic than many aggressive cancers. Consequently, doxycycline ranks unusually high because of its ability to impair mitochondrial protein synthesis, and metformin ranks highly for its effects on AMPK activation and mTOR inhibition. EGCG is also notable because it has been evaluated in early-phase clinical studies in CLL and has demonstrated biological activity, although it has not become standard therapy. Overall, this ranking emphasizes mitochondrial metabolism, BCR signaling, immune regulation, and chronic inflammation, while recognizing that current evidence for these adjunctive agents remains largely preclinical or early clinical and does not replace established CLL therapies.
Polycythemia Vera
Treatment for polycythemia vera (PV) focuses on reducing the risk of blood clots and controlling symptoms by keeping the hematocrit (red cell level) low and, when needed, lowering other blood counts. Therapy is individualized based mainly on age, history of thrombosis, symptoms, and tolerance of drugs.
Core first-line treatments
Phlebotomy (regular blood removal) is the mainstay for most people and is used to keep hematocrit below about 45%, which clearly lowers the risk of thrombosis
Low-dose aspirin (often 75–100 mg daily) is recommended for essentially all PV patients without contraindications, because it further reduces clotting risk.
Risk‑adapted cytoreductive therapy
“High‑risk” patients (typically age ≥60 or with a prior clot) are usually offered cytoreductive medication in addition to phlebotomy and aspirin to lower blood counts and clot risk.
Common first‑line cytoreductive drugs include, Hydroxyurea, an oral chemotherapy widely used in older or high‑risk patients.
For polycythemia vera (PV), the biology differs substantially from both solid tumors and acute leukemias. PV is a chronic myeloproliferative neoplasm (MPN) driven primarily by constitutive activation of JAK2 signaling (JAK2 V617F in approximately 95% of patients), leading to excessive erythrocyte production and a chronic inflammatory state.
Unlike AML, PV is not primarily driven by highly proliferative glycolytic metabolism, but rather by:
JAK–STAT activation (dominant driver)
Chronic inflammation (NF-κB, IL-6, TNF-α)
PI3K–AKT–mTOR
Abnormal hematopoietic stem cells
Oxidative stress
Bone marrow microenvironment
Thrombo-inflammation
Progression to myelofibrosis or AML
Consequently, anti-inflammatory and immune-modulating agents rank higher than strongly antiproliferative or mitochondrial-targeting agents.
The rankings below are hypothesis-driven, based on mechanistic rationale, preclinical evidence, safety, and limited clinical data. They should not replace established therapies such as phlebotomy, low-dose aspirin, interferon-α, hydroxyurea, or JAK inhibitors (e.g., ruxolitinib) when indicated.
The Most Important Repurposed Drugs and Nutraceuticals for Polycythemia Vera
🥇 Tier 1
Vitamin D3
Curcumin
Metformin
Melatonin
Omega-3 Fatty Acids
Berberine
Sulforaphane
EGCG
🥈 Tier 2
Thymosin-α1
Luteolin
Quercetin
Resveratrol/Pterostilbene
Ivermectin
Aged Garlic Extract
Propranolol
🥉 Tier 3
Doxycycline
Mebendazole
Atorvastatin (when otherwise indicated)
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Lycopene
High-Risk Polycythemia Vera
In patients with prior thrombosis or advanced disease, reducing inflammation and vascular risk becomes particularly important.
Highest priorities
Vitamin D3
Curcumin
Omega-3 Fatty Acids
Metformin
Melatonin
Berberine
Sulforaphane
EGCG
Aged Garlic Extract
Luteolin
Polycythemia Vera Receiving Ruxolitinib
Adjunctive strategies should focus on reducing residual inflammation and improving metabolic health.
Highest priorities
Vitamin D3
Curcumin
Metformin
Melatonin
Omega-3 Fatty Acids
Berberine
Sulforaphane
EGCG
Thymosin-α1
Luteolin
Overall Perspective
Unlike most cancers, polycythemia vera is driven primarily by dysregulated JAK–STAT signaling, chronic inflammation, and abnormal hematopoietic stem-cell function rather than by pronounced glycolysis or mitochondrial dependence. Consequently, anti-inflammatory and immune-modulating agents such as curcumin, vitamin D3, melatonin, omega-3 fatty acids, and sulforaphane are prioritized, while metformin and berberine provide complementary effects through AMPK activation and metabolic regulation. The primary clinical goals in PV remain prevention of thrombosis, control of blood counts, reduction of inflammatory symptoms, and prevention of progression to myelofibrosis or AML. These adjunctive agents have promising mechanistic rationale but should be considered investigational supportive therapies rather than established disease-modifying treatments.
Sarcomas
Sarcomas are cancers that arise from connective tissues such as bone, muscle, fat, and blood vessels, and usually have a poor prognosis for several key reasons:
Late diagnosis
High grade and aggressiveness
Large tumor size
Metastasis at diagnosis
Tumor location
Incomplete surgical removal
Tumor heterogeneity
Resistance to conventional therapy
Evidence shows sarcomas typically demonstrate the metabolic reprogramming characteristic of the Warburg effect. This metabolic shift contributes to their aggressive growth and provides potential therapeutic targets within cancer cell glycolytic pathways. While the prognosis remains poor and data on the use of repurposed drugs are limited, the following agents are suggested as adjunctive therapy:
For sarcoma, the dominant biology includes mesenchymal invasion, EMT-like programs, angiogenesis, PI3K–AKT–mTOR activation, cancer stem cells, mitochondrial plasticity, hypoxia, and metastatic spread, especially to lung.
The Most Important Repurposed Drugs and Nutraceuticals for Sarcoma
🥇 Tier 1
Metformin
Ivermectin
Doxycycline
Curcumin
Sulforaphane
Melatonin
Berberine
Vitamin D3
🥈 Tier 2
Mebendazole
EGCG
Propranolol
Omega-3 fatty acids
Luteolin
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
Lycopene
Bottom line: Sarcoma is a strong candidate for a CSC- and mitochondria-focused metabolic strategy because invasion, metastatic spread, hypoxia adaptation, PI3K/mTOR signaling, and mitochondrial plasticity are central to sarcoma progression and treatment resistance.
Mesothelioma
Surgery, radiation and chemotherapy appear to have a limited role in the treatment of mesothelioma. Niclosamide, used for parasitic infections, was found to exhibit anti-proliferative and pro-apoptotic activity against mesothelioma tumor cells, with studies showing inhibition of mTORC1 signaling and tumor growth in animal models. However, oral niclosamide has almost zero absorption.
For malignant mesothelioma, especially pleural mesothelioma, the dominant biology includes chronic asbestos-driven inflammation, NF-κB activation, PI3K–AKT–mTOR signaling, YAP/TAZ activation, cancer stem cells, angiogenesis, immune suppression, mitochondrial plasticity, fibrosis, and invasive local growth.
The Most Important Repurposed Drugs and Nutraceuticals for Mesothelioma
🥇 Tier 1
Ivermectin
Metformin
Curcumin
Melatonin
Vitamin D3
Sulforaphane
Berberine
EGCG
🥈 Tier 2
Doxycycline
Mebendazole
Propranolol
Omega-3 fatty acids
Luteolin
Quercetin
Resveratrol/Pterostilbene
🥉 Tier 3
Atorvastatin/Simvastatin
Thymosin-α1
Honokiol
Boswellia
Modified Citrus Pectin
Mistletoe
Apigenin
Genistein
Aged Garlic Extract
Lycopene
Bottom line: Mesothelioma is a strong candidate for a multi-target strategy because it is driven by chronic inflammation, YAP/TAZ signaling, mTOR activation, immune suppression, angiogenesis, fibrosis, and invasive CSC-like biology.
Safety Considerations
Curcumin and blood thinning
Curcumin has been reported to have blood-thinning properties, which may impair the body’s ability to form clots. The bleeding risk is heightened when curcumin is combined with certain medications:
Anticoagulants: Warfarin, heparin, and other blood thinners
Antiplatelet drugs: Aspirin, clopidogrel (Plavix)
NSAIDs: Nonsteroidal anti-inflammatory drugs
Potential manifestations of increased bleeding risk include:
Easy bruising
Abnormal bleeding (e.g., nosebleeds, bleeding gums)
Blood in stool or urine
Prolonged bleeding times
Excessive bleeding during surgery
To mitigate risk:
Discontinue curcumin supplementation at least two weeks before any scheduled surgery.
Avoid combining curcumin with other herbal supplements that may affect clotting (e.g., garlic, ginkgo biloba, fish oil).
Monitor for signs of increased bleeding, such as easy bruising or prolonged bleeding from cuts.
Metformin and berberine
Metformin and berberine both lower blood glucose. To prevent hypoglycemia, blood glucose should be monitored when the two are used simultaneously. Alternatively, reduce the dose of berberine to once daily or metformin to 500 mg twice daily.
Doxycycline and the microbiome
Doxycycline appears to have minimal impact on the overall composition and diversity of the gut microbiome:
· No significant differences in bacterial taxonomic alpha or beta diversity have been observed between doxycycline users and controls.
· The normalized bacterial mass of the gut microbiome remains stable after doxycycline use.
· No consistent differential abundance of bacterial genera was found between baseline and six months after doxycycline use.
Green tea (EGCG) and hepatotoxicity
EGCG is rarely associated with liver injury. The risk of toxicity is reduced when the daily dose is kept below 800 mg, the dose is gradually increased over several weeks, and it is taken with food and/or vitamin C. Drinking brewed green tea (≤4 cups/day) poses minimal risk of hepatotoxicity.
Curcumin taken with EGCG may increase the risk of hepatotoxicity. Concomitant use with piperine may further elevate this risk.
Liver function tests should be monitored regularly, particularly when initiating therapy. These supplements should be avoided in patients with a history of liver disease or those receiving chronic lymphocytic leukemia-directed therapy. USP-verified supplements are recommended.
Zinc and prostate cancer
Prostate cancer cells exhibit a 70–80% reduction in zinc levels compared to healthy prostate tissue. Low-dose (1–24 mg/day) zinc supplementation after diagnosis has been associated with a lower risk of lethal prostate cancer and all-cause mortality among men with nonmetastatic disease (stage 1–3). However, high-dose supplementation (>75 mg/day) and prolonged use (10 years or more) have been linked to increased risk and aggressiveness of prostate cancer. While zinc shows therapeutic potential, its dose-dependent biphasic effects require careful clinical management. Current evidence supports cautious low-dose use, particularly in early-stage patients, while avoiding high-dose or long-term supplementation.
Conclusion
Repurposed drugs and metabolic strategies can provide meaningful adjuncts to conventional cancer therapy, particularly by targeting CSCs and treatment resistance. While promising, their use should be individualized, closely monitored, and integrated with standard care. Continued research is essential to define best practices and confirm therapeutic potential.

Dear Dr. Marik, an uncle of mine is said to have questioned the artist of a painting about what he considered an exorbitant price. In answer to my uncle’s query, “How long did it take you to make this piece?”, the artist said, “All my life”. … Having watched your careful attention to Covid patients, and your gradual transfer from the intensive-care theater to that of cancer care, I estimate the “value” of this paper, (i.e. the price, if such could be applied) would be “all your life”. And yet, you are generously sharing details of a novel pathway, or adjunct approach to cancer therapy, with any person who cares to know, at zero monetary cost. I have watched you share your personal response to the denial of life-saving repurposed drugs to your hospitalized patients. Therefore, I hope this paper serves to preclude that sort of outcome for patients with cancer. … My thanks can best be expressed in a prayer: May the blessings of our Divine Physician descend upon you and remain with you forever.
Thank you Dr Marik for your unselfish dedication to the healing profession, and your sharing of this “invaluable” work/knowledge!