

In my previous post, I reviewed strategies for preventing colorectal cancer, highlighting lifestyle measures, dietary interventions, and the role of screening colonoscopy. Following its publication, several subscribers raised an important point: in many healthcare settings, flexible sigmoidoscopy may offer a practical and effective alternative to full colonoscopy.
This thoughtful feedback prompted me to take a closer look at the evidence. In this post, I examine the role of flexible sigmoidoscopy in colorectal cancer screening, comparing its benefits, limitations, and effectiveness with colonoscopy. For many individuals, the choice between these procedures is not straightforward, and understanding the strengths and weaknesses of each can help patients make more informed decisions in consultation with their healthcare providers.
Introduction
Colorectal cancer (CRC) is the third most diagnosed cancer worldwide and remains one of the leading causes of cancer-related mortality. In the United States alone, more than 150,000 new cases are diagnosed annually, and approximately 50,000 people die from the disease each year. Unlike many other cancers, colorectal cancer is particularly amenable to prevention because most malignancies develop gradually through the adenoma–carcinoma sequence over a period of 10 to 15 years. During this prolonged preclinical phase, adenomatous polyps can be identified and removed before malignant transformation occurs, making colorectal cancer screening one of the few interventions capable of both preventing cancer and reducing cancer-related mortality.
Several screening strategies are currently available, including stool-based tests, CT colonography, colon capsule endoscopy, flexible sigmoidoscopy, and colonoscopy. Among these, colonoscopy has traditionally been regarded as the “gold standard” because it permits direct visualization of the entire colon and simultaneous removal of premalignant polyps. However, colonoscopy is an invasive procedure that requires full bowel preparation, sedation in most patients, specialized equipment, and highly trained personnel. It also carries a small but measurable risk of serious complications, including bleeding and perforation.
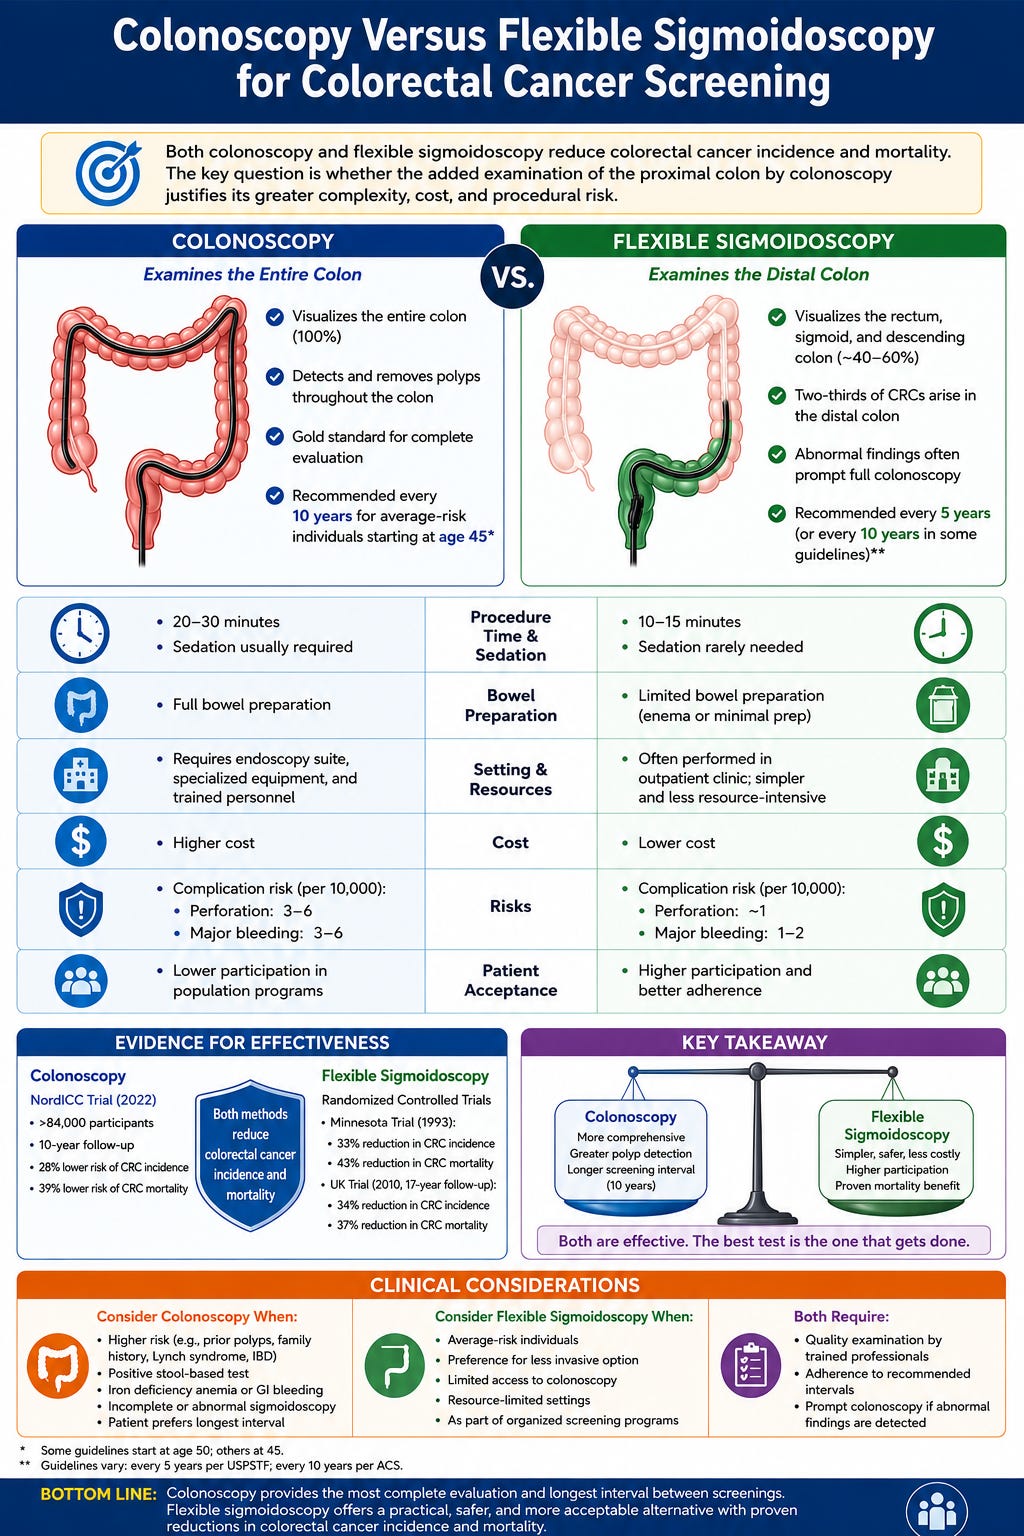
Flexible sigmoidoscopy represents a simpler alternative. The procedure examines only the distal colon but is quicker, less invasive, less expensive, and associated with substantially fewer complications. Importantly, several large randomized clinical trials have demonstrated significant reductions in colorectal cancer incidence and mortality with flexible sigmoidoscopy, whereas randomized evidence supporting colonoscopy has emerged only recently.
The central question therefore is not whether colorectal cancer screening is beneficial—it clearly is—but whether the additional examination of the proximal colon provided by colonoscopy justifies its greater complexity, cost, and procedural risk compared with flexible sigmoidoscopy.
Colonoscopy
Colonoscopy remains the most comprehensive endoscopic examination of the large intestine. The colonoscope is advanced from the rectum to the cecum, allowing direct visualization of the entire colon.
Its principal advantage lies in its dual diagnostic and therapeutic capability. During a single procedure, physicians can detect adenomatous polyps, remove them using polypectomy techniques, obtain biopsies of suspicious lesions, identify inflammatory bowel disease, investigate gastrointestinal bleeding, and evaluate unexplained anemia or changes in bowel habit.
Current guidelines generally recommend screening colonoscopy every ten years for average-risk individuals beginning at age 45, provided the examination is complete and no advanced neoplasia is detected.
Because colonoscopy visualizes the entire colon, it has long been assumed to provide superior protection against colorectal cancer compared with more limited examinations.
Flexible Sigmoidoscopy
Flexible sigmoidoscopy examines only the rectum, sigmoid colon, and descending colon, typically extending to the splenic flexure. Consequently, approximately 40–60% of the colon is directly visualized.
Although the examination is anatomically limited, this does not necessarily translate into proportionally reduced clinical benefit.
Historically, approximately two-thirds of colorectal cancers arise within the distal colon, placing them within reach of the sigmoidoscope. Furthermore, many patients who harbor advanced proximal neoplasms also possess distal adenomas, meaning that abnormal findings on sigmoidoscopy frequently trigger a complete colonoscopy.(1)
Unlike colonoscopy, flexible sigmoidoscopy usually requires only limited bowel preparation, rarely requires sedation, can often be performed in an outpatient clinic, and typically takes only 10–15 minutes.(1)
These practical advantages have been translated into higher patient acceptance in many screening programs.
Evidence Supporting Colonoscopy
For many years, the widespread adoption of colonoscopy occurred despite the absence of randomized clinical trial evidence.
Recommendations were based primarily on:
observational cohort studies,
case-control studies,
biological plausibility,
and the demonstrated effectiveness of polypectomy.
The first randomized evidence emerged with publication of the NordICC Trial in 2022.
The NordICC Trial
The Nordic-European Initiative on Colorectal Cancer (NordICC) enrolled more than 84,000 adults aged 55 to 64 years from four European countries.(2)
Participants were randomized either to receive an invitation for screening colonoscopy or to continue with usual care.
After approximately ten years of follow-up, colorectal cancer developed in:
0.98% of individuals invited for colonoscopy
1.20% of controls
This represented an 18% relative reduction in colorectal cancer incidence.
The absolute reduction, however, was modest—approximately 0.22%.
With respect to colorectal cancer mortality, no statistically significant reduction was observed in the primary intention-to-screen analysis.
These findings generated considerable debate.(1)
However, only 42% of individuals invited to undergo colonoscopy actually completed the procedure. Among patients who underwent colonoscopy (per-protocol analysis), substantially greater reductions in both colorectal cancer incidence and mortality were observed.
Consequently, many investigators concluded that the trial primarily highlighted the importance of screening participation, rather than questioning the efficacy of colonoscopy itself.
Evidence Supporting Flexible Sigmoidoscopy
In contrast to colonoscopy, flexible sigmoidoscopy is supported by several large randomized clinical trials.(1)
These include:
the UK Flexible Sigmoidoscopy Trial, (3-5)
the SCORE Trial, (6)
the NORCCAP Trial, (7)
and the PLCO Trial. (8)
Collectively, these studies enrolled more than 400,000 participants.
Meta-analyses consistently demonstrate that flexible sigmoidoscopy reduces:(9, 10)
colorectal cancer incidence by approximately 20–25%
colorectal cancer mortality by approximately 25–30%
These findings have remained remarkably consistent across different populations and healthcare systems.
In the UK Flexible Sigmoidoscopy Trial, a single flexible sigmoidoscopy continued to provide substantial protection from colorectal cancer diagnosis and death, with protection lasting at least 21 years. (4, 5)
The strength of this randomized evidence explains why flexible sigmoidoscopy continues to occupy an important role in colorectal cancer screening despite its inability to examine the entire colon.
Why Does Flexible Sigmoidoscopy Work So Well?
Several biological factors explain its surprisingly high effectiveness.(1)
First, most colorectal cancers arise within the distal colon.
Second, distal adenomas frequently serve as markers for synchronous proximal neoplasia, leading to referral for colonoscopy.
Third, removal of distal adenomas interrupts progression along the adenoma–carcinoma sequence.
Finally, participation rates are often substantially higher than those achieved with colonoscopy because the examination is shorter, simpler, and better tolerated.(1)
These factors together compensate for the inability to visualize the proximal colon directly.
Right-Sided Colon Cancer
The principal limitation of flexible sigmoidoscopy is its inability to examine the proximal colon.(1)
Approximately 30–40% of colorectal cancers develop proximal to the splenic flexure.
These include malignancies arising within the:
ascending colon,
transverse colon,
and cecum.
Colonoscopy clearly offers an advantage in detecting these lesions.
Nevertheless, recent research has demonstrated that right-sided colorectal cancers differ biologically from left-sided tumors.(11, 12)
Many arise through the serrated neoplasia pathway rather than the conventional adenoma–carcinoma sequence.
They are often:
flatter,
more difficult to detect,
covered by mucus,
and less conspicuous during endoscopy.
Consequently, even colonoscopy provides less protection against right-sided cancers than against left-sided lesions.
Thus, although colonoscopy unquestionably visualizes more of the colon, the additional benefit is not as large as might initially be expected.(1)
Risks and Complications
Both procedures are considered safe.
However, colonoscopy carries a higher complication rate.(13)
Major complications include:
bleeding following polypectomy,
perforation,
post-polypectomy syndrome,
cardiopulmonary complications related to sedation.
Perforation occurs in approximately 0.5–1 per 1,000 procedures, while significant bleeding occurs in approximately 2–8 per 1,000 procedures, particularly after removal of larger polyps.(13)
Although mortality is extremely uncommon, deaths related to colonoscopy have been estimated at approximately 1–3 per 100,000 procedures.
Flexible sigmoidoscopy has a substantially lower complication rate.(13)
Because sedation is rarely required and less extensive instrumentation is performed, perforation occurs approximately five- to ten-fold less frequently than during colonoscopy.
Major bleeding is uncommon.
These safety differences become increasingly important when screening millions of asymptomatic individuals.
Patient Acceptance and Participation
One of the most important determinants of screening success is patient participation.
Many individuals decline colonoscopy because of:
full bowel preparation,
sedation,
need for transportation,
time away from work,
anxiety regarding the procedure.
Flexible sigmoidoscopy avoids many of these barriers.(1)
It requires only limited bowel preparation, is usually performed without sedation, and allows patients to resume normal activities immediately afterward.
Consequently, participation rates in organized screening programs are frequently higher than those achieved with colonoscopy.
Since screening effectiveness depends not only on test sensitivity but also on the proportion of the population screened, higher participation may substantially increase the public health impact of flexible sigmoidoscopy.
Cost-Effectiveness
Economic analyses consistently demonstrate that flexible sigmoidoscopy is substantially less expensive than colonoscopy.(14, 15)
When combined with annual or biennial fecal immunochemical testing (FIT), flexible sigmoidoscopy achieves reductions in colorectal cancer mortality approaching those observed with colonoscopy while requiring fewer resources and exposing fewer individuals to procedural complications.
This combined strategy has therefore been adopted in several national screening programs.(16)
Which Patients Should Undergo Colonoscopy?
Despite the advantages of flexible sigmoidoscopy, colonoscopy remains the preferred investigation for patients with increased colorectal cancer risk.(1)
These include individuals with:
a positive FIT,
rectal bleeding,
iron deficiency anemia,
previous adenomatous polyps,
inflammatory bowel disease,
hereditary colorectal cancer syndromes,
strong family history of colorectal cancer,
unexplained gastrointestinal symptoms.
In these patients, complete examination of the colon is essential.
Screening Average-Risk Individuals
For average-risk adults, current evidence supports several acceptable screening strategies.
These include:(16)
colonoscopy every ten years,
flexible sigmoidoscopy every five to ten years,
annual or biennial FIT,
stool DNA testing,
CT colonography.
Increasingly, experts emphasize that the best screening test is the one that the patient is willing to complete.
A highly sensitive examination provides no benefit if it is never performed.
Conclusions
Both colonoscopy and flexible sigmoidoscopy are effective methods of colorectal cancer screening, but they represent different balances between diagnostic completeness, procedural risk, patient acceptance, and healthcare costs.
Colonoscopy remains the most comprehensive examination and is clearly preferred for patients at increased risk or with abnormal screening tests. Its ability to detect and remove lesions throughout the entire colon is unmatched.
Flexible sigmoidoscopy, however, has stronger randomized clinical trial evidence demonstrating reductions in colorectal cancer incidence and mortality, while offering lower cost, fewer complications, shorter procedure times, and higher patient participation. When combined with FIT testing, it provides an effective and highly cost-efficient screening strategy for many average-risk individuals.
Ultimately, the objective of colorectal cancer screening is not simply to perform the most comprehensive examination but to maximize participation, detect premalignant lesions, and reduce colorectal cancer mortality. From this perspective, both colonoscopy and flexible sigmoidoscopy have important roles, and the optimal strategy should be individualized according to a patient’s risk profile, preferences, access to care, and overall health.
References
1. Powell K, Prasad V. Interpreting the results from the first randomised controlled trial of colonoscopy: does it save lives? BMJ Evid Based Med. 2023;28(5):306–8.
2. Bretthauer M, Løberg M, Wieszczy P, Kalager M, Emilsson L, Garborg K, et al. Effect of Colonoscopy Screening on Risks of Colorectal Cancer and Related Death. N Engl J Med. 2022;387(17):1547–56.
3. Atkin WS, Edwards R, Kralj-Hans I, Wooldrage K, Hart AR, Northover JM, et al. Once-only flexible sigmoidoscopy screening in prevention of colorectal cancer: a multicentre randomised controlled trial. Lancet. 2010;375(9726):1624–33.
4. Atkin W, Wooldrage K, Parkin DM, Kralj-Hans I, MacRae E, Shah U, et al. Long term effects of once-only flexible sigmoidoscopy screening after 17 years of follow-up: the UK Flexible Sigmoidoscopy Screening randomised controlled trial. Lancet. 2017;389(10076):1299–311.
5. Wooldrage K, Robbins EC, Duffy SW, Cross AJ. Long-term effects of once-only flexible sigmoidoscopy screening on colorectal cancer incidence and mortality: 21-year follow-up of the UK Flexible Sigmoidoscopy Screening randomised controlled trial. Lancet Gastroenterol Hepatol. 2024;9(9):811–24.
6. Segnan N, Armaroli P, Bonelli L, Risio M, Sciallero S, Zappa M, et al. Once-only sigmoidoscopy in colorectal cancer screening: follow-up findings of the Italian Randomized Controlled Trial--SCORE. J Natl Cancer Inst. 2011;103(17):1310–22.
7. Holme Ø, Løberg M, Kalager M, Bretthauer M, Hernán MA, Aas E, et al. Effect of flexible sigmoidoscopy screening on colorectal cancer incidence and mortality: a randomized clinical trial. Jama. 2014;312(6):606–15.
8. Schoen RE, Pinsky PF, Weissfeld JL, Yokochi LA, Church T, Laiyemo AO, et al. Colorectal-cancer incidence and mortality with screening flexible sigmoidoscopy. N Engl J Med. 2012;366(25):2345–57.
9. Juul FE, Cross AJ, Schoen RE, Senore C, Pinsky P, Miller E, et al. 15-Year Benefits of Sigmoidoscopy Screening on Colorectal Cancer Incidence and Mortality : A Pooled Analysis of Randomized Trials. Ann Intern Med. 2022;175(11):1525–33.
10. Holme Ø, Schoen RE, Senore C, Segnan N, Hoff G, Løberg M, et al. Effectiveness of flexible sigmoidoscopy screening in men and women and different age groups: pooled analysis of randomised trials. Bmj. 2017;356:i6673.
11. Lee MS, Menter DG, Kopetz S. Right Versus Left Colon Cancer Biology: Integrating the Consensus Molecular Subtypes. J Natl Compr Canc Netw. 2017;15(3):411–9.
12. Salem ME, Weinberg BA, Xiu J, El-Deiry WS, Hwang JJ, Gatalica Z, et al. Comparative molecular analyses of left-sided colon, right-sided colon, and rectal cancers. Oncotarget. 2017;8(49):86356–68.
13. Kindt IS, Martiny FHJ, Gram EG, Bie AKL, Jauernik CP, Rahbek OJ, et al. The risk of bleeding and perforation from sigmoidoscopy or colonoscopy in colorectal cancer screening: A systematic review and meta-analyses. PLoS One. 2023;18(10):e0292797.
14. Lansdorp-Vogelaar I, Knudsen AB, Brenner H. Cost-effectiveness of colorectal cancer screening. Epidemiol Rev. 2011;33(1):88–100.
15. Diedrich L, Brinkmann M, Dreier M, Rossol S, Schramm W, Krauth C. Is there a place for sigmoidoscopy in colorectal cancer screening? A systematic review and critical appraisal of cost-effectiveness models. PLoS One. 2023;18(8):e0290353.
16. Davidson KW, Barry MJ, Mangione CM, Cabana M, Caughey AB, Davis EM, et al. Screening for Colorectal Cancer: US Preventive Services Task Force Recommendation Statement. Jama. 2021;325(19):1965–77.
New Here?
Start with the: Cancer and the Metabolic Library

The approach to screening should be individualized based on risk factors and patient choice;; you would seem to be in the very low risk group.
Why should folks who have none of the history, risk, or symptoms undergo any of these tests? I eat a healthy diet of organic and home grown produce and locally produced meats, plus home grown herbs and teas. I have no issues with digestion at all, but am constantly being told to get these tests!