

I used to be a type II diabetic. My HbA1C hovered around 8%, even while taking metformin and Jardiance. Every doctor told me the same thing: type II diabetes is progressive, lifelong, and inevitably leads to complications. I accepted it — I exercised, took my medications, and tried to make peace with that prognosis.
Then came COVID, and it completely changed how I saw my health. I began questioning what I had been told and discovered that much of it simply wasn’t true. With surprisingly simple lifestyle changes — eating real, unprocessed food, incorporating intermittent fasting, and losing weight — I reversed my diabetes. Today, my HbA1C is 4.9%.
My name is Paul, and this is my story. It could just as easily be yours.
Over the past half century, a profound shift has occurred in the global burden of disease. Conditions once considered distinct—type 2 diabetes, cardiovascular disease, obesity, and even aspects of cancer and neurodegeneration—are increasingly recognized as interconnected manifestations of a single underlying disorder: insulin resistance.
Insulin resistance is not merely a biochemical abnormality. It is a systemic failure of metabolic regulation—an adaptive response to chronic nutritional excess and environmental mismatch. At its clinical extreme, this process is expressed as metabolic syndrome, a constellation of abnormalities that now affects more than one-third of adults in the United States and approximately one-quarter of the global population.
Importantly, insulin resistance precedes overt disease by years, often decades. It is therefore both a predictor and a driver of chronic illness. Understanding its biology provides not only insight into disease pathogenesis, but also a powerful framework for prevention and reversal.
Pathophysiology of Insulin Resistance
Insulin is the central hormone regulating energy utilization, facilitating the uptake of glucose into muscle and adipose tissue while suppressing hepatic glucose production. In insulin resistance, target tissues—primarily skeletal muscle, liver, and adipose tissue—become less responsive to insulin signaling. The pancreas compensates by increasing insulin secretion, leading to hyperinsulinemia, which initially maintains normoglycemia but ultimately fails, resulting in hyperglycemia and type 2 diabetes.
However, the pathological consequences of insulin resistance extend far beyond glucose metabolism. The condition is characterized by a triad of:
Hyperglycemia
Hyperinsulinemia
Chronic low-grade inflammation
These processes act synergistically to damage vascular endothelium, promote atherogenesis, disrupt mitochondrial function, and impair cellular signaling across multiple organ systems.
The Central Role of Visceral Adiposity
A key driver of insulin resistance is visceral (intra-abdominal) fat. Unlike subcutaneous fat, visceral adipose tissue is metabolically active and highly inflammatory. It secretes a range of cytokines—collectively termed adipokines—that promote systemic inflammation and interfere with insulin signaling.
Notably, visceral fat produces significantly higher levels of inflammatory mediators than subcutaneous fat, creating a state of chronic immune activation that affects the liver, pancreas, cardiovascular system, and brain.
The Liver as a Metabolic Hub
The liver plays a central role in the development of insulin resistance. Accumulation of fat within hepatocytes (non-alcoholic fatty liver disease) leads to:
Increased gluconeogenesis
Increased lipogenesis
Impaired insulin signaling
This creates a self-reinforcing cycle in which hepatic fat accumulation drives further metabolic dysfunction.
Figure 1. Insulin Resistance
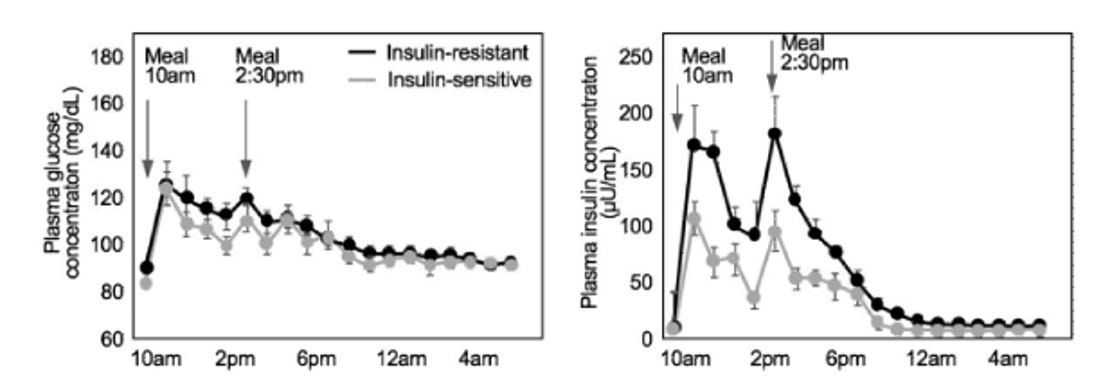
Must measure both glucose and insulin simultaneously and calculate the HOMA (Homeostasis Model Assessment) for Insulin Resistance
Metabolic Syndrome: The Clinical Expression
Metabolic syndrome represents the clinical manifestation of insulin resistance. It is defined by the presence of multiple cardiometabolic abnormalities, including central obesity, hypertension, dyslipidemia, and impaired glucose metabolism.
The syndrome is not merely a diagnostic construct; it is a powerful predictor of:
Type 2 diabetes
Cardiovascular disease
Stroke
Accelerated biological aging
Importantly, metabolic syndrome reflects a system-wide failure of energy regulation, rather than isolated organ dysfunction.
Etiology: A Disease of Modern Lifestyle
Although genetic predisposition may play a role, insulin resistance is fundamentally a disease of environmental mismatch.
Human metabolism evolved under conditions characterized by:
Intermittent food availability
High physical activity
Minimal exposure to refined carbohydrates
In contrast, the modern environment is defined by:
Continuous caloric intake
High consumption of refined carbohydrates and fructose
Processed foods and industrial seed oils
Sedentary behavior
This mismatch overwhelms metabolic pathways, leading to chronic elevations in insulin and glucose and ultimately to metabolic dysfunction.
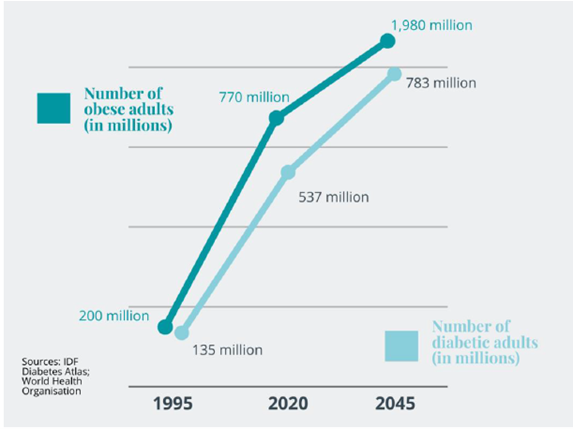
Figure 2. Worldwide incidence of obesity and diabetes (1980-2020, projected to 2045
Diagnosis and Clinical Assessment
The diagnosis of metabolic syndrome is based on simple clinical and laboratory parameters, including waist circumference, blood pressure, fasting glucose, triglycerides, and HDL cholesterol.
Of particular importance is the triglyceride-to-HDL ratio, which may be a more sensitive marker of metabolic dysfunction and cardiovascular risk than traditional lipid measurements.
In clinical practice, insulin resistance often precedes abnormalities in fasting glucose or HbA1c, highlighting the importance of early recognition.
Core Tests
Fasting glucose
HbA1c
Triglycerides
HDL
Key Insight (Important clinically)
TG/HDL ratio is emphasized as a superior predictor of cardiovascular risk
👉 Target: ≤2:1
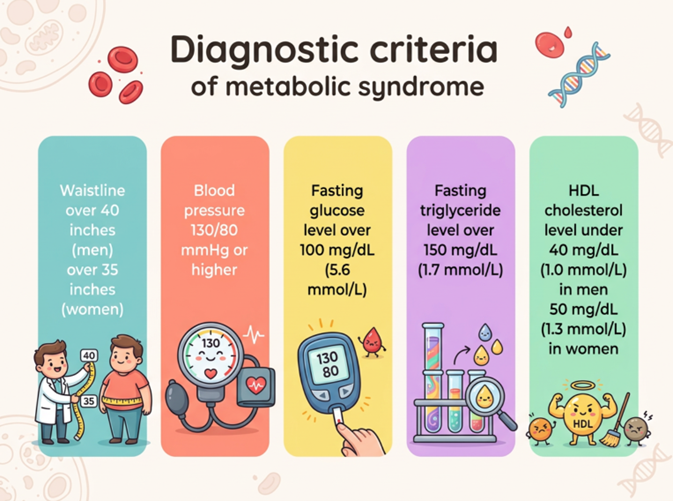
Diagnostic Criteria (any ≥3):
Central obesity (waist >40 in men, >35 in women)
BP ≥130/80 mmHg
Fasting glucose >100 mg/dL
Triglycerides >150 mg/dL
Low HDL (<40 men, <50 women)
Figure 3. Diagnostic Criteria of Metabolic Syndrome
Therapeutic Principles: Reversing the Root Cause
A central theme of this approach is that insulin resistance is not an inevitable, progressive disease, but rather a reversible metabolic state.
Treatment strategies should therefore focus on correcting the underlying drivers rather than merely controlling blood glucose. THIS IS A REVERSIBLE METABOLIC CONDITION.
Dietary Intervention
The cornerstone of therapy is a low-carbohydrate, nutrient-dense diet designed to reduce insulin secretion and restore metabolic flexibility.
Such diets emphasize:
Healthy fats (saturated and monounsaturated)
Omega-3 fatty acids
Whole, unprocessed foods
and restrict:
Refined carbohydrates
Sugars and fructose
Processed foods
Industrial seed oils
Reducing carbohydrate intake directly lowers insulin levels, thereby addressing the primary hormonal driver of insulin resistance.
Intermittent Fasting and Time-Restricted Eating
Among all interventions, intermittent fasting emerges as one of the most powerful tools for restoring insulin sensitivity.
Fasting:
Reduces circulating insulin levels
Promotes lipolysis and fat oxidation
Enhances mitochondrial function
Activates autophagy and cellular repair pathways
Time-restricted eating—gradually reducing the daily eating window—provides a practical and sustainable approach to implementing fasting in clinical practice.
Figure 4. Mediterranean “real food” diet with healthy oils and no processed food.

Physical Activity and Stress Modulation
Regular physical activity improves insulin sensitivity by enhancing glucose uptake and mitochondrial function. However, excessive endurance exercise may increase cortisol and worsen metabolic control, highlighting the importance of balance.
Chronic stress, through activation of the hypothalamic–pituitary–adrenal axis, increases cortisol and catecholamines, both of which elevate blood glucose and exacerbate insulin resistance.
Pharmacologic and Nutraceutical Interventions
While lifestyle modification remains the foundation of therapy, several agents may provide additional metabolic benefit.
Metformin
Metformin improves insulin sensitivity and reduces hepatic glucose production. It remains a first-line pharmacologic agent in type 2 diabetes and has additional cardiometabolic and potential anti-aging effects.
Berberine
Berberine is a particularly notable agent, acting through multiple pathways to:
Improve insulin sensitivity
Reduce hepatic glucose production
Enhance lipid metabolism
Decrease inflammation
Clinical studies suggest that berberine may be as effective as metformin in improving metabolic parameters, with potential synergistic effects when used in combination.
Additional Adjuncts
Other agents—including magnesium, melatonin, omega-3 fatty acids, resveratrol, cinnamon, and probiotics—may contribute to metabolic improvement through effects on inflammation, mitochondrial function, and the gut microbiome.
A Paradigm Shift in Chronic Disease
The traditional view of type 2 diabetes as a chronic, progressive disease requiring lifelong pharmacotherapy is increasingly being challenged. Emerging evidence suggests that, by targeting the root causes of insulin resistance, it is possible to achieve meaningful and sustained reversal.
This represents a fundamental shift—from disease management to metabolic restoration.
Conclusion
Insulin resistance is the central metabolic disturbance underlying many of the most prevalent diseases of modern society. It is driven primarily by lifestyle factors, particularly excessive carbohydrate intake, visceral adiposity, and chronic inflammation.
Crucially, insulin resistance is reversible.
Interventions that reduce insulin levels—most notably low-carbohydrate nutrition and intermittent fasting—address the root cause of metabolic dysfunction. When combined with targeted pharmacologic and nutraceutical strategies, these approaches offer a comprehensive and effective framework for restoring metabolic health.
In this light, metabolic syndrome is not simply a diagnosis, but a warning signal—an opportunity to intervene before irreversible disease develops.
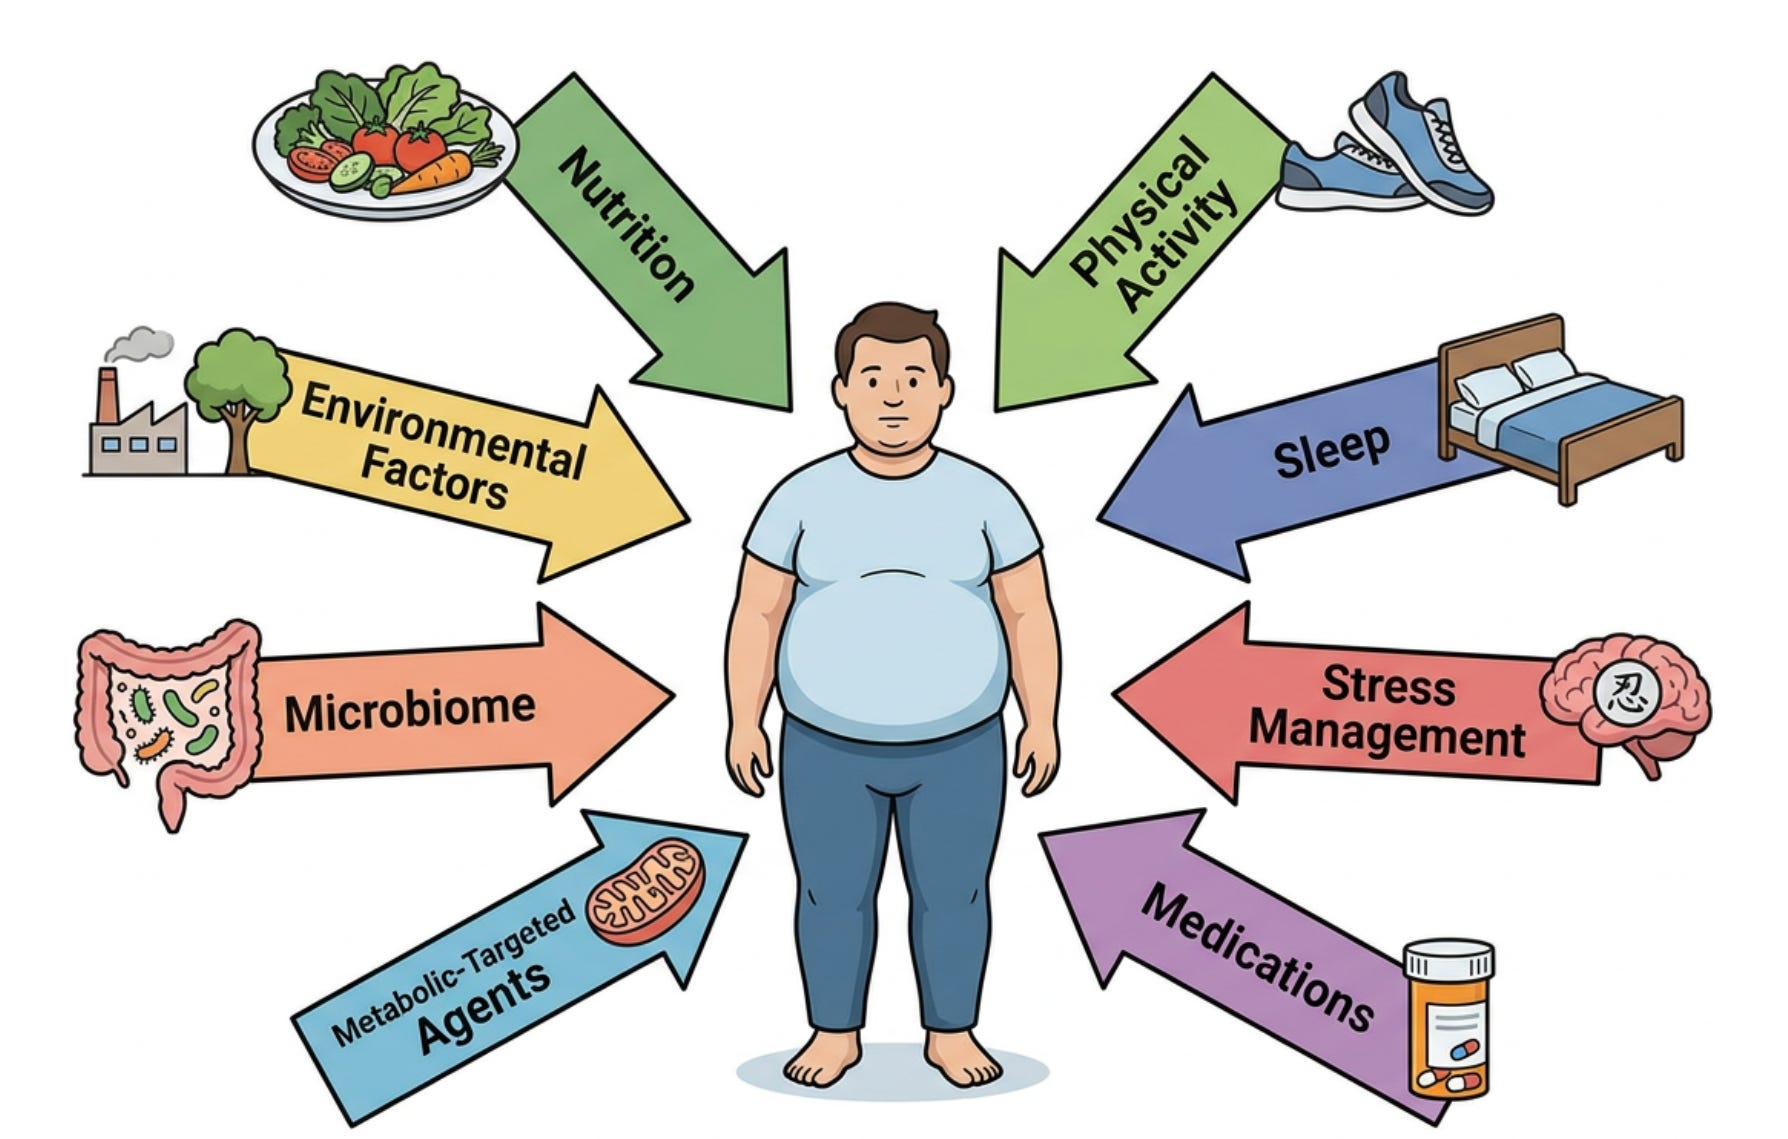
Figure 4. The multi-axis approach to reversing the metabolic syndrome

Medical Disclaimer: The discussion of repurposed medications and nutraceuticals in this article is intended to review the scientific literature and does not constitute a recommendation for self-treatment. Decisions regarding the use of off-label therapies should be made in consultation with a qualified healthcare professional familiar with the patient’s medical history and current treatment plan. Please see the full Medical Disclaimer on the introductory page to Marik’s Cancer & Metabolic Healing Playbook.
Basically, we have excellent emergency\trauma care in the U.S. The rest is for the most part, based on what is most profitable. That is what the incentive dictates so that is the result you get. It isn’t a complicated concept.
Paul, brilliant synthesis of the central problem axis! Hope to see you in RI. I am the ortho surgeon in NC whom you helped with Covid Rx during the height of that debacle which woke many of us up.