

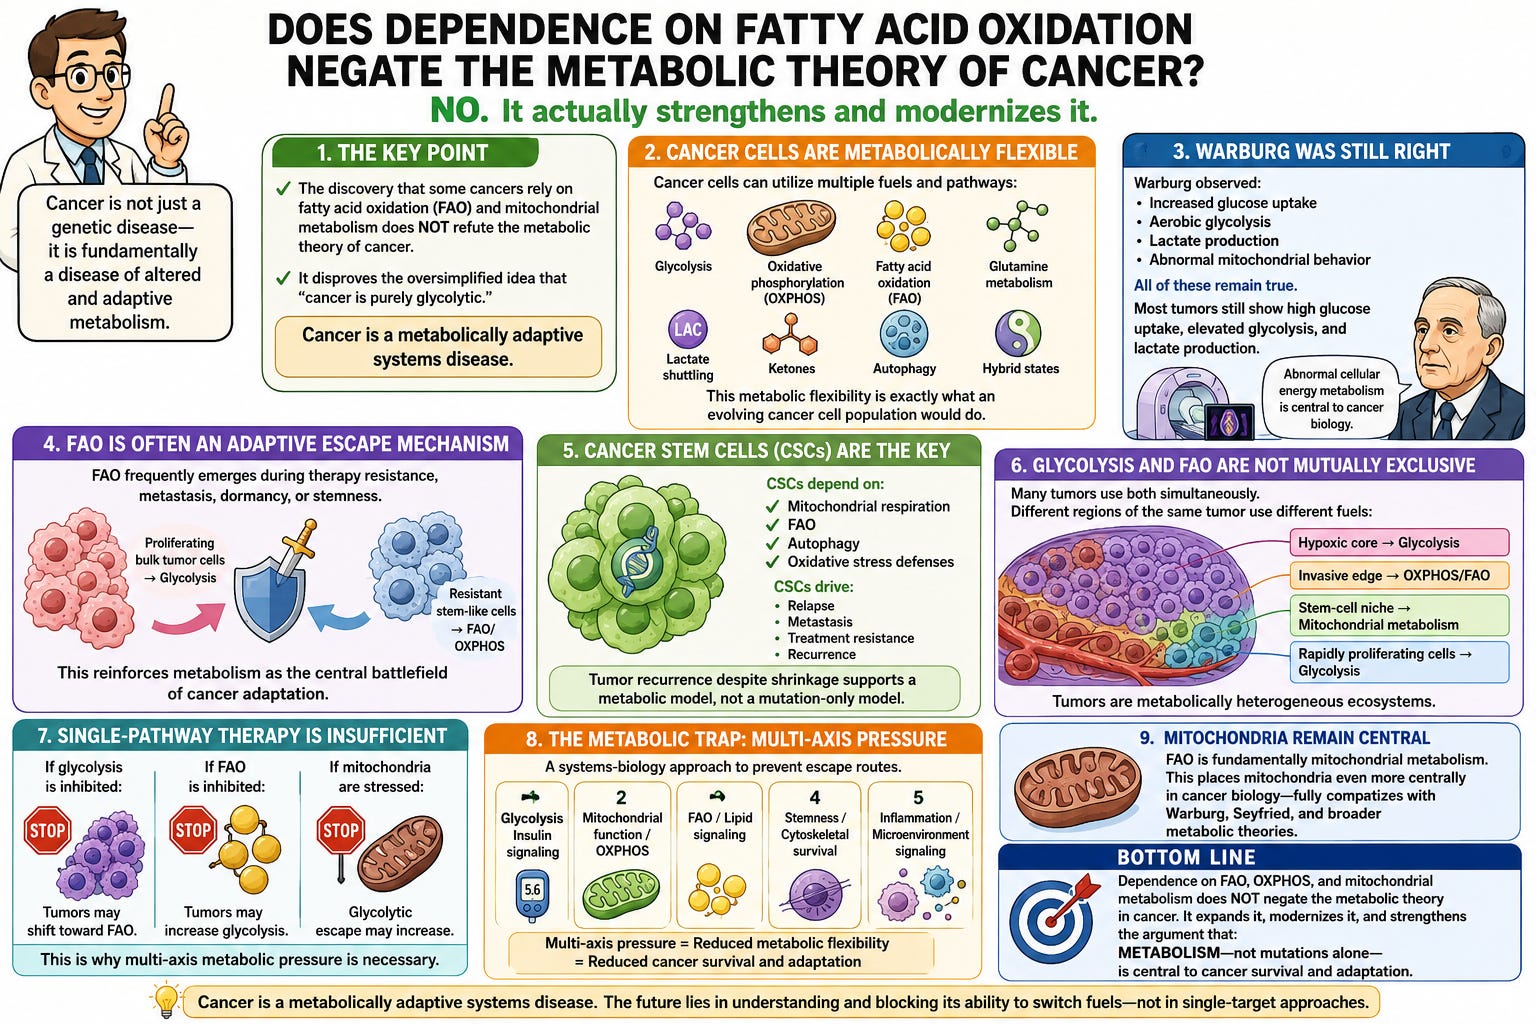
No. In many ways, the discovery that some cancers depend heavily on:
fatty acid oxidation (FAO) and mitochondrial metabolism
actually:
strengthens and modernizes the metabolic theory of cancer rather than disproving it.
What it disproves is:
an overly simplistic interpretation of the Warburg effect.
There is a major difference between:
“Cancer is purely glycolytic,”
and:“Cancer is fundamentally a disease of altered and adaptive metabolism.”
The second statement remains strongly supported.
The critical misunderstanding
Many people incorrectly equated the:
metabolic theory of cancer
with:
“all cancers only use glucose.”
That was never really Warburg’s deeper point.
Warburg’s central thesis was that:
abnormal cellular energy metabolism and mitochondrial dysfunction are central to cancer biology.
Modern research strongly supports this broader concept.
What the FAO data actually shows
The FAO/OXPHOS literature demonstrates that:
cancer cells are metabolically flexible.
Cancer cells may utilize:
glycolysis,
oxidative phosphorylation,
fatty acid oxidation,
glutamine metabolism,
lactate shuttling,
ketones,
autophagy,
and hybrid metabolic states.
This is exactly what one would expect from:
an evolving metabolic systems disease.
The discovery of FAO dependence does not refute metabolic theory.
Instead it reveals that:
cancer metabolism is more sophisticated and adaptable than originally appreciated.
Warburg was still fundamentally correct
Warburg observed:
increased glucose uptake,
aerobic glycolysis,
lactate production,
and abnormal mitochondrial behavior.
All of these remain true.
FDG-PET imaging itself depends on:
increased tumor glucose uptake.
Most tumors still demonstrate:
elevated glycolysis,
high glucose consumption,
insulin sensitivity,
and lactate production.
What modern oncology has added is that:
tumors can switch fuels under stress.
FAO often represents an adaptive escape mechanism
One of the most important insights is that:
FAO frequently emerges during therapy resistance, metastasis, dormancy, or stemness.
In many cancers:
proliferating bulk tumor cells → glycolysis
while:resistant stem-like cells → FAO/OXPHOS.
This does not negate metabolic theory.
It actually reinforces:
metabolism as the central battlefield of cancer adaptation.
Cancer stem cells are the key
Cancer stem cells (CSCs) appear particularly dependent upon:
mitochondrial respiration,
FAO,
autophagy,
and oxidative stress defenses.
This is enormously important because CSCs drive:
relapse,
metastasis,
treatment resistance,
and recurrence.
The failure of conventional oncology to eradicate CSCs is one reason why:
tumors recur despite initial shrinkage.
Again:
this supports a metabolic model.
It simply means:
CSC metabolism differs from bulk-tumor metabolism.
Glycolysis and FAO are not mutually exclusive
Many tumors use:
both simultaneously.
Different regions of the same tumor may utilize different fuels:
hypoxic core → glycolysis
invasive edge → OXPHOS/FAO
stem-cell niche → mitochondrial metabolism
rapidly proliferating cells → glycolysis
Tumors are metabolically heterogeneous ecosystems.
The real implication: single-pathway metabolic therapy is insufficient
The FAO data mainly argues against:
simplistic ketogenic absolutism,
“starve cancer with glucose restriction alone,”
or single-target metabolic interventions.
If glycolysis alone is inhibited:
tumors may shift toward FAO.
If FAO alone is inhibited:
tumors may increase glycolysis.
If mitochondria are stressed:
glycolytic escape may increase.
This is exactly why:
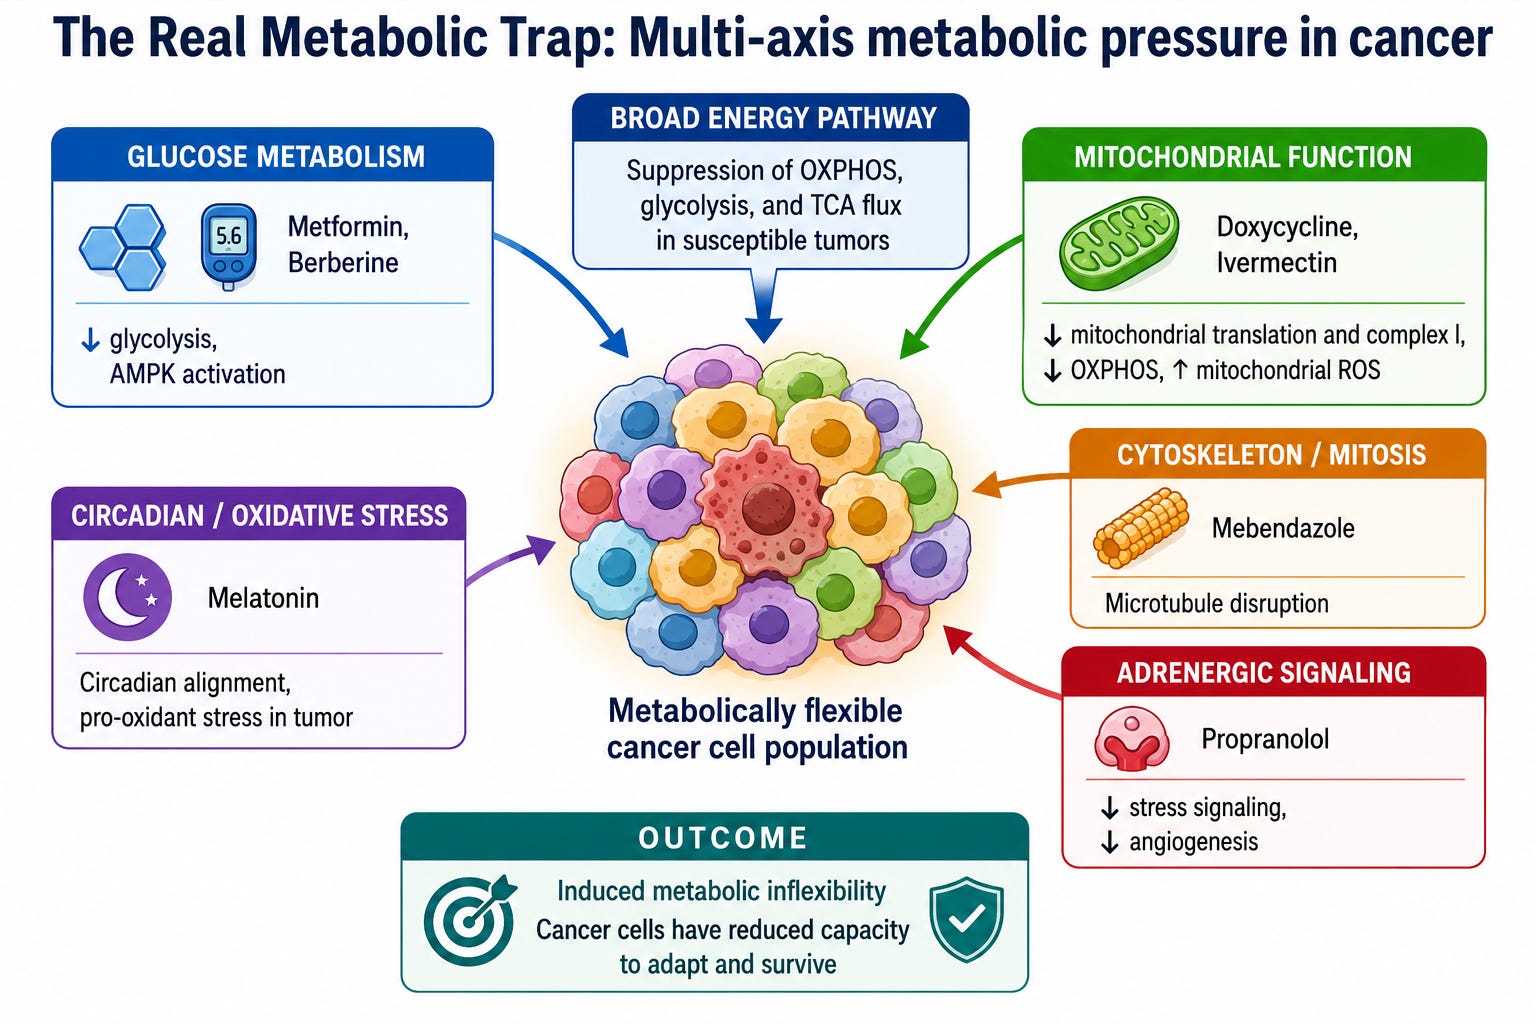
multi-axis metabolic pressure
becomes biologically logical.
The metabolic trap becomes more important—not less
The recognition of FAO dependence strongly supports:
a systems-biology metabolic approach.
The metabolic trap attempts simultaneous pressure on:
Glycolysis/insulin signaling
Mitochondrial function/OXPHOS
FAO/lipid signaling
Stemness/cytoskeletal survival
Inflammation/microenvironmental signaling
The rationale is:
prevent metabolic escape routes.
The somatic mutation theory struggles more with FAO than metabolic theory does
Interestingly, FAO dependence may actually create greater problems for:
purely mutation-centered models.
Why?
Because:
genetically distinct tumors often converge on similar metabolic phenotypes,
metastatic behavior correlates strongly with metabolic adaptation,
and stemness often reflects metabolic state more than mutation burden alone.
In many cases:
metabolic phenotype predicts behavior better than genotype.
Mitochondria remain central
Perhaps the most important point is:
FAO is fundamentally mitochondrial metabolism.
FAO occurs in mitochondria.
Thus the FAO literature actually places:
mitochondria even more centrally in cancer biology.
That is entirely compatible with:
Warburg,
Seyfried,
and broader metabolic theories.
The modern view
The modern metabolic view of cancer is not:
“cancer only eats sugar.”
It is:
cancer is a metabolically adaptive systems disease characterized by dysregulated energy sensing, mitochondrial adaptation, inflammatory signaling, and evolutionary metabolic flexibility.
That is a far more powerful and biologically accurate framework.
Bottom line
The discovery that some cancers depend heavily on:
fatty acid oxidation,
oxidative phosphorylation,
and mitochondrial metabolism
does:
NOT negate the metabolic theory of cancer.
Rather, it:
expands it,
modernizes it,
and strengthens the argument that:
metabolism—not mutations alone—is central to cancer survival and adaptation.
What FAO dependence really disproves is:
simplistic one-dimensional models of cancer metabolism.
The future likely lies not in:
“glycolysis versus FAO,”
but in understanding:
how cancer dynamically switches between metabolic states to survive.


Great article my friend. This remarkable analysis provides an exceptional framework regarding the spatial and metabolic flexibility of advanced solid masses .Recognizing that fatty acid oxidation serves as a primary adaptive escape mechanism confirms exactly why blocking a single glycolytic pathway remains entirely insufficient to halt progression permanently. Implementing simultaneous multi axis pressure is the only definitive solution to shatter these redundant mitochondrial fuel loops and ensure total safety for the host organism.
I would avoid fenbendazole. Firstly it is only approved for use in animals so we dont understand its human pharmacology (see my post on mebendazole). Second in higher doses fenbendazole is hepato-toxic.