

Hypertension is called a “silent killer” because most people feel completely fine until it has already caused a heart attack, stroke, or other life-threatening damage.
Lifestyle and metabolic interventions are foundational to the treatment of hypertension
- Paul
Introduction
Hypertension remains one of the most prevalent and consequential chronic conditions worldwide, serving as a leading driver of cardiovascular disease, stroke, chronic kidney disease, and premature mortality. Despite its ubiquity, hypertension is often clinically silent, evolving over decades before manifesting overt organ damage. Understanding how hypertension is diagnosed—and more importantly, why it develops—is central to effective prevention and management.
Diagnosis of Hypertension
The diagnosis of hypertension is deceptively simple but frequently misapplied in clinical practice. It is defined by persistently elevated arterial blood pressure, not by a single abnormal reading.
Blood Pressure Thresholds
Most contemporary guidelines (e.g., American College of Cardiology / American Heart Association) define hypertension as:
Normal: <120/80 mmHg
Elevated: 120–129/<80 mmHg
Stage 1 hypertension: 130–139 or 80–89 mmHg
Stage 2 hypertension: ≥140 or ≥90 mmHg
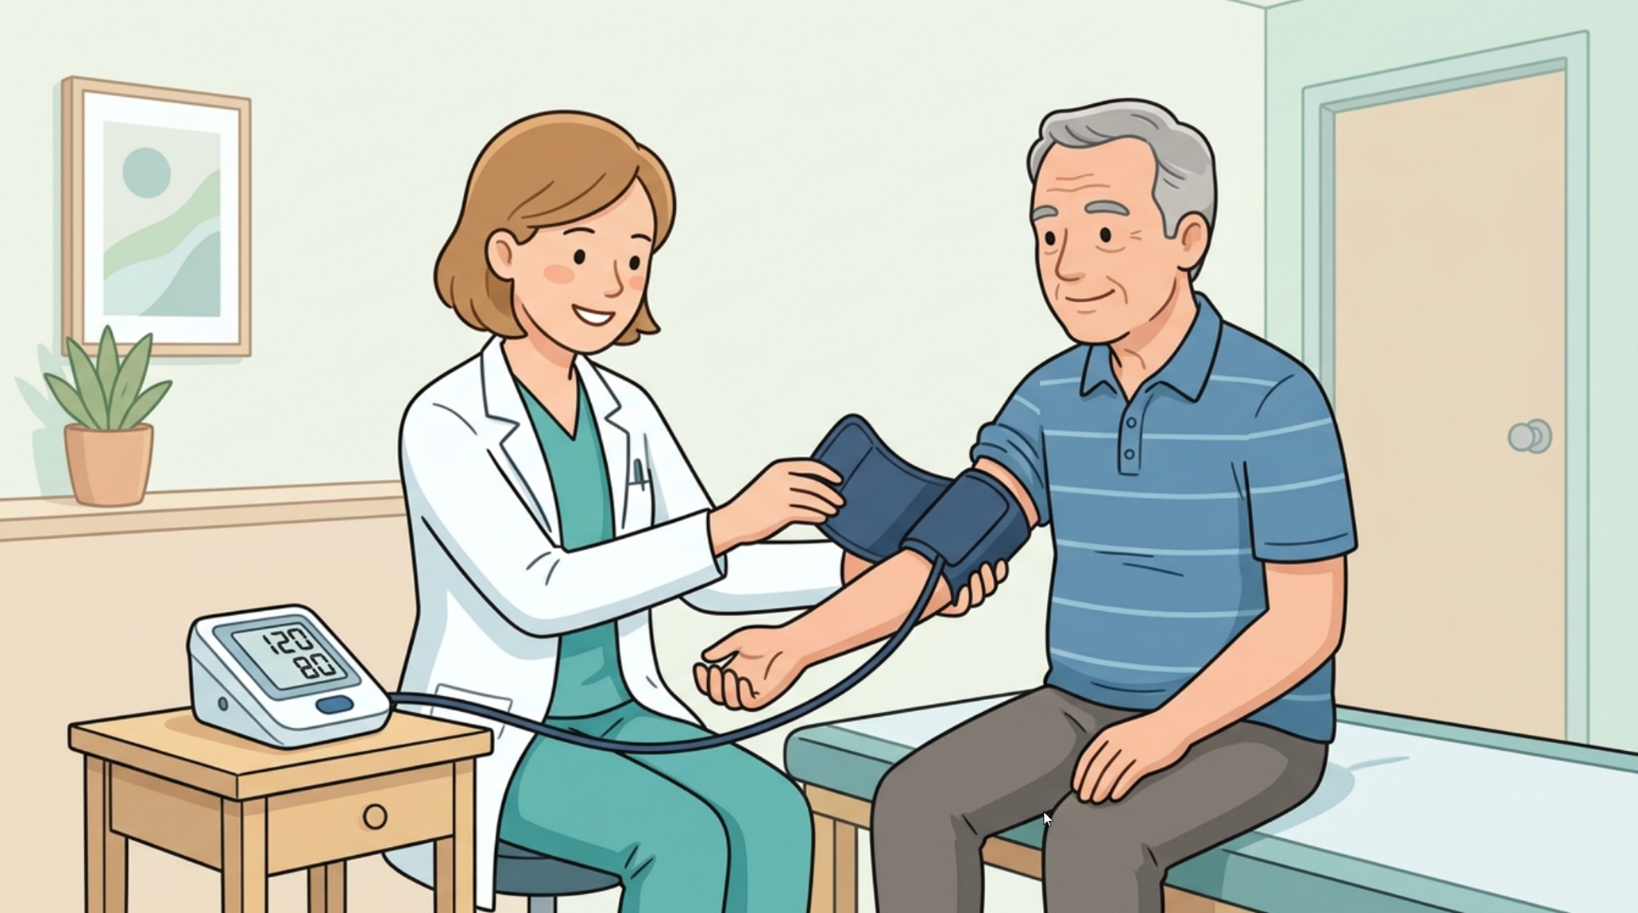
However, diagnosis requires multiple readings on separate occasions, ideally using standardized measurement techniques.
Patients with hypertension should buy a home blood pressure meter (not expensive) to better track the trends in blood pressure.
Figure 1. Measurement of Blood Pressure
Pathophysiology: A Systems Disorder
Hypertension is not a single disease but a complex systems disorder involving the interaction of vascular, renal, neural, endocrine, and metabolic pathways. Approximately 90–95% of cases are classified as PRIMARY HYPERTENSION, meaning no single identifiable cause. However, this term obscures a convergence of multiple biological drivers, most notably:
Metabolic Factors
There is a strong association between hypertension and:
Insulin resistance
Obesity
Metabolic syndrome
Hyperinsulinemia promotes sodium retention and sympathetic activation, linking metabolic disease with elevated blood pressure.
Lifestyle and Environmental Factors
Modern lifestyle is a dominant driver of hypertension:
High sodium intake
Low potassium intake
Physical inactivity
Chronic stress
Excess alcohol consumption
These factors interact with genetic susceptibility to accelerate disease onset
Secondary Hypertension
Approximately 5–10% of patients have a secondary, potentially reversible cause. Recognition is critical, particularly in:
Resistant hypertension
Early-onset (<30 years)
Sudden worsening of previously stable blood pressure
Common Causes
Renal Causes
Chronic kidney disease
Renal artery stenosis
Endocrine Causes
Primary aldosteronism
Pheochromocytoma
Cushing syndrome
Thyroid disorders
Secondary hypertension often reflects specific pathophysiologic mechanisms (e.g., aldosterone excess → sodium retention and hypokalemia).
A Unifying Perspective
Rather than viewing hypertension as a binary diagnosis, it is more accurately understood as a continuum of dysregulated physiology. Most patients exhibit overlapping contributions from:
Renal dysfunction
Neurohormonal activation
Vascular remodeling
Metabolic disturbance
This integrative perspective helps explain why single-agent therapies are often insufficient, and why lifestyle and metabolic interventions are foundational.
Hypertension is a silent, multifactorial disorder rooted in the interplay between genetic predisposition and environmental exposure. Accurate diagnosis requires careful measurement and confirmation, while understanding its causes demands a systems-level view of cardiovascular regulation. Recognizing hypertension not as an isolated abnormality but as a manifestation of broader physiological dysregulation is essential for developing more effective, individualized treatment strategies.
The Disease That Doesn’t Hurt—Until It Kills
Rethinking the “Silent Killer”
There is a disease that quietly reshapes your arteries, thickens your heart, scars your kidneys, and injures your brain—year after year, without causing pain.
No warning.
No symptoms.
No urgency.
Until one day, it declares itself—
with a stroke, a heart attack, or the slow unraveling of memory and function.
We call it hypertension.
But calling it a “silent killer” doesn’t go far enough.
Because hypertension is not silent.
It is quietly destructive.
The Illusion of Harmlessness
One of the most dangerous misconceptions in medicine is that elevated blood pressure is merely a number—a risk factor to be “managed.”
It is not.
Hypertension is an active, progressive disease of the vascular system, and its complications are not incidental—they are inevitable when the condition is ignored or inadequately treated.
Every elevated reading reflects mechanical stress on the arterial wall, triggering a cascade of biological injury:
Endothelial dysfunction
Inflammation
Oxidative stress
Structural remodeling
This is not benign physiology.
It is chronic vascular injury in real time.
Cardiovascular Complications
The heart is one of the earliest and most significantly affected organs.
Left Ventricular Hypertrophy (LVH)
Persistent pressure overload leads to:
Myocardial thickening
Reduced ventricular compliance
Diastolic dysfunction
LVH is a major predictor of mortality and arrhythmias.
Coronary Artery Disease (CAD)
Hypertension accelerates atherosclerosis, increasing the risk of:
Stable angina
Acute coronary syndromes
Myocardial infarction
Heart Failure
Over time, hypertensive heart disease progresses to:
Heart failure with preserved ejection fraction (HFpEF) (most common)
Later, systolic dysfunction (HFrEF)
Cerebrovascular Complications
Hypertension is the most important modifiable risk factor for stroke.
Ischemic Stroke
Due to accelerated atherosclerosis and small vessel disease
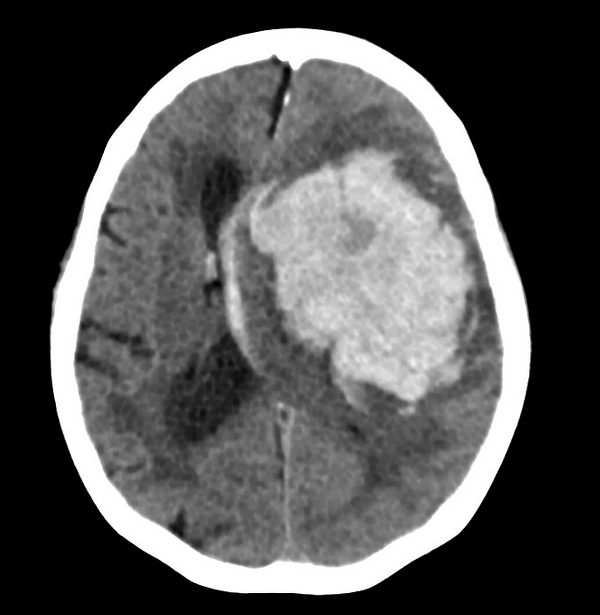
Hemorrhagic Stroke
Resulting from rupture of weakened intracerebral vessels (see figure 2)
Chronic Small Vessel Disease
Leads to:
Vascular dementia
Cognitive decline
White matter changes (leukoaraiosis)
Renal Complications
The kidneys are both a cause and a victim of hypertension.
Hypertensive Nephrosclerosis
Chronic pressure leads to:
Glomerular injury
Progressive fibrosis
Declining glomerular filtration rate (GFR)
Chronic Kidney Disease (CKD)
Hypertension is a leading cause of end-stage renal disease
Creates a vicious cycle, as kidney dysfunction further elevates blood pressure
Vascular Complications
Hypertension induces widespread vascular injury.
Atherosclerosis
Accelerated plaque formation in large arteries
Peripheral Artery Disease (PAD)
Reduced blood flow to limbs
Claudication and impaired wound healing
Aortic Aneurysm and Dissection
Chronic wall stress weakens the aorta
Can result in catastrophic rupture or dissection
Ophthalmologic Complications
The retinal circulation provides a window into systemic vascular damage.
Hypertensive Retinopathy
Arteriolar narrowing
Arteriovenous nicking
Hemorrhages and exudates
In severe cases: papilledema
These findings correlate with overall cardiovascular risk.
A Unifying Mechanism
Across all organ systems, the complications of hypertension reflect three core processes:
Endothelial dysfunction
Vascular remodeling and stiffness
Microvascular injury and ischemia
Over time, these processes culminate in irreversible organ damage.
Sumary
Hypertension is not merely a number—it is a chronic, systemic disease that progressively damages nearly every major organ system. Its complications—cardiovascular, cerebrovascular, renal, vascular, and retinal—are the true drivers of morbidity and mortality. Early recognition and sustained control of blood pressure remain among the most powerful interventions in all of medicine.
Figure 2. Intracerebral bleed; a devastating complication of hypertension
How to Reverse the Process
Hypertension Is Not Inevitable
The first part of this Post was about what hypertension does, this is about something far more important:
What can be done about it.
Because the most dangerous myth in medicine is not that hypertension is silent.
It is that it is inevitable.
That it is simply a function of aging.
That once it appears, it can only be “managed,” not fundamentally changed.
This is not true.
In many patients, hypertension is not a fixed disease—it is a dynamic, reversible physiological state, driven by modifiable inputs.
The Metabolic Root
At the center of modern hypertension lies a familiar axis; it’s a METABOLIC DISEASE:
Insulin resistance
Hyperinsulinemia
Visceral adiposity
Insulin is not just a metabolic hormone.
It is also a vascular hormone.
Chronically elevated insulin levels:
Promote renal sodium retention
Activate the sympathetic nervous system
Impair endothelial function
This is why hypertension so often travels with:
Central obesity
Type 2 diabetes
Metabolic syndrome
Address the metabolism—and blood pressure often follows.
Food as a Hemodynamic Intervention
Dietary change is one of the most powerful tools available—and one of the most underutilized.
Reduce Sodium—But Understand the Context
Excess sodium contributes to volume expansion, particularly in salt-sensitive individuals.
But sodium restriction alone is rarely sufficient.
The modern diet is not just high in sodium—it is:
Low in potassium
High in ultra-processed foods
Metabolically disruptive
Increase Potassium Intake
Potassium has direct blood pressure–lowering effects:
Promotes natriuresis
Relaxes vascular smooth muscle
Improves endothelial function
Whole foods—vegetables, fruits, legumes—restore this balance.
Correct the Metabolic Environment
Dietary patterns that improve insulin sensitivity are consistently effective:
Whole-food, minimally processed diets
Reduction in refined carbohydrates
Time-restricted eating or intermittent fasting (in appropriate patients)
This is not about a specific “diet.”
It is about restoring metabolic coherence.
Weight Loss: A Hemodynamic Reset
Even modest weight reduction has profound effects:
Decreases sympathetic activity
Improves insulin sensitivity
Reduces vascular resistance
In many patients, a 5–10% reduction in body weight leads to clinically meaningful drops in blood pressure.
More importantly, it begins to reverse the underlying biology.
The Nervous System: An Overlooked Driver
Chronic stress is not benign.
It is a persistent sympathetic stimulus.
Elevated catecholamines lead to:
Vasoconstriction
Increased heart rate
Sustained blood pressure elevation
Interventions that reduce sympathetic tone are not ancillary—they are central:
Sleep optimization
Mindfulness or relaxation practices
Regular physical activity
The autonomic nervous system is not separate from cardiovascular health.
It is integral to it.
Exercise: Medicine for the Vasculature
Regular physical activity produces measurable physiologic changes:
Improved endothelial function
Reduced arterial stiffness
Lower resting sympathetic tone
Both aerobic and resistance training are effective.
The key is consistency, not intensity.
Sleep and Circadian Biology
Hypertension is tightly linked to sleep quality and circadian rhythm.
Conditions such as obstructive sleep apnea are common and underdiagnosed contributors.
Poor sleep leads to:
Increased sympathetic activity
Hormonal dysregulation
Impaired vascular repair
Restoring sleep is not optional.
It is therapeutic.
Targeted Pharmacology: When Needed
Lifestyle interventions form the foundation.
But medications are often necessary—and lifesaving.
When used appropriately, they:
Reduce vascular resistance
Modulate neurohormonal pathways
Protect end organs
The key is not to view pharmacologic therapy as failure, but as support while underlying drivers are addressed.
Most guidelines recommend starting with one of three primary classes:
1. Renin–Angiotensin–Aldosterone System (RAAS) Inhibitors
ACE Inhibitors:
Examples:
Lisinopril
Enalapril
Angiotensin II Receptor Blockers (ARBs)
Examples:
Losartan
Valsartan
2. Calcium Channel Blockers (CCBs)
Examples:
Amlodipine
3. Diuretics
Thiazide Diuretics
Examples:
Hydrochlorothiazide
Chlorthalidone
Combination therapy is often required to achieve adequate blood pressure control.
ACEi/ARB + CCB (effective in Caucasians)
ACEi/ARB + diuretic (effective in African Americans)
Beta-blockers should not be used to treat hypertension. Although they reduce blood pressure, they do not reduce the risk of end-organ damage. ACE, ARBS, amlodipine and diuretics are they only drugs that have been proven to lower blood pressure AND reduce the risk of end-organ damage. It serves no (ZERO) purpose to use an anti-hypertensive drug that does not reduce the risk of end-organ damage.
Nutraceuticals
Several nutraceuticals have clinically detectable blood pressure–lowering effects and are being used as adjuncts to lifestyle change and standard drugs.
Key nutraceuticals with BP‑lowering data
Aged garlic extract – Multiple trials and reviews report modest systolic and diastolic BP reductions, often in the 5–10 mmHg range in hypertensive patients.
Fish oil (omega‑3s) – EPA/DHA (typically 2–4 g/day) can slightly lower BP and improve cardiometabolic risk markers, especially in higher‑risk patients.
Cocoa flavanols – Cocoa/dark chocolate rich in flavanols have shown modest BP reductions, likely via improved nitric oxide signaling.
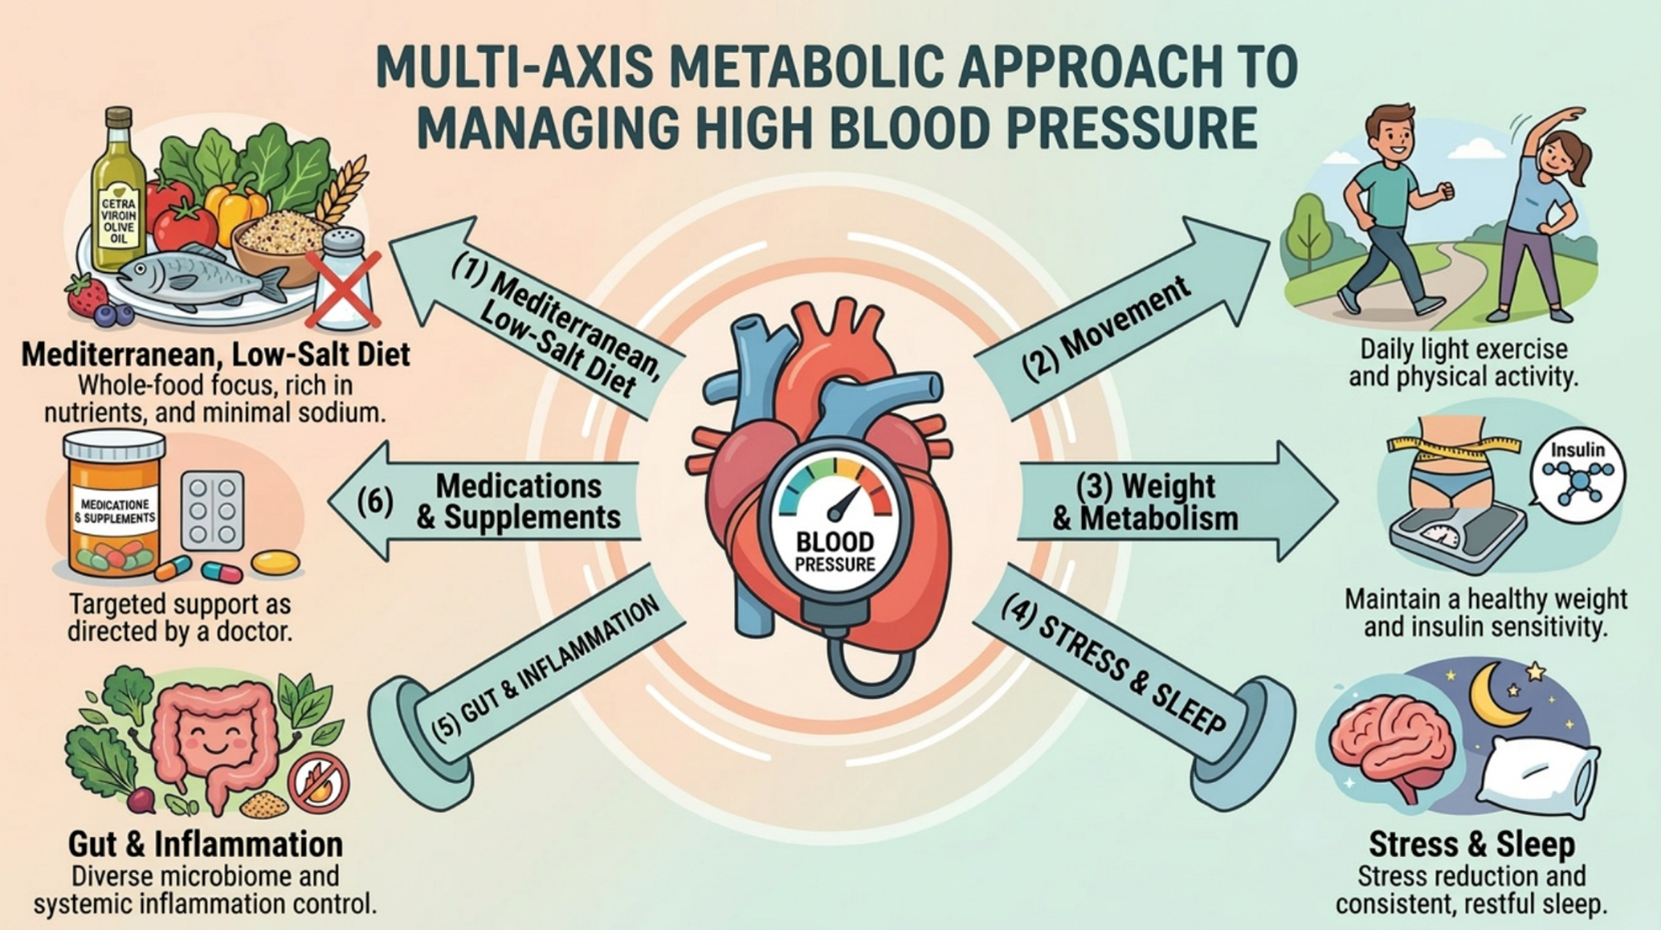
Figure 3. Multi-axis approach to treatment of hypertension

Medical Disclaimer: The discussion of repurposed medications and nutraceuticals in this article is intended to review the scientific literature and does not constitute a recommendation for self-treatment. Decisions regarding the use of off-label therapies should be made in consultation with a qualified healthcare professional familiar with the patient’s medical history and current treatment plan. Please see the full Medical Disclaimer on the introductory page to Marik’s Cancer & Metabolic Healing Playbook.
I recently saw a 19 year old morbid obese female with elevated blood pressure, who needed a refill on her birth control pills . I refused , and ordered blood to rule out cushings triad , metabolic syndrome, thyroid ,, ect …. Her mother blasted me to the office staff and social media . Yepppers …. She has cushings . You can’t fix stupid
My husband's BP dropped within weeks of starting a low carb lifestyle, allowing him to drop one of his BP meds. Probably could have dropped the B-blocker too, but his body had adapted and it was hard to wean off without developing palpitations.
Maddeningly, his cardiologists refused to recognize white-coat HTN and kept his HTN diagnosis on his chart for years, despite his bringing in his home logs of quite normal BPs into the office. They were idiots.