

For decades, liver disease was viewed through a narrow lens—alcohol, viruses, toxins. If a patient did not drink excessively and tested negative for hepatitis, their liver was assumed to be safe.
That assumption is now dangerously outdated.
Nonalcoholic steatohepatitis (NASH)—the progressive and inflammatory form of fatty liver disease—is not rare, not benign, and not incidental. It is the hepatic manifestation of a systemic metabolic crisis. And like coronary artery disease, type 2 diabetes, and hypertension, it is fundamentally driven by insulin resistance and metabolic dysfunction, not by isolated organ pathology.
NASH is not a liver disease.
It is a metabolic disease that happens to involve the liver.
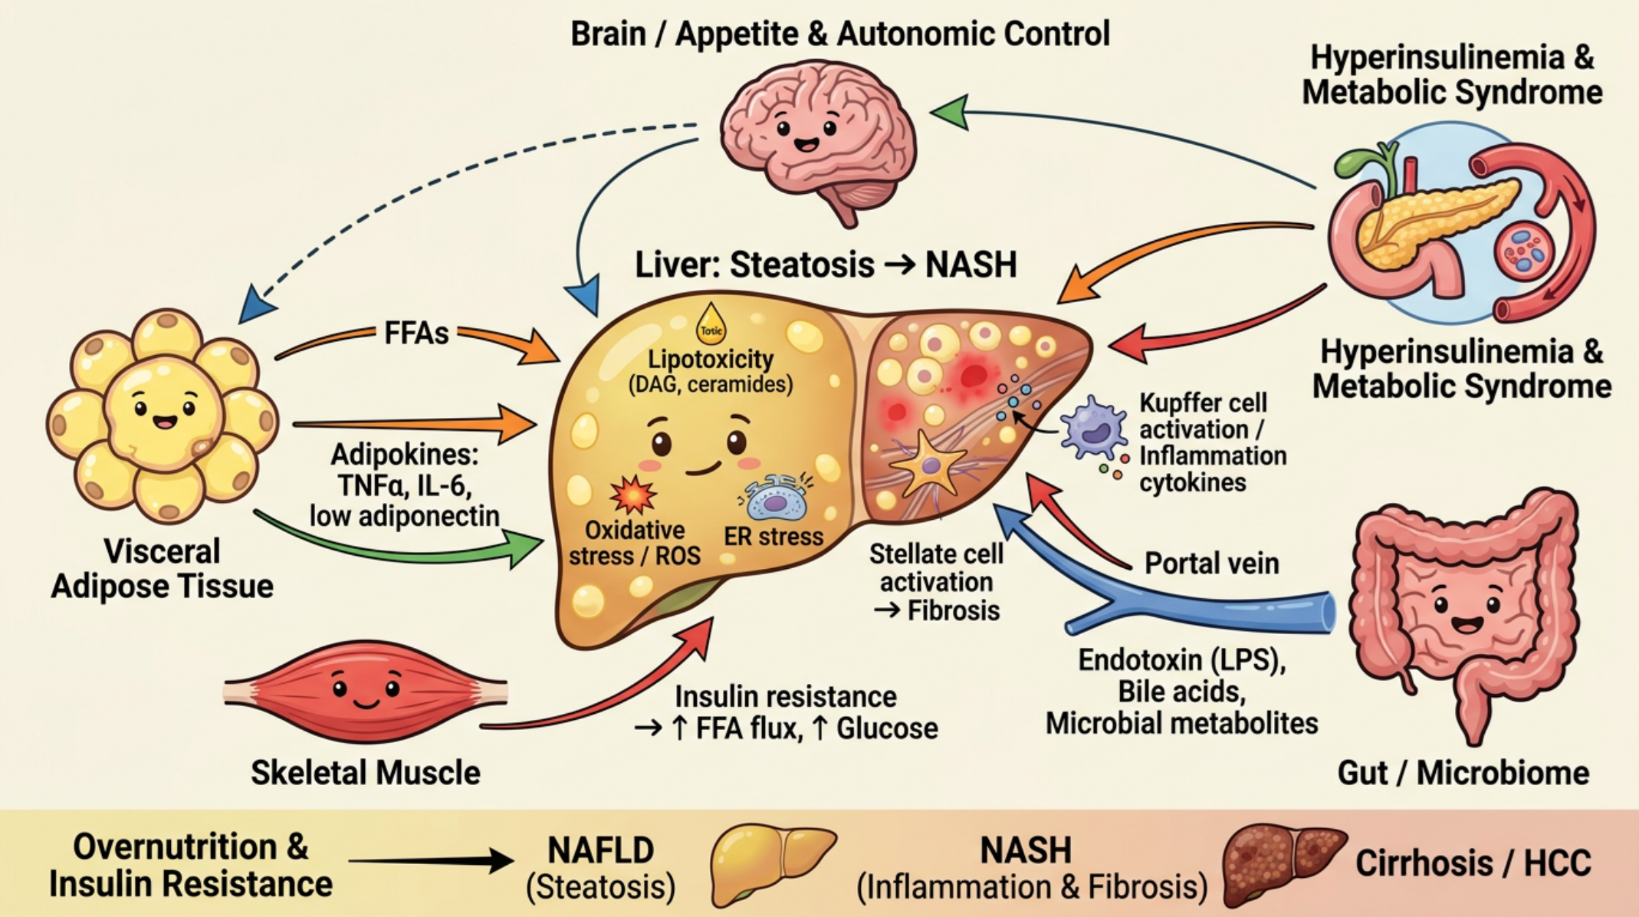
Figure 1. Metabolic Pathways in Nash
The Spectrum: From NAFLD to NASH
NASH exists along a continuum:
NAFLD (Nonalcoholic Fatty Liver Disease) → simple fat accumulation
NASH (Nonalcoholic Steatohepatitis) → fat + inflammation + hepatocellular injury
Fibrosis → Cirrhosis → Hepatocellular carcinoma
This progression mirrors other metabolic diseases—silent early stages followed by irreversible damage if the root cause is not addressed.
What drives this progression is not fat alone, but metabolic dysfunction interacting with inflammation, oxidative stress, and mitochondrial failure.
The Central Driver: Insulin Resistance
At the core of NASH lies a single unifying abnormality:
Insulin resistance
This is the same pathophysiologic engine that drives:
Type 2 diabetes
Metabolic syndrome
Coronary artery disease
Obesity
And critically:
NASH
Mechanistically:
Hyperinsulinemia increases hepatic fat production
Insulin stimulates de novo lipogenesis
Excess glucose is converted to fat in the liver
Adipose tissue becomes dysfunctional
Increased lipolysis → free fatty acids flood the liver
Hepatic fat accumulates
Triglyceride deposition is initially protective
Lipotoxicity develops
Toxic lipid intermediates (ceramides, DAGs) trigger inflammation
This is not passive fat storage.
It is active metabolic injury.
Mitochondrial Dysfunction: The Second Hit
The transition from benign steatosis to NASH requires a second layer of injury:
Mitochondrial dysfunction
The liver becomes overwhelmed by excess substrate:
Free fatty acids
Glucose
Fructose
Mitochondria attempt to oxidize this overload, resulting in:
Excess reactive oxygen species (ROS)
Impaired ATP production
Cellular stress signaling
This leads to:
Hepatocyte injury
Inflammatory cytokine release
Activation of stellate cells → fibrosis
In many respects, NASH mirrors the Warburg-like metabolic dysfunction seen in cancer:
Inefficient energy handling
Oxidative stress
Altered substrate utilization
Fructose, Seed Oils, and the Modern Diet
NASH is not a disease of bad luck—it is a disease of environment.
Fructose: The Hepatic Toxin
Unlike glucose, fructose is metabolized almost exclusively in the liver.
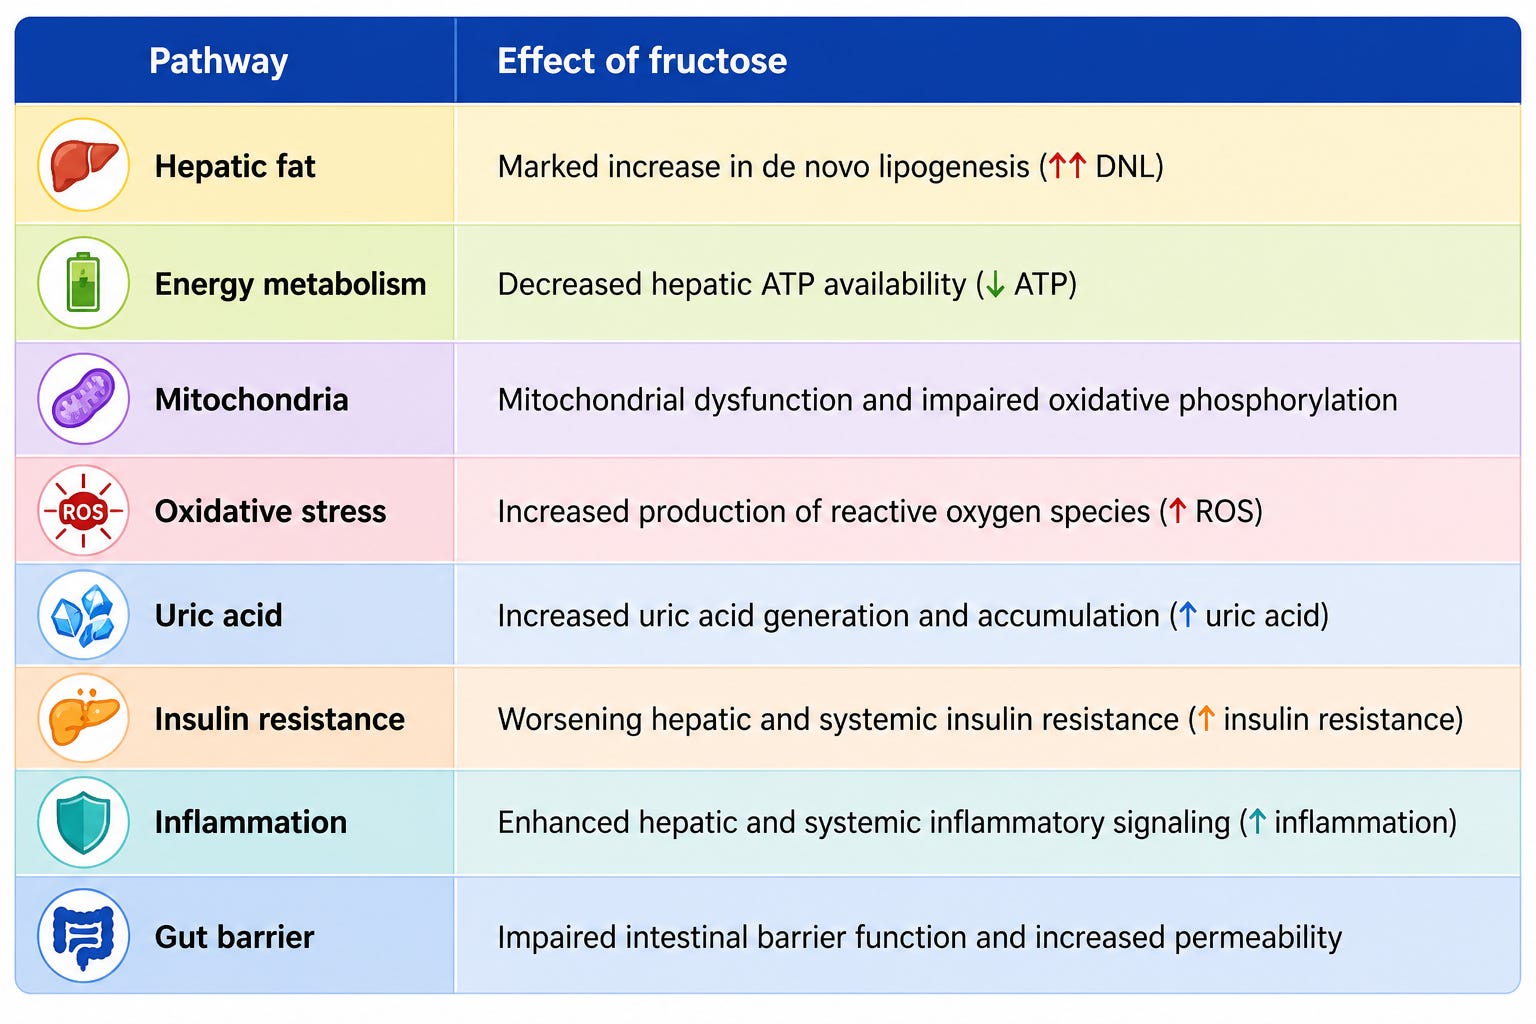
Drives de novo lipogenesis
Depletes ATP
Generates uric acid → oxidative stress
High intake (sugar, HFCS) directly accelerates NASH.
Omega-6 Seed Oils and Lipotoxicity
Modern diets are dominated by omega-6 polyunsaturated fats:
Highly prone to lipid peroxidation
Generate oxidative stress and inflammatory mediators
These oils amplify:
Hepatic inflammation
Mitochondrial injury
Disease progression
Ultra-Processed Foods
The convergence of:
Refined carbohydrates
Industrial fats
Additives
Creates the perfect metabolic storm:
hyperinsulinemia + oxidative stress + inflammation
Inflammation: The Turning Point
Fat alone does not define NASH.
Inflammation does.
Triggers include:
Oxidative stress
Gut-derived endotoxin (LPS)
Adipokine imbalance
This results in:
TNF-α, IL-6 activation
Immune cell infiltration
Hepatocyte ballooning
At this stage, the disease becomes self-perpetuating.
The Gut–Liver Axis
An often underappreciated contributor:
Gut dysfunction
Increased intestinal permeability (“leaky gut”)
Translocation of endotoxin
This drives:
Hepatic inflammation
Immune activation
Fibrosis progression
NASH is therefore not just liver + metabolism—
It is a systems disease involving the gut, adipose tissue, and immune system.
Fibrosis: The Point of No Return
Chronic injury activates hepatic stellate cells:
Collagen deposition
Extracellular matrix expansion
Fibrosis is the strongest predictor of:
Mortality
Liver-related complications
Once advanced fibrosis develops, reversal becomes difficult.
NASH and Cardiovascular Disease
Paradoxically, most patients with NASH do not die from liver failure.
They die from:
Heart attacks
Strokes
This reinforces the central thesis:
NASH is a manifestation of systemic metabolic disease.
Reframing the Disease
The conventional model asks:
“What drug treats NASH?”
The correct question is:
“What caused the metabolic dysfunction driving NASH?”
Because without addressing the root cause, pharmacologic interventions are largely cosmetic.
Therapeutic Implications: Treat the Metabolic Disease
1. Dietary Intervention (Foundation)
The most powerful intervention:
Low glycemic, whole-food diet
Elimination of:
Refined carbohydrates
Fructose
Ultra-processed foods
Reduction of omega-6 seed oils
This directly targets:
Insulin resistance
Hepatic fat accumulation
2. Weight Loss (if applicable)
Even modest weight loss (5–10%) can:
Reduce liver fat
Improve inflammation
Reverse early fibrosis
3. Metabolic Pharmacology
Agents targeting metabolic dysfunction:
Metformin → improves insulin sensitivity
Berberine → AMPK activation
GLP-1 agonists → weight loss, insulin regulation
These are not “liver drugs.”
They are metabolic therapies.
4. Mitochondrial Support
Exercise
Intermittent fasting
Nutraceuticals:
Omega-3 fatty acids
Polyphenols (curcumin, resveratrol)
5. Anti-inflammatory Strategies
Vitamin D optimization
Gut health restoration
Reduction of oxidative stress
A New Paradigm
NASH represents a failure of the prevailing medical model.
It is not:
A cholesterol disease
A liver-specific disease
A condition requiring a single “targeted drug”
It is:
A systems-level metabolic disorder
Driven by:
Insulin resistance
Mitochondrial dysfunction
Chronic inflammation
Dietary toxicity
Conclusion: The Disease We Created
NASH is not a mystery.
It is the predictable consequence of:
Industrialized food
Sedentary living
Chronic metabolic stress
And like other metabolic diseases, it is largely:
Preventable
Reversible (early)
Understandable through first principles biology
The tragedy is not that we don’t understand NASH.
The tragedy is that we continue to treat it as something it is not.
The link between FRUCTOSE and NASH
The link between fructose and NASH is not incidental—it is central, mechanistic, and causal. Fructose is uniquely positioned among nutrients to drive hepatic fat accumulation, mitochondrial dysfunction, and inflammation, the three pillars of NASH.
Fructose and NASH: The Metabolic Connection
1. Fructose Is Metabolized Almost Exclusively in the Liver
Unlike glucose, which is distributed throughout the body, fructose is handled primarily by the liver.
This matters.
Because the liver becomes the metabolic “sink” for fructose load—particularly in the modern diet where intake is high (sugar, high-fructose corn syrup, processed foods).
Key consequence:
The liver is forced to convert fructose into fat
2. Fructose Drives De Novo Lipogenesis (Fat Creation)
Fructose bypasses normal metabolic regulation and is rapidly converted into triglycerides.
Mechanism:
Fructose → enters hepatocytes → bypasses phosphofructokinase (a key regulatory step)
Uncontrolled flux into:
Acetyl-CoA
→ fatty acid synthesis
→ triglyceride accumulation
Result:
Hepatic steatosis (fatty liver)
This is the first step in the NASH cascade.
3. Fructose Depletes Cellular Energy (ATP)
Fructose metabolism is energy-intensive and inefficient.
Rapid phosphorylation of fructose → ATP depletion
Leads to:
Increased AMP
Activation of uric acid production
Why this matters:
Low ATP = cellular stress
Uric acid = mitochondrial dysfunction + oxidative stress
4. Uric Acid and Oxidative Stress
Fructose uniquely increases intracellular uric acid, which:
Inhibits mitochondrial function
Increases reactive oxygen species (ROS)
Promotes inflammation
This is a critical transition point:
From:
Benign fat accumulation
To:
Inflammatory liver injury (NASH)
5. Fructose Promotes Insulin Resistance
Chronic fructose intake contributes to:
Hepatic insulin resistance
Hyperinsulinemia
Which further drives:
More fat production
Reduced fat oxidation
Vicious metabolic cycle
6. Lipotoxicity: The Real Damage
Not all fat is harmful—but fructose promotes the formation of toxic lipid intermediates:
Diacylglycerols (DAGs)
Ceramides
These molecules:
Disrupt insulin signaling
Trigger inflammation
Damage hepatocytes
This is lipotoxicity, the hallmark of NASH.
7. Fructose and the Gut–Liver Axis
Fructose also affects the intestine:
Increases gut permeability
Promotes endotoxin (LPS) translocation
This leads to:
Activation of liver immune cells
Amplified inflammation
8. Fructose Does Not Trigger Satiety
Unlike glucose:
Fructose does not stimulate insulin or leptin effectively
Does not suppress ghrelin
Result:
Increased caloric intake
Chronic overnutrition
9. Clinical and Epidemiologic Evidence
High fructose intake correlates strongly with:
NAFLD prevalence
NASH severity
Sugary beverages are a major driver
Reduction in fructose intake:
Rapidly reduces liver fat (within weeks)
10. Fructose vs Whole Fruit
Important distinction:
Whole fruit:
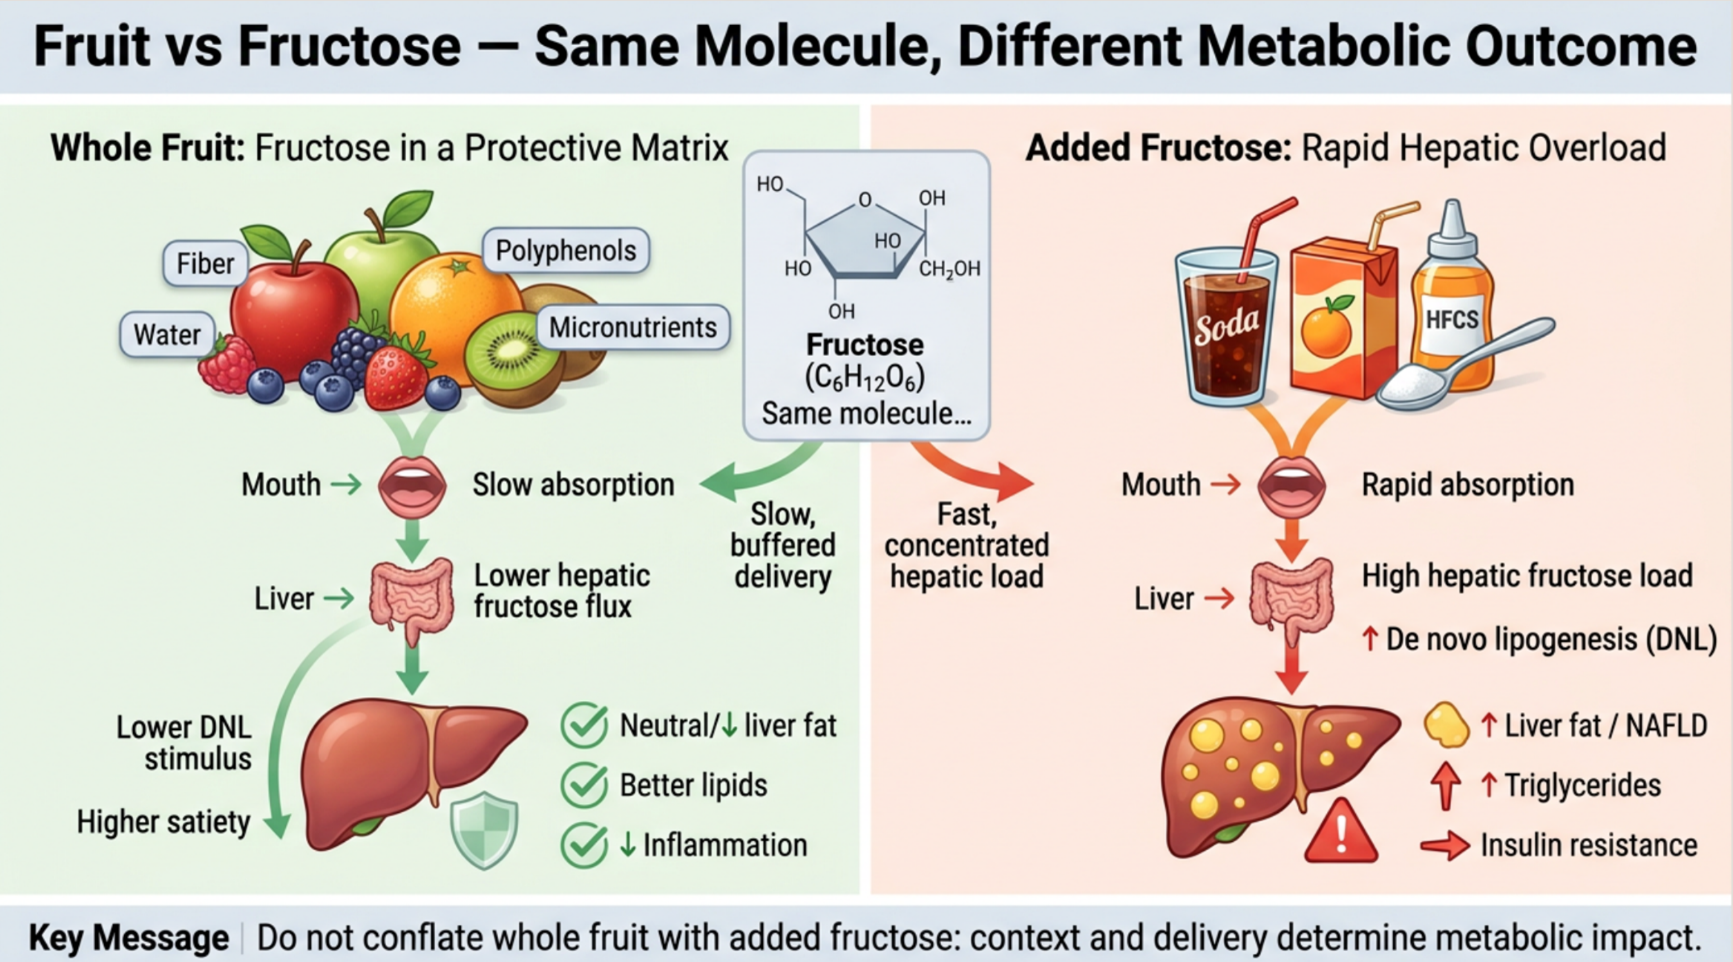
Contains fiber → slows absorption
Lower total fructose load
Associated with metabolic health
Processed fructose (HFCS, sugar):
Rapid delivery to liver
High dose
No buffering
The Big Picture
Fructose hits every major axis of NASH pathophysiology
Conclusion
Fructose is not just “empty calories.”
It is a metabolic toxin when consumed in excess, uniquely capable of:
Driving fat into the liver
Disrupting mitochondrial function
Triggering inflammation
In doing so, it transforms simple fatty liver into:
NASH
Does Eating Excess Fruit Cause NASH?
This is a nuanced question—and the answer is not what most people expect.
Short answer:
Whole fruit, even in relatively high amounts, rarely causes NASH
Excess fructose—especially from processed sources—clearly contributes to NASH
The distinction is critical.
The Core Issue: Fructose vs Fruit
Fructose is the metabolic driver we discussed. But fruit is not fructose in isolation.
Whole fruit contains:
Fiber
Water
Polyphenols (antioxidants)
Micronutrients
These fundamentally change how fructose is handled.
1. Dose Matters—And Fruit Is Self-Limiting
To reach harmful fructose levels from whole fruit alone is difficult.
For example:
A typical apple: ~8–10 g fructose
A can of soda: ~20–25 g fructose (rapidly absorbed)
Eating 5–6 pieces of fruit:
Slower absorption
Earlier satiety
Lower glycemic and metabolic impact
Drinking the equivalent in juice or soda:
Rapid hepatic overload
No satiety
2. Fiber Changes Everything
Fiber in fruit:
Slows intestinal absorption
Reduces peak fructose delivery to the liver
Improves insulin sensitivity
Supports gut microbiome
Result:
The liver is not overwhelmed in the same way as with processed fructose.
3. Polyphenols Counteract Damage
Fruit contains bioactive compounds:
Flavonoids
Vitamin C
Antioxidants
These:
Reduce oxidative stress
Improve mitochondrial function
Blunt inflammation
This directly opposes the mechanisms driving NASH.
4. Epidemiologic Evidence
Consistently shows:
Whole fruit intake is associated with:
↓ insulin resistance
↓ metabolic syndrome
↓ fatty liver risk
Sugary beverages are associated with:
↑ NAFLD/NASH
↑ visceral adiposity
These are not equivalent exposures.
5. When Fruit Can Become a Problem
There are scenarios where fruit contributes to metabolic dysfunction:
A. Very high intake (extreme consumption)
Large quantities (e.g., fruit-only diets, excessive smoothies/juicing)
B. Fruit juice (critical distinction)
Removes fiber
Concentrates fructose
Rapid delivery to liver
C. Pre-existing metabolic disease
Severe insulin resistance
Established NAFLD/NASH
In these patients:
Even moderate fructose loads may worsen disease
Bottom Line
Whole fruit:
Generally protective or neutral
Safe in moderate amounts
Often beneficial
Fruit juice / high-fructose foods:
Strongly associated with NASH
Should be minimized or eliminated
Figure 2. Fructose vs. Fructose

As an ob/gyn doc I have wrestled with this my whole career. The pediatricians need to intervene early . By the time I see them for menstrual irregularities or secondary amenorrhea ;behavioral and dietary changes that need to change , are difficult to overcome. If they get pregnant , PIH / preeclampsia and / or gestational diabetes rears its ugly head. As older adults, this leads into your discussion for today . Exhausting. 😢
Thank you Dr. Marik for all you do. I love your writings . . . easy to read, to the point, well documented, and always relevant. I never get lost in the weeds!