

Metabolic therapy should begin alongside standard oncologic treatment, starting with therapeutic nutrition. This is not optional—it is essential. This includes measures to prevent metastases during biopsy and surgery (see upcoming post).
Figure 1.
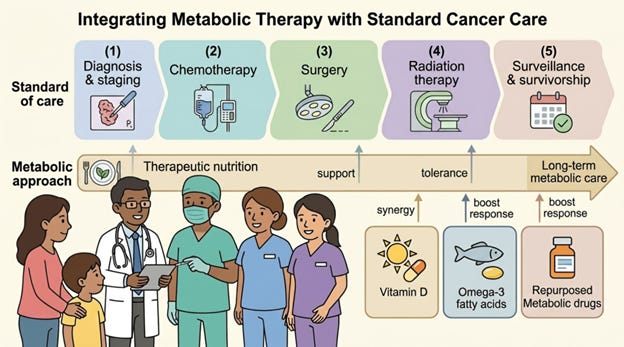
The Missing Layer in Cancer Care: Why Metabolic Therapy Can No Longer Be Ignored
For more than half a century, modern oncology has been built on a single dominant idea: cancer is fundamentally a genetic disease. Mutations accumulate, signaling pathways become dysregulated, and the solution—naturally—has been to target those mutations with increasingly sophisticated drugs. This paradigm has driven enormous scientific progress. Yet despite billions of dollars in research and thousands of new therapies, the outcome for many patients remains sobering: modest gains in survival, frequent relapse, and a growing burden of treatment-related toxicity.
There is a growing recognition—quiet but persistent—that something fundamental is missing from this model.
That missing piece is metabolism.
Metabolic Therapy should be initiated at the initiation of traditional oncological treatment starting with dietary changes. … this is not optional this is essential.
Cancer as a Metabolic Disease
Nearly a century ago, Otto Warburg made a simple but profound observation: cancer cells generate energy differently from normal cells. Even in the presence of oxygen, they preferentially rely on glycolysis rather than mitochondrial oxidative phosphorylation—a phenomenon now known as the Warburg effect.
This is not a trivial biochemical curiosity. It reflects a deeper reality: cancer cells are metabolically reprogrammed to support rapid growth, resist apoptosis, and adapt to hostile environments. They are not just genetically abnormal—they are metabolically distinct.
More recent work by researchers such as Thomas Seyfried has expanded this concept, proposing that mitochondrial dysfunction and metabolic dysregulation may be the primary drivers of cancer, with genetic mutations acting downstream rather than upstream.
Whether one fully accepts this paradigm shift or not, the implication is unavoidable: metabolism is not peripheral to cancer biology—it is central.
The Limits of a Genetics-Only Approach
The genetic model of cancer has led to targeted therapies designed to inhibit specific mutations or signaling pathways. While these drugs can produce dramatic responses in select patients, their limitations are well documented.
First, tumors are heterogeneous. A single tumor may contain multiple subclones with different genetic profiles. Targeting one mutation often leaves others untouched.
Second, cancer evolves. Under therapeutic pressure, resistant clones emerge. This is why initial responses to targeted therapies are so often followed by relapse.
Third, the clinical benefit is often modest. Many newly approved cancer drugs extend survival by only a few months, frequently at significant financial and physiological cost.
These limitations are not failures of science—they are the predictable consequence of targeting a moving genetic target without addressing the underlying metabolic engine that fuels it.
The Metabolic Advantage: Targeting What Cancer Cannot Easily Change
Unlike genetic mutations, which are diverse and constantly evolving, metabolic dependencies are more conserved. Cancer cells—regardless of their genetic makeup—share common metabolic features:
Increased glucose uptake and glycolysis
Dependence on glutamine and other substrates
Altered mitochondrial function
Increased oxidative stress
Dysregulated lipid metabolism
These are not optional features. They are essential for survival.
Targeting these vulnerabilities creates a fundamentally different therapeutic strategy: instead of chasing mutations, one disrupts the core processes that sustain cancer cells.
This is the essence of metabolic therapy.
Multi-Axis Metabolic Pressure: A Systems Approach
Cancer is not sustained by a single pathway but by an interconnected network of metabolic adaptations. This is why single-agent therapies—whether targeted drugs or metabolic interventions—are rarely sufficient.
A more effective strategy is to apply multi-axis metabolic pressure—simultaneously targeting multiple metabolic dependencies to create a hostile environment from which cancer cells cannot escape.
This approach typically involves:
Glycolytic inhibition (e.g., metformin, berberine, dietary carbohydrate restriction)
Mitochondrial targeting (e.g., doxycycline)
Cytoskeletal disruption (e.g., mebendazole)
Stress signaling modulation (e.g., propranolol)
Circadian and oxidative regulation (e.g., melatonin)
Individually, these interventions may have modest effects. Together, they create a metabolic trap—a coordinated assault on cancer cell survival.
Importantly, many of these agents are inexpensive, widely available, and have well-established safety profiles.
Why Diet Is Foundational
No discussion of metabolic therapy is complete without addressing diet. If cancer is, in part, a disease of dysregulated energy metabolism, then the patient’s metabolic environment matters profoundly.
A high-carbohydrate diet drives insulin secretion, activates the mTOR signaling pathway, and fuels glycolysis—the very processes that cancer cells depend on.
Conversely, a low-glycemic or ketogenic dietary approach reduces insulin levels, activates AMP-activated protein kinase, and shifts the metabolic landscape in a way that is hostile to cancer cells but tolerable for normal cells.
To ignore diet while prescribing metabolic therapies is to undermine the entire strategy. It is analogous to treating diabetes without addressing carbohydrate intake.
Synergy with Conventional Oncology
Metabolic therapy is not a replacement for conventional oncology—it is a necessary complement.
Chemotherapy, radiation, and immunotherapy target different aspects of cancer biology. However, their effectiveness is often limited by resistance mechanisms that are, at their core, metabolic.
By altering the metabolic environment, one can:
Enhance the sensitivity of cancer cells to chemotherapy
Reduce the emergence of resistant clones
Improve immune function and response to immunotherapy
Potentially reduce treatment-related toxicity
For example, lowering insulin and glucose levels may reduce tumor growth signals, while mitochondrial targeting can sensitize cancer stem cells—often resistant to chemotherapy.
This is not speculative. A growing body of preclinical and clinical evidence supports these synergistic effects.
The Evidence Gap—and Why It Exists
Critics often point out that metabolic therapies lack large randomized controlled trials (RCTs). This is true—but it is also misleading.
RCTs are designed to test single interventions in controlled settings. They are poorly suited to evaluating multi-agent, systems-based approaches like metabolic therapy.
Moreover, there is little financial incentive to fund large trials of inexpensive, off-patent drugs.
The absence of large RCTs does not equate to absence of evidence. There is a substantial body of mechanistic research, observational data, and smaller clinical studies supporting the use of metabolic interventions.
In many areas of medicine, such evidence would be considered sufficient to inform practice—particularly when the interventions are low-risk and potentially high-reward.
The Ethical Imperative
At its core, the question is not whether metabolic therapy is perfect or complete. It is whether it is reasonable, safe, and potentially beneficial.
If the answer is yes—and the current evidence strongly suggests that it is—then there is an ethical obligation to consider its integration into patient care.
Patients facing life-threatening illness deserve more than a narrow, single-paradigm approach. They deserve a comprehensive strategy that addresses all dimensions of the disease.
Ignoring metabolism is no longer defensible.
A Shift in Perspective
Incorporating metabolic therapy requires a shift in how oncologists think about cancer:
From a purely genetic disease to a metabolic–genetic hybrid
From single-target interventions to systems-based strategies
From reactive treatment to proactive metabolic optimization
This does not diminish the importance of conventional therapies—it enhances them.
It also aligns oncology with a broader understanding of chronic disease, where metabolism plays a central role in conditions ranging from diabetes to cardiovascular disease to neurodegeneration.
The Path Forward
The integration of metabolic therapy into oncology will not happen overnight. It requires:
Education and awareness among clinicians
Development of practical, evidence-informed protocols
Collaboration between oncologists, metabolic specialists, and researchers
Well-designed observational studies and pragmatic trials
Most importantly, it requires a willingness to question long-held assumptions and to embrace a more comprehensive view of cancer biology.
Conclusion
Cancer is not just a genetic disease. It is a metabolic disease.
To continue treating it as purely genetic is to address only part of the problem.
Metabolic therapy offers a rational, biologically grounded, and clinically practical way to target the fundamental processes that sustain cancer. It is not a fringe idea—it is a necessary evolution in cancer care.
The question is no longer whether metabolism matters.
The question is whether we are willing to act on it.

Medical Disclaimer: The discussion of repurposed medications and nutraceuticals in this article is intended to review the scientific literature and does not constitute a recommendation for self-treatment. Decisions regarding the use of off-label therapies should be made in consultation with a qualified healthcare professional familiar with the patient’s medical history and current treatment plan. Please see the full Medical Disclaimer on the introductory page to Marik’s Cancer & Metabolic Healing Playbook.
Absolutely great and timely article — as always.
This is an exciting time in medicine when we collectively begin to understand the human body is not just a collection of isolated organ systems (as most of us were taught in medical school back in the day), but an integrated organism made of tightly interconnected organ systems that influence and depend on each other. A dysfunction in one system has far reaching consequences affecting every other system in the body — what we were taught to regard as different diseases.
Metabolic medicine is the most elegant example of the tight integration of systems in our body: a singular disruption of the insulin-resistance mechanism is directly responsible for a wide array of diseases — obesity, T2DM, hypertension, abnormal lipids, renal disease, liver disease, cancer, dementia, cardiovascular disease and the list goes on.
And the reality of conventional cancer treatments many people fail to realize: most traditional cancer treatment are poisons.
This is not a hyperbole, is a factual characterization.
The mechanisms by which most antibiotics work is by targeting specific processes on bacterias, processes our human cells do not possess or operate in the similar fashion. In the case of most traditional chemotherapy agents, the mechanisms they target on cancer cells are shared by many, if not all, normal human cells in our body. The same way those drugs exert their toxic effect on cancer cells, they exert similar effects on normal cells, which explains the serious side effects associated with many of these treatments. Unfortunately until now, these drugs have been the only hope for patients suffering from these devastating diseases.
Metabolic medicine, in combination with standard treatments, as a new mechanic in cancer therapy should usher a new era, where prevention can become a reality, and treatment may evolve into a more effective, less toxic endeavor — particularly with the evolving field of immunotherapy agents that promise a more effective and targeted approach to cancer therapy.
To your point of lack of evidence do to lack of research, fortunately the metabolic disease and cancer link is evolving as a very active area in clinical research and may provide solid evidence about the mechanisms behind it. For now we can safely advise the readers to adopt dietary/exercise interventions to target metabolic disease without much reserve while waiting for science to catch up. Metabolic interventions have no major adverse reactions on the majority of patients and regardless of any potential effectiveness on cancer therapy, they will lead to a healthier life overall — so in my mind is a win-win intervention everyone can adopt today.
To the people asking where can they find doctors that apply these principles, I can say you are unlikely to for many reasons. Since this is not yet a mainstream believe in modern medicine, most will be unlikely to adopt as part of their recommended therapy for fear of potential medical liability and/or disciplinary actions from regulatory bodies. The good news is you can continue getting traditional care from your oncologist while adopting better dietary habits on your own. One does not exclude the other.
My son has been fighting stage 4 cancer for five years. Oncologist have ZERO interest in truth or health of cancer patients. They are brainwashed idiots who are financially rewarded for being who they are.