

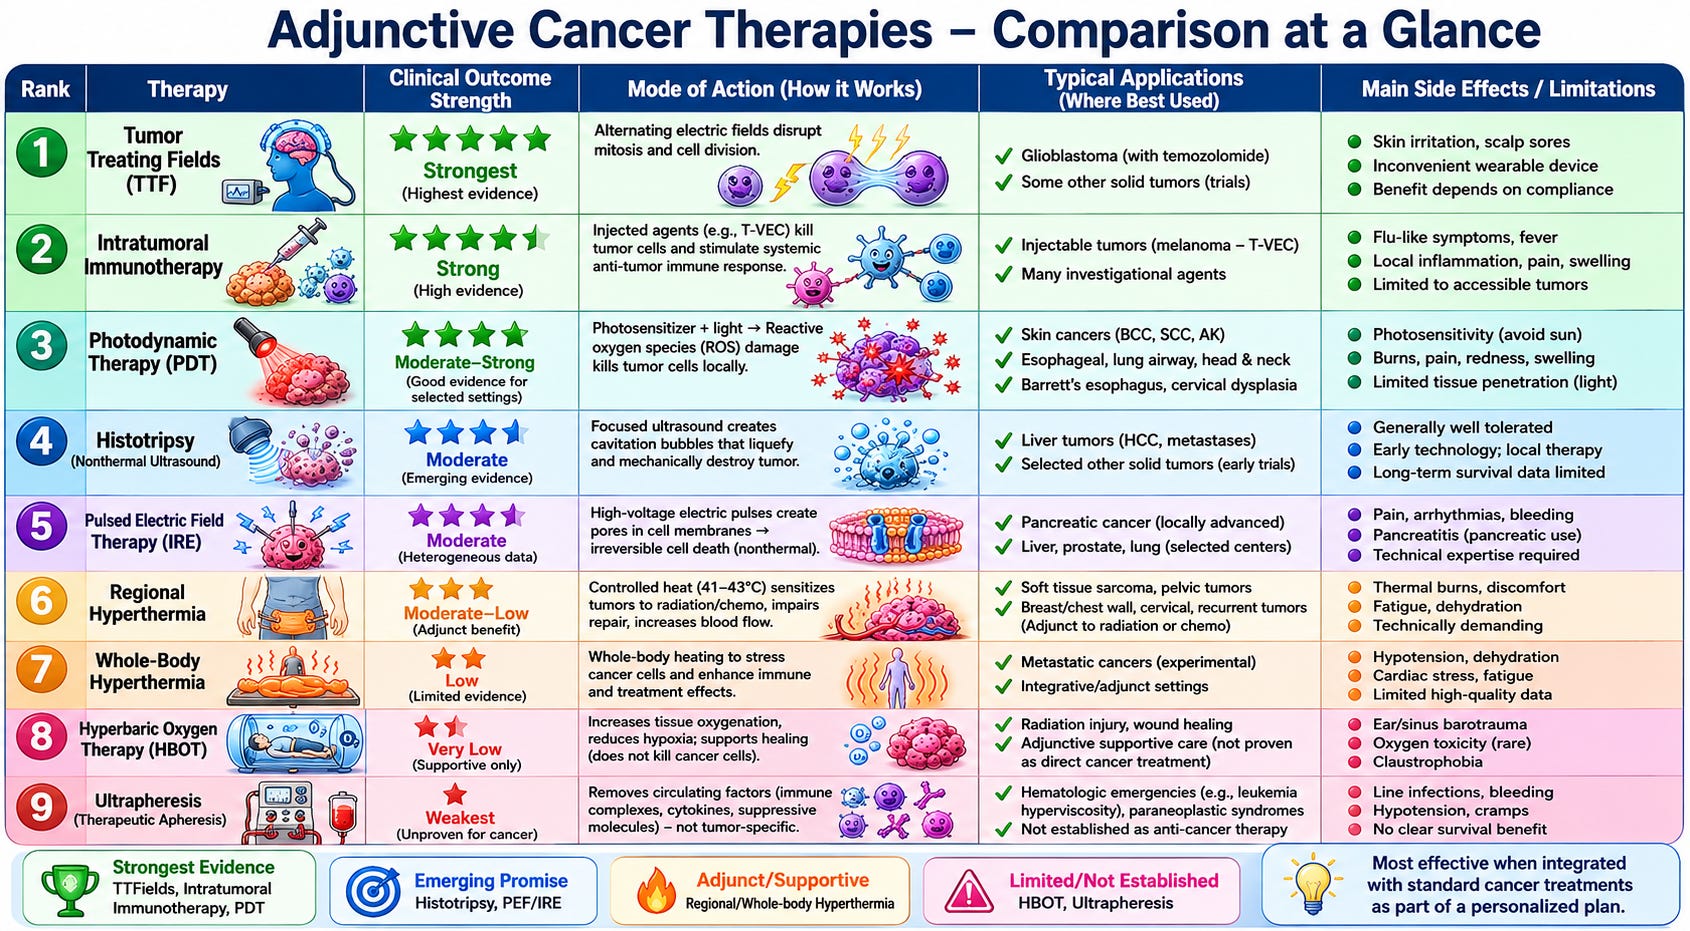
TUMOR TREATING FIELDS
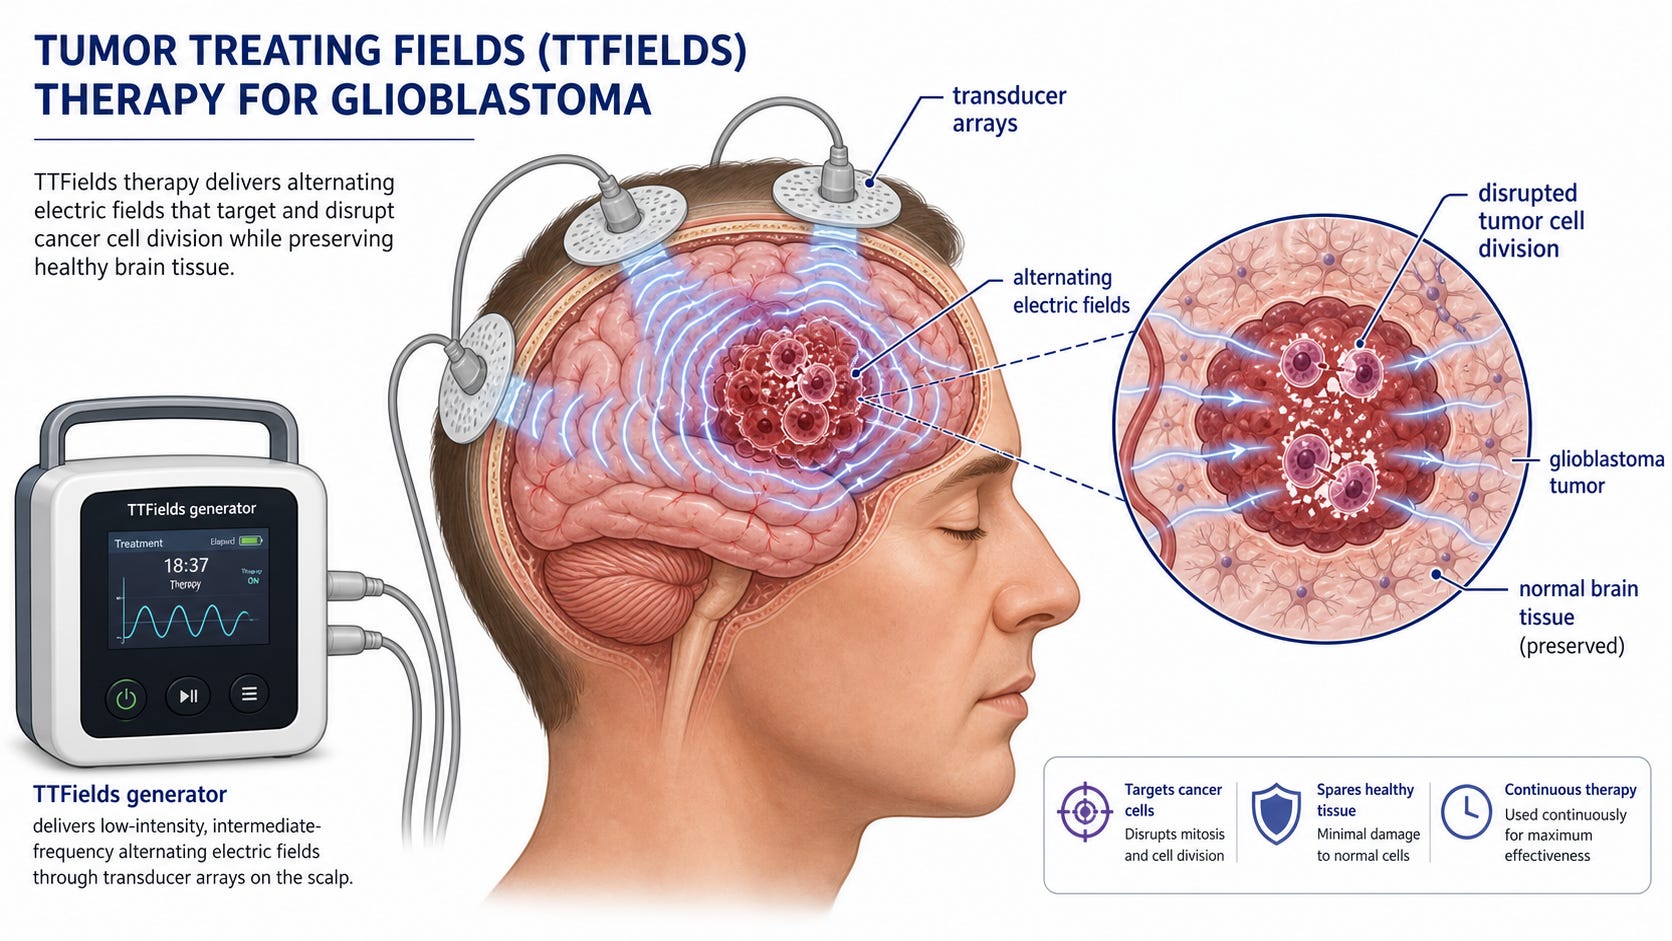
Tumor Treating Fields are low-intensity (≈1–3 V/cm), intermediate-frequency (100–300 kHz) alternating electric fields delivered non-invasively via transducer arrays placed on the skin over the tumor region. They are designed to disrupt cancer cell division without using cytotoxic drugs or ionizing radiation. The only commercially available system is Optune, developed by Novocure. (1, 2) Transducer arrays are activated sequentially each second, affecting a direction change of the incident field on the target. (3) TTF mechanism of action involves polarizable intra-cellular structures and mitotic disruption. TTF induces mitotic spindle assembly checkpoint arrest leading to a cell-cycle arrest, followed by mitotic slippage, and subsequent cell death or senescence. (3) In addition, TTF promotes autophagy by inducing AMPK, miR29b and other drivers of autophagy. TTF has immunological effects including activation of the STING pathway, increased expression of MHC II, CD80, and CD40 on dendritic cells and M1 macrophage polarization. (3) TTF has been shown to suppress the migration and invasion of LN-18 glioma cells in experimental models. TTF do not have a systemic half-life like oral or intravenous therapies and exert their therapeutic effect while the electric fields are being applied only on actively dividing cancer cells but not on healthy cells. Thus, compliance with treatment is critical to maximize effectiveness. (1)
TTF has been studied most extensively in patients with glioblastoma multiforme (GBM).(2) In patients with GBM, TTF is delivered to the region of the tumor via transducer arrays placed on the patient’s scalp. The Phase III EF-14 RCT (n=695) in newly diagnosed GBM patients demonstrated significantly improved progression-free survival (HR, 0.63; 95%CI, 0.52-0.76; P < .001) and overall survival (HR, 0.63; 95%CI, 0.53-0.76; P < .001) when TTF were used together with maintenance temozolomide (TMZ) compared with TMZ alone. (4, 5) The National Comprehensive Cancer Network (NCCN) recommends TTF in combination with TMZ for the treatment of patients with both newly diagnosed and recurrent glioblastoma. (6) Based on this information patients with GBM should consider TTF, when feasible, as an adjunctive treatment option. (7) TTF are also FDA‑approved for unresectable, locally advanced or metastatic malignant pleural mesothelioma, used with pemetrexed and platinum chemotherapy.(8) TTF is currently undergoing evaluation as adjunctive treatment in patients with NSCLC, pancreatic and ovarian cancer. (3)
Figure 1. Optune Tumor Treating Device
Figure 2. Tumor treating fields (TTF) interact with cells during mitosis.(2)
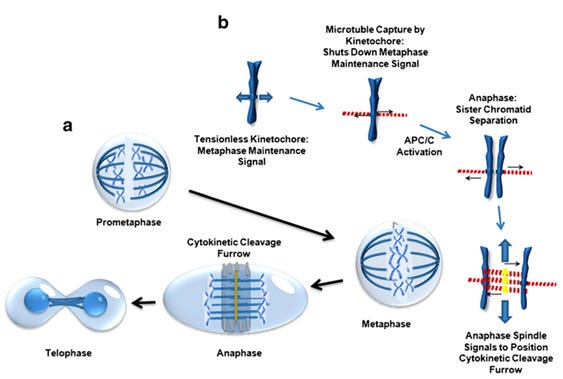
Figure 3. Tumor Treating Device
PHOTODYNAMIC THERAPY
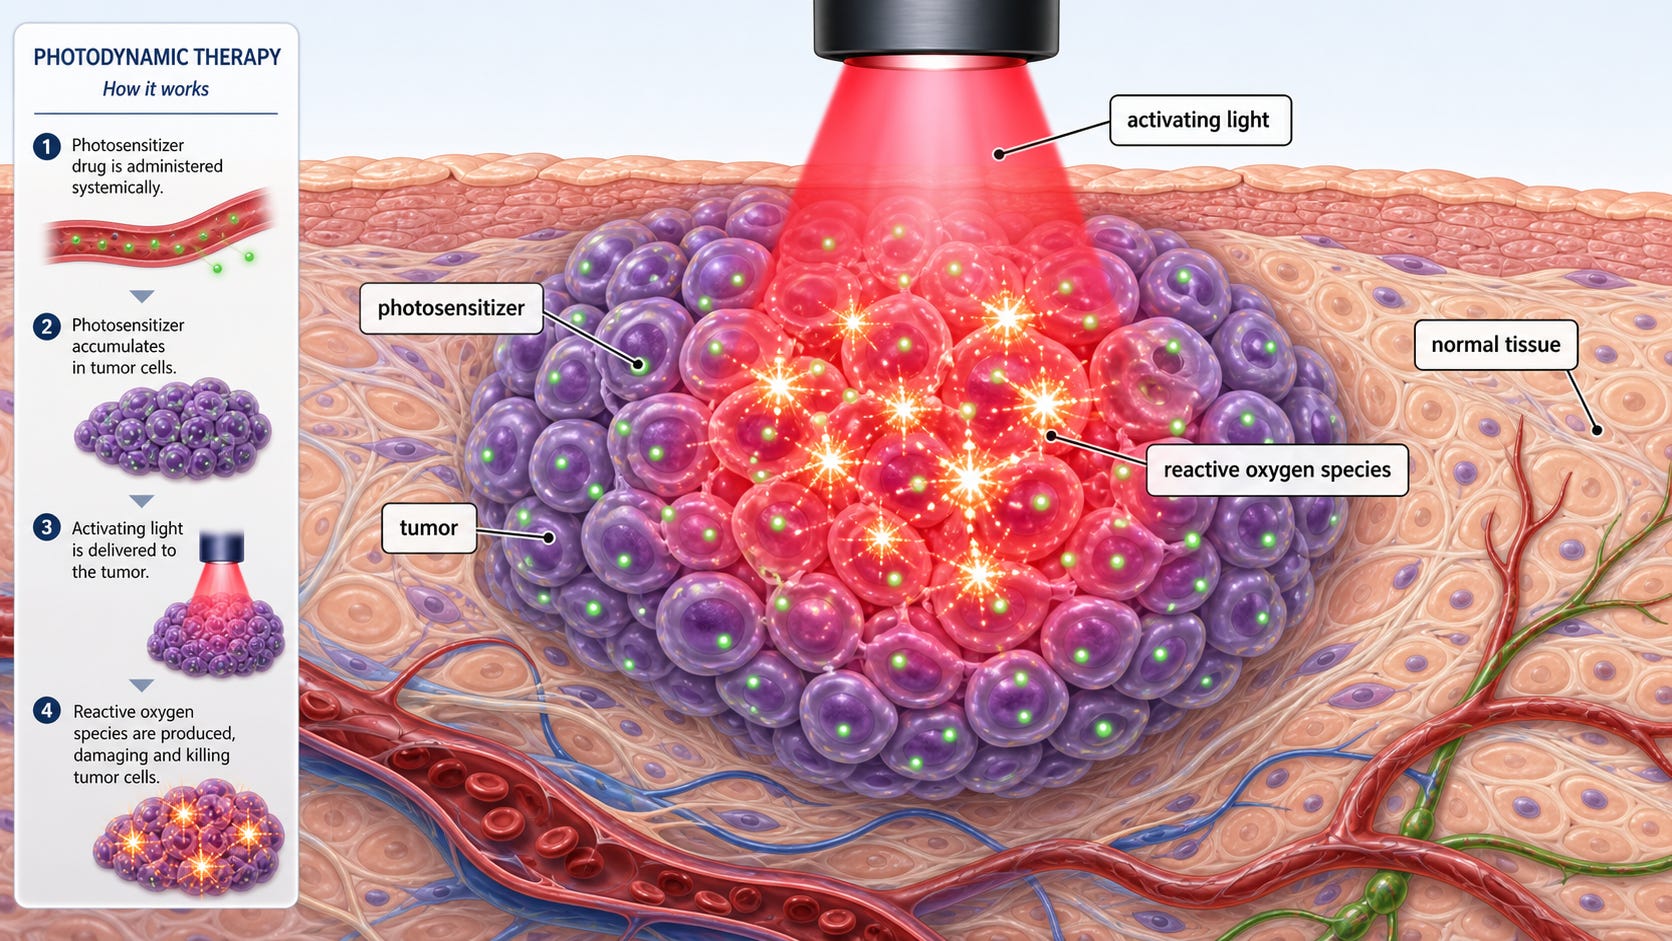
Photodynamic therapy (PDT) is a minimally invasive cancer treatment that uses a light‑activated drug and oxygen to generate toxic reactive species that selectively destroy tumor tissue, especially in superficial or endoluminal cancers. (9) PDT requires three components: a photosensitizer drug, light of a specific wavelength, and oxygen in the tissue. The photosensitizer is given systemically or applied locally, accumulates preferentially in tumor and associated vasculature, and is then activated by light delivered via lasers, LEDs, or fiberoptics. When sensitizer molecules are exposed to light energy, electrons at low‐energy singlet states jump to high-energy singlet states, and some spontaneously convert to excited triplet states. The excited triplet state interacts with oxygen-producing reactive oxygen species. Reactive oxygen species cause cell death locally through a complex interplay of apoptosis, necrosis, and autophagy‐associated cell death. (10)
Light has been known to provide a therapeutic potential for several thousands of years. Over 3,000 years ago, since the ancient Indian and Chinese civilizations, it has been used for the treatment of various diseases mainly in combination with reactive chemicals, for example, to treat conditions like vitiligo, psoriasis, and skin cancer. Sunshine has enormous therapeutic effects both due to ultraviolet-B (UVB) and the synthesis of vitamin D in the skin and near infrared (NIR) radiation (about 40% of solar radiation), which has enormous health benefits including mitochondrial melatonin synthesis. (11, 12) Due to our modern lifestyle, modern man has a profound deficiency of NIR exposure. (12)
Of all the wavelengths of sunlight, NIR-A radiation has the deepest penetration into tissues, up to 23 cm. During the 1918 influenza pandemic, “open-air treatment of influenzae” (sunshine) appears to have been the most effective treatment for seriously ill patients. (13) A more recent prospective study demonstrated that avoiding sun exposure is a risk factor for all-cause mortality. (14) In this study, the mortality rate amongst avoiders of sun exposure was approximately twofold higher compared with the highest sun exposure group.
Dermatologists commonly use PDT with a topical photosensitizing agent for the treatment of actinic keratoses and early nonmelanoma skin cancers, but the potential applications for PDT are far broader, including solid tumors. (9) When PDT is utilized to treat malignant and premalignant tumors, a patient is administered a sensitizer agent that preferentially accumulates in neoplastic lesions and is activated by light to produce cell death. (10)
PDT for cutaneous indications commonly utilizes a topical photosensitizer, such as 5‐aminolevulinic acid or methyl aminolevulinate, which are precursors of protoporphyrin IX.(9) Treatment of visceral tumors requires an intravenous or oral photosensitizer, and the most commonly used photosensitizing agent for this indication is porfimer sodium. Porfimer sodium absorbs light at 630 nm (red light). PDT has been performed with various light sources including lasers, incandescent light, laser-emitting diodes, transcutaneous fiberoptic devices, and daylight. (15)
Chlorophyll derivatives, eg chlorin e6, have superseded porphyrin compounds because they are nontoxic and are of course common in our diet. Porphyrin is metabolized via the rate limited enzyme ALA synthetase. Elimination is consequently very slow and patients may suffer photosensitivity (skin blistering) for several weeks. This has been a confounding factor for the adoption of PDT for almost a century. Chlorin e6 is rapidly eliminated and it produces a quantum more ROS.
While the efficacy of PDT in killing cancer cells has been demonstrated in experimental models, (16) clinical studies demonstrating the benefit of this modality in patients with non-cutaneous malignancies is limited. (15, 17-19)
Current clinical uses
PDT is approved for several malignancies and precancers, mainly where light can easily reach the lesion. Common oncologic indications include:
Non‑melanoma skin cancers (basal cell, early squamous cell) and actinic keratoses.
Early or superficial esophageal cancer and Barrett esophagus with dysplasia.
Central non‑small cell lung cancers accessible via bronchoscopy, and for palliation of obstructing endobronchial lesions.
Cutaneous T‑cell lymphoma and some other superficial or mucosal tumors, often in specialized centers.
Meta‑analyses and umbrella reviews suggest meaningful local control for select oral squamous cell carcinoma, cutaneous metastases, prostate, and bladder cancers, but evidence quality and protocols vary, so PDT is usually used as an adjunct or for patients unfit for surgery or radiotherapy.(20)
Figure 4. Photodynamic Therapy
PULSED ELECTRIC FIELD THERAPY
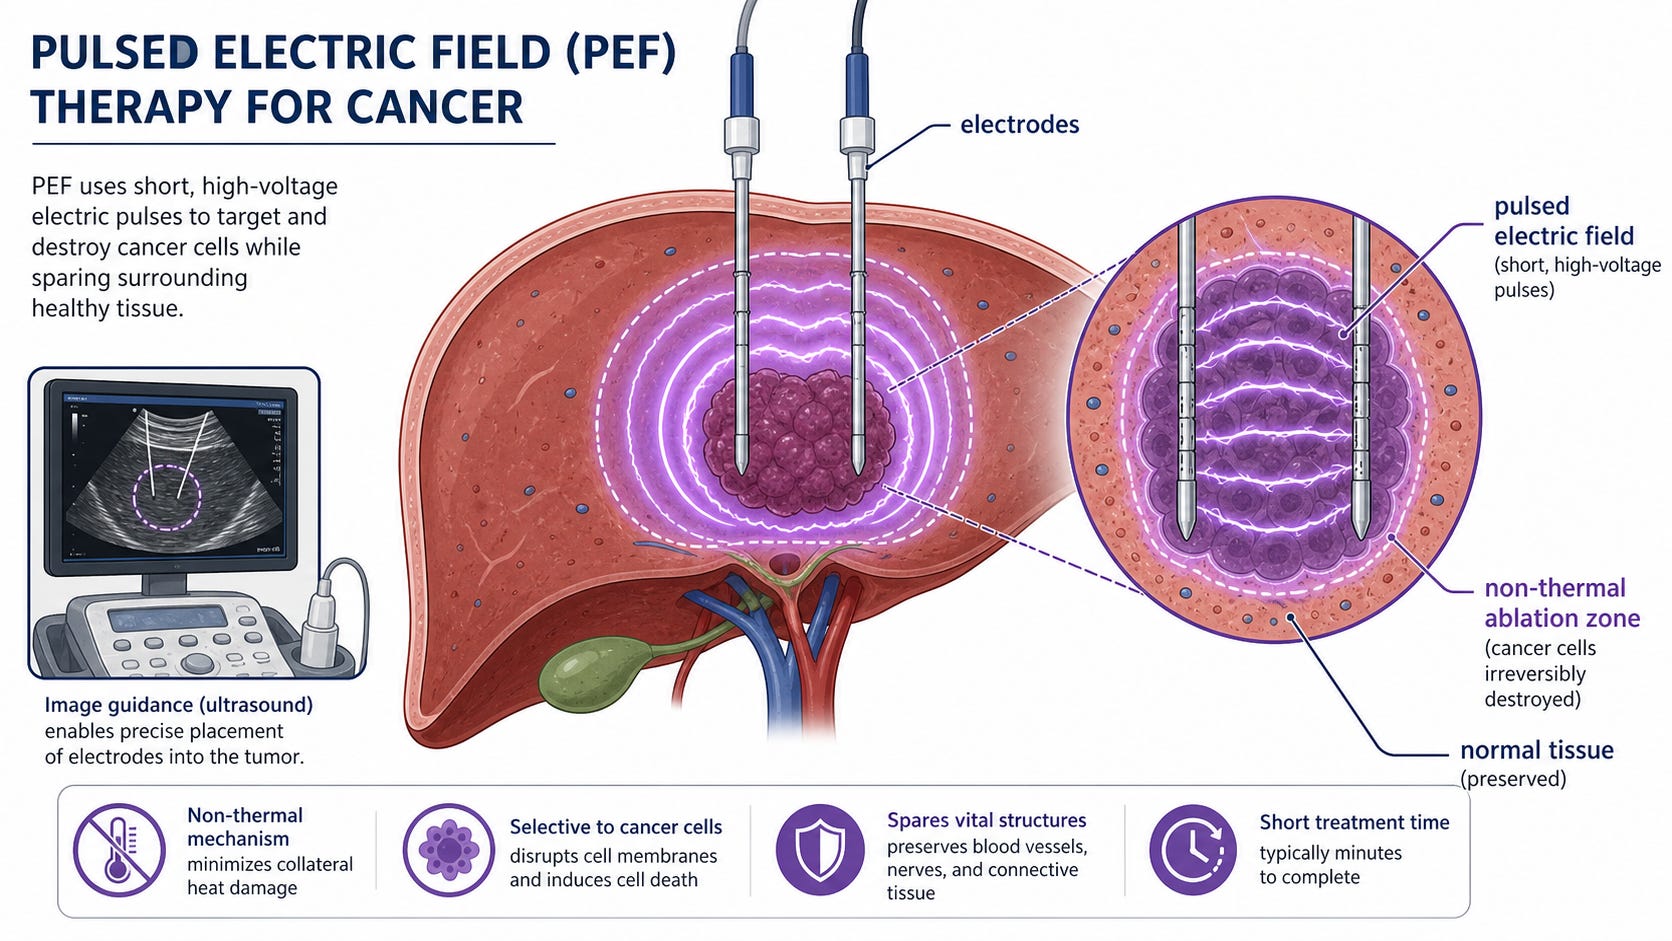
Pulsed electric field (PEF) therapy is an emerging, non‑thermal modality that uses brief, high‑voltage electrical pulses to ablate tumors and potentially prime systemic antitumor immunity.(21, 22) Pulsed electric field (PEF) therapy, most commonly implemented clinically as irreversible electroporation (IRE), represents a non-thermal tumor ablation modality that has gained attention for its potential to both destroy tumors locally and stimulate systemic antitumor immunity. Unlike conventional ablation techniques that rely on heat or cold, IRE induces tumor cell death through electrical disruption of cell membranes, while largely preserving the structural integrity of surrounding tissues.
This technology is increasingly being investigated as a platform therapy that can synergize with immunotherapies, potentially converting tumors that are immunologically “cold” into those capable of generating durable immune responses.
Mechanism and technology
PEF therapy delivers microsecond–millisecond pulses through needle or catheter‑based electrodes to generate intense electric fields within the tumor, inducing irreversible electroporation of cancer cell membranes and subsequent cell death. Unlike thermal ablation, which destroys tissue through heat or freezing, PEF preserves extracellular matrix and collateral structures such as vessels, bile ducts, bronchi, and nerves, making it attractive for tumors near critical anatomy. As dying tumor cells release neoantigens and damage‑associated molecular patterns, early studies suggest PEF can remodel the tumor microenvironment and augment both innate and adaptive immune responses, raising the possibility of in situ vaccination effects when combined with systemic therapies.
Oncologic applications and clinical experience
PEF‑based approaches span a spectrum from conventional electrochemotherapy (ECT) and irreversible electroporation (IRE) to newer non‑thermal systems such as Aliya for percutaneous or bronchoscopic tumor ablation. In solid tumors, PEF ablation has been used for liver, lung, colorectal, sarcoma, and superficial soft‑tissue metastases, including patients who have progressed on or are ineligible for standard therapies. A 2023 snapshot review highlighted growing locoregional PEF use in oncology and emphasized its particular value where surgical margins are constrained or thermal techniques are unsafe. Institutional reports from centers such as Roswell Park and Duke describe technically successful ablation with outpatient procedures, short recovery, and feasibility even in complex thoracic locations via percutaneous or bronchoscopic access.(23)
Safety profile
Across early clinical series, PEF appears to have a favorable safety profile, with high technical success, low procedure‑related complication rates, and minimal impact on downstream systemic therapy. In the AFFINITY study of lung tumors treated with Aliya PEF, local control of ablated lesions approached 96–100%, with only one serious percutaneous access complication (pneumothorax) that resolved without long‑term sequelae.(24) Patients typically experience transient chest wall discomfort or flu‑like symptoms, and most procedures are performed under general anesthesia as same‑day interventions. Importantly, PEF is designed to limit collateral injury to adjacent esophagus, nerves, and vasculature—a benefit already demonstrated in large atrial fibrillation trials using pulsed field ablation in cardiac tissue.
Immunologic effects and combinations
Preclinical and early translational studies indicate that PEF can induce immunogenic cell death, increase inflammatory infiltrates, and enhance tumor antigen presentation within the treated field. Clinical observations from lung cancer cohorts suggest that PEF ablation alone may trigger systemic immune activation, with upregulation of both adaptive and innate immune signatures even in patients not receiving concurrent systemic therapy. These findings have stimulated growing interest in combining PEF with checkpoint inhibitors or other immunotherapies to convert “cold” tumors into “hot” lesions and potentially generate abscopal responses. Multiple ongoing trials are now evaluating PEF in metastatic lung and breast cancers, often integrating image‑guided ablation with standard systemic regimens to define optimal sequencing and patient selection.(25)
Limitations and future directions
Despite its promise, PEF therapy remains in an early phase of oncologic adoption, with heterogeneity in devices, dosing parameters, and treatment protocols that complicate cross‑study comparisons. Most available data derive from single‑arm feasibility and safety studies with relatively small cohorts and short follow‑up, leaving key questions about long‑term local control, survival benefit, and predictive biomarkers unanswered. Future priorities include randomized comparisons versus radiofrequency or cryoablation, formal integration with immuno‑oncology combinations, and mechanistic work to refine field strength, pulse number, and electrode configuration for different tumor types and anatomic sites. Nonetheless, current evidence supports PEF as a safe, organ‑sparing, and potentially immunogenic locoregional option that may expand the therapeutic toolkit for patients with otherwise limited local control strategies.(26)
Figure 5. Pulsed Electric Field Therapy
Intratumoral Immunotherapy
Intratumoral immunotherapy delivers immune‑activating agents directly into the tumor microenvironment to generate potent local inflammation and, ideally, durable systemic antitumor immunity. Unlike conventional systemic immunotherapy, which exposes the entire body to immune modulators, intratumoral injection concentrates the drug at the disease site, enhancing pharmacodynamic intensity in the tumor while reducing off‑target toxicity.(27, 28)
Rationale and mechanisms
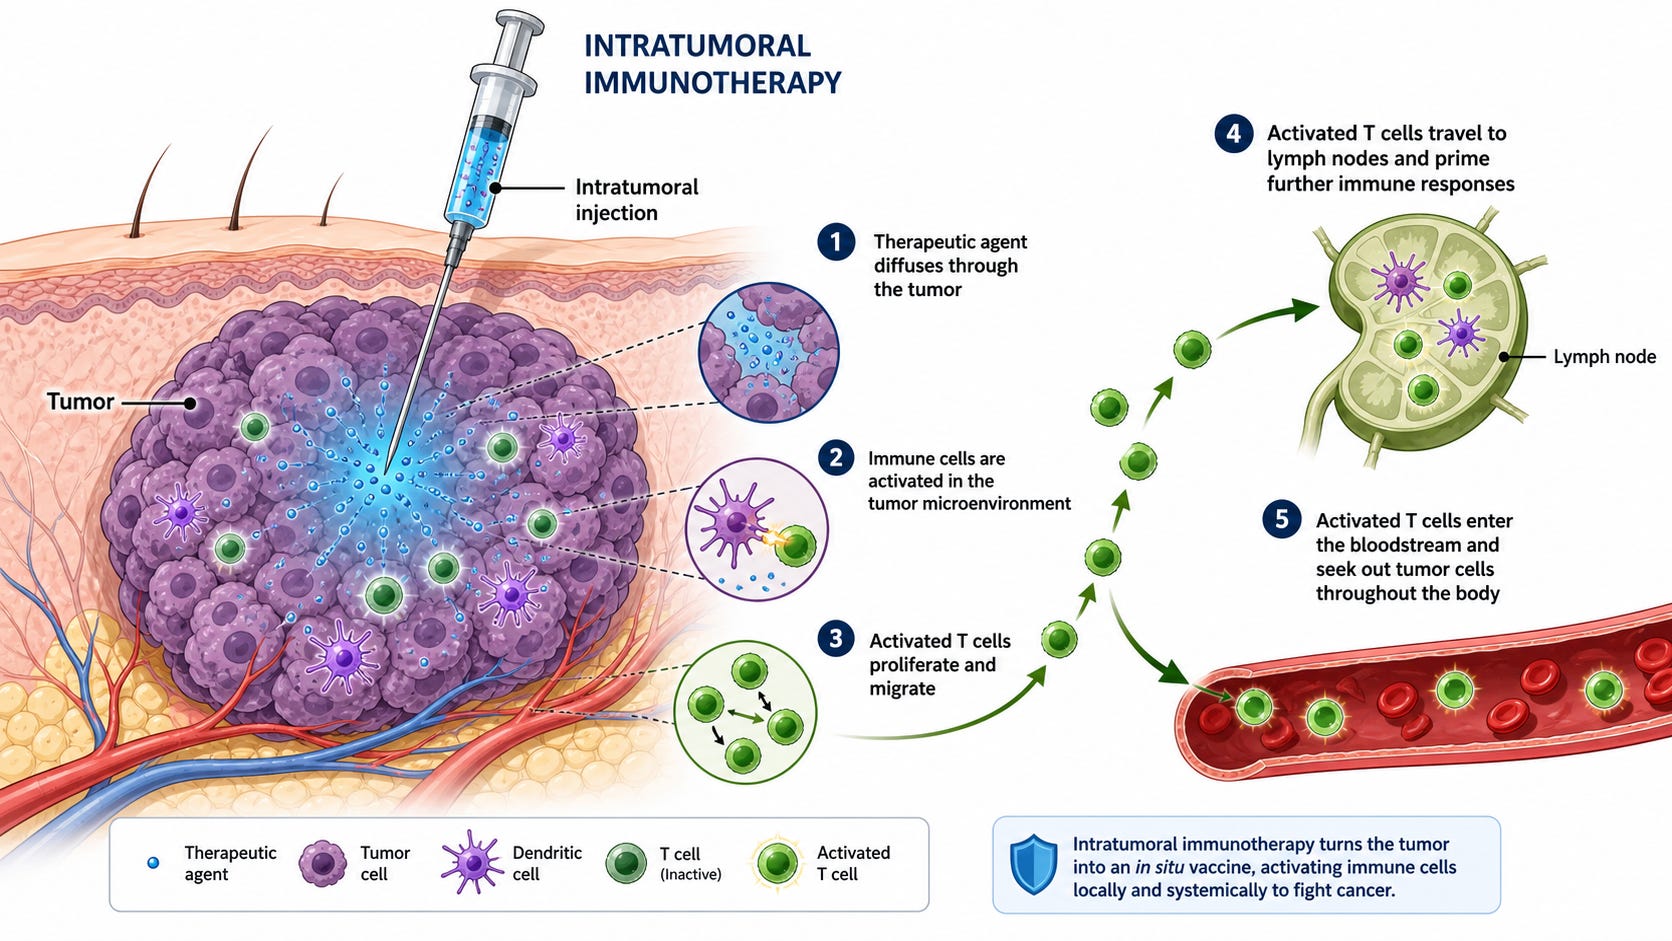
Direct injection into one or more tumor lesions allows high local drug concentrations, reshaping the immunosuppressive microenvironment and converting “cold” tumors into “hot,” inflamed lesions rich in antigen‑presenting cells and effector T cells. Tumor cell death and stress induced by these agents drive release of neoantigens and danger signals, which dendritic cells capture and present in draining lymph nodes, effectively turning the injected tumor into an in situ vaccine. This process can generate systemic T‑cell responses against shared antigens and, in some patients, regression of non‑injected metastases—the so‑called abscopal effect—especially when intratumoral therapy is combined with checkpoint blockade or radiotherapy.(29)
Figure 6. Intratumoral Immunotherapy
Mechanistically, intratumoral immunotherapy spans several platforms: oncolytic viruses that selectively replicate in tumor cells and release cytokines, pattern‑recognition agonists (e.g., TLR/STING ligands), cytokine constructs, and cellular products such as dendritic cells or T cells. Oncolytic viral therapy, exemplified by talimogene laherparepvec (T‑VEC) for melanoma, remains the most clinically validated modality and illustrates how local viral oncolysis plus GM‑CSF expression can drive both local responses and systemic immunity.(30)
The strategy aims to trigger local tumor destruction and systemic antitumor immune responses by converting the tumor itself into an in-situ vaccine.
This class of therapies includes:
Nonviral oncolytic agents (e.g., PV-10)
Toll-like receptor (TLR) agonists
Oncolytic viruses (e.g., T-VEC, CAVATAK, Pexa-Vec, HF10, PVS-RIPO)
Among these, Talimogene laherparepvec (T-VEC) is currently the only FDA-approved intratumoral oncolytic virus therapy, approved for unresectable melanoma
Clinical applications and evidence
Early work has focused on accessible solid tumors, including melanoma, non‑melanoma skin cancers, head and neck squamous cell carcinoma, and liver and gastrointestinal malignancies. In melanoma, intratumoral T‑VEC has demonstrated durable local responses and improved durable response rates, particularly when combined with systemic checkpoint inhibitors, supporting the synergy between local priming and systemic PD‑1/CTLA‑4 blockade. In gastrointestinal cancers, image‑guided intratumoral injection using endoscopy or interventional radiology enables delivery of viral vectors, cytokines, or dendritic cells directly into deep visceral lesions, with early trials showing feasible procedures, acceptable toxicity, and evidence of both local control and distant immune effects. Head and neck and other mucosal tumors are being actively explored, with contemporary reviews emphasizing promising response signals but also the need for standardized protocols and larger controlled trials.(31)
Neoadjuvant intratumoral immunotherapy—administering injections prior to surgical resection—is an area of particular interest. By inflaming the primary tumor bed and expanding tumor‑specific T‑cell clones before surgery, this strategy aims to sterilize micrometastatic disease and reduce recurrence, with early clinical data demonstrating robust immune activation in blood and tumor and acceptable perioperative safety.(28)
Advantages, limitations, and future directions
Key advantages include high intratumoral drug levels, lower systemic toxicity, the potential for in situ vaccination, and the ability to rescue tumors that are refractory to systemic immunotherapy by locally reversing immune exclusion. Intratumoral delivery also allows flexible combinations with radiation and chemotherapy, which can be timed to maximize immunogenic cell death and antigen release.
However, several limitations remain. Intratumoral approaches require image‑guided access, which may be challenging for deeply seated or small lesions, and repeated injections can be logistically demanding. Drug distribution within heterogeneous tumor architecture is variable, and optimal dosing, scheduling, and number of lesions to inject are not yet standardized across platforms. Many available data come from early‑phase or single‑arm studies, so the true incremental benefit over systemic therapy alone is still being defined.
Future directions include rational combinations with checkpoint inhibitors and targeted agents; biomarker‑guided selection based on baseline immune contexture; and development of novel vectors and delivery systems that can safely reach visceral and CNS lesions. If these hurdles are addressed in ongoing phase II–III trials, intratumoral immunotherapy may evolve from a niche intervention for accessible lesions into a central strategy for converting immunologically cold tumors into systemically controlled disease.
Histotripsy for the Treatment of Cancer
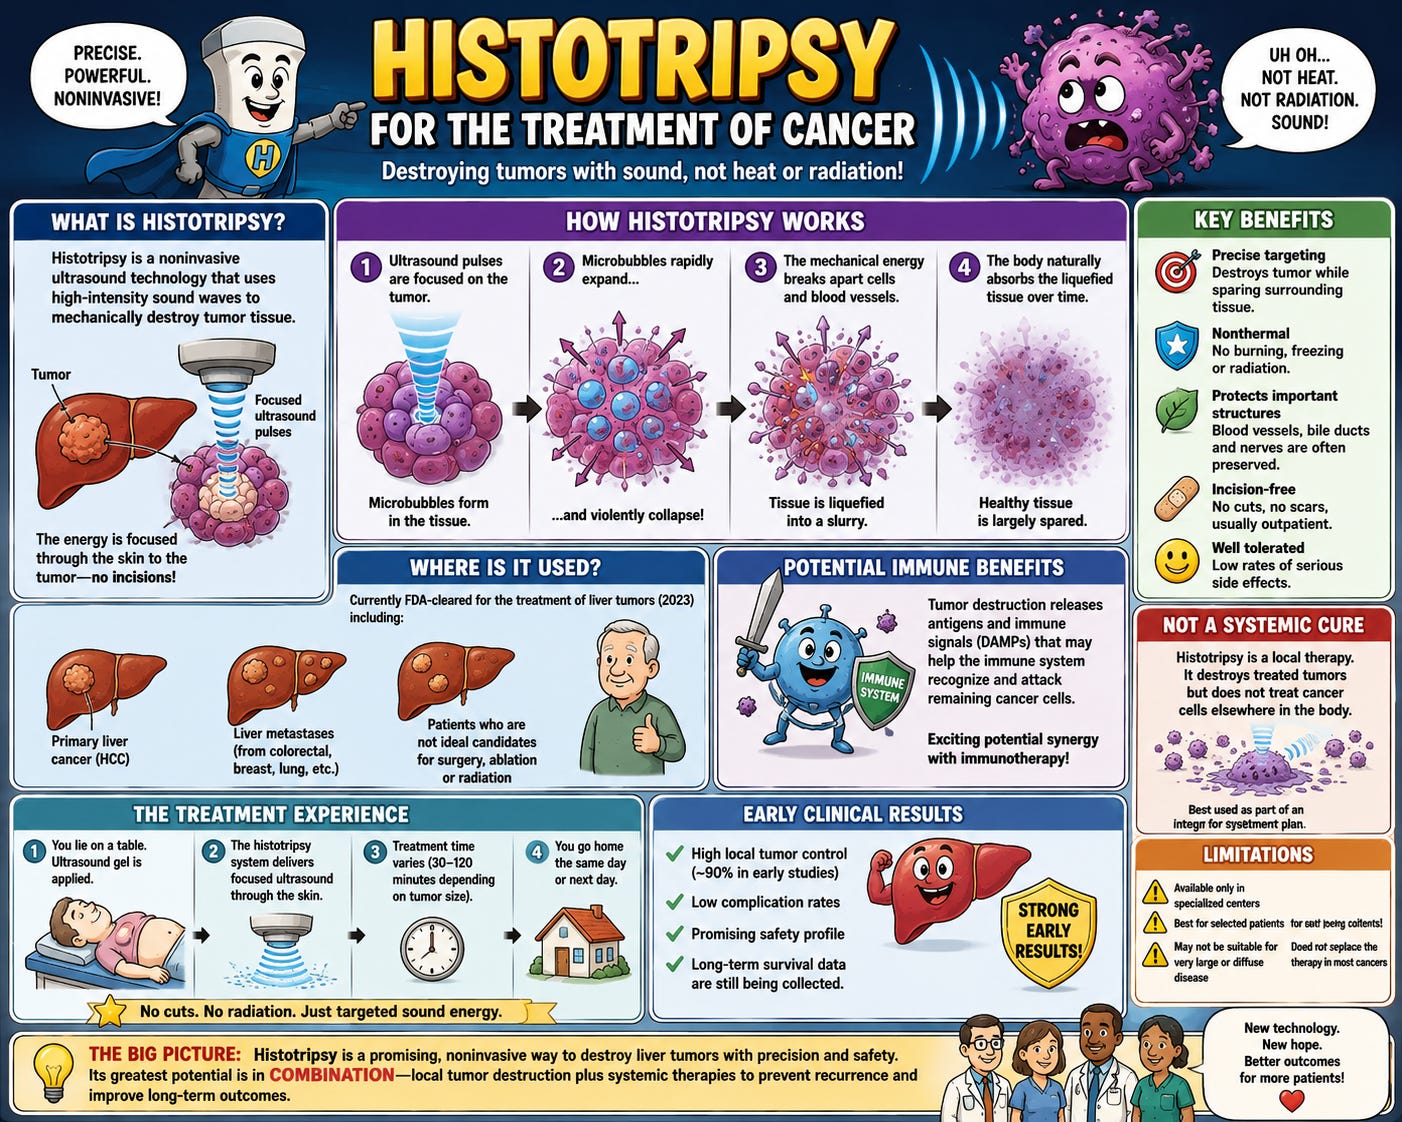
Histotripsy is a newer, noninvasive tumor-ablation technology that uses focused ultrasound pulses to mechanically destroy tissue. Unlike thermal ablation, radiation, or surgery, histotripsy does not primarily burn, freeze, or cut the tumor. Instead, it creates rapidly forming and collapsing microbubbles inside the target tissue, a process called acoustic cavitation, which mechanically liquefies the tumor.(32) It received FDA clearance for treatment of liver tumors in 2023.
The major appeal of histotripsy is that it is nonthermal, nonionizing, and incision-free. Because the energy is focused through the skin, the surrounding tissue may be relatively spared, and important structures such as blood vessels and bile ducts may be less vulnerable than with heat-based ablation. This makes the technology particularly attractive for tumors in difficult anatomic locations. (33)
At present, the main clinical application is liver tumors, including primary liver cancers and liver metastases. Centers using the technology describe it as a potential option for selected patients who are not ideal candidates for surgery, thermal ablation, or radiation. However, it remains primarily a local therapy; it destroys targeted lesions but does not treat systemic micrometastatic disease. (33)
Mechanistically, histotripsy may have advantages beyond local tumor destruction. Tumor liquefaction may release tumor antigens and damage-associated molecular patterns, potentially stimulating immune recognition. This raises interest in combining histotripsy with immunotherapy, metabolic therapy, or other systemic strategies. However, the immune effects remain investigational.
The early clinical experience is encouraging, with reports of good short-term local tumor control and relatively low procedural toxicity. Some early data suggest approximately 90% local tumor control in liver lesions, but mature long-term survival data are still limited.
The limitations are important. Histotripsy is not yet proven to improve overall survival across cancer types. Its current use is largely confined to visible, targetable liver tumors. It may not be appropriate for very large lesions, diffuse disease, tumors poorly visualized by ultrasound, or patients with high systemic tumor burden.
Histotripsy is a promising noninvasive local therapy for selected liver tumors. Its greatest potential may be as part of an integrated strategy: local tumor destruction plus systemic treatment aimed at micrometastases, immune escape, metabolic adaptation, and recurrence. It is exciting, but still early.
Figure 7.
REGIONAL AND WHOLE-BODY HYPERTHERMIA
Beginning with the early observations by Dr. William Cooley in the 1890s that infections in cancer patients are associated with tumor regression and that injection of cocktails of attenuated bacterial cultures induces a fever and a significant anti-tumor effect, there has been a revival of interest in therapeutic hyperthermia (TH) for cancer therapy. (34) TH can be defined as a therapy able to raise the temperature in the tumor mass between 41 and 45oC by external physical means.(35, 36) TH was first used in combination with radiotherapy by Warren in 1935. (37) In this series all 32 patients appeared to respond to this treatment modality. Subsequently TH has been combined with radiotherapy and/or chemotherapy with remarkable success in treating advanced and recurrent cancers. Phase II/III clinical trials have demonstrated that hyperthermia combination therapy is beneficial for local tumor control and survival in patients with high-risk tumors including cervical cancer, recurrent breast cancer, head and neck cancer, melanoma, sarcomas, liver, glioblastoma and pancreatic cancer. (36, 38-41)
Hyperthermia uses controlled heat to damage or sensitize cancer cells and is usually given together with radiation or chemotherapy, not as a stand‑alone cure. Whole‑body and regional hyperthermia differ mainly in how much of the body is heated, the strength of clinical evidence, and how commonly they are integrated into standard cancer care.(38)
What hyperthermia is
Hyperthermia therapy raises tissue temperature (typically about 39–43 °C) to injure or kill cancer cells and to make tumors more sensitive to radiation and some chemotherapy drugs.
Heat can directly damage cancer cell proteins and membranes, impair DNA repair after radiation, improve blood flow and oxygenation in tumors, and enhance drug delivery.
Regional (loco‑regional) hyperthermia
Regional or local hyperthermia heats a tumor and a small surrounding region (for example, a limb, pelvis, or chest wall) using external applicators, intraluminal probes, or perfusion techniques.(38, 42)
It is most often combined with radiotherapy and/or chemotherapy for difficult or recurrent tumors (e.g., soft‑tissue sarcoma, recurrent breast cancer in the chest wall, cervical cancer, some GI and pelvic tumors).(42)
Evidence and indications
A randomized trial in high‑risk soft‑tissue sarcoma found that adding regional hyperthermia to chemotherapy improved local progression‑free survival and disease‑free survival compared with chemotherapy alone.(43)
Reviews of loco‑regional hyperthermia report improved local control and sometimes survival when added to chemoradiation in several settings (recurrent breast cancer, cervical cancer, bladder cancer, rectal cancer, some pancreatic and esophageal cancers).(38)
Some medical policies consider local hyperthermia medically necessary when used with radiation for superficial primary or metastatic tumors (e.g., chest wall recurrences, superficial melanoma, cervical lymph nodes from head and neck cancer) when other options are limited.
Whole‑body hyperthermia
Whole‑body hyperthermia (WBH) raises core body temperature (often to about 38.5–40.5 °C) using devices such as thermal chambers, heated beds with infrared lamps, heated blankets, or warm‑water systems.(44)
It is being studied mainly for metastatic or recurrent cancer, often as an adjunct to chemotherapy or immune‑modulating treatments, rather than as a routine part of standard oncology pathways.
Many cancer guidelines in the U.S. do not list WBH as standard care; it is more often offered in specialized or complementary oncology centers, sometimes as part of clinical trials or integrative protocols.
HYPERBARIC OXYGEN THERAPY
HBOT involves breathing 100% oxygen in a pressurized chamber, which raises the amount of dissolved oxygen in the blood and tissues. It is FDA‑cleared for specific problems such as decompression sickness, carbon monoxide poisoning, certain serious infections, and radiation‑related tissue injury, but not for treating cancer itself.
Hypoxia is a critical hallmark of solid tumors and involves enhanced cell survival, angiogenesis, glycolytic metabolism, and metastasis. Hyperbaric oxygen treatment (HBOT) has for centuries been used to improve or cure disorders involving hypoxia and ischemia, by enhancing the amount of dissolved oxygen in plasma and thereby increasing O2 delivery to the tissue. (45)
HBOT leads to hyperoxia and elevated levels of reactive oxygen species (ROS), which overwhelm the cancer cells’ antioxidant defense and lead to cell death. (46, 47) The molecular mechanisms behind hyperoxia-induced cell death involve a complex signaling system including protein kinases and receptors such as RAGE, CXCR2, TLR3, and TLR4.(48) Furthermore, contrary to what would be expected, HBOT has been shown to induce an antiangiogenic effect in tumor models. (46, 49)
While HBOT appears to have limited effects on cancer growth, it may potentiate the effects of other treatment modalities. Hoff et al demonstrated that a ketogenic diet combined with HBO had significant anticancer effects in a natural model of systemic metastatic cancer.(50) Hypoxia has been described as an important factor for chemotherapeutic resistance. (45) Studies on HBOT as a chemotherapeutic adjuvant have shown augmented effects both in vitro and in vivo. (45) However, it is important to emphasize Mayer et al. list five chemotherapeutic agents (doxorubicin, bleomycin, disulfiram, cisplatin, and mafenide acetate) which are strongly contraindicated in combination with HBOT due to potential potentiation of toxicity. Radiotherapy in combination with HBOT has been used clinically in two different applications: (a) as a therapeutic agent for treating late radiation injury and (b) as a radiosensitizer, aiming to increase the effect of radiotherapy. (45) An updated Cochrane systematic review concluded that “there is some evidence that HBOT improves local tumor control and mortality in tumors of the head and neck; however, the outcomes seem to be related to the use of unusual fractionation schemes and thereby conclude that the benefits of HBOT should be interpreted with caution.” (51) While HBOT may have promise as an anticancer intervention, especially when combined with other treatment modalities, the clinical data to support this intervention is limited at this time.
ULTRAPHERESIS
Ultrapheresis refers to an experimental form of therapeutic apheresis that was explored mainly in the 1980s–1990s as a cancer treatment. It is not a standard‑of‑care therapy today.
What ultrapheresis is
It is a modified plasmapheresis technique in which whole blood is continuously processed through a filter system designed to remove low–molecular weight, circulating “blocking” or immunosuppressive factors (e.g., certain proteins, immune complexes, tumor‑derived factors) thought to inhibit anti‑tumor immunity.
Unlike routine plasmapheresis (which non‑selectively removes plasma), ultrapheresis was intended to be more selective for these small suppressive molecules while returning most other plasma components to the patient.
Proposed anti‑cancer rationale
Tumors release soluble factors such as soluble TNF receptors and other immunosuppressive molecules that can neutralize TNF‑α and blunt cytotoxic immune responses.
Early ultrapheresis protocols aimed to lower the levels of these circulating suppressive factors, thereby restoring endogenous TNF‑α activity and enabling T‑cell and macrophage‑mediated tumor killing.
In small, early‑phase studies, some patients showed tumor‑specific inflammatory reactions and partial tumor regressions after courses of ultrapheresis, but the data were limited (small numbers, no randomized controls, heterogeneous tumors).
Current status
Ultrapheresis as originally performed is not a routine or widely available oncology treatment; it remains an investigational or historical approach mentioned in reviews of therapeutic apheresis in cancer.
More modern concepts build on the same “subtractive immunotherapy” idea—using selective apheresis columns to remove soluble TNF receptors or other immunosuppressive factors (sometimes branded as “immunopheresis”) to restore TNF‑α–driven anti‑tumor activity—these are in early‑stage clinical development.

New Here?
Start with the:
Cancer and Metabolic Library

Medical Disclaimer: The discussion of repurposed medications and nutraceuticals in this article is intended to review the scientific literature and does not constitute a recommendation for self-treatment. Decisions regarding the use of off-label therapies should be made in consultation with a qualified healthcare professional familiar with the patient’s medical history and current treatment plan. Please see the full Medical Disclaimer on the introductory page to Marik’s Cancer & Metabolic Healing Playbook.
References
1. Kinzel A, Ambrogi M, Varshaver M, Kirson ED. Tumor Treating Fields for Glioblastoma Treatment: Patient Satisfaction and Compliance With the Second-Generation Optune(®) System. Clin. Med Insights Oncol. 2019;13:1179554918825449.
2. Swanson KD, Lok E, Wong ET. An Overview of Alternating Electric Fields Therapy (NovoTTF Therapy) for the Treatment of Malignant Glioma. Curr Neurol Neurosci Rep. 2016;16(1):8.
3. Moser JC, Salvador E, Deniz K, Swanson K, Tuszynski J, Carlson KW, et al. The Mechanisms of Action of Tumor Treating Fields. Cancer Res. 2022;82(20):3650–8.
4. Stupp R, Taillibert S, Kanner A, Read W, Steinberg D, Lhermitte B, et al. Effect of Tumor-Treating Fields Plus Maintenance Temozolomide vs Maintenance Temozolomide Alone on Survival in Patients With Glioblastoma: A Randomized Clinical Trial. JAMA. 2017;318(23):2306–16.
5. Kim CY, Paek SH, Nam DH, Chang JH, Hong YK, Kim JH, et al. Tumor treating fields plus temozolomide for newly diagnosed glioblastoma: a sub-group analysis of Korean patients in the EF-14 phase 3 trial. J Neurooncol. 2020;146(3):399–406.
6. NCCN clinical practice guidelines in oncology, Central nervous systems cancer, Version 1. https://www.nccn.org/login?returnURL=https://www.nccn.org/professionals/physician_gls/pdf/cns.pdf; 2018.
7. Ghiaseddin AP, Shin D, Melnick K, Tran DD. Tumor Treating Fields in the Management of Patients with Malignant Gliomas. Curr. Treat. Options Oncol. 2020;21(9):76.
8. Li X, Liu K, Xing L, Rubinsky B. A review of tumor treating fields (TTFields): advancements in clinical applications and mechanistic insights. Radiol Oncol. 2023;57(3):279–91.
9. Yanovsky RL, Bartenstein DW, Rogers GS, Isakoff SJ, Chen ST. Photodynamic therapy for solid tumors: A review of the literature. Photodermatol. Photoimmunol. Photomed. 2019;35(5):295–303.
10. Dos Santos AF, de Almeida DR, Terra LF, Baptista M, Labriola L. Photodynamic therapy in cancer treatment - an update review. J. Cancer Metastasis Treat. 2019;5:25.
11. Reiter RJ, Ma Q, Sharma R. Melatonin in mitochondria: Mitigating clear and present dangers. Physiology. 2020;35:86–95.
12. Zimmerman S, Reiter RJ. Melatonin and the optics of the human body. Melatonin Res. 2019;2:138–60.
13. Hobday RA, Cason JW. The open-air treatment of pandemic influenza. Am. J. Public Health. 2022;99 Suppl.2:S236–S42.
14. Lindqvist PG, Epstein E, Landin-Olsson M, Ingvar C, Nielsen K, stenbeck M, et al. Avoidance of sun exposure is a risk factor for all-cause mortality: results form the Melanoma in Southern Sweden cohort. Journal of Internal Medicine. 2014;276:77–86.
15. Moore CM, Nathan TR, Lees WR, Mosse CA, Freeman A, Emberton M, et al. Photodynamic therapy using meso tetra hydroxy phenyl chlorin (mTHPC) in early prostate cancer. Lasers Surg. Med. 2006;38(5):356–63.
16. Dos Santos AF, Terra LF, Wailemann RA, Oliveira TC, Gomes VM, Mineiro MF, et al. Methylene blue photodynamic therapy induces selective and massive cell death in human breast cancer cells. BMC Cancer. 2017;17(1):194.
17. Kostron H. Photodynamic diagnosis and therapy and the brain. In: Gomer CJ, ed. Photodynamic Therapy. Methods and Protocols: Humana Press; 2010:261–80.
18. Windahl T, Andersson SO, Lofgren L. Photodynamic therapy of localised prostatic cancer. Lancet. 1990;336(8723):1139.
19. Bredell MG, Besic E, Maake C, Walt H. The application and challenges of clinical PD-PDT in the head and neck region: a short review. J Photochem. Photobiol. B. 2010;101(3):185–90.
20. El-Sadek MZ, El-Aziz MKA, Shaaban AH, Mostafa SA, Wadan AS. Advancements and emerging trends in photodynamic therapy: innovations in cancer treatment and beyond. Photochem Photobiol Sci. 2025;24(8):1489–511.
21. Campana LG, Daud A, Lancellotti F, Arroyo JP, Davalos RV, Di Prata C, et al. Pulsed Electric Fields in Oncology: A Snapshot of Current Clinical Practices and Research Directions from the 4th World Congress of Electroporation. Cancers (Basel). 2023;15(13).
22. Senders ZJ, Martin RCG, 2nd. Intratumoral Immunotherapy and Tumor Ablation: A Local Approach with Broad Potential. Cancers (Basel). 2022;14(7).
23. Guo S, Sersa G, Heller R. Editorial: Pulsed electric field based technologies for oncology applications. Front Oncol. 2023;13:1183900.
24. Moreno-Gonzalez A, Nafie EHO, Pastori C, Mammarappallil J, Seshaiah P, Plentl MB, et al. Six-Month Local Control Rates and Immune Responses After Pulsed Electric Field Ablation in Metastatic Cancer. Cancers (Basel). 2025;17(21).
25. Arciga BM, Walters DM, Kimchi ET, Staveley-O’Carroll KF, Li G, Teixeiro E, et al. Pulsed electric field ablation as a candidate to enhance the anti-tumor immune response to immune checkpoint inhibitors. Cancer Lett. 2025;609:217361.
26. Zhang L, Dong S, Teng F, Wang Y, Xu W, Chen Y, et al. Pulsed electric fields: a sharp sword in the battle against cancers. Front Immunol. 2025;16:1682539.
27. Hamid O, Ismail R, Puzanov I. Intratumoral Immunotherapy-Update 2019. Oncologist. 2020;25(3):e423–e38.
28. Silihe Kamga K, Fiering S. Intratumoral immunotherapy prior to cancer surgery, a promising therapeutic approach. Front Immunol. 2025;16:1545000.
29. Skalickova M, Hadrava Vanova K, Uher O, Leischner Fialova J, Petrlakova K, Masarik M, et al. Injecting hope: the potential of intratumoral immunotherapy for locally advanced and metastatic cancer. Front Immunol. 2024;15:1479483.
30. Savjani R. Intratumoral Immunotherapy: A Potential Treatment for Gastrointestinal Malignancies. Radiol Imaging Cancer. 2021;3(3):e219011.
31. Sheth RA, Wehrenberg-Klee E, Patel SP, Brock KK, Fotiadis N, de Baère T. Intratumoral Injection of Immunotherapeutics: State of the Art and Future Directions. Radiology. 2024;312(1):e232654.
32. Wehrle CJ, Sayed Ahmed AF, Knott E, Hong H, Uysal M, Schlegel A, et al. The first full year of histotripsy for liver tumors: Local tumor control and preliminary oncologic efficacy. Surgery. 2026;191:109898.
33. Queen H, Ferris SF, Cho CS, Ganguly A. The Emerging Role of Histotripsy in Liver Cancer Treatment: A Scoping Review. Cancers (Basel). 2025;17(6).
34. Hoption Cann SA, van Netten JP, van Netten C. Dr William Coley and tumour regression: a place in history or in the future. Postgrad Med J. 2003;79(938):672–80.
35. Rao W, Deng ZS, Liu J. A review of hyperthermia combined with radiotherapy/chemotherapy on malignant tumors. Crit Rev Biomed Eng. 2010;38(1):101–16.
36. Baronzio G, Parmar G, Ballerini M, Szasz A, Baronzio M. A Brief Overview of Hyperthermia in Cancer Treatment. Integrative Oncology. 2014;3:115.
37. Warren SL. Preliminary study of the effects of artificial fever upon hopeless tumor cases. Am J Roentgenol Radium Ther. 1935;33:75–87.
38. Fiorentini G, Sarti D, Gadaleta CD, Ballerini M, Fiorentini C, Garfagno T, et al. A Narrative Review of Regional Hyperthermia: Updates From 2010 to 2019. Integr Cancer Ther. 2020;19:1534735420932648.
39. Hu Y, Li Z, Mi DH, Cao N, Zu SW, Wen ZZ, et al. Chemoradiation combined with regional hyperthermia for advanced oesophageal cancer: a systematic review and meta-analysis. J Clin Pharm Ther. 2017;42(2):155–64.
40. Huilgol NG, Gupta S, Sridhar CR. Hyperthermia with radiation in the treatment of locally advanced head and neck cancer: a report of randomized trial. J Cancer Res Ther. 2010;6(4):492–6.
41. Lukácsi S, Munkácsy G, Győrffy B. Harnessing Hyperthermia: Molecular, Cellular, and Immunological Insights for Enhanced Anticancer Therapies. Integr Cancer Ther. 2024;23:15347354241242094.
42. Datta NR, Kok HP, Crezee H, Gaipl US, Bodis S. Integrating Loco-Regional Hyperthermia Into the Current Oncology Practice: SWOT and TOWS Analyses. Front Oncol. 2020;10:819.
43. Issels RD, Lindner LH, Verweij J, Wust P, Reichardt P, Schem BC, et al. Neo-adjuvant chemotherapy alone or with regional hyperthermia for localised high-risk soft-tissue sarcoma: a randomised phase 3 multicentre study. Lancet Oncol. 2010;11(6):561–70.
44. Hohneck AL, Schmitz-Solheid V, Gencer D, Schroeder M, Riess H, Gerhards A, et al. Predictors of Successful Whole-Body Hyperthermia in Cancer Patients: Target Temperature Achievement and Safety Analysis. Cancers (Basel). 2025;17(16).
45. Moen I, Stuhr LE. Hyperbaric oxygen therapy and cancer--a review. Target Oncol. 2012;7(4):233–42.
46. Raa A, Stansberg C, Steen VM, Bjerkvig R, Reed RK, Stuhr LE. Hyperoxia retards growth and induces apoptosis and loss of glands and blood vessels in DMBA-induced rat mammary tumors. BMC Cancer. 2007;7:23.
47. Stuhr LE, Raa A, Oyan AM, Kalland KH, Sakariassen PO, Petersen K, et al. Hyperoxia retards growth and induces apoptosis, changes in vascular density and gene expression in transplanted gliomas in nude rats. J Neurooncol. 2007;85(2):191–202.
48. Gore A, Muralidhar M, Espey MG, Degenhardt K, Mantell LL. Hyperoxia sensing: from molecular mechanisms to significance in disease. J Immunotoxicol. 2010;7(4):239–54.
49. Moen I, Oyan AM, Kalland KH, Tronstad KJ, Akslen LA, Chekenya M, et al. Hyperoxic treatment induces mesenchymal-to-epithelial transition in a rat adenocarcinoma model. PloS ONE. 2009;4(7):e6381.
50. Poff AM, Ari C, Seyfried TN, D’Agostino DP. The ketogenic diet and hyperbaric oxygen therapy prolong survival in mice with systemic metastatic cancer. PloS ONE. 2013;8(6):e65522.
51. Bennett MH, Feldmeier J, Smee R, Milross C. Hyperbaric oxygenation for tumour sensitisation to radiotherapy. Cochrane Database Syst. Rev. 2018;4(4):CD005007.
does she have cancer; then yes. If no, the would not, instead nattokinase, aged garlic extract, good diet, etc.
His IL-15 (interleukin-15) preparation is not all that it is made to be.. and its very very expensive. Aged Garlic Extract increases T-killer cells at a fraction of the price.