
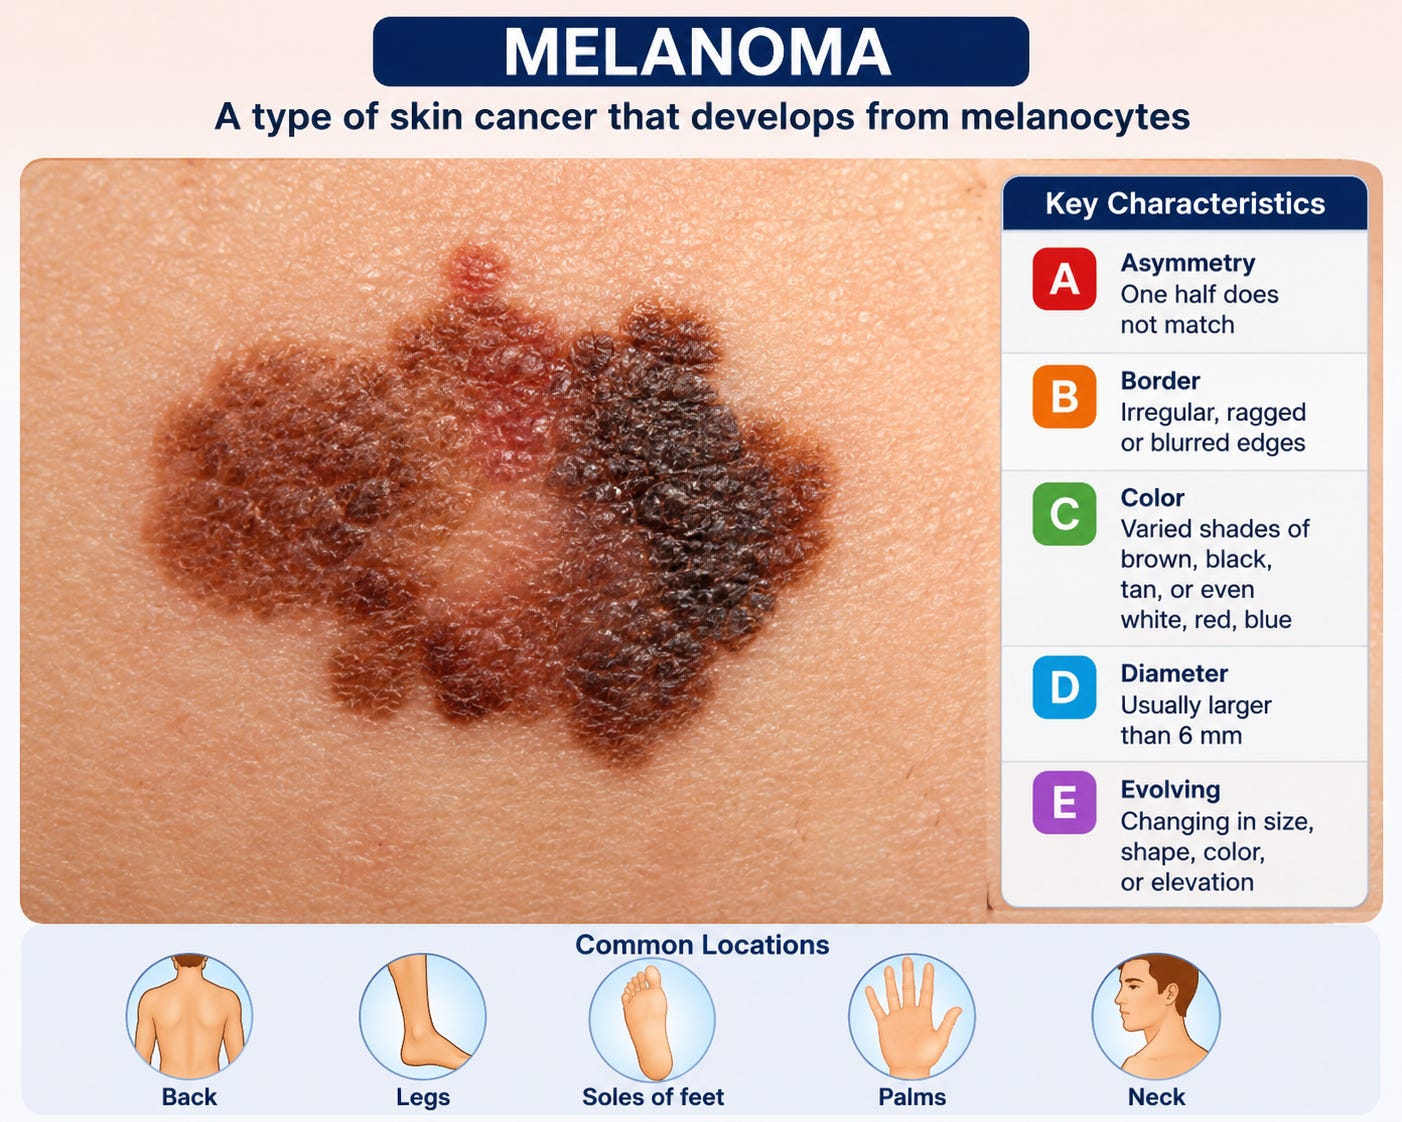
Melanoma is a malignant tumor arising from melanocytes, the pigment-producing cells of the skin. Although it accounts for only a small proportion of skin cancers, it is responsible for the majority of skin-cancer–related deaths because of its strong metastatic potential.

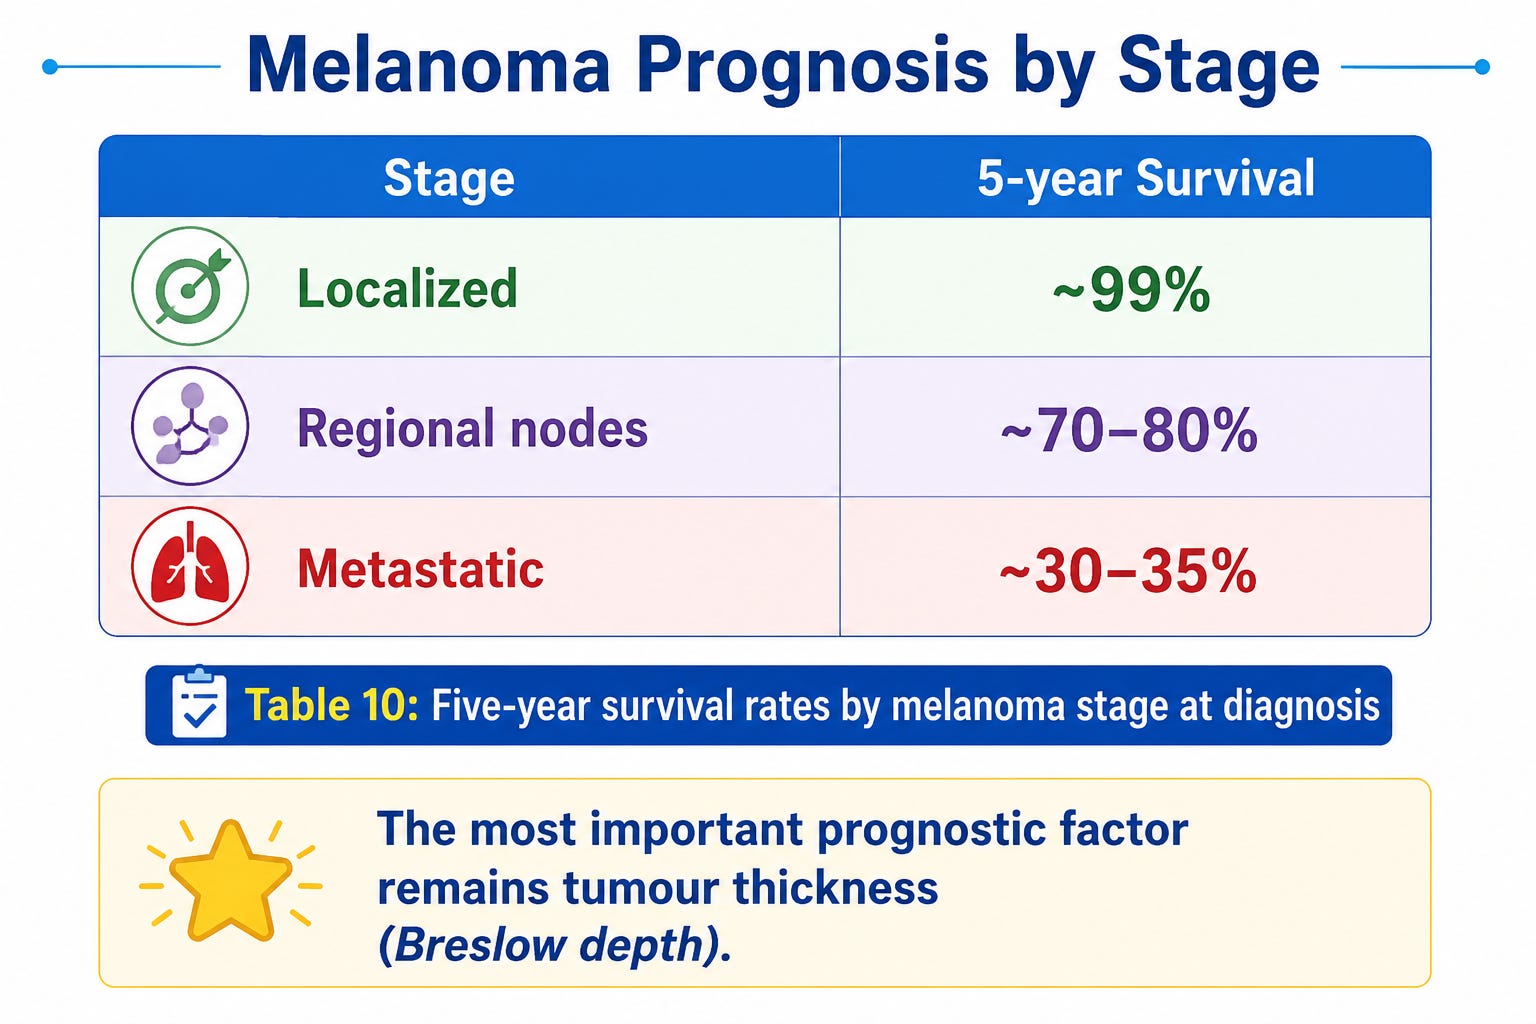
Notes
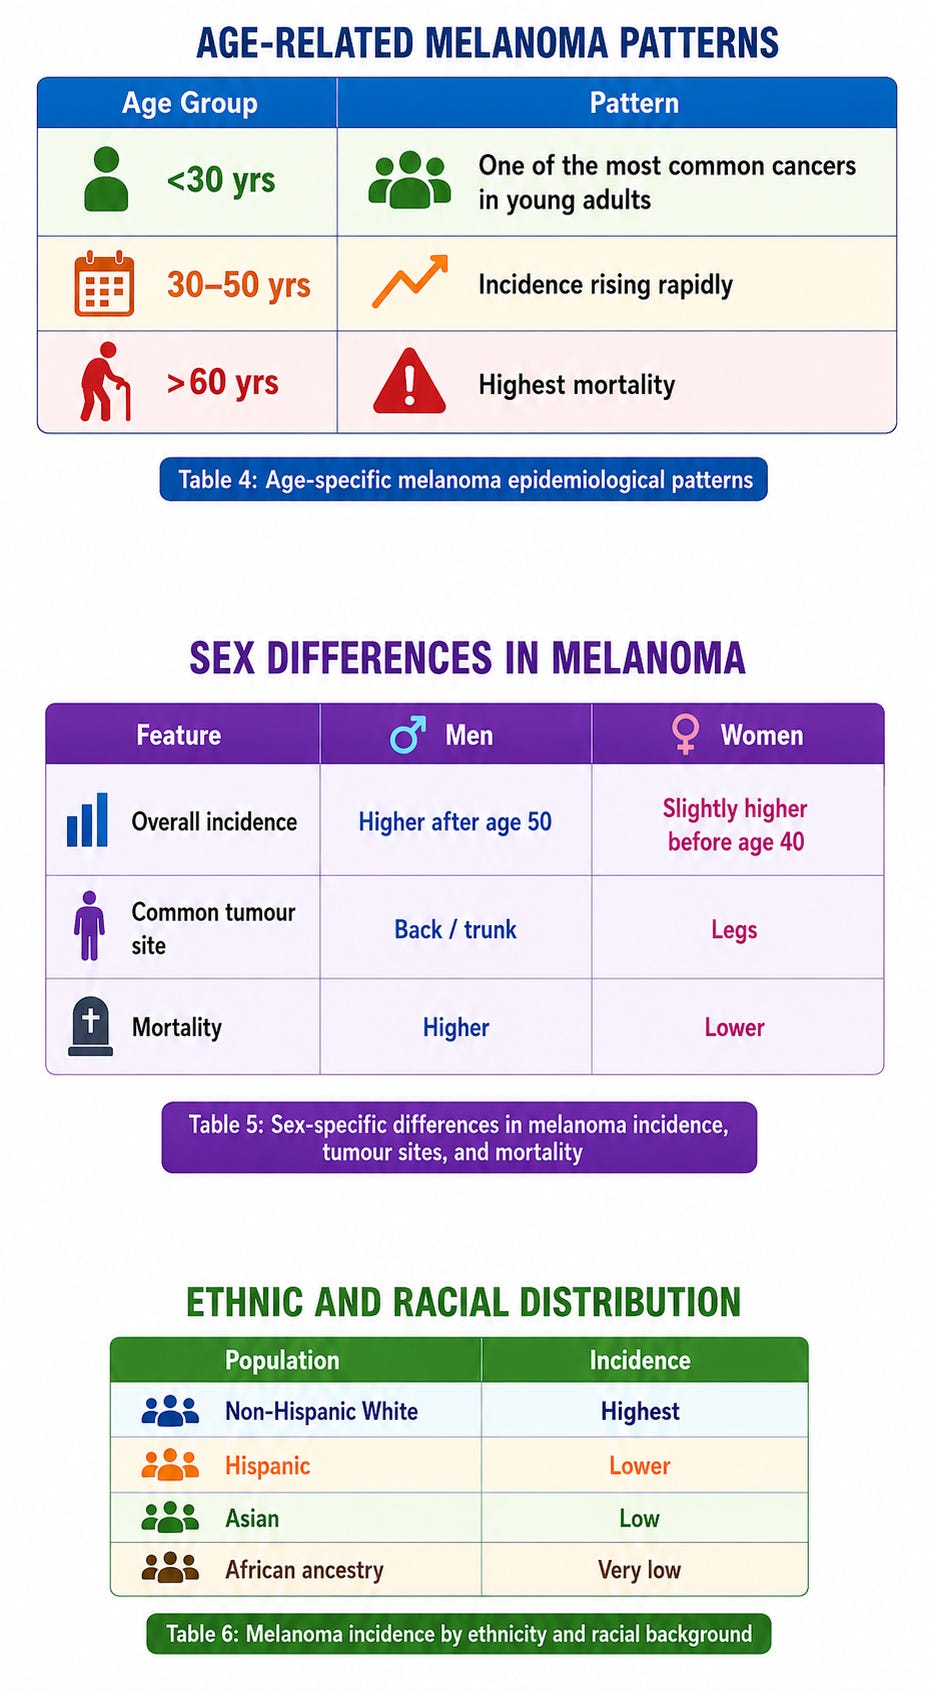
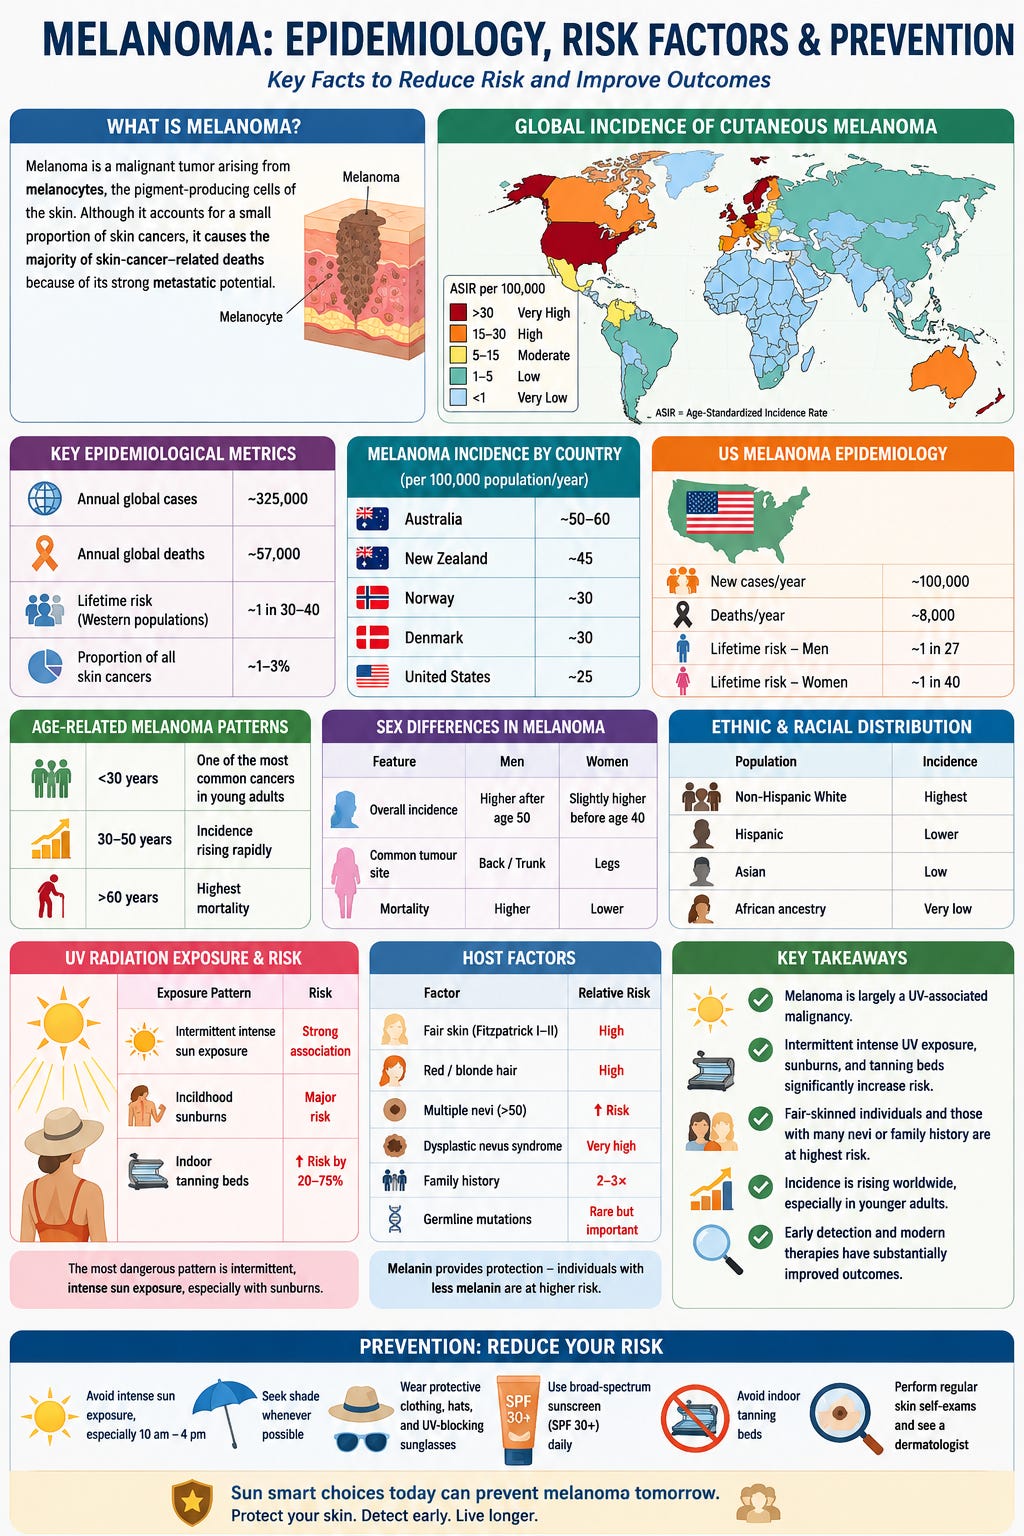
These tables present key epidemiological metrics for melanoma skin cancer. The first table shows global incidence, mortality, lifetime risk in Western populations, and the relative proportion among all skin cancer types. The second table highlights melanoma incidence rates in countries with the highest burden, demonstrating the significant geographic variation in melanoma risk. Australia and New Zealand show the highest incidence rates globally, reflecting the impact of UV exposure in populations with predominantly fair skin types and high sun exposure. The third table focuses on US-specific data, showing approximately 100,000 new cases and 8,000 deaths annually, with men having a higher lifetime risk than women. The fourth table illustrates age-related patterns, showing melanoma’s unique epidemiology across the lifespan: it is one of the most common cancers in young adults under 30, shows rapidly rising incidence in the 30-50 age group, and demonstrates highest mortality in those over 60. The fifth table demonstrates important sex-based differences in melanoma presentation and outcomes, with distinct patterns in age-related incidence, anatomical distribution, and mortality rates.
Important Epidemiologic Observations
Several features of melanoma epidemiology are particularly striking:
Explosive rise since the 1970s
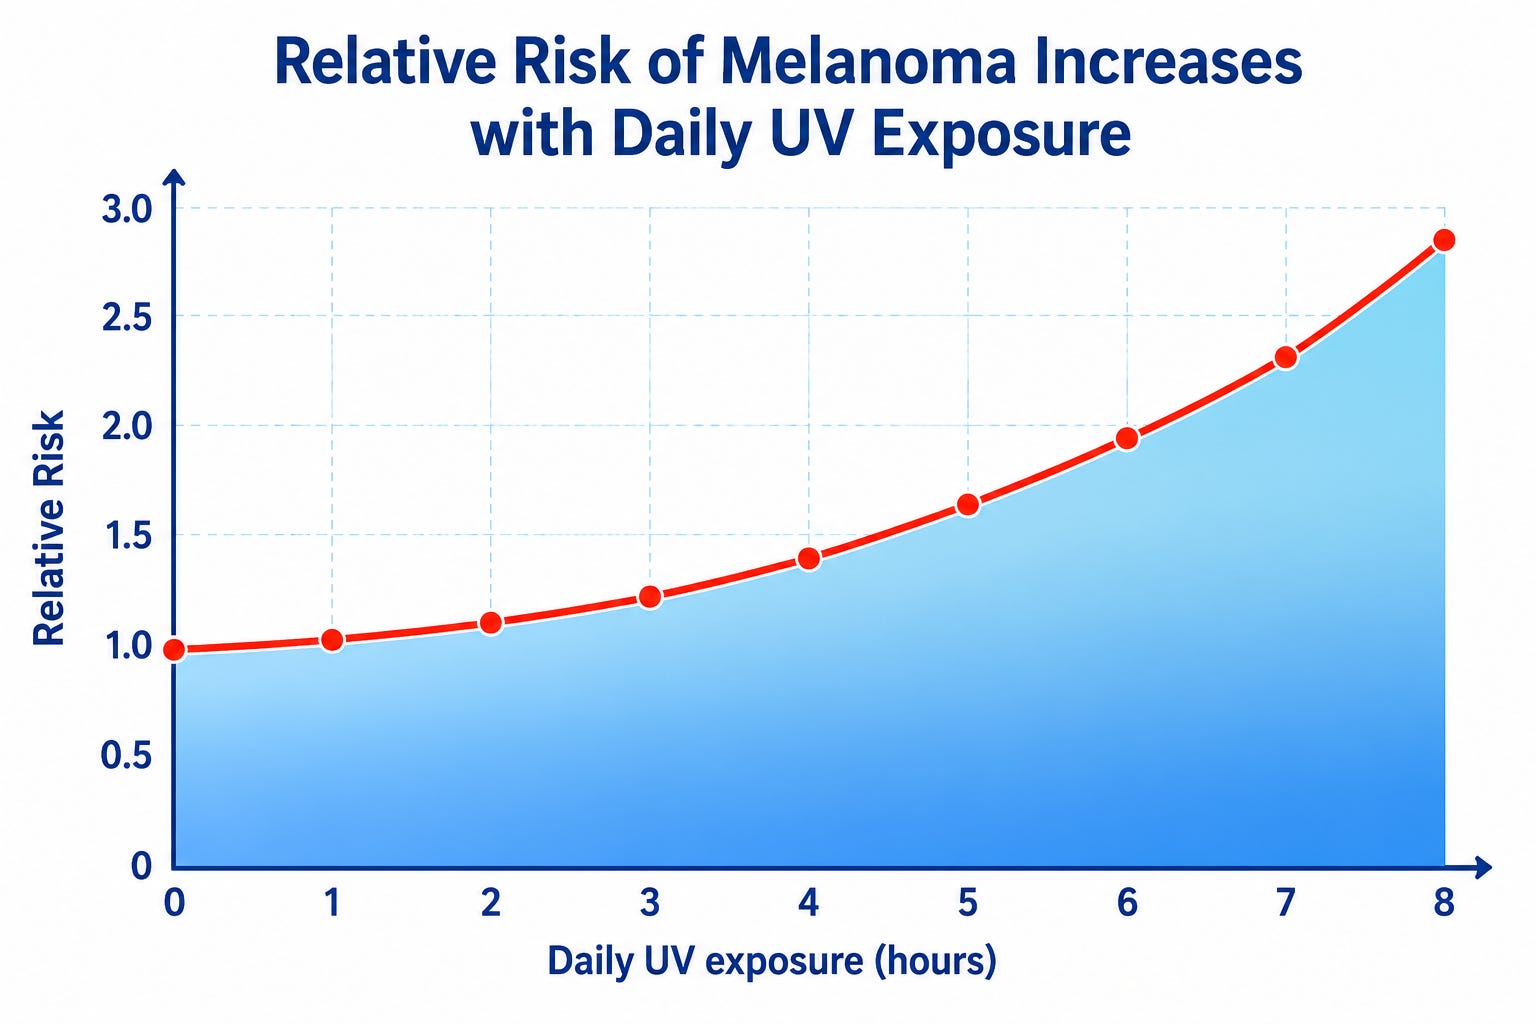
Strong link with intermittent UV exposure
Marked geographic variation
Higher risk in fair-skinned populations
Increasing incidence in younger adults
✅ Key epidemiologic message
Melanoma is largely a UV-associated malignancy occurring predominantly in genetically susceptible individuals, but early detection and modern therapies have substantially improved outcomes.
Figure 1. Global Incidence of Melanoma
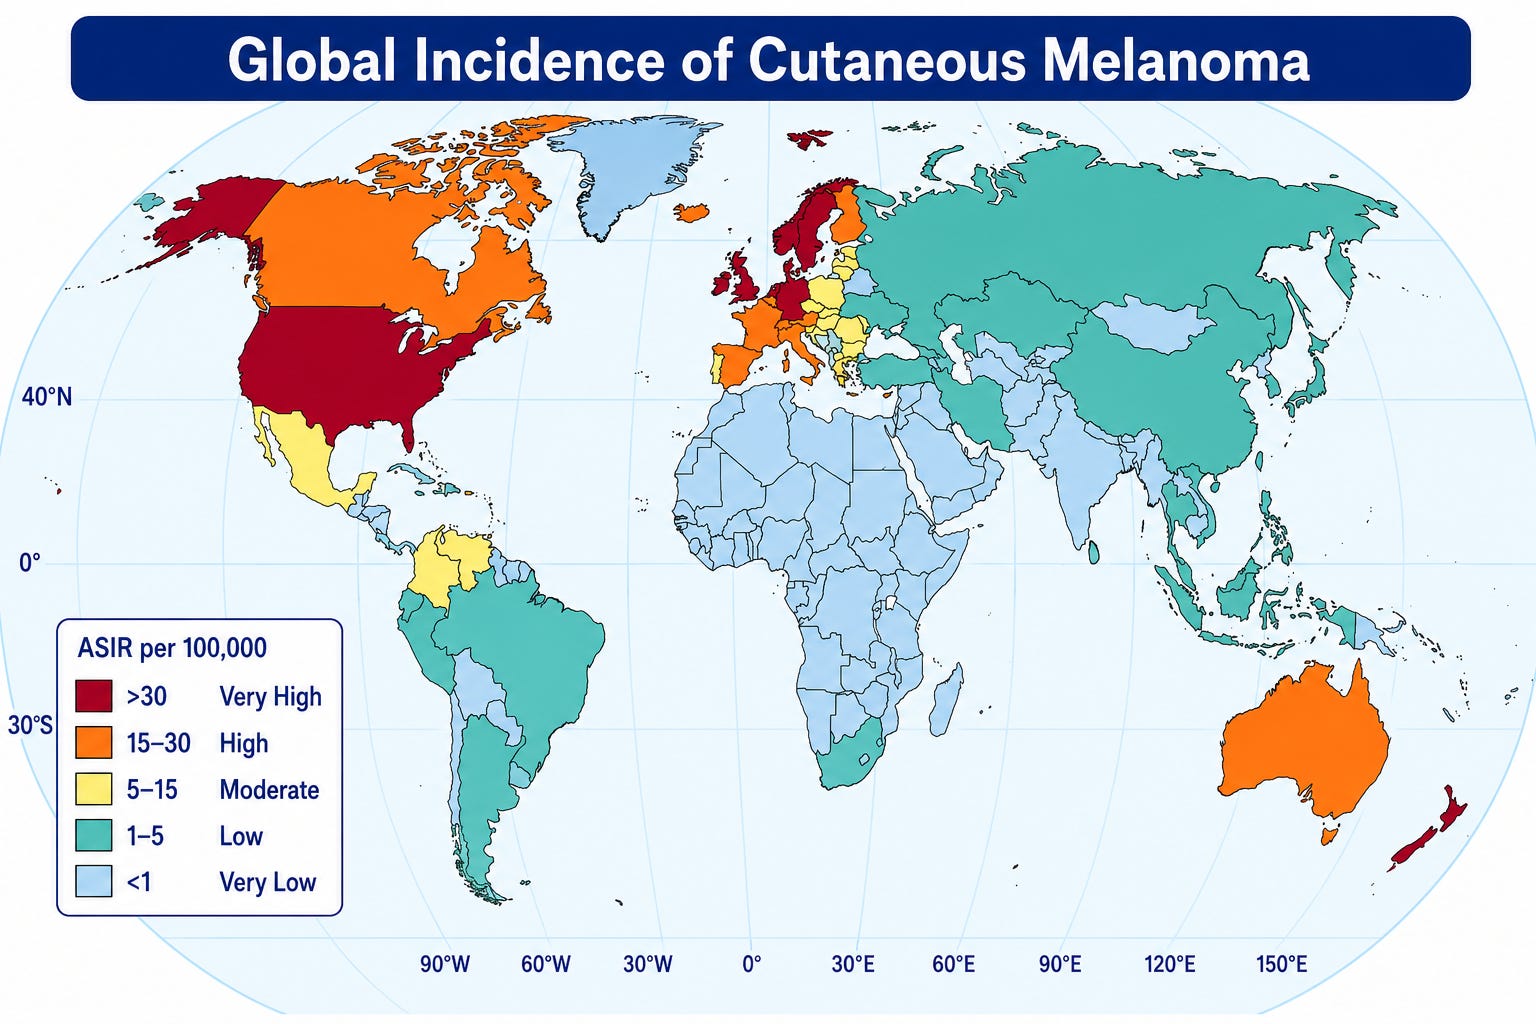
Figure 2. Daily UV exposure and risk of melanoma
Does Excessive Sun Tanning Cause Melanoma?
Short answer: Yes — excessive ultraviolet (UV) exposure from sun tanning is a major causal factor in melanoma.
However, the relationship is more nuanced than “any sun exposure causes melanoma.” The pattern and intensity of UV exposure matter greatly.
1. Ultraviolet Radiation Is the Primary Environmental Cause
Melanoma is strongly linked to UV radiation (UVR) from:
Sunlight
Tanning beds
UV radiation damages DNA in melanocytes through:
Direct DNA photoproducts (cyclobutane pyrimidine dimers)
Oxidative stress
Mutation of tumor suppressor genes
Common melanoma mutations associated with UV damage include:
BRAF
NRAS
TP53
Large epidemiologic studies show that UV signature mutations are present in the majority of cutaneous melanomas.
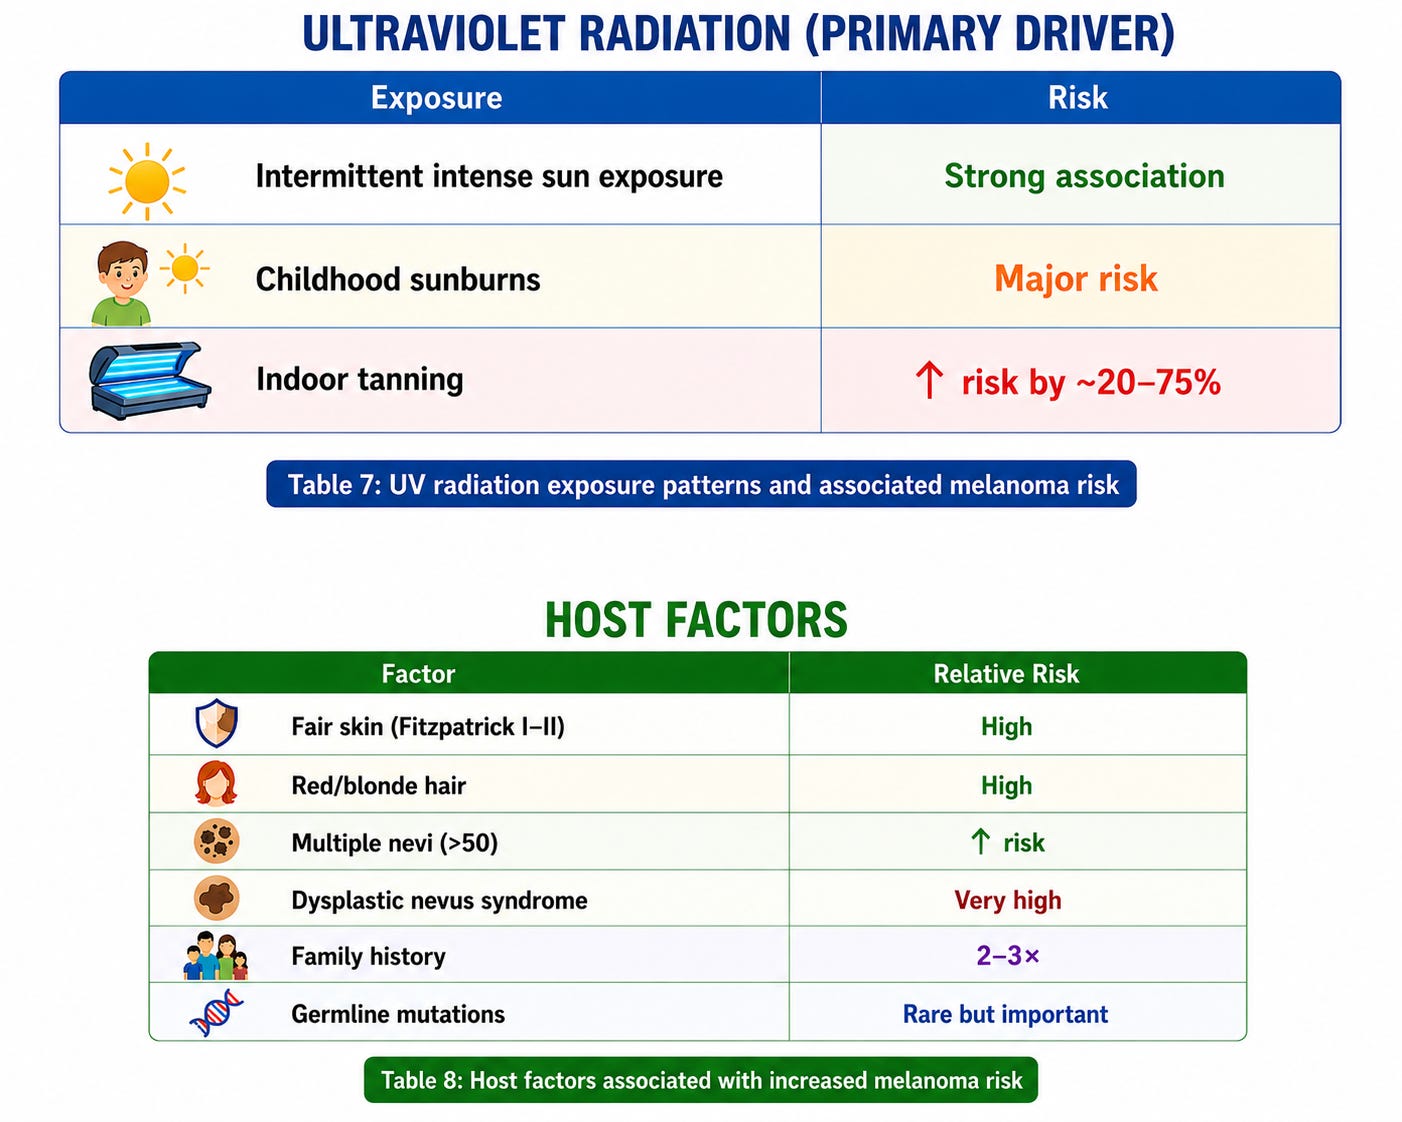
2. Intermittent Intense Exposure Is the Most Dangerous Pattern
Interestingly, melanoma risk correlates most strongly with:
Intermittent, intense sun exposure rather than continuous exposure.
High-risk pattern:
Occasional intense sun exposure
Severe sunburns
Vacation sun exposure
Indoor workers suddenly exposed to strong sunlight
Especially dangerous:
Childhood and adolescent sunburns
People with ≥5 severe sunburns have about a 2–3× higher melanoma risk.
3. Tanning Beds Increase Risk
Artificial UV tanning is clearly linked to melanoma.
Meta-analyses show:
~20–30% increased melanoma risk with tanning bed use
~75% increased risk if tanning begins before age 35
Because of this, many countries restrict tanning bed use in minors.
4. Why Fair-Skinned People Are Most Vulnerable
Melanin protects against UV damage.
Higher melanoma risk occurs in people with:
Fair skin
Red or blond hair
Blue/green eyes
Freckles
Poor tanning ability
These individuals accumulate UV-induced DNA damage more rapidly.
5. Chronic Sun Exposure Is More Linked to Other Skin Cancers
Interestingly, the cancers most associated with chronic daily sun exposure are:
Basal cell carcinoma
Squamous cell carcinoma
Melanoma tends to arise more often with intermittent intense UV exposure.
6. Sun Exposure Is Not the Only Cause
Although UV radiation is a major driver, melanoma can also occur without heavy sun exposure.
Examples:
Acral melanoma (palms, soles, nail beds)
Mucosal melanoma
Uveal melanoma
These subtypes are not strongly UV-related.
Genetic predisposition also contributes.
7. A Key Epidemiologic Paradox
An interesting observation in melanoma research:
People with moderate regular sun exposure sometimes have lower melanoma risk than those with intermittent exposure.
Possible explanations include:
Skin adaptation
Increased melanin production
Vitamin D effects
Avoidance of severe sunburns
But intentional tanning is not considered protective.
✅ Bottom line
Excessive UV exposure — especially sunburn and tanning beds — clearly increases melanoma risk.
The most dangerous pattern is intermittent intense sun exposure rather than steady moderate exposure.
Explaining the paradox, that melanoma occurs most frequently in areas not sun exposed.
This paradox has puzzled dermatologists for decades. At first glance it seems contradictory: UV radiation is the major environmental cause of melanoma, yet many melanomas arise on body sites that receive little routine sun exposure (back, trunk, thighs). Once you look more closely at how melanoma develops, the “paradox” starts to make sense.
1. Intermittent Sun Exposure vs Chronic Exposure
The key insight is that melanoma is linked most strongly to intermittent intense UV exposure, not continuous daily exposure.
Typical high-risk pattern:
Indoor lifestyle most of the year
Sudden intense sun exposure (vacations, beach days)
Episodes of sunburn
During these exposures, normally covered areas like:
back
chest
upper thighs
receive large bursts of UV radiation, which can produce significant DNA damage in melanocytes.
So those sites are not truly “unexposed.” They are episodically overexposed.
2. Body Sites With Many Melanocytes
The trunk contains a high density of melanocytes and nevi (moles).
Melanoma frequently arises from:
pre-existing nevi
dysplastic nevi
These are particularly common on:
the back
the chest
This partly explains why the trunk is the most common site in men.
3. Chronic Sun Exposure Causes Different Skin Cancers
Another important point:
Chronic UV exposure tends to produce different cancers.
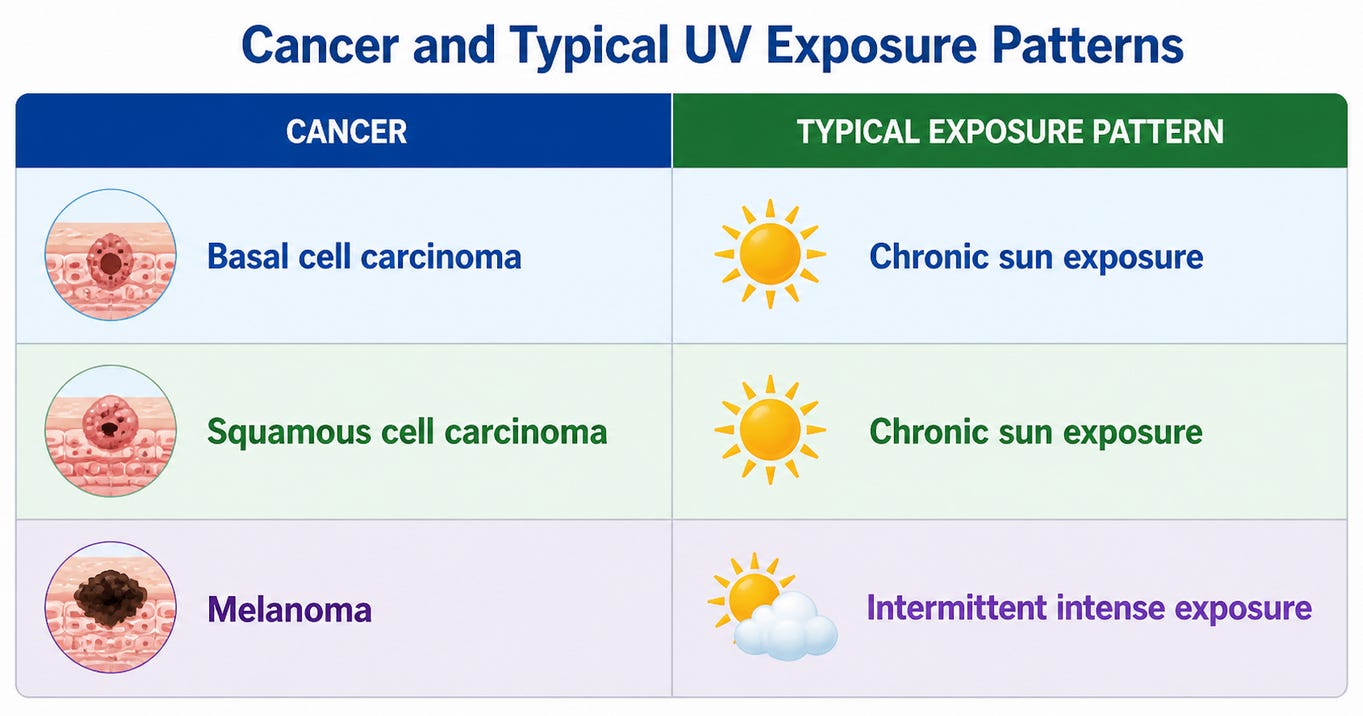
So areas constantly exposed to sun (face, scalp, hands) more often develop keratinocyte cancers, not melanoma.
4. Skin Adaptation and Photoprotection
Skin that is chronically exposed to sunlight develops protective changes:
thickened epidermis
increased melanin
enhanced DNA repair
This adaptation may reduce melanoma risk compared with skin that is normally protected but suddenly exposed.
5. Sex Differences Support the Theory
Melanoma distribution varies with clothing patterns.
Men
most common site: back and trunk
Women
most common site: legs
These are areas that often experience intermittent UV exposure.
6. Some Melanomas Are Not UV-Driven
A minority of melanomas occur in areas unrelated to sun exposure:
acral melanoma (palms, soles, nail beds)
mucosal melanoma
uveal melanoma
These likely arise from different biological mechanisms.
✅ The “melanoma paradox” summarized
Melanoma often appears on seemingly sun-protected areas because the highest risk comes from intermittent intense UV exposure to previously protected skin, not from constant daily sun exposure.
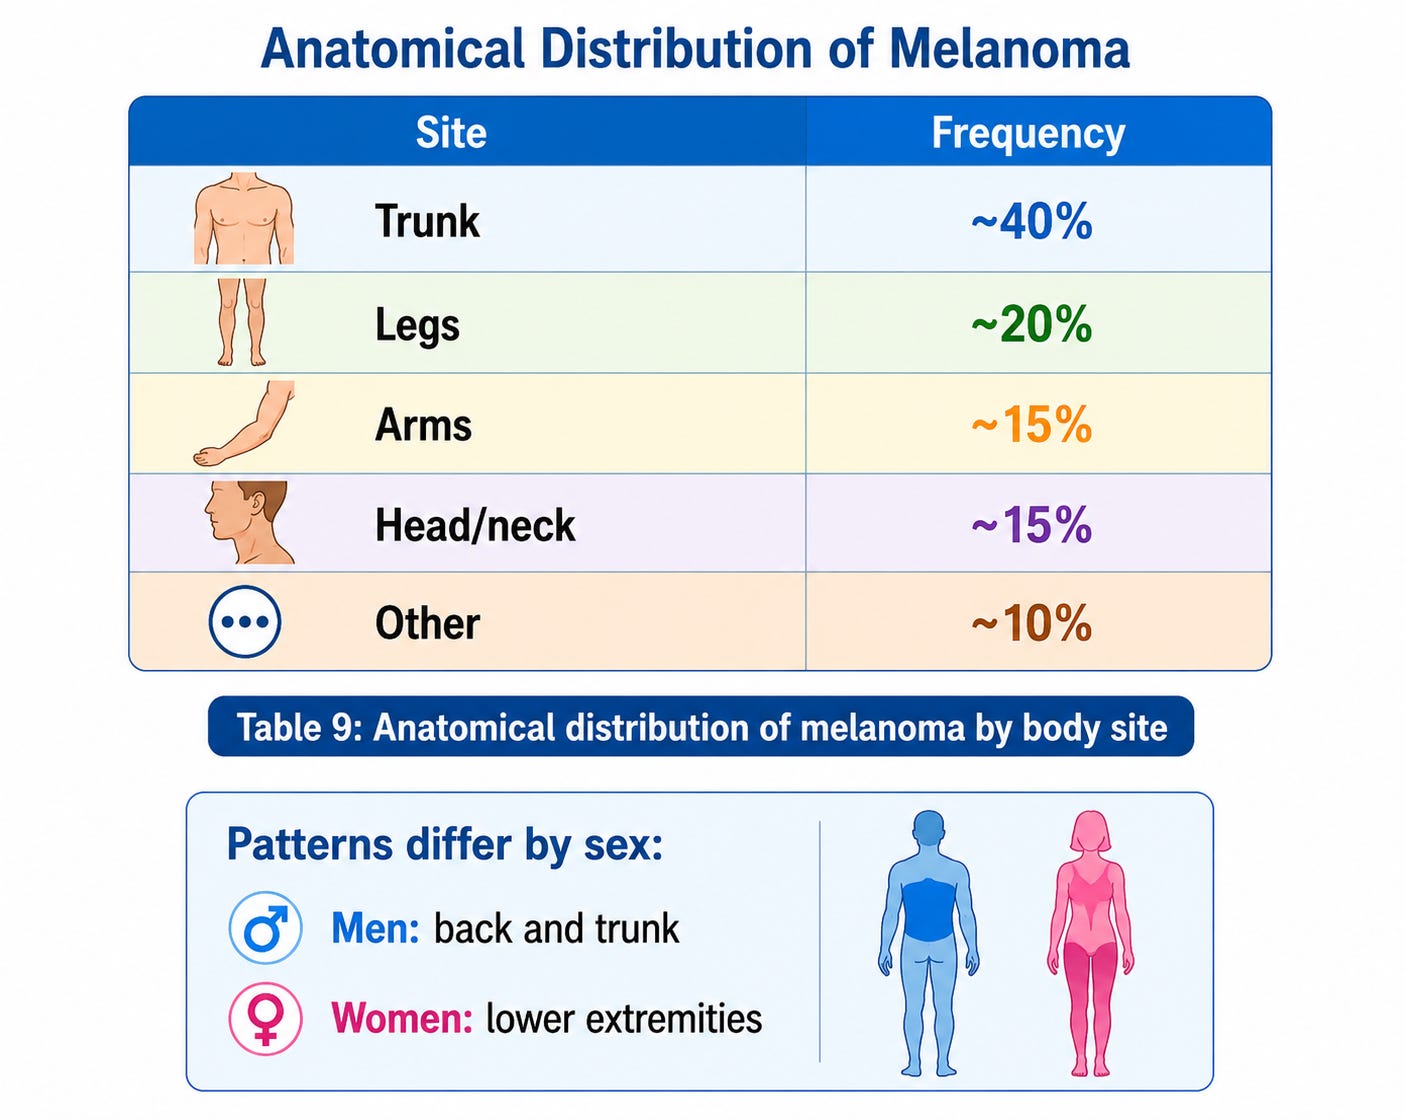
Body-Site Pattern of Melanoma
Across many countries and decades of data, melanoma shows a remarkably consistent anatomical pattern.
Overall distribution
Approximate proportions:
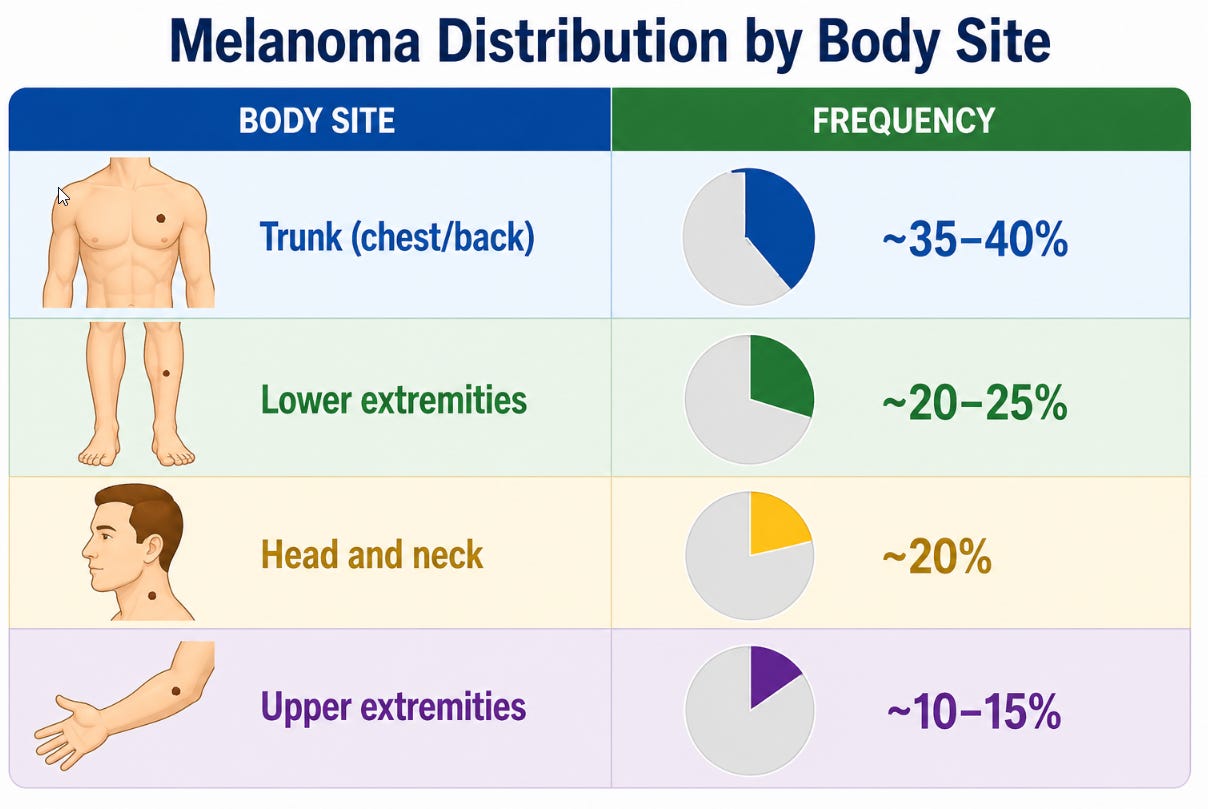
However, the interesting patterns appear when you separate by sex, age, and latitude.
1. Strong Sex Differences
Men
Most common site:
Back and trunk
Reasons likely include:
intermittent sun exposure (beach, outdoor sports)
shirtless exposure
large numbers of nevi on the back
Back melanoma is actually one of the most characteristic epidemiologic findings in male melanoma.
Women
Most common site:
Legs
This pattern has been extremely consistent for decades.
Possible explanations:
clothing patterns (skirts, shorts)
intermittent sun exposure
shaving trauma to nevi (possible minor factor)
2. Age Changes the Pattern
Melanoma location also shifts with age.
Younger patients
More common on:
trunk
legs
This corresponds with intermittent recreational sun exposure.
Older patients
More common on:
head and neck
This likely reflects cumulative lifetime sun exposure.
3. Latitude Matters
Latitude produces another striking gradient.
High-UV countries
Examples:
Australia
New Zealand
Southern United States
More melanomas on:
trunk
shoulders
These areas get intense sun exposure during recreation.
Northern latitudes
Examples:
Scandinavia
Northern Europe
More melanomas on:
intermittently exposed sites
Because sunlight is weaker and exposure tends to occur during vacations or summer bursts.
4. What This Pattern Reveals About UV Exposure
Putting these observations together tells a clear story.
Melanoma risk is driven largely by:
Intermittent intense UV exposure to previously protected skin.
Typical scenario:
Indoor living
Occasional intense sun exposure
Severe sunburn
This explains why melanoma often occurs on:
back
shoulders
thighs
rather than on constantly sun-exposed areas like the face.
5. The “Nevus Distribution” Clue
Another layer of the puzzle:
Melanoma frequently arises from pre-existing nevi (moles).
And nevi are most common on the trunk.
So the trunk is essentially a melanocyte-rich landscape where UV bursts can trigger malignant transformation.
✅ Key epidemiologic insight
The body-site pattern of melanoma strongly supports the theory that episodic UV injury interacting with nevus biology is the major driver of melanoma development.
Sunscreen and Skin Cancer Risk
1. Strong evidence for non-melanoma skin cancers
There is good clinical evidence that regular sunscreen use reduces:
Squamous cell carcinoma (SCC) strongest evidence
Actinic keratoses (precancerous lesions)
The landmark Australian randomized trial (Green et al., JCO 2011) followed people for 4.5 years and found:
~40% reduction in squamous cell carcinoma in the daily sunscreen group.
Basal cell carcinoma reductions were less clear, probably because BCC develops after decades of sun exposure.
2. Evidence that sunscreen reduces melanoma risk
Melanoma is rarer and takes longer to develop, so studies are harder to perform. However:
The same Australian randomized trial later showed a ~50% reduction in invasive melanoma in people using daily sunscreen during follow-up.
Large cohort studies in Europe and Australia show consistent trends toward lower melanoma risk in regular sunscreen users.
So overall, most dermatologists and epidemiologists conclude:
Regular sunscreen use likely reduces melanoma risk.
3. Why earlier studies were confusing
Older observational studies sometimes suggested higher melanoma rates in sunscreen users. That paradox occurred because:
People who use sunscreen often
→ spend more time in the sun
→ or have sun-sensitive skin
This is called “confounding by indication.”
When randomized trials control for this, sunscreen shows protective effects.
4. The key factor: how sunscreen is used
Sunscreen protects best when used properly:
Important points:
Broad spectrum (UVA + UVB)
SPF ≥30
Reapply every ~2 hours
Apply adequate quantity (most people apply only ~25–50% of recommended amount)
Use with shade, hats, and clothing
Sunscreen alone is not enough protection if someone intentionally sunbathes for long periods.
5. A key epidemiologic insight
Interestingly:
Chronic occupational sun exposure (farmers, sailors)
→ lower melanoma ratesIntermittent intense exposure (sunburns, vacations)
→ much higher melanoma risk
So the biggest risk factor is actually:
intermittent high-dose UV exposure causing sunburn.
✅ Bottom line
Sunscreen clearly reduces squamous cell carcinoma.
Evidence strongly suggests it also reduces melanoma risk, especially when used regularly.
The greatest protection comes from avoiding sunburn and intense intermittent UV exposure.
New Here?
Start with the: Cancer and the Metabolic Library

I think there is a difference between being exposed to the sun and getting blistering sunburn.
Thanks my friend.. I have taken some heat on this.