

Am I WRONG
My recent post on melanoma generated a surprising amount of feedback—some of it quite vigorous. Two criticisms came up repeatedly.
The first was that ultraviolet (UV) radiation is not a cause of melanoma, a view promoted by the Midwestern Doctor (see below) The second was that the dramatic increase in seed oil consumption is the principal reason melanoma rates have risen over the past several decades.
Whenever readers challenge my interpretation of the evidence, I try to approach the issue with an open mind. I therefore went back to the literature and carefully re-examined the available data.
My conclusions
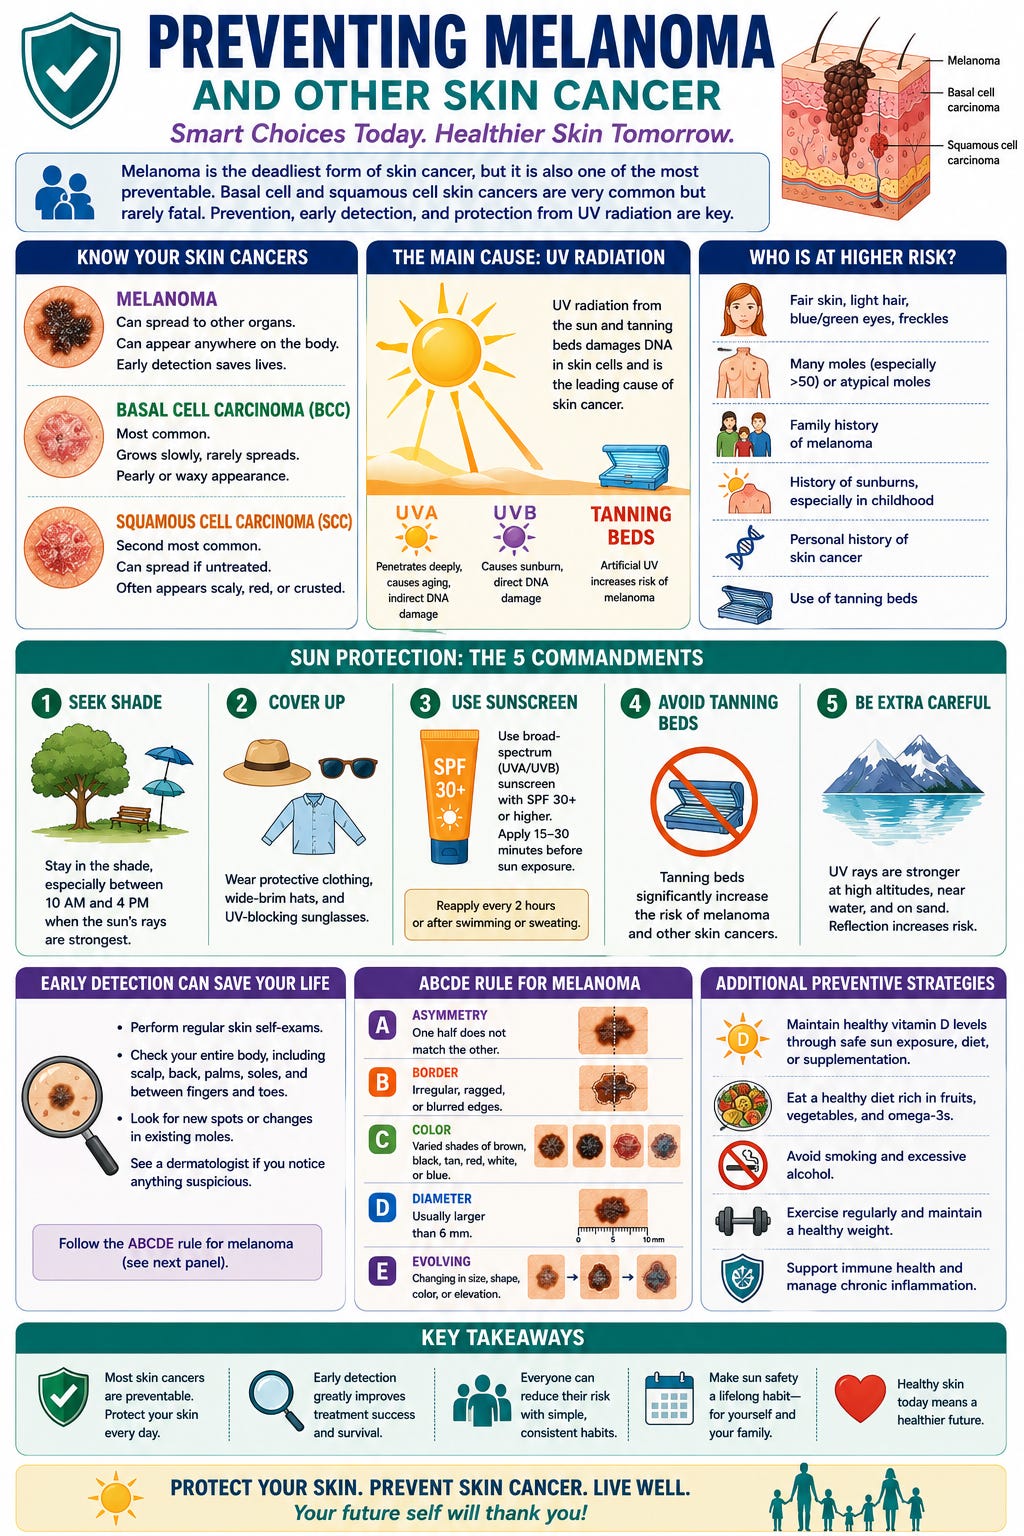
After reviewing the evidence, I remain convinced that UV radiation is the best-established environmental risk factor for melanoma.
UV radiation damages the DNA of melanocytes—the pigment-producing cells of the skin—creating mutations that can initiate malignant transformation. It also suppresses the skin’s local immune surveillance, reducing its ability to recognize and eliminate abnormal cells before they develop into cancer.
Melanoma differs from basal cell and squamous cell carcinoma in an important way. Rather than correlating primarily with lifetime cumulative sun exposure, melanoma is most strongly associated with intermittent, intense UV exposure, particularly blistering sunburns during childhood and adolescence, as well as indoor tanning bed use.
That said, UV radiation is not the whole story. Melanoma is a multifactorial disease. Genetic susceptibility—including fair skin, poor tanning ability, numerous or atypical moles, and a family history of melanoma—interacts with environmental exposures to determine an individual’s overall risk. UV exposure is therefore best viewed as an important contributor rather than the sole cause. It is also likely that other factors such as obesity, insulin resistance, high carbohydrate diet, ingestion of chemicals and carcinogens, smoking, air pollution and exposure to pesticides may play a role.
The evidence for seed oils is considerably less robust.
A handful of small observational studies have reported associations between higher intake of vegetable oils or linoleic acid and an increased risk of melanoma. There is also a biologically plausible mechanism: linoleic acid within cell membranes could undergo UV-induced lipid peroxidation, generating reactive by-products capable of damaging DNA and other cellular structures.
However, biological plausibility is not the same as clinical proof.
The available human studies are subject to important confounding factors, including differences in sun exposure, body weight, physical activity, and overall dietary patterns. Consequently, the frequently repeated claim that seed oils act like “gasoline on the fire,” dramatically amplifying UV-induced melanoma, goes well beyond what the current evidence can support.
This does not mean seed oils play no role. They may indeed contribute to melanoma risk, and this hypothesis deserves further investigation. However, based on the current body of evidence, their contribution—if any—appears to be secondary to the well-established effects of excessive UV exposure.
A final point about sunlight
Some readers interpreted my previous article as advocating that people should avoid the sun altogether. That is not my position.
Sunlight is fundamental to human health. It regulates our circadian rhythm, supports vitamin D production, influences immune function, and contributes to overall metabolic and psychological well-being.
The goal should not be to fear the sun, but to respect it.
For most people, this means enjoying regular sunlight exposure while avoiding excessive exposure and, most importantly, avoiding sunburn. Like many things in medicine, the relationship between sunlight and health is not black and white. Both too little sunlight and too much can be harmful. The challenge is finding the balance that allows us to benefit from the sun while minimizing its risks.
As always, I am prepared to change my views if higher-quality evidence emerges. That is how science should work.
One additional point.. the use of sunscreens and melanoma
Several early observational studies reported that regular sunscreen users appeared to have a higher incidence of melanoma. However, these studies were subject to important sources of bias. People most likely to use sunscreen are also those at highest baseline risk—individuals with fair skin, numerous moles, or heavy sun exposure. Many sunscreen users also stay in the sun longer, increasing their cumulative UV dose, a phenomenon known as the "sunscreen paradox." When the totality of the evidence is considered, including several large meta-analyses, there is no convincing evidence that sunscreen itself increases the risk of melanoma. Rather, the apparent association is largely explained by confounding and behavioral factors. Sunscreen should therefore be viewed as one component of a broader sun-protection strategy that also includes avoiding sunburn, limiting excessive UV exposure, wearing protective clothing, and seeking shade when appropriate.

A summary of my previous post:
Now back to my original post.
Repurposed Drugs and Nutraceuticals That May Reduce Melanoma Risk
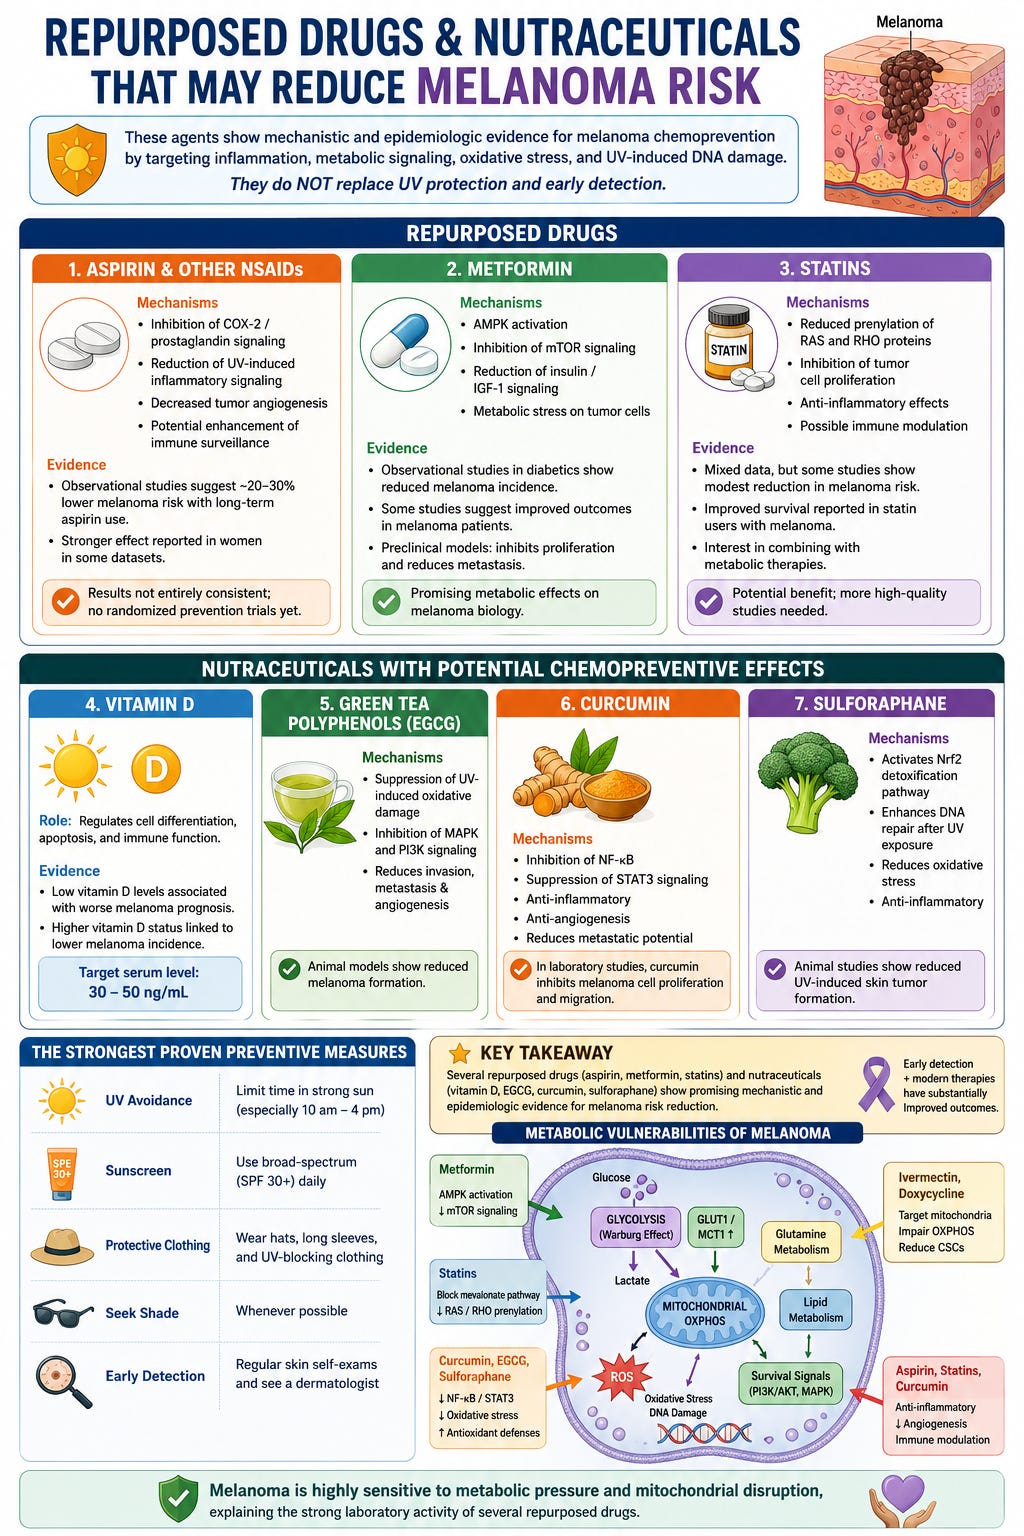
There is growing interest in whether repurposed drugs and selected nutraceuticals might help reduce the risk of melanoma by targeting biological pathways involved in carcinogenesis, including chronic inflammation, metabolic signaling, oxidative stress, and UV-induced DNA damage. Although none of these agents should be considered a substitute for established preventive measures—such as limiting excessive UV exposure, using appropriate sun protection, and regular skin surveillance—several have shown promising mechanistic and epidemiologic evidence suggesting potential chemopreventive benefits. At present, these agents are best viewed as adjuncts to, rather than replacements for, proven strategies that reduce UV exposure and promote early detection.
1. Aspirin and Other NSAIDs
Mechanisms
Inhibition of COX-2 / prostaglandin signaling
Reduction of UV-induced inflammatory signaling
Decreased tumor angiogenesis
Potential enhancement of immune surveillance
Evidence
Several observational studies suggest that regular aspirin use may modestly reduce melanoma risk, particularly with long-term use.
Example findings:
~20–30% lower melanoma risk in some cohort analyses
Stronger effect reported in women in some datasets
However, results are not entirely consistent, and randomized prevention trials are lacking.
2. Metformin
Mechanisms
Metformin may influence melanoma development through:
AMPK activation
Inhibition of mTOR signaling
Reduction of insulin / IGF-1 signaling
Metabolic stress on tumor cells
Evidence
Observational studies in diabetics suggest:
Reduced melanoma incidence
Potential improvement in outcomes in some melanoma patients
Preclinical models show that metformin can inhibit melanoma cell proliferation and reduce metastatic potential.
3. Statins
Statins inhibit HMG-CoA reductase, suppressing the mevalonate pathway, which plays an important role in cancer signaling.
Mechanisms
Reduced prenylation of RAS and RHO proteins
Inhibition of tumor cell proliferation
Anti-inflammatory effects
Possible immune modulation
Evidence
Data are mixed, but some studies show:
modest reduction in melanoma risk
improved survival in statin users with melanoma
Interest is increasing in combining statins with metabolic therapies.
Nutraceuticals With Potential Melanoma Chemoprevention
4. Vitamin D
Vitamin D signaling influences cell differentiation, apoptosis, and immune regulation.
Evidence
Low vitamin D levels correlate with worse melanoma prognosis
Some epidemiologic studies suggest lower incidence with higher vitamin D status
Typical preventive target serum level:
30–50 ng/mL
5. Green Tea Polyphenols (EGCG)
The major green tea catechin EGCG has several anti-melanoma effects.
Mechanisms
Suppression of UV-induced oxidative damage
Inhibition of MAPK and PI3K signaling
Reduction of tumor invasion and metastasis
Anti-angiogenic activity
Animal models show reduced melanoma formation with green tea polyphenols.
6. Curcumin
Curcumin has multiple anti-cancer effects relevant to melanoma.
Mechanisms
Inhibition of NF-κB
Suppression of STAT3 signaling
Anti-inflammatory effects
Anti-angiogenesis
Reduction of metastatic potential
In laboratory studies, curcumin inhibits melanoma cell proliferation and migration.
7. Sulforaphane
Sulforaphane from broccoli sprouts activates cellular antioxidant defenses.
Mechanisms
Activation of Nrf2 detoxification pathway
Enhanced DNA repair after UV exposure
Reduction in oxidative stress
Anti-inflammatory effects
Animal studies show reduced UV-induced skin tumor formation.
✅ Key Takeaway
The strongest proven preventive measures for melanoma remain:
UV avoidance
sunscreen
protective clothing
early detection
However, several repurposed drugs (aspirin, metformin, statins) and nutraceuticals (vitamin D, EGCG, curcumin, sulforaphane) show promising mechanistic and epidemiologic evidence for melanoma risk reduction.
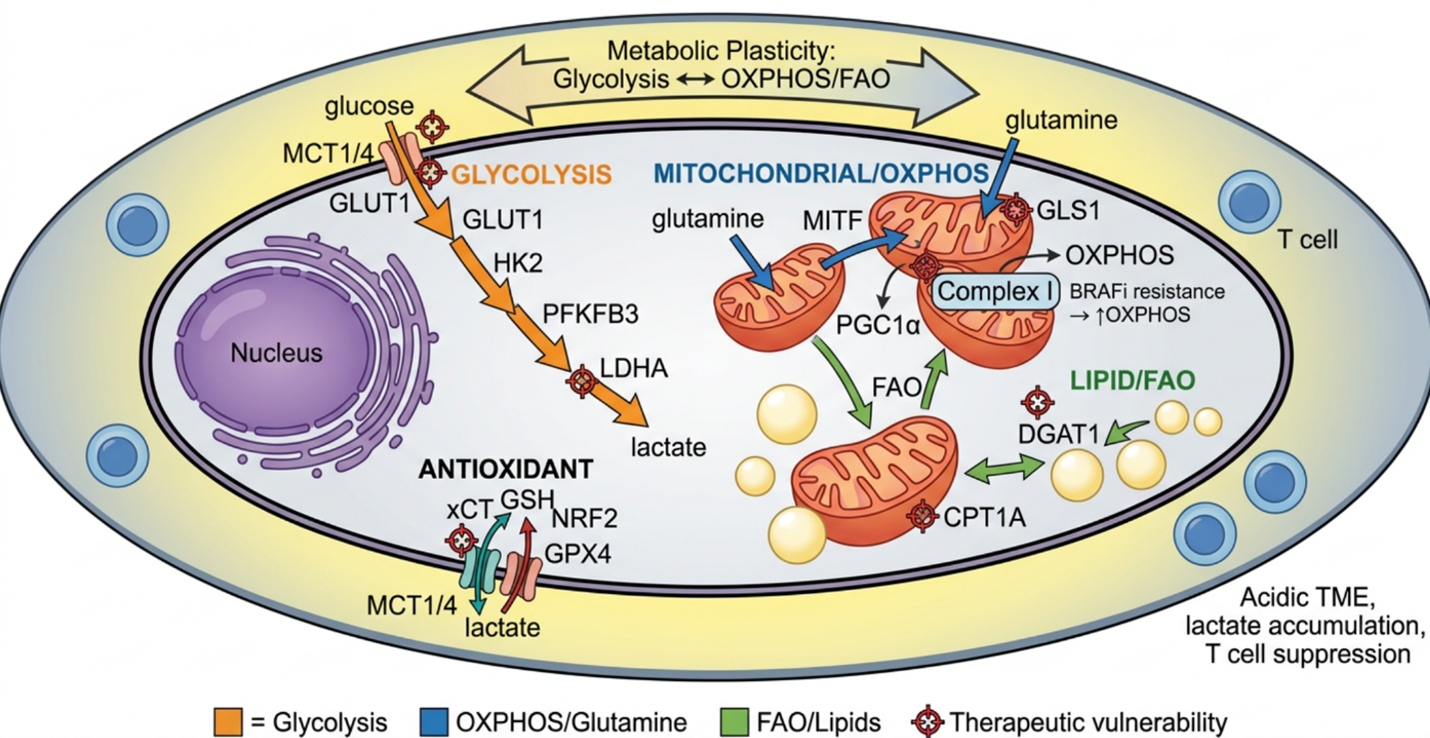
Melanoma appears unusually sensitive to metabolic pressure and mitochondrial disruption, which is why several repurposed drugs (metformin, doxycycline, ivermectin, statins) show surprisingly strong laboratory activity against melanoma.
Figure 1. Metabolic Vulnerabilities of melanoma
New Here?
Start with the: Cancer and the Metabolic Library

Medical Disclaimer: The discussion of repurposed medications and nutraceuticals in this article is intended to review the scientific literature and does not constitute a recommendation for self-treatment. Decisions regarding the use of off-label therapies should be made in consultation with a qualified healthcare professional familiar with the patient’s medical history and current treatment plan. Please see the full Medical Disclaimer on the introductory page to Marik’s Cancer & Metabolic Healing Playbook.
Thank you. There is no established correlation between melasma and skin cancer, including melanoma, basal cell carcinoma (BCC), or squamous cell carcinoma (SCC).
Several early observational studies reported that regular sunscreen users appeared to have a higher incidence of melanoma. However, these studies were subject to important sources of bias. People most likely to use sunscreen are also those at highest baseline risk—individuals with fair skin, numerous moles, or heavy sun exposure. Many sunscreen users also stay in the sun longer, increasing their cumulative UV dose, a phenomenon known as the "sunscreen paradox." When the totality of the evidence is considered, including several large meta-analyses, there is no convincing evidence that sunscreen itself increases the risk of melanoma. Rather, the apparent association is largely explained by confounding and behavioral factors. Sunscreen should therefore be viewed as one component of a broader sun-protection strategy that also includes avoiding sunburn, limiting excessive UV exposure, wearing protective clothing, and seeking shade when appropriate.