

Prostate-specific antigen (PSA) screening remains one of the most controversial topics in modern medicine. Since its introduction in the late 1980s, PSA testing has dramatically altered the landscape of prostate cancer diagnosis. It has unquestionably increased the detection of prostate cancer and contributed to reductions in metastatic disease at presentation. Yet it has also fueled concerns regarding overdiagnosis, overtreatment, unnecessary biopsies, psychological distress, and treatment-related morbidity.
At the center of the debate lies a fundamental question:
Does PSA screening save lives—or does it primarily identify indolent disease that would never have harmed the patient?
The answer is complex. PSA screening likely does both.
This review examines the biology of PSA, the rationale behind screening, the major clinical trials, the limitations of PSA testing, evolving screening strategies, and the future direction of precision prostate cancer detection.
What is PSA?
PSA is a serine protease produced primarily by prostate epithelial cells. Its normal physiologic role is to liquefy seminal fluid. Small amounts leak into the bloodstream and can be measured with a blood test.
Importantly:
PSA is prostate-specific, but not cancer-specific.
Elevated PSA levels may occur with:
benign prostatic hyperplasia (BPH),
prostatitis,
urinary retention,
infection,
recent ejaculation,
prostate manipulation,
aging,
and prostate cancer.
Thus, PSA is best viewed not as a cancer test, but as a marker of prostate gland activity and disruption.
Why PSA Screening Became Popular
Before PSA testing, most prostate cancers were diagnosed:
late,
symptomatically,
or after metastatic spread.
The introduction of PSA screening shifted diagnosis toward:
earlier-stage disease,
organ-confined tumors,
and potentially curable cancers.
The logic was compelling:
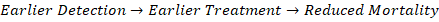
Initially, PSA screening was widely embraced because prostate cancer mortality appeared to decline during the PSA era.
However, whether this decline was entirely due to screening soon became controversial.
The Problem of Overdiagnosis
Many prostate cancers are biologically indolent.
Autopsy studies demonstrate that a substantial proportion of elderly men harbor microscopic prostate cancers that never caused symptoms during life.
PSA screening detects many of these tumors.
This creates the problem of:
overdiagnosis,
and subsequent overtreatment.
Treatment complications may include:
urinary incontinence,
erectile dysfunction,
bowel dysfunction,
psychological stress.
Consequently, critics argued that PSA screening often converts healthy men into cancer patients unnecessarily.
The Major Screening Trials
Two landmark trials largely shaped the modern PSA debate.
The ERSPC Trial
The European Randomized Study of Screening for Prostate Cancer (ERSPC) demonstrated:
a reduction in prostate cancer mortality with PSA screening,
but at the cost of significant overdiagnosis.
Longer follow-up strengthened evidence for mortality benefit.
The study suggested that PSA screening can reduce prostate cancer deaths, particularly when performed systematically and followed by appropriate risk stratification.
The PLCO Trial
The U.S.-based PLCO trial initially showed little mortality benefit.
However, interpretation became problematic because:
many men in the control group also underwent PSA testing,
creating substantial “contamination.”
This blurred differences between screened and unscreened populations.
As a result, many experts now believe the PLCO trial underestimated the benefit of screening.
Current Consensus
Most modern guidelines no longer recommend:
universal aggressive PSA screening,
nor complete abandonment of screening.
Instead, the trend has shifted toward:
individualized,
risk-adapted,
shared-decision screening.
This represents a major evolution in prostate cancer management.
The Limitations of PSA
PSA has several important weaknesses.
1. Poor Specificity
Many non-cancerous conditions elevate PSA.
This results in:
false positives,
unnecessary biopsies,
patient anxiety.
2. Some Aggressive Cancers Produce Little PSA
This is critically important.
Highly aggressive tumors—including:
neuroendocrine prostate cancer,
dedifferentiated tumors,
and some high-grade cancers—
may produce relatively little PSA despite substantial disease burden.
Thus:
A “normal” PSA does not completely exclude dangerous cancer.
3. PSA Does Not Reliably Distinguish Aggressive vs Indolent Disease
Some men with mildly elevated PSA harbor lethal cancer.
Others with high PSA have only benign enlargement.
The biological behavior matters more than the number alone.
Improving PSA Interpretation
Modern prostate cancer screening increasingly uses PSA in context rather than isolation.
PSA Velocity
The rate of PSA rise over time may provide useful information (see below).
Rapid PSA increases may suggest:
aggressive disease,
inflammation,
or rapid tumor growth.
PSA Density
PSA density accounts for prostate volume:
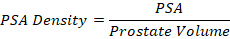
Large prostates naturally produce more PSA.
Higher PSA density may indicate greater cancer risk.
Free vs Total PSA
Lower free PSA percentages are associated with higher cancer risk.
This may help reduce unnecessary biopsies.
Age-Adjusted PSA
PSA normally rises somewhat with age due to BPH.
Age-specific thresholds may improve specificity.
MRI Revolution in Screening
One of the biggest advances in modern prostate cancer detection is multiparametric MRI (mpMRI).
MRI allows:
visualization of suspicious lesions,
improved biopsy targeting,
and reduction of unnecessary biopsies.
MRI has significantly changed the screening pathway.
Instead of:
elevated PSA → immediate biopsy,
the modern approach increasingly becomes:
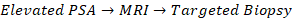
This has improved detection of clinically significant cancers while reducing diagnosis of low-risk disease.
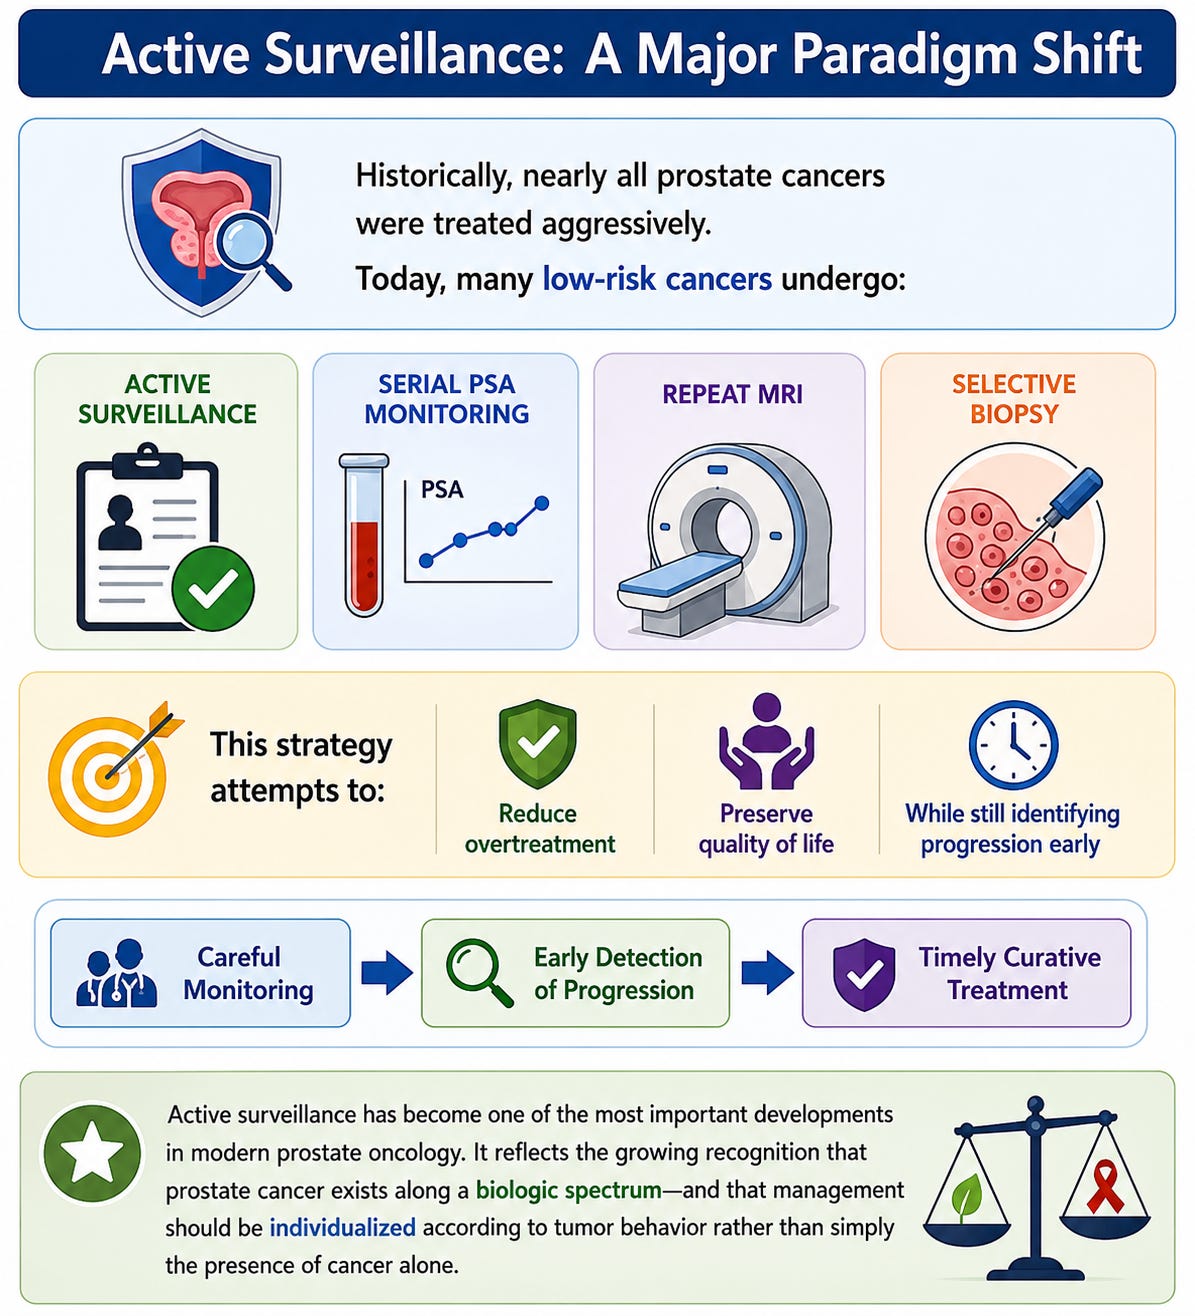
Active Surveillance: A Major Paradigm Shift
Historically, nearly all prostate cancers were treated aggressively.
Today, many low-risk cancers undergo:
active surveillance,
serial PSA monitoring,
repeat MRI,
selective biopsy.
This strategy attempts to:
reduce overtreatment,
preserve quality of life,
while still identifying progression early.
Active surveillance represents one of the most important paradigm shifts in modern prostate oncology. It reflects the growing recognition that prostate cancer exists along a biologic spectrum—and that management should be individualized according to tumor behavior rather than simply the presence of cancer alone.
Active surveillance should be combined with the “Preventing Prostate Cancer Protocol” (See previous post).
Who Benefits Most from PSA Screening?
Men at higher risk likely derive greater benefit.
Higher-risk groups include (see previous post):
men with strong family history,
African American men,
BRCA mutation carriers,
men with known genetic predisposition.
These individuals may develop:
earlier,
more aggressive disease.
At What Age Should Screening Begin?
Guidelines vary, but many recommend:
discussion beginning around age 45–50,
earlier for high-risk individuals.
Routine screening in elderly men with limited life expectancy is often discouraged because:
many prostate cancers are slow growing,
and competing mortality risks dominate.
The Metabolic Perspective
From a metabolic standpoint, PSA reflects more than simply cancer burden.
PSA production is closely linked to:
androgen receptor signaling,
prostate differentiation,
and lipid metabolism.
Conceptually:
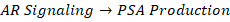
This becomes critically important in advanced disease.
As prostate cancer evolves toward:
glycolytic metabolism,
stem-cell dominance,
neuroendocrine transformation,
and AR independence,
PSA production may paradoxically decline.
This explains why some aggressive cancers become:
“PSA silent.”
The Future of Screening
The future of prostate cancer screening will likely move toward:
precision medicine,
molecular profiling,
metabolic imaging,
and individualized risk prediction.
Emerging tools include:
MRI-guided pathways,
PSMA PET imaging,
liquid biopsies,
genomic classifiers,
AI-based risk models,
metabolomics,
and polygenic risk scoring.
The goal is no longer simply:
detecting more cancer,
but rather:
identifying dangerous cancer while avoiding unnecessary treatment of indolent disease.
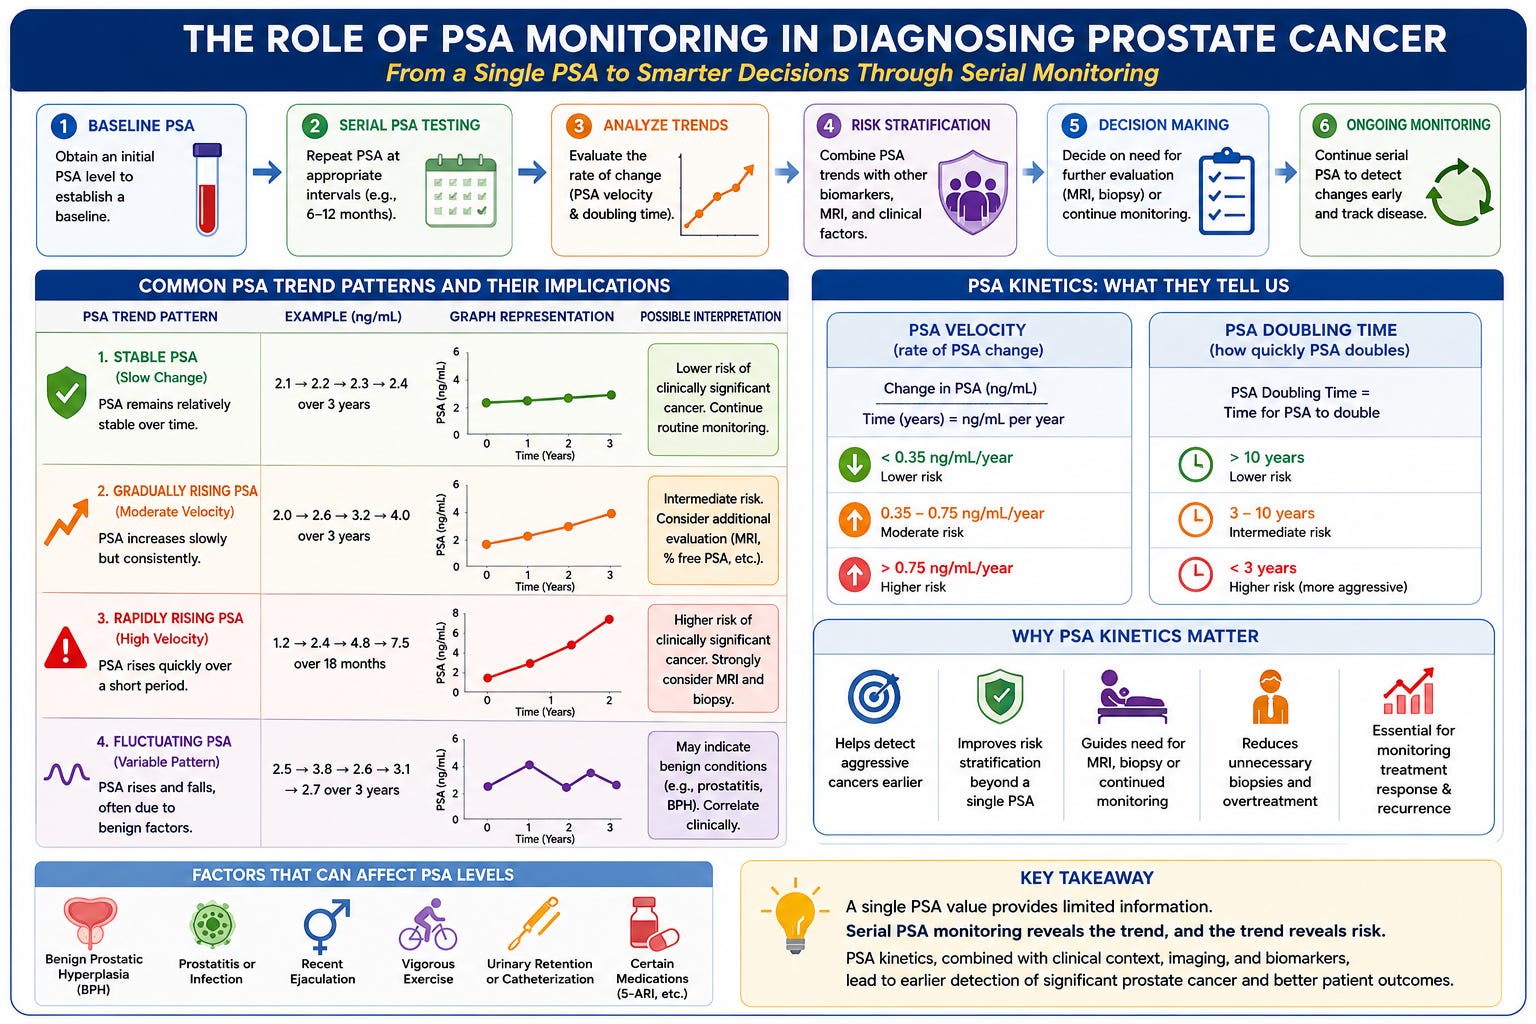
Serial PSA Trending and PSA Kinetics
The Role of PSA Velocity, Doubling Time, and Longitudinal Change in Assessing Prostate Cancer Risk
The interpretation of prostate-specific antigen (PSA) has evolved substantially over the past three decades. Initially, PSA was viewed largely as a static laboratory threshold—most famously the cutoff of 4.0 ng/mL above which biopsy was often recommended. However, modern prostate cancer screening increasingly recognizes that:
The trajectory of PSA over time may be more informative than a single PSA value.
This concept has led to growing interest in:
serial PSA monitoring,
PSA velocity,
PSA doubling time,
and PSA kinetics.
These measurements attempt to distinguish:
benign stable PSA elevations,
from biologically aggressive prostate cancer.
The central idea is intuitive:
A slowly stable PSA may reflect benign prostate enlargement or indolent disease, whereas a rapidly rising PSA may indicate:
aggressive tumor biology,
higher tumor burden,
inflammatory activity,
or treatment resistance.
Serial PSA trending therefore attempts to convert PSA from a simple static biomarker into a dynamic biologic signal.
Why a Single PSA Measurement Is Limited
A single PSA level provides only a snapshot in time.
Yet PSA levels fluctuate due to numerous factors:
benign prostatic hyperplasia (BPH),
prostatitis,
ejaculation,
urinary retention,
recent instrumentation,
aging,
medications,
and biologic variability.
Thus:
two men with the same PSA may have completely different risks.
For example:
one man with a stable PSA of 4.5 ng/mL over 10 years may have benign disease,
while:another whose PSA rose from 1.0 to 4.5 ng/mL within 18 months may harbor aggressive cancer.
The kinetics matter.
The Biological Basis of PSA Kinetics
PSA production is closely linked to:
androgen receptor signaling,
prostate epithelial activity,
glandular disruption,
and tumor growth.
Conceptually:
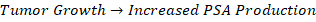
Rapidly proliferating tumors often:
disrupt gland architecture,
produce more PSA,
and increase serum PSA more quickly.
However, this relationship is imperfect because:
some aggressive tumors produce relatively little PSA,
particularly:neuroendocrine,
dedifferentiated,
or AR-independent cancers.
Nonetheless, in most conventional prostate adenocarcinomas, PSA kinetics provide valuable biologic information.
PSA Velocity
PSA velocity refers to:
the rate of PSA change over time.
It is typically expressed as:
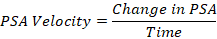
usually in:
ng/mL per year.
Why PSA Velocity Matters
Several studies demonstrated that:
rapidly rising PSA levels correlate with:
increased prostate cancer risk,
higher Gleason grade,
metastatic potential,
and mortality.
Historically:
PSA velocity >0.75 ng/mL/year
was considered concerning in men with PSA between 4–10 ng/mL.
Later studies suggested:
even lower thresholds may be important in younger men.
Important Clinical Insight
A rapidly rising PSA may be more concerning than:
a mildly elevated but stable PSA.
For example:
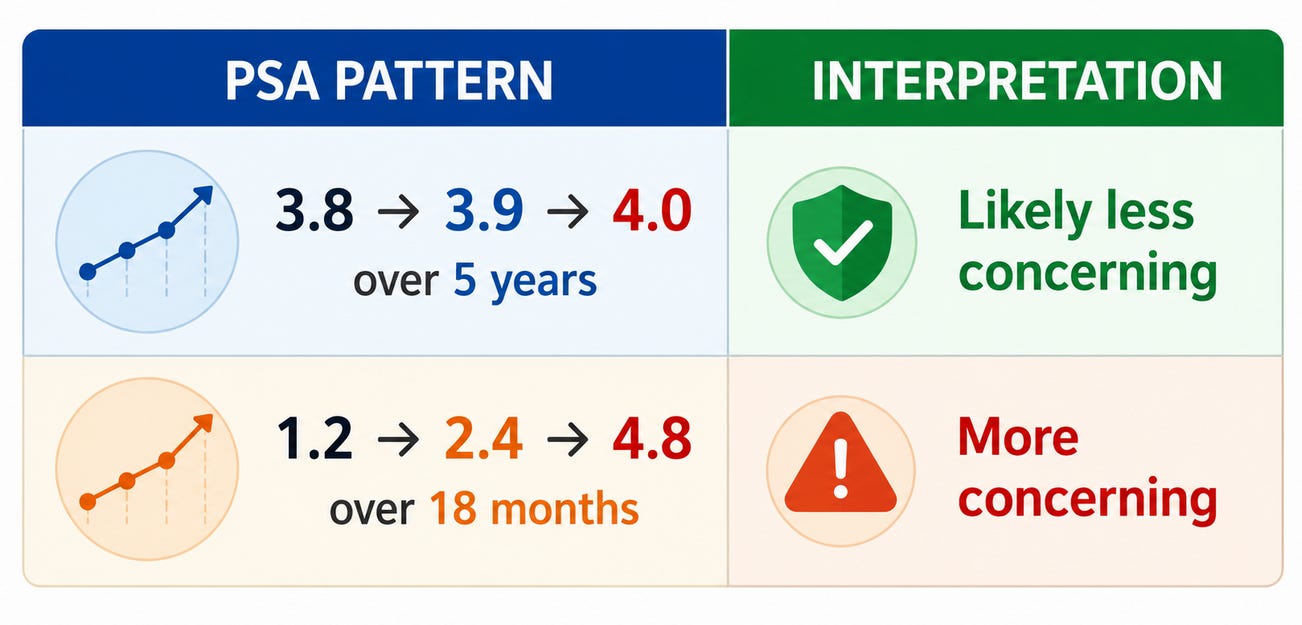
The second pattern suggests:
active biologic progression.
Limitations of PSA Velocity
Despite initial enthusiasm, PSA velocity is imperfect.
Problems include:
biologic variability,
prostatitis,
assay variability,
overinterpretation of small fluctuations.
Short-term PSA “noise” may falsely suggest danger.
Consequently:
isolated PSA velocity alone is no longer considered sufficient to trigger biopsy.
Instead:
it is interpreted alongside:
MRI,
PSA density,
free PSA,
family history,
age,
genomics,
and clinical context.
PSA Doubling Time
PSA doubling time (PSADT) measures:
how long it takes PSA to double.
Conceptually:
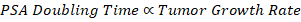
Short doubling times generally indicate:
more aggressive disease.
Clinical Importance of PSA Doubling Time
PSADT is especially valuable in:
recurrent disease,
post-treatment monitoring,
active surveillance,
biochemical recurrence.
Rapid doubling times often correlate with:
metastasis,
treatment failure,
and mortality.
Approximate Clinical Interpretation
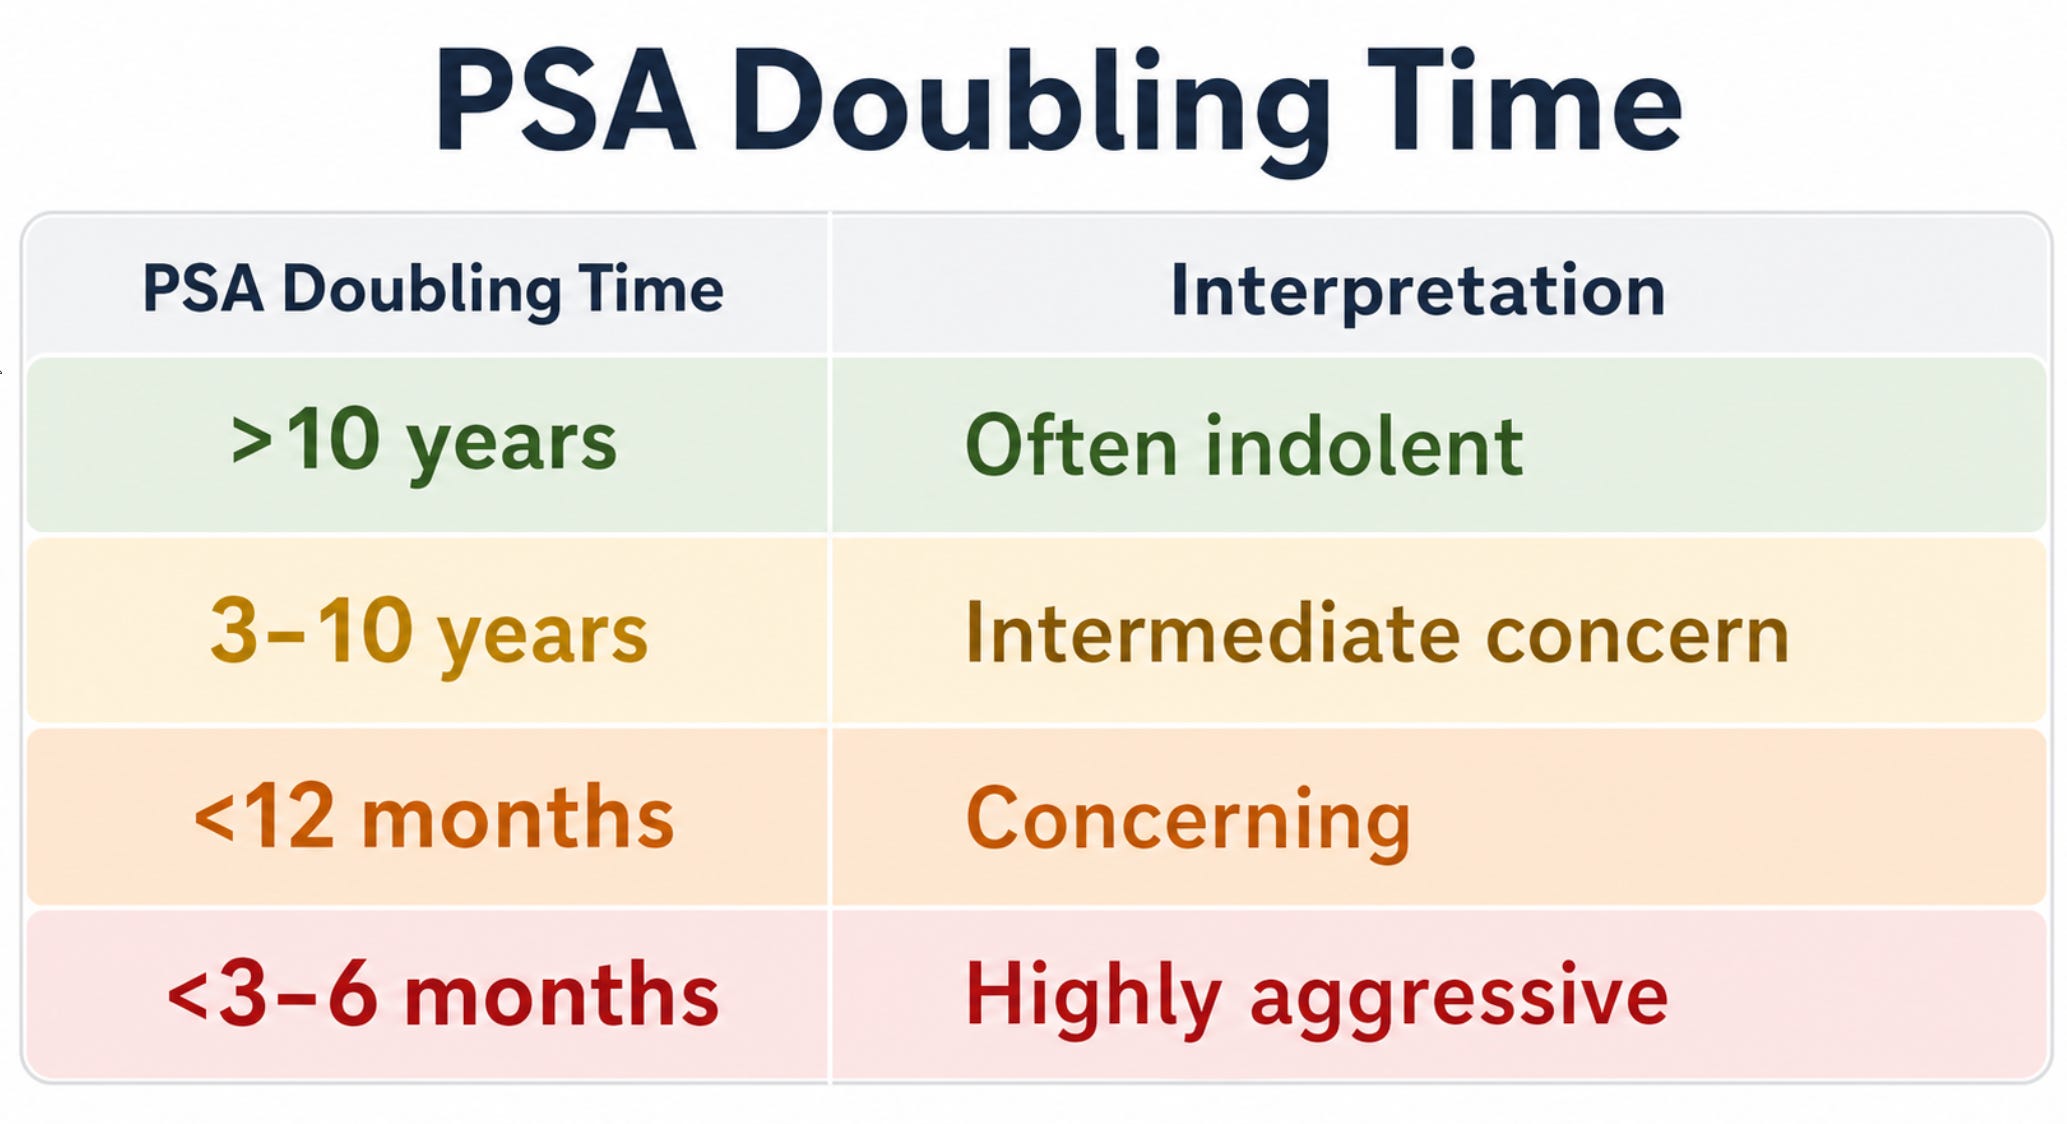
Very short doubling times may suggest:
aggressive biology,
occult metastases,
or treatment resistance.
Serial PSA Trends During Active Surveillance
Active surveillance depends heavily on serial PSA monitoring.
The goal is:
to identify which low-risk tumors remain biologically quiet,
and:which begin progressing.
Concerning patterns include:
accelerating PSA rise,
shortening doubling time,
rising PSA density,
MRI progression.
Importantly:
PSA kinetics alone rarely dictate treatment.
Rather:they trigger further evaluation.
PSA Density and Serial Trends
PSA density combines PSA with prostate size:
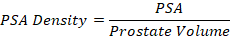
A man with:
large benign enlargement
may naturally produce higher PSA.
Serial increases in PSA density are often more informative than PSA alone.
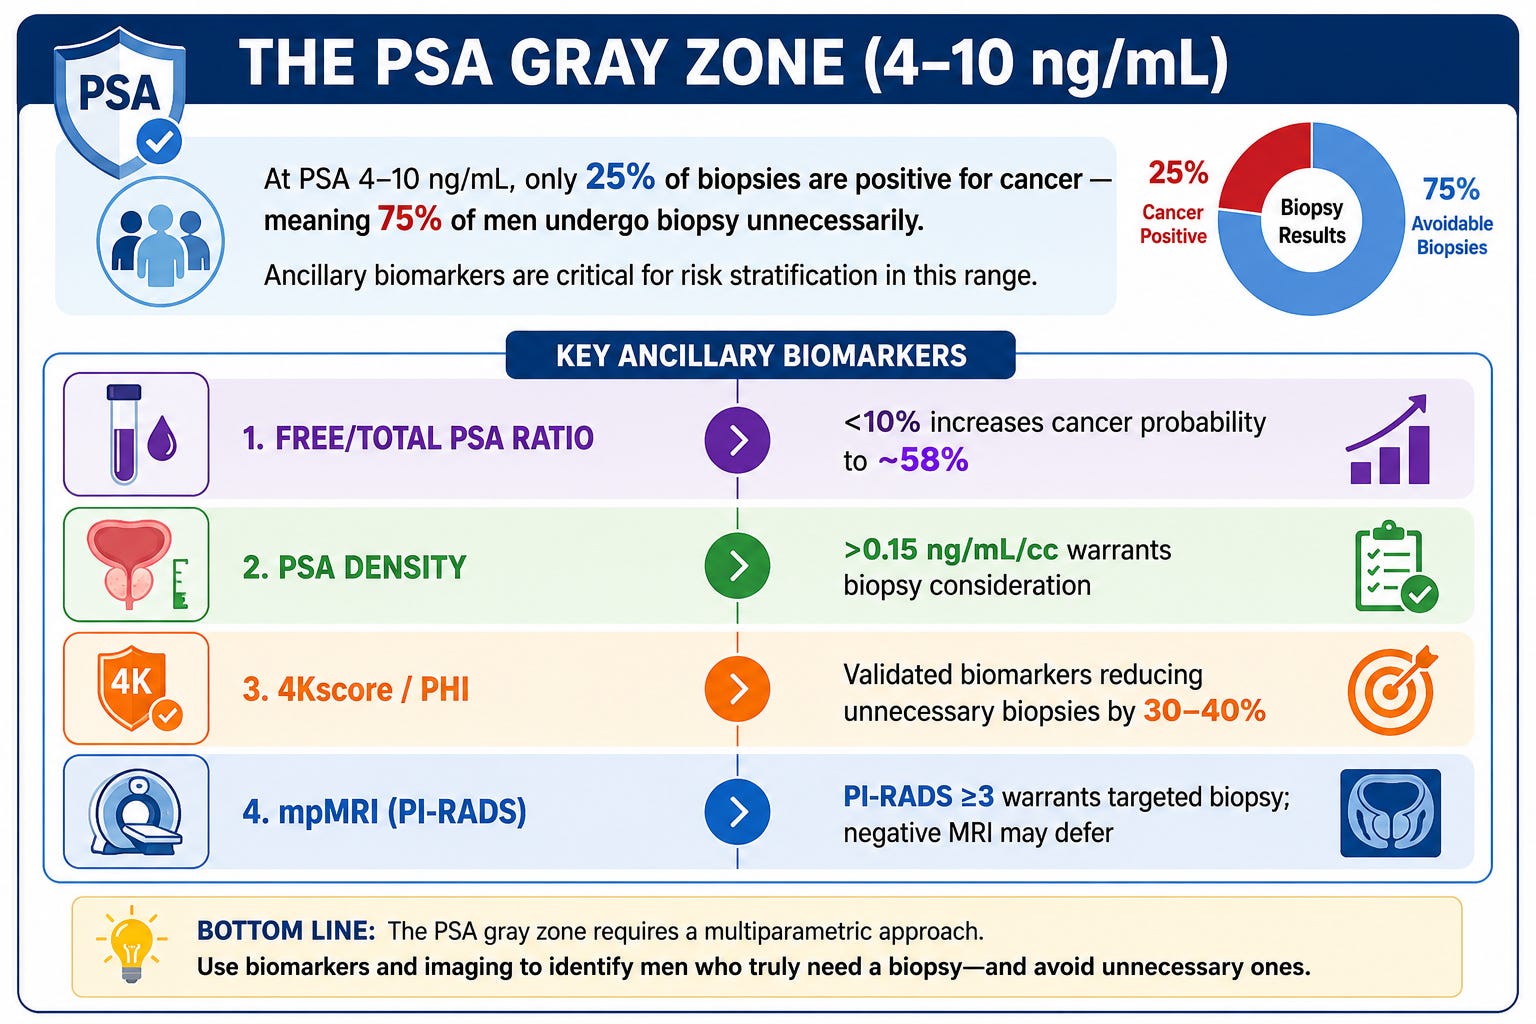
The “PSA Gray Zone”
The range between:
4–10 ng/mL
is often called the PSA gray zone.
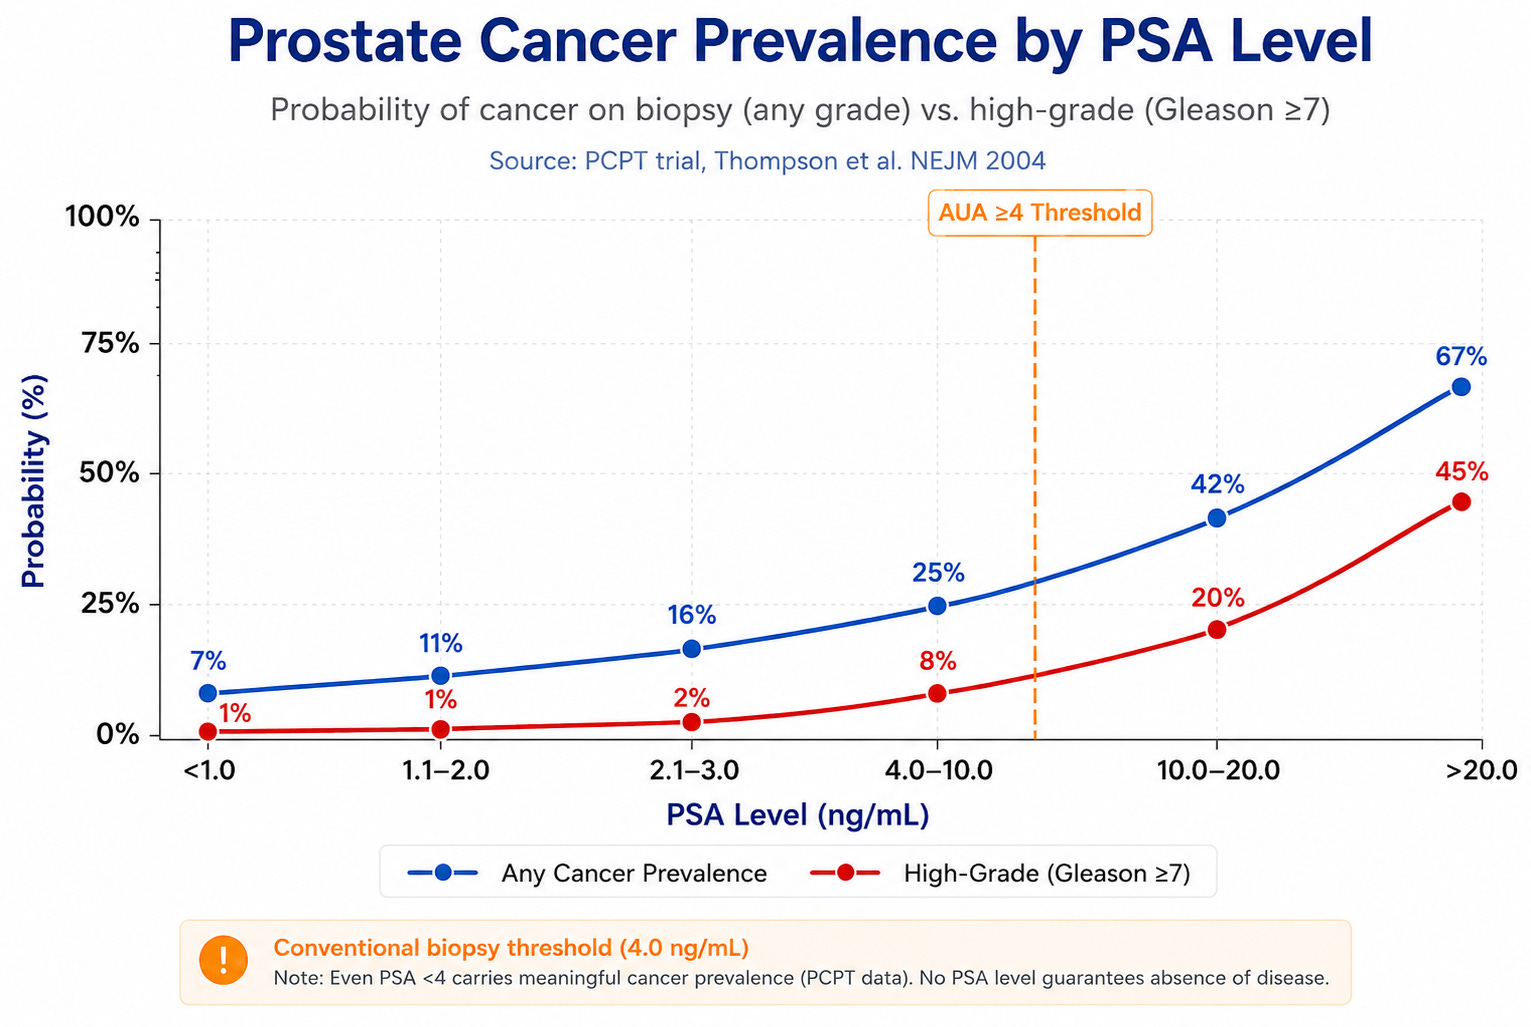
Only about:
25% of biopsies
in this range reveal cancer.
Thus:
75% of men may undergo unnecessary biopsy.
This is why:
PSA kinetics,
MRI,
4Kscore,
PHI,
and PSA density
have become increasingly important.
MRI and PSA Trending
One of the most important modern developments is combining:
serial PSA trends
with:multiparametric MRI.
The modern pathway increasingly becomes:
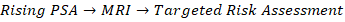
MRI helps determine whether:
PSA progression reflects:
clinically significant cancer,
or benign disease.
This has significantly reduced unnecessary biopsies.
The Metabolic Perspective
From a metabolic standpoint, PSA kinetics may indirectly reflect:
tumor growth rate,
androgen receptor signaling,
and metabolic adaptation.
Early prostate cancer is often:
AR driven,
lipid dependent,
and relatively differentiated.
These tumors typically produce:
substantial PSA.
However, as tumors evolve toward:
glycolysis,
stem-cell dominance,
neuroendocrine transition,
and AR independence,
PSA production may paradoxically decline despite progression.
This is critically important.
When PSA Becomes Misleading
Aggressive cancers may:
metastasize rapidly,
become FDG-avid,
and progress clinically
while PSA rises only minimally.
This is particularly true in:
neuroendocrine prostate cancer,
dedifferentiated disease,
treatment-emergent lineage plasticity.
Thus:
Stable or modest PSA does not always mean stable disease.
This limitation becomes increasingly important in advanced cancer.
The Future of PSA Kinetics
The future likely lies in integrating PSA trends with:
MRI,
genomics,
liquid biopsy,
AI prediction models,
metabolomics,
PSMA PET imaging,
and molecular profiling.
The goal is not merely:
detecting prostate cancer,
but:distinguishing dangerous cancer from indolent disease.
Marik’s Practical Approach to Prostate Cancer Screening and initial treatment
This approach is driven by the fact that most prostate cancers are slow-growing and therefore the patient has time to decide if and what treatment approach he would prefer (informed patient driven decision making). The urologist should never scare the patient into believing that urgent prostatectomy is required. This is one of many approaches to PSA monitoring.
Start PSA screening at 45 -50 years (age 40 if high risk features- see previous post)
If PSA < 1.5 ng/ml and no clinical suspicion of cancer – follow up PSA in 3-5 years
If PSA 1.5-4 ng/ml and no clinical suspicion of cancer – start Prostrate Cancer Prevention Protocol (previous post) and repeat PSA in 6 months -1 year
If PSA 4-10 ng/ml and ancillary markers (see below) suggest low probability of cancer start Prostrate Cancer Prevention Protocol (previous post) and repeat PSA in 6 months - 1 year.
If PSA 4-10 ng/ml and ancillary markers suggest high probability of cancer suggest BIOPSY and start full Prostate Cancer Treatment protocol (see Prostate Cancer: The Evolution of Fuel Utilization and the Five-Axis Metabolic Pressure Model).
If PSA > 10 ng/ml - BIOPSY and start full Prostate Cancer Treatment protocol.
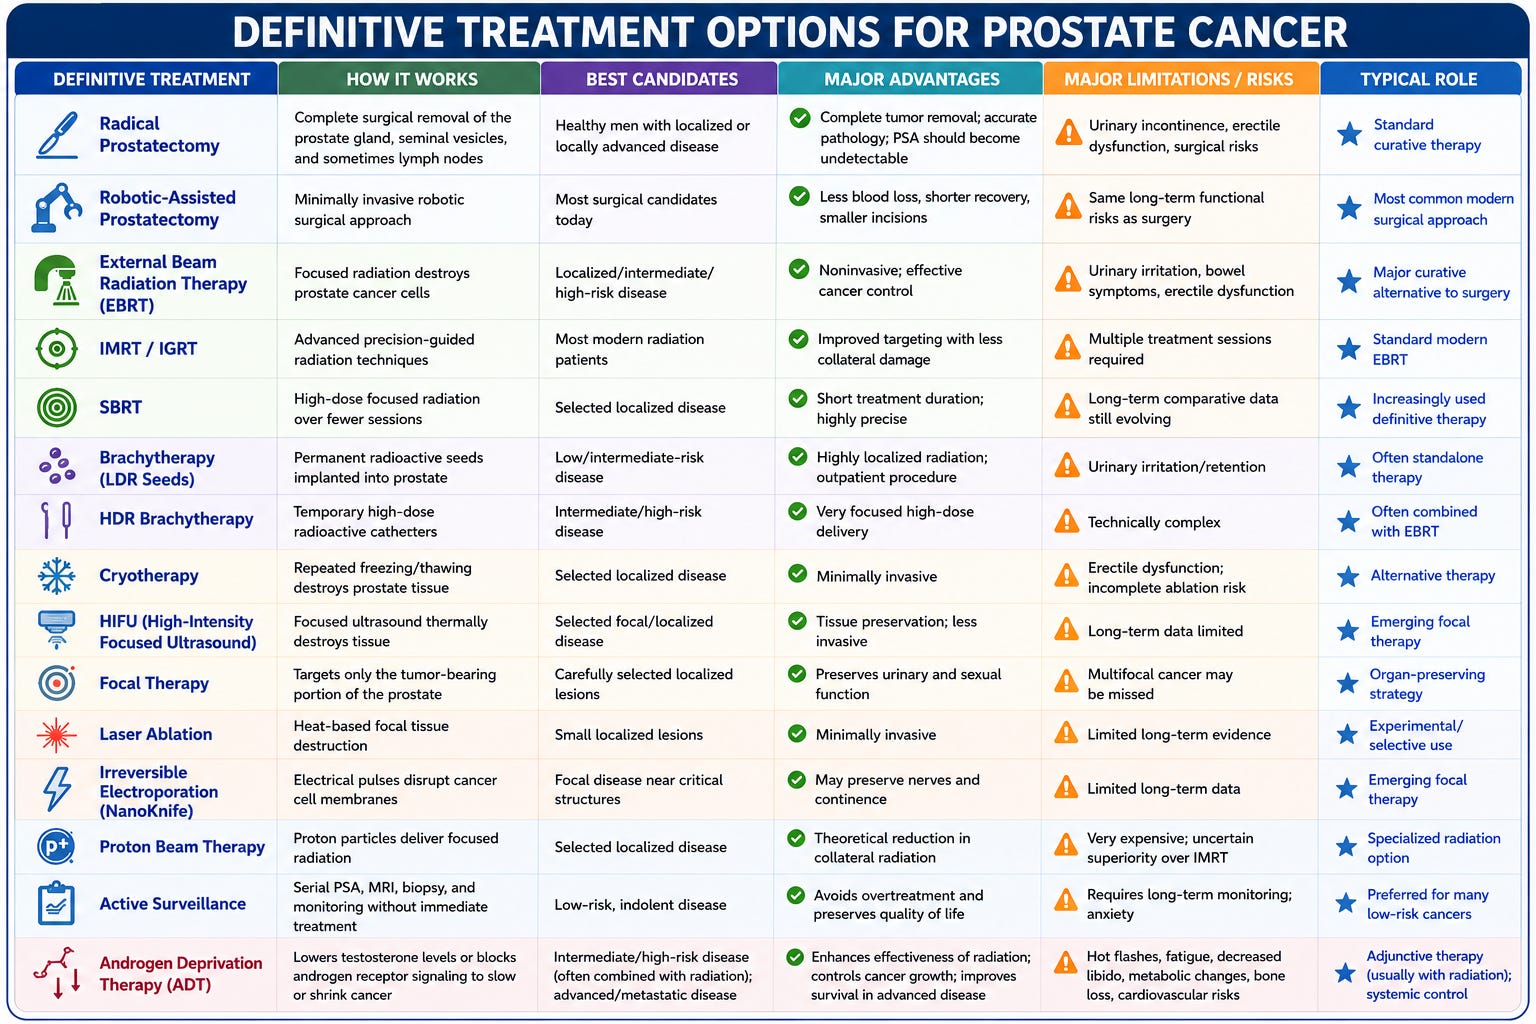
Should the patient have biopsy proven prostate cancer the treatment strategy should ultimately depend upon the patient’s age, the stage of the disease, the patient’s comorbidities and the Gleason score and most importantly the patients’ preferences. Many treatment options are currently available (See the table below). It should be recognized that total prostatectomy (including robotic surgery) is frequently associated with quality-of-life altering complications and has a recurrence rate of up to 40% in 3-5 years. Androgen deprivation therapy (ADT), while commonly prescribed, is usually very poorly tolerated by patients (severe fatigue). Furthermore, ADT by blocking a single metabolic pathway has a high risk of converting the cancer into a neuroendocrine prostatic tumor (see post). The patient may elect to follow the full Prostate Cancer Treatment protocol while monitoring the PSA, PSA ratio, and PSA kinetics (active surveillance) before deciding on any” definitive” treatment (if ever). It is important to recognize that most patients die with prostate cancer rather than from prostate cancer.
Conclusion
PSA screening has transformed prostate cancer detection, but its benefits come with important limitations. PSA is neither a perfect cancer marker nor a simple binary test. Rather, it is one piece of a much larger biologic puzzle.
The modern approach increasingly recognizes that prostate cancer exists along a spectrum:
from indolent metabolic/hormonal disease,
to highly aggressive glycolytic and treatment-resistant phenotypes.
The challenge is not merely finding prostate cancer—but distinguishing:
which cancers matter,
which men truly benefit from treatment,
and which tumors are biologically dangerous.
The future of screening will likely depend less on PSA alone and more on integrated biologic assessment combining:
PSA kinetics,
MRI,
genomics,
metabolic profiling,
and individualized risk stratification.
In this evolving framework, PSA remains valuable—but no longer sufficient by itself.
If you’ve found this work valuable, please consider upgrading to a paid subscription. Your support helps me continue independent research and share practical, evolving insights—while giving you access to deeper content and more direct engagement.
New Here?
Start with the: Cancer and the Metabolic Library

Watchful waiting PLUS repurposed drugs and nutraceuticals ... surgery is awful.
Thank you