

Cancer progression is not simply a problem of uncontrolled cell growth. It is also a failure of immune surveillance. In a healthy host, abnormal cells are detected and eliminated by natural killer cells, cytotoxic CD8+ T cells, dendritic cells, macrophages, and coordinated cytokine signaling. In cancer, this system is progressively disabled. Tumors recruit suppressive immune cells, exhaust T cells, polarize macrophages toward a tumor-supportive phenotype, stimulate angiogenesis, and create a metabolically hostile microenvironment rich in lactate, hypoxia, inflammatory cytokines, and oxidative stress.
The goal of adjunctive repurposed drugs and nutraceuticals is therefore not merely to “kill cancer cells,” but to help restore the host terrain: improve systemic immunity, reduce immune suppression, normalize inflammatory signaling, and make the tumor microenvironment more visible and vulnerable to immune attack.
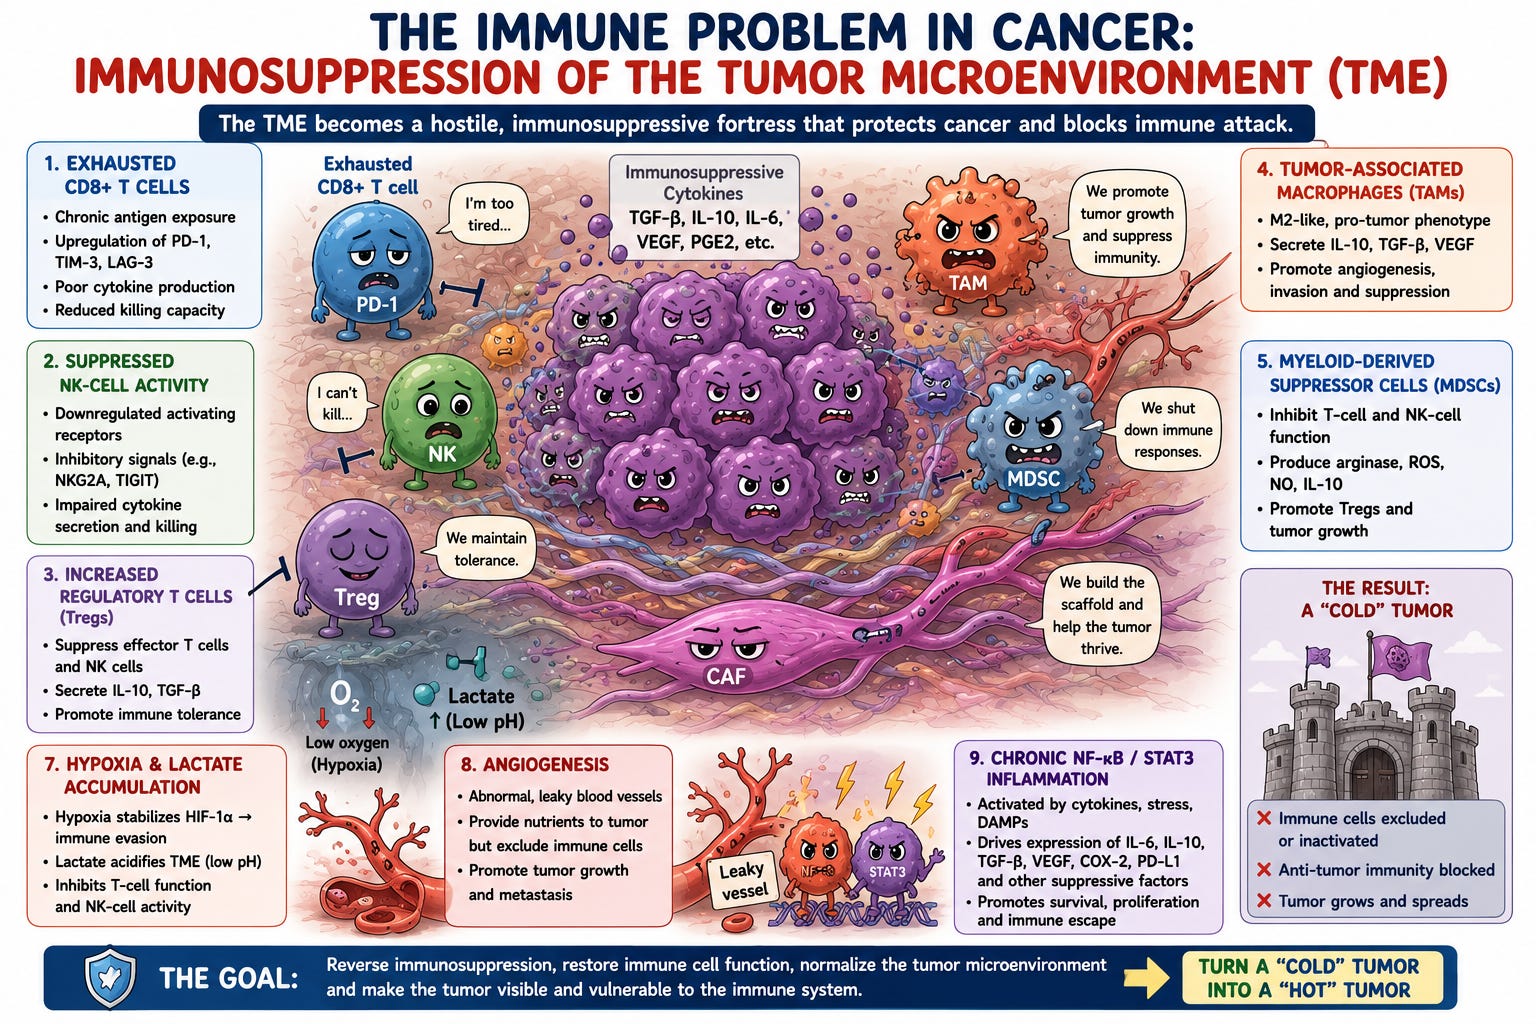
The Immune Problem in Cancer
The tumor microenvironment is often dominated by:
Exhausted CD8+ T cells
Suppressed NK-cell activity
Increased regulatory T cells
Tumor-associated macrophages
Myeloid-derived suppressor cells
Cancer-associated fibroblasts
Hypoxia and lactate accumulation
Angiogenesis
Chronic NF-κB / STAT3 inflammation
This creates the classic “cold tumor”: one poorly infiltrated by effective immune cells and protected by an immunosuppressive stromal barrier.
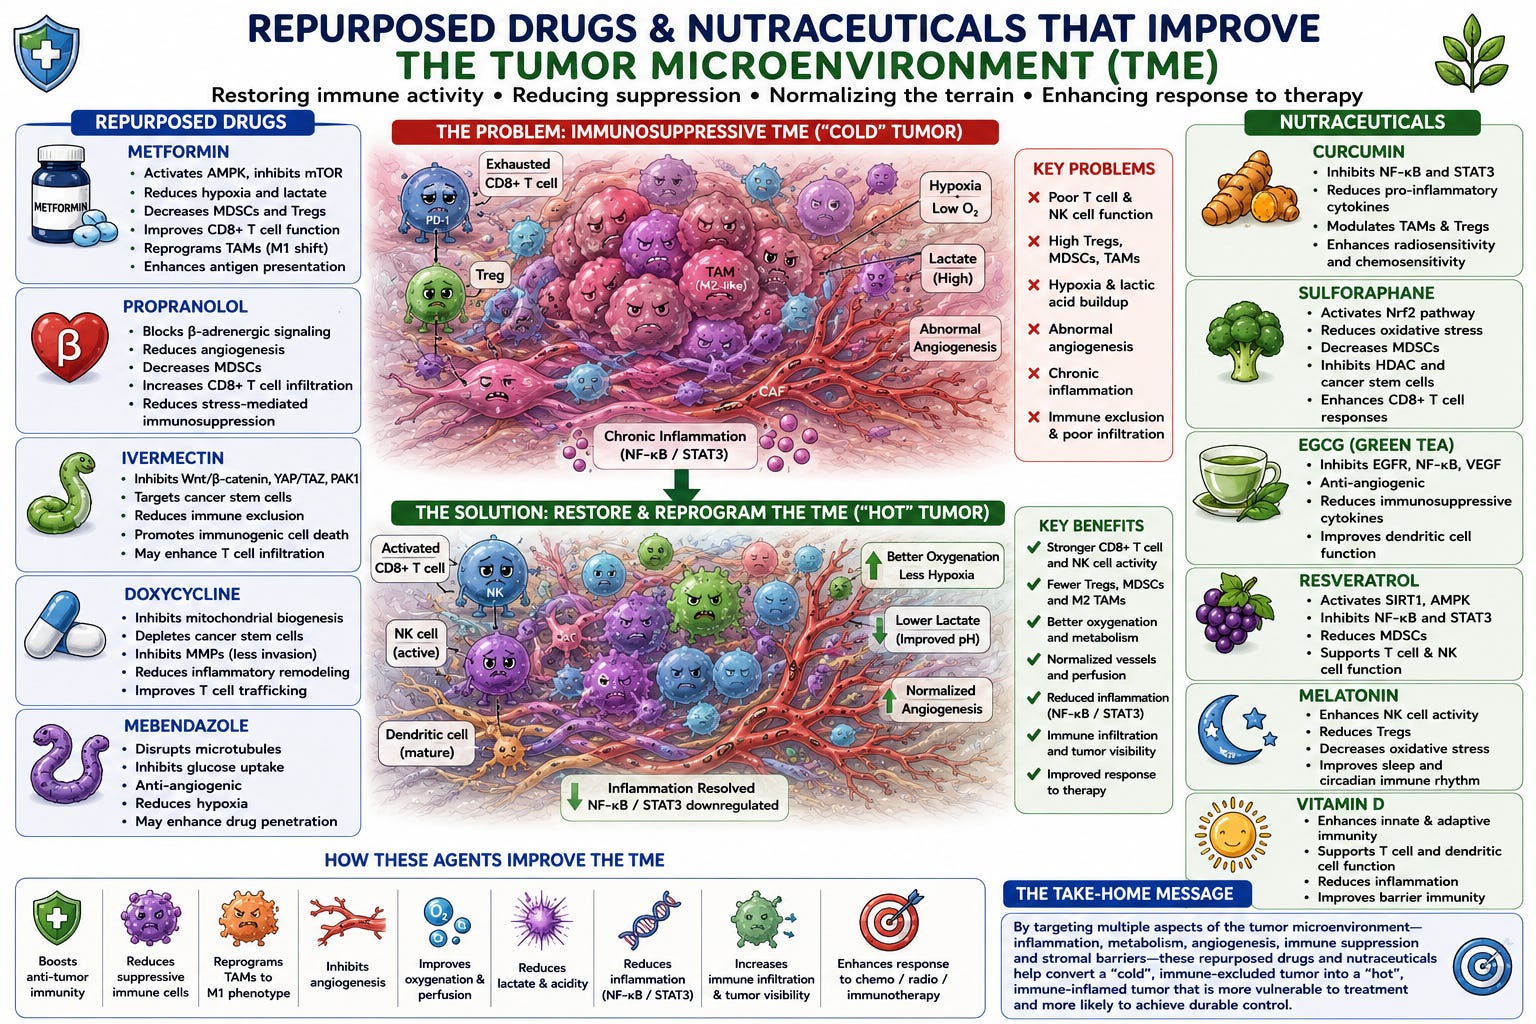
The ideal adjunctive agent should therefore do several things at once: support NK cells, restore T-cell function, reduce Tregs and MDSCs, shift macrophages toward an anti-tumor phenotype, inhibit inflammatory signaling, and improve metabolic conditions inside the tumor.
Metformin
Metformin is one of the most important immune-metabolic repurposed drugs. Its central action is activation of AMPK and inhibition of mTOR, but its immune effects are equally important. Metformin can improve T-cell fitness, reduce tumor hypoxia, inhibit immunosuppressive signaling, and modulate tumor-infiltrating immune cells. Reviews describe effects on NK-cell antitumor activity, MHC-I expression, PD-L1 signaling, tumor-associated macrophages, angiogenesis, and cancer-associated fibroblasts.
Mechanistically, metformin improves the immune terrain by lowering insulin/IGF-1 signaling, reducing glycolytic pressure, inhibiting inflammatory NF-κB signaling, and improving metabolic competition between cancer cells and immune cells. This is important because activated T cells require metabolic flexibility. A lactate-rich, glucose-depleted tumor environment paralyzes cytotoxic immunity.
Immune role: improves T-cell function, supports NK-cell recognition, reduces hypoxia, inhibits immunosuppressive TME signaling.
Propranolol
Cancer is strongly influenced by the stress axis. β-adrenergic signaling promotes angiogenesis, invasion, metastasis, inflammation, and immune suppression. Propranolol, a non-selective beta-blocker, may help interrupt this stress-mediated cancer biology.
Preclinical studies suggest propranolol can reduce angiogenesis and shift the tumor microenvironment toward an antitumor state, including increased T-cell infiltration and reduced myeloid-derived suppressor cells. One study found that the full antitumor effect of propranolol required T cells, highlighting that its benefit is not simply vascular but immunologic.
Immune role: reduces stress-mediated immune suppression, increases CD8+ T-cell infiltration, decreases MDSCs, reduces angiogenesis.
Melatonin
Melatonin is more than a sleep hormone. It is a circadian immune regulator with important anticancer properties. It supports NK-cell cytotoxicity, modulates T-cell activation, reduces oxidative stress, suppresses inflammatory signaling, and may reduce regulatory T cells and cancer-associated fibroblast activity. Reviews describe melatonin as an immune-supportive adjunct to chemotherapy, radiotherapy, immunotherapy, and tumor vaccination strategies.
Melatonin may be especially valuable because circadian disruption itself impairs immunity. Poor sleep, nocturnal light exposure, and dysregulated cortisol/melatonin rhythms can weaken NK-cell activity and T-cell coordination.
Immune role: enhances NK-cell activity, supports T-cell function, reduces oxidative stress, improves circadian immune regulation.
Vitamin D
Vitamin D is a major regulator of innate and adaptive immunity. It affects dendritic cells, macrophages, T cells, antimicrobial peptides, inflammatory cytokines, and epithelial barrier function. In cancer models, vitamin D can modulate tumor growth, inflammation, and CD8+ T-cell behavior in the tumor microenvironment.
Vitamin D may also influence anticancer immunity through the gut microbiome. Experimental work has shown that vitamin D bioavailability can shape microbiome-dependent antitumor immunity and may influence responses to immunotherapy.
Immune role: improves innate immunity, antigen presentation, CD8+ T-cell function, microbiome-linked antitumor immunity.
Curcumin
Curcumin is a broad immune-modulating nutraceutical. It targets NF-κB, STAT3, COX-2, inflammatory cytokines, macrophage polarization, Tregs, NK cells, and dendritic cells. Reviews describe curcumin as capable of modulating T cells, B cells, macrophages, neutrophils, NK cells, dendritic cells, cytokines, and chemokines.
Curcumin may also enhance NK-cell function and reduce the suppressive behavior of tumor-associated immune cells. Its value is less as a single cytotoxic agent and more as a terrain-modifying compound: it quiets the chronic inflammatory signaling that cancers exploit.
Immune role: reduces NF-κB/STAT3 inflammation, supports NK-cell activity, modulates macrophages, may reduce Tregs.
Sulforaphane
Sulforaphane, derived from cruciferous vegetables, is a potent activator of Nrf2 and regulator of detoxification, oxidative stress, epigenetics, and inflammation. It also has important effects on cancer stem cells and the tumor microenvironment. Recent work suggests sulforaphane can remodel the tumor immune microenvironment, reduce MDSCs, and activate CD8+ T-cell antitumor responses.
This is highly relevant because MDSCs are among the most powerful suppressors of antitumor immunity. A tumor rich in MDSCs is often resistant to immune clearance and less responsive to immunotherapy.
Immune role: reduces oxidative and inflammatory stress, suppresses MDSCs, supports CD8+ T-cell activity, targets cancer stem cells.
EGCG
EGCG, the major catechin in green tea, has broad antioxidant, anti-inflammatory, anti-angiogenic, and signaling effects. It modulates multiple cancer-relevant pathways, including EGFR, NF-κB, VEGF, PI3K/AKT, and inflammatory cytokines. Reviews describe EGCG as regulating numerous molecular targets relevant to cancer biology and inflammation.
EGCG’s role in immunity is mainly indirect: it reduces inflammatory noise, oxidative stress, angiogenesis, and signaling pathways that promote immune escape. It may also help reduce stromal and vascular support for tumors.
Immune role: anti-inflammatory, anti-angiogenic, reduces oxidative stress, may improve immune visibility of tumor cells.
Ivermectin
Ivermectin has attracted interest because of its multi-target anticancer effects: inhibition of Wnt/β-catenin, YAP/TAZ, PAK1, Akt/mTOR, mitochondrial function, and cancer stem-cell signaling. From an immune standpoint, its most important theoretical role is reducing pathways associated with immune exclusion and stem-cell persistence.
The strongest data remain preclinical. The rationale is that ivermectin may help make tumors less stem-like, less invasive, and more immunologically vulnerable. However, clinical evidence in cancer remains limited, and its role should be considered investigational.
Immune role: potential reduction of cancer stem-cell immune evasion, Wnt/YAP-mediated immune exclusion, and resistance biology.
Doxycycline
Doxycycline is relevant because mitochondria are central to cancer stem-cell survival and immune evasion. Doxycycline inhibits mitochondrial biogenesis and matrix metalloproteinases. By targeting cancer stem cells and invasive behavior, it may indirectly improve the tumor microenvironment.
It may also reduce tissue-destructive inflammatory remodeling through MMP inhibition. This matters because tumors use MMPs to invade, remodel extracellular matrix, and recruit suppressive stromal cells.
Immune role: targets mitochondrial cancer stem-cell biology, reduces invasion, may reduce inflammatory matrix remodeling.
Mebendazole
Mebendazole disrupts microtubules, inhibits glucose uptake, reduces angiogenesis, and interferes with proliferative signaling. Its immune effects are less direct than metformin, melatonin, vitamin D, or curcumin, but by reducing angiogenesis and tumor cell plasticity, it may help weaken immune-protective tumor architecture.
Immune role: anti-angiogenic, anti-proliferative, may reduce tumor structural resistance to immune attack.
The Combined Effect: Turning a Cold Tumor Hot
The most important concept is synergy. These agents do not all act through the same pathway. They apply pressure across multiple immune-metabolic axes:
Systemic immunity
NK-cell activation: melatonin, curcumin, vitamin D
CD8+ T-cell support: metformin, vitamin D, sulforaphane, propranolol
Improved antigen presentation: vitamin D, metformin
Better circadian immune function: melatonin
Tumor microenvironment
Reduced MDSCs: propranolol, sulforaphane
Reduced Tregs / CAF activity: melatonin, curcumin
Reduced angiogenesis: propranolol, EGCG, mebendazole
Reduced NF-κB / STAT3 inflammation: curcumin, EGCG, metformin
Reduced hypoxia / metabolic suppression: metformin
Reduced cancer stem cells: doxycycline, ivermectin, sulforaphane, metformin
In practical terms, the goal is to shift the tumor from an immunologically protected niche to a more inflamed, visible, and vulnerable target.
Conclusion
Repurposed drugs and nutraceuticals may improve anticancer immunity not by “boosting” the immune system indiscriminately, but by correcting the immune-metabolic dysfunction that tumors create. The most compelling adjunctive agents include metformin, propranolol, melatonin, vitamin D, curcumin, sulforaphane, EGCG, doxycycline, mebendazole, and ivermectin.
Their shared purpose is to restore immune competence: strengthen NK cells and cytotoxic T cells, reduce suppressive myeloid and regulatory cells, inhibit inflammatory signaling, normalize angiogenesis, target cancer stem cells, and improve the tumor microenvironment. This is the biological logic behind combining repurposed drugs and nutraceuticals with standard cancer therapy—not as alternatives, but as rational adjuncts designed to make the host less permissive to cancer.
If you’ve found value in this work, I’d encourage you to consider upgrading to a paid subscription. Your support allows me to continue researching, writing, and sharing these evolving insights—free from institutional constraints and focused entirely on what matters most: the patient. It also gives you access to deeper analyses, practical protocols, and a more direct line of communication as this field continues to move forward.

Medical Disclaimer: The discussion of repurposed medications and nutraceuticals in this article is intended to review the scientific literature and does not constitute a recommendation for self-treatment. Decisions regarding the use of off-label therapies should be made in consultation with a qualified healthcare professional familiar with the patient’s medical history and current treatment plan. Please see the full Medical Disclaimer on the introductory page to Marik’s Cancer & Metabolic Healing Playbook.
You can leave out propranolol.
See updated protocol: https://paulmarik.substack.com/p/approach-to-the-use-of-repurposed
Great article 👌