


This section builds on the evolutionary and metabolic framework described in Part 1 and applies those principles to specific drug rotations used in metabolic oncology protocols.
I. Why rotate Doxycycline and Mebendazole
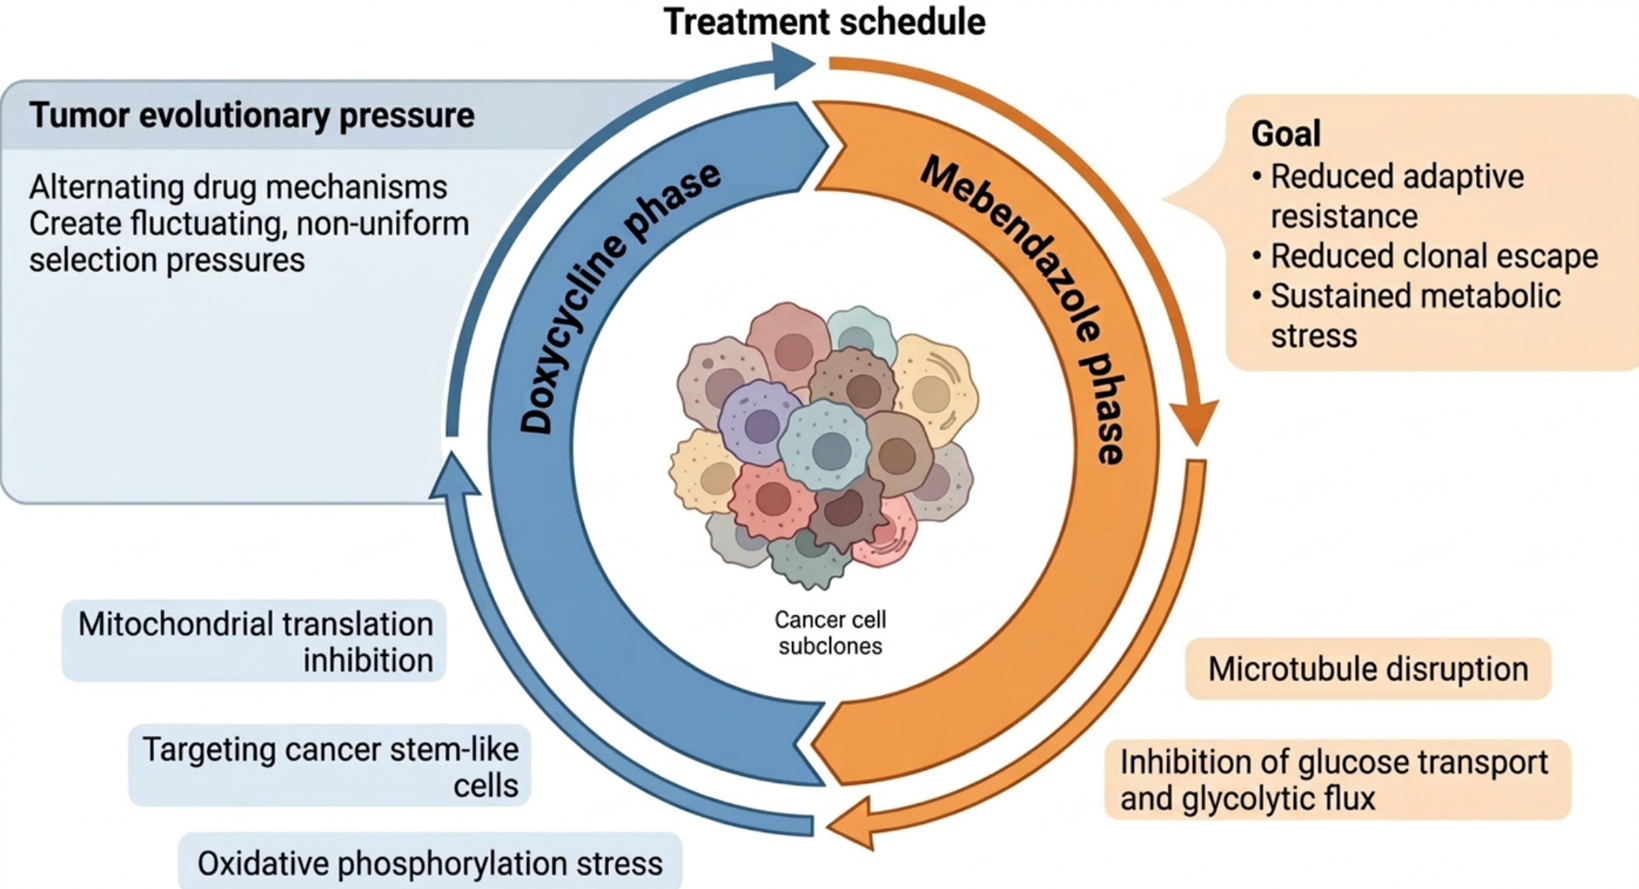
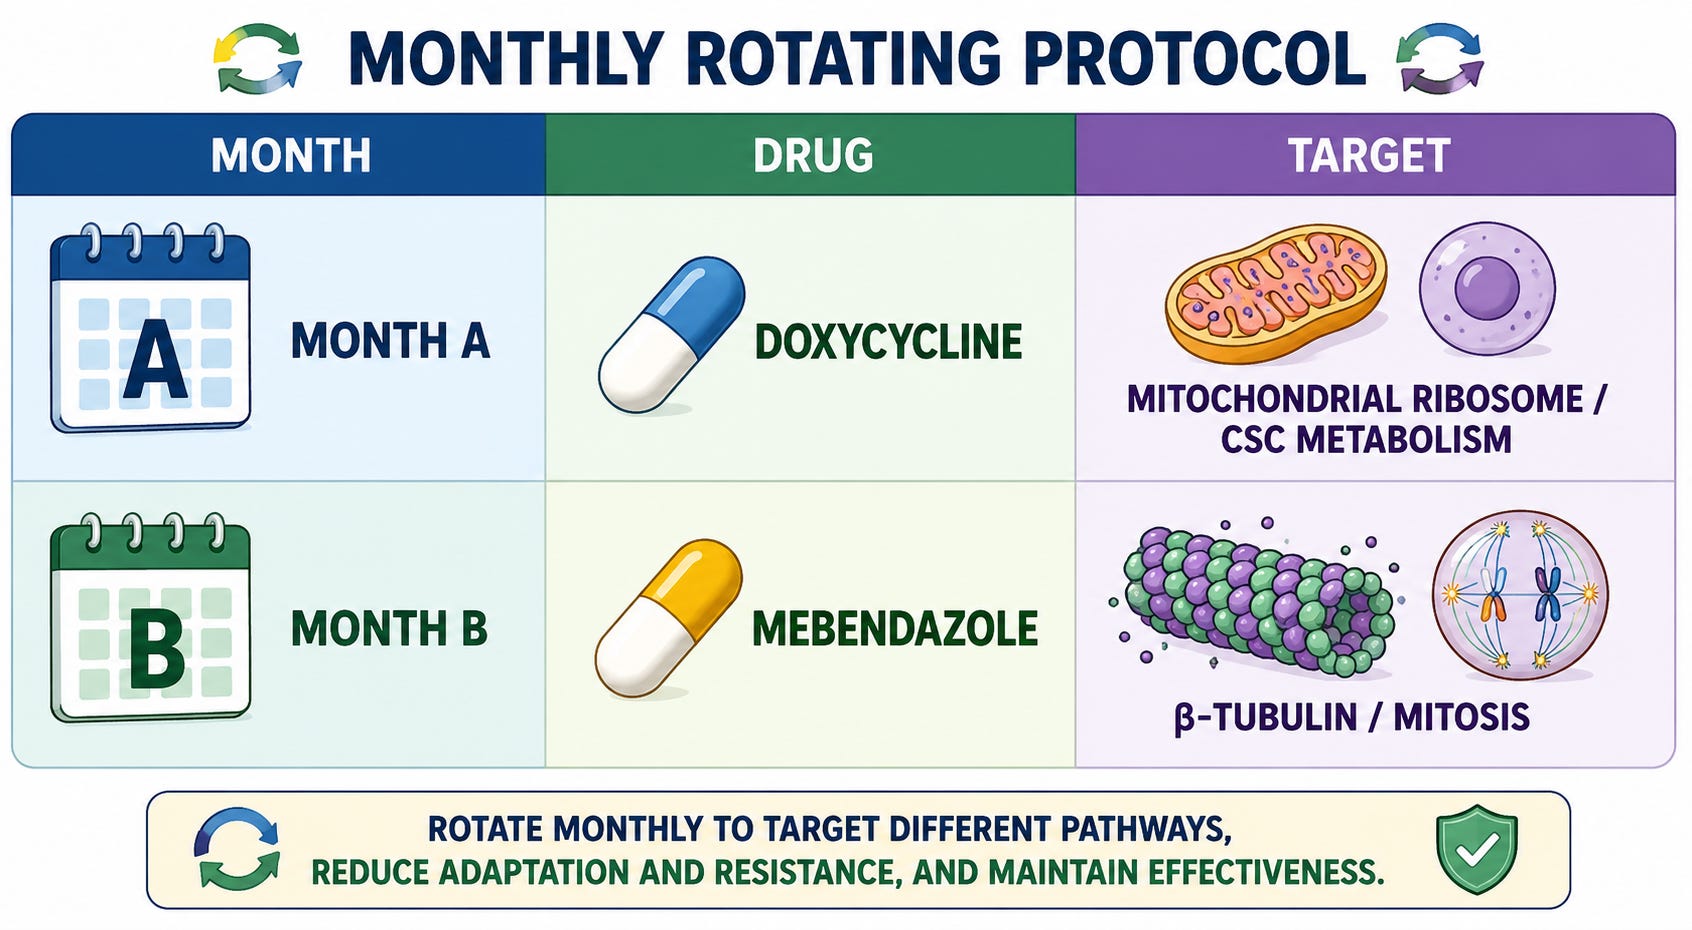
In the Care Oncology “Metrics” protocol (from Care Oncology Clinic), doxycycline is alternated monthly with mebendazole rather than given continuously together. Although the clinic has not published a mechanistic statement explicitly explaining this rotation, the rationale can be inferred from pharmacology, tumor biology, and resistance-management principles
Rotating Doxycycline and Mebendazole is a strategy intended to reduce the probability that cancer cells develop adaptive resistance under continuous metabolic pressure. The rationale is rooted in tumor evolutionary biology and biochemical pathway targeting.
Below are the key biochemical reasons.
1. They Target Different Cellular Systems
Doxycycline: mitochondrial translation inhibitor
Doxycycline inhibits the 70S-like mitochondrial ribosome, blocking mitochondrial protein synthesis.
Biochemical consequences:
↓ synthesis of mitochondrial electron transport chain proteins
↓ oxidative phosphorylation (OXPHOS)
↓ ATP production in mitochondria
preferential toxicity toward cancer stem cells (CSCs) which rely heavily on mitochondrial metabolism
This mechanism exploits the bacterial ancestry of mitochondria.
Key pathway pressure: Mitochondrial biogenesis / oxidative phosphorylation
Mebendazole: microtubule and mitotic inhibitor
Mebendazole binds β-tubulin, preventing microtubule polymerization.
Biochemical consequences:
mitotic spindle disruption
metaphase arrest
apoptosis during cell division
inhibition of intracellular trafficking
Additional reported effects:
inhibition of VEGFR2 signaling
suppression of Hedgehog signaling
impairment of tumor angiogenesis
Key pathway pressure: Cytoskeleton / mitosis / signaling pathways
2. Continuous Pressure on One Pathway Drives Metabolic Adaptation
Cancer cells evolve quickly. If a single metabolic vulnerability is attacked continuously:
Examples of adaptations under chronic doxycycline:
upregulation of glycolysis (Warburg compensation)
increased mitochondrial biogenesis
activation of mitophagy
selection of clones less dependent on OXPHOS
Conversely, chronic microtubule inhibition (as with mebendazole or taxanes) leads to:
β-tubulin mutations
tubulin isotype switching
efflux pump upregulation (P-glycoprotein)
Rotating agents changes the selective pressure, preventing a single resistant clone from dominating.
3. Evolutionary “Collateral Sensitivity”
Some adaptations that help a tumor resist one drug make it more vulnerable to another.
Examples:
Cells adapting to mitochondrial stress (doxycycline):
become more dependent on cytoskeletal transport and glycolysis
are more vulnerable to microtubule disruption
Cells adapting to microtubule stress (mebendazole):
rely more heavily on mitochondrial metabolism
become more susceptible to mitochondrial inhibitors
This phenomenon is known as collateral sensitivity cycling.
4. Cancer Stem Cell Suppression
Cancer stem cells (CSCs) are a major driver of relapse.
Evidence suggests:
Doxycycline → inhibits mitochondrial metabolism in CSCs
Mebendazole → disrupts mitosis and signaling pathways important for CSC survival (Hedgehog/Wnt)
Rotation helps prevent CSC metabolic reprogramming, which is a key mechanism of resistance.
5. Preventing Darwinian Clonal Selection
Tumors behave like evolving ecosystems.
Constant therapy:
Drug A → resistant clone expands → relapse
Rotating therapy:
Drug A pressure → switch → Drug B kills emerging resistant clones
This is conceptually similar to:
antibiotic cycling in infectious disease
adaptive therapy in oncology
6. Maintaining Multi-Axis Metabolic Stress
In metabolic oncology protocols (e.g., Care Oncology–style approaches):
Backbone agents such as:
Metformin
Berberine
apply chronic AMPK activation and mTOR suppression.
Rotating doxycycline and mebendazole adds alternating stress on:
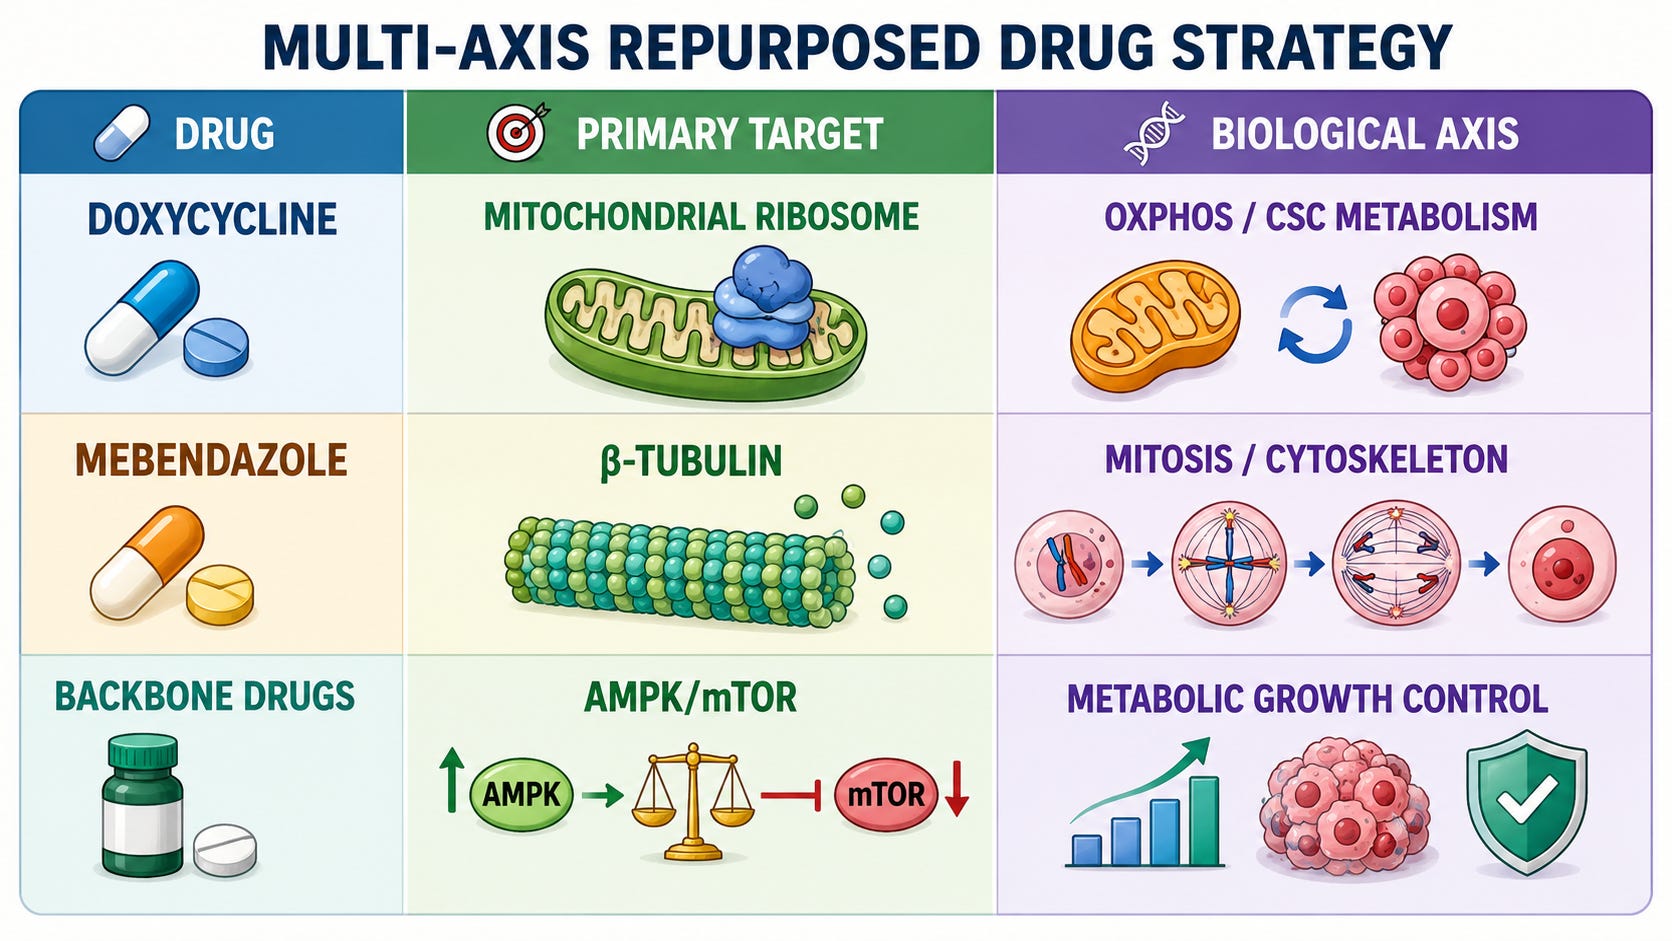
This multi-axis pressure reduces the probability of adaptive escape.
✅ In summary
The biochemical logic for rotating doxycycline and mebendazole is to:
Target distinct cellular systems (mitochondria vs microtubules).
Prevent metabolic adaptation to a single pathway blockade.
Exploit collateral sensitivity between mitochondrial and mitotic stress.
Suppress cancer stem cell survival pathways.
Reduce Darwinian selection of resistant tumor clones.
Figure 1. Rationale for alternating doxycycline and mebendazole
II. Should metformin and berberine be cycled separately in alternating months?
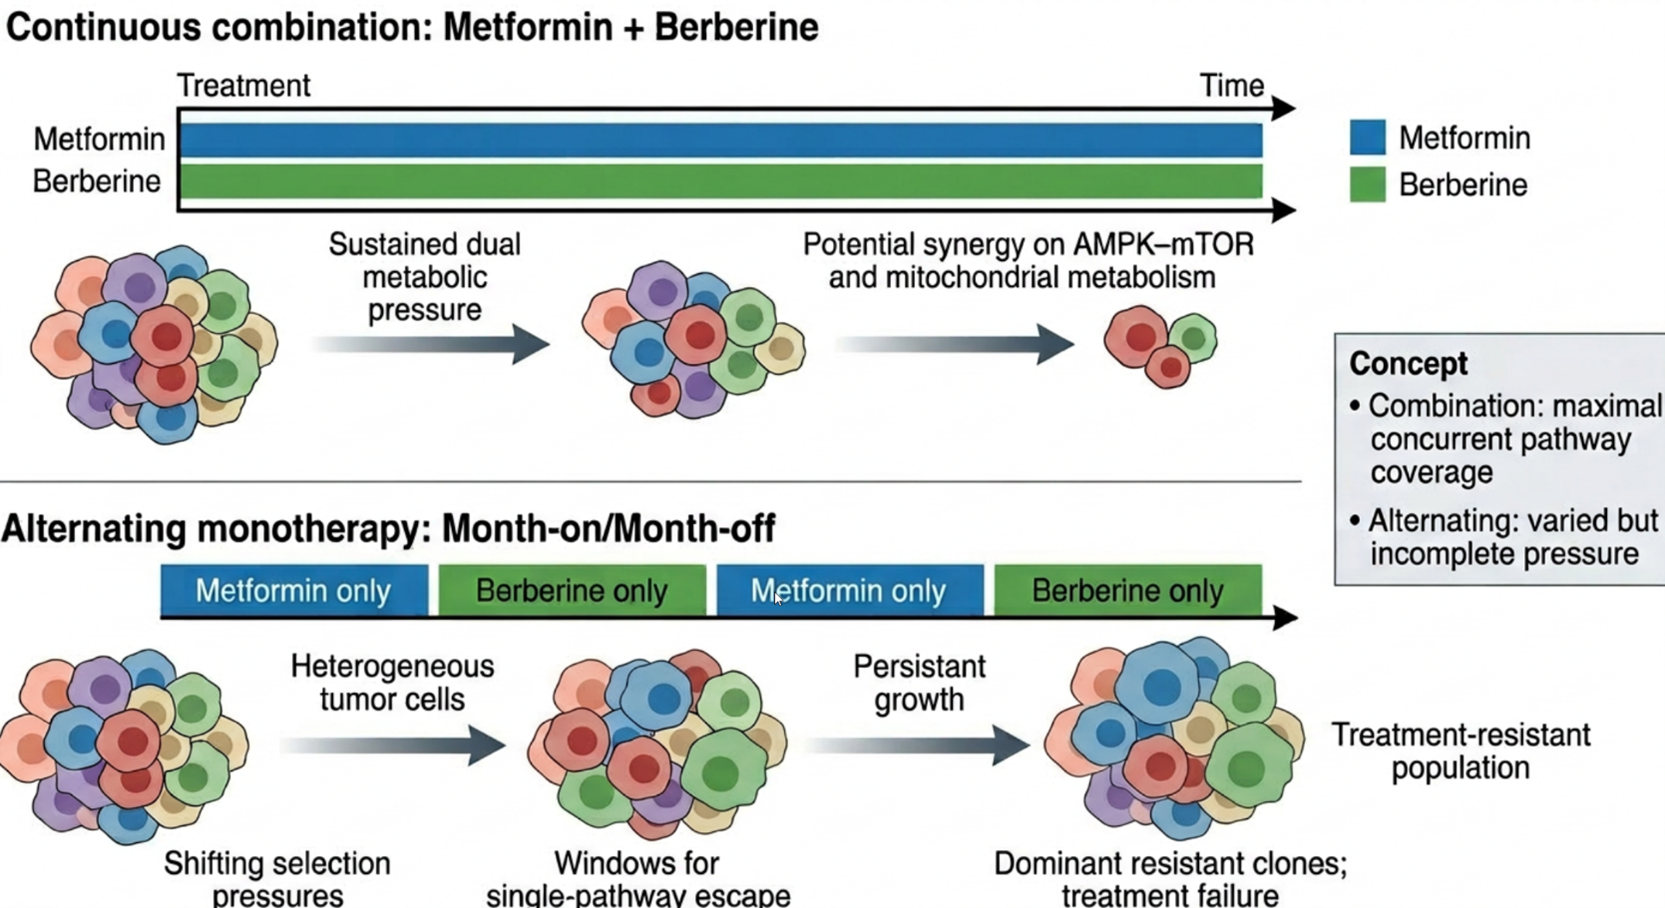
In general, there is little biochemical rationale for cycling Metformin and Berberine in alternating months. In most metabolic oncology strategies, they are used continuously together rather than rotated, because their mechanisms are complementary and resistance to them develops differently from classical cytotoxic drugs.
Below is the biochemical reasoning.
1. Both Drugs Target the Same Core Metabolic Axis
Both agents activate AMP-activated protein kinase (AMPK) and suppress mTOR signaling pathway.
Metformin
Primary mechanisms:
Inhibition of mitochondrial complex I
↑ AMP/ATP ratio
AMPK activation
↓ hepatic gluconeogenesis
↓ insulin and IGF-1 signaling
Berberine
Primary mechanisms:
Also inhibits mitochondrial complex I
AMPK activation
↓ insulin signaling
↓ lipid synthesis
microbiome effects
Because they converge on the same metabolic stress pathway, alternating them generally does not create a new evolutionary pressure for tumor cells.
2. Resistance Mechanisms Are Different From Cytotoxic Drugs
Cancer resistance to drugs like:
taxanes
platinum chemotherapy
targeted kinase inhibitors
often involves specific molecular mutations.
In contrast, metabolic drugs primarily create energetic stress, which tumors cannot easily bypass with a single mutation.
Typical adaptations include:
↑ glycolysis
↑ glutamine metabolism
↑ fatty acid oxidation
These adaptations occur gradually and are better countered by multi-pathway metabolic pressure, not cycling between two AMPK activators.
3. The Two Drugs Are Synergistic
There are several reasons they work better together than separately.
Complementary pharmacology
Metformin:
acts primarily in liver and systemic metabolism
Berberine:
has stronger direct cellular metabolic effects
influences gut microbiome and glucose absorption
Together they produce stronger:
AMPK activation
insulin suppression
metabolic stress on tumor cells.
4. Continuous Pressure Is Desirable
In metabolic oncology frameworks the goal is chronic metabolic restriction.
Think of it as lowering the tumor’s metabolic ceiling continuously.
Typical strategy:
Continuous backbone
metformin
berberine
vitamin D
melatonin
Rotating stressors
doxycycline
mebendazole
The rotation is applied to agents targeting different cellular systems, not to drugs that share the same metabolic pathway.
Practical Metabolic Oncology Model
Continuous backbone
Metformin
Berberine
Rotating stressors
Month A
Doxycycline
Month B
Mebendazole
This creates stable metabolic pressure with rotating vulnerability targeting.
✅ In short
Metformin and berberine generally should not be cycled because:
they hit the same metabolic pathway
they are synergistic when combined
resistance arises through metabolic adaptation rather than mutation
Therefore, they function best as a continuous metabolic backbone, while drugs that attack different cellular systems are rotated.
Figure 2. Rotation of Metformin and Berberine
III. Should Metformin AND Berberine be cycled in alternative months.
No. In most metabolic oncology frameworks metformin and berberine should not be cycled in alternating months. They are generally used continuously together as a metabolic backbone, while other agents that hit different cellular systems are rotated.
Below is the biochemical reasoning.
1. They Act on the Same Core Energy-Sensing Pathway
Both Metformin and Berberine activate the cellular energy sensor AMP-activated protein kinase. This produces downstream inhibition of mTOR signaling pathway, a major driver of tumor growth.
Mechanistic overlap:
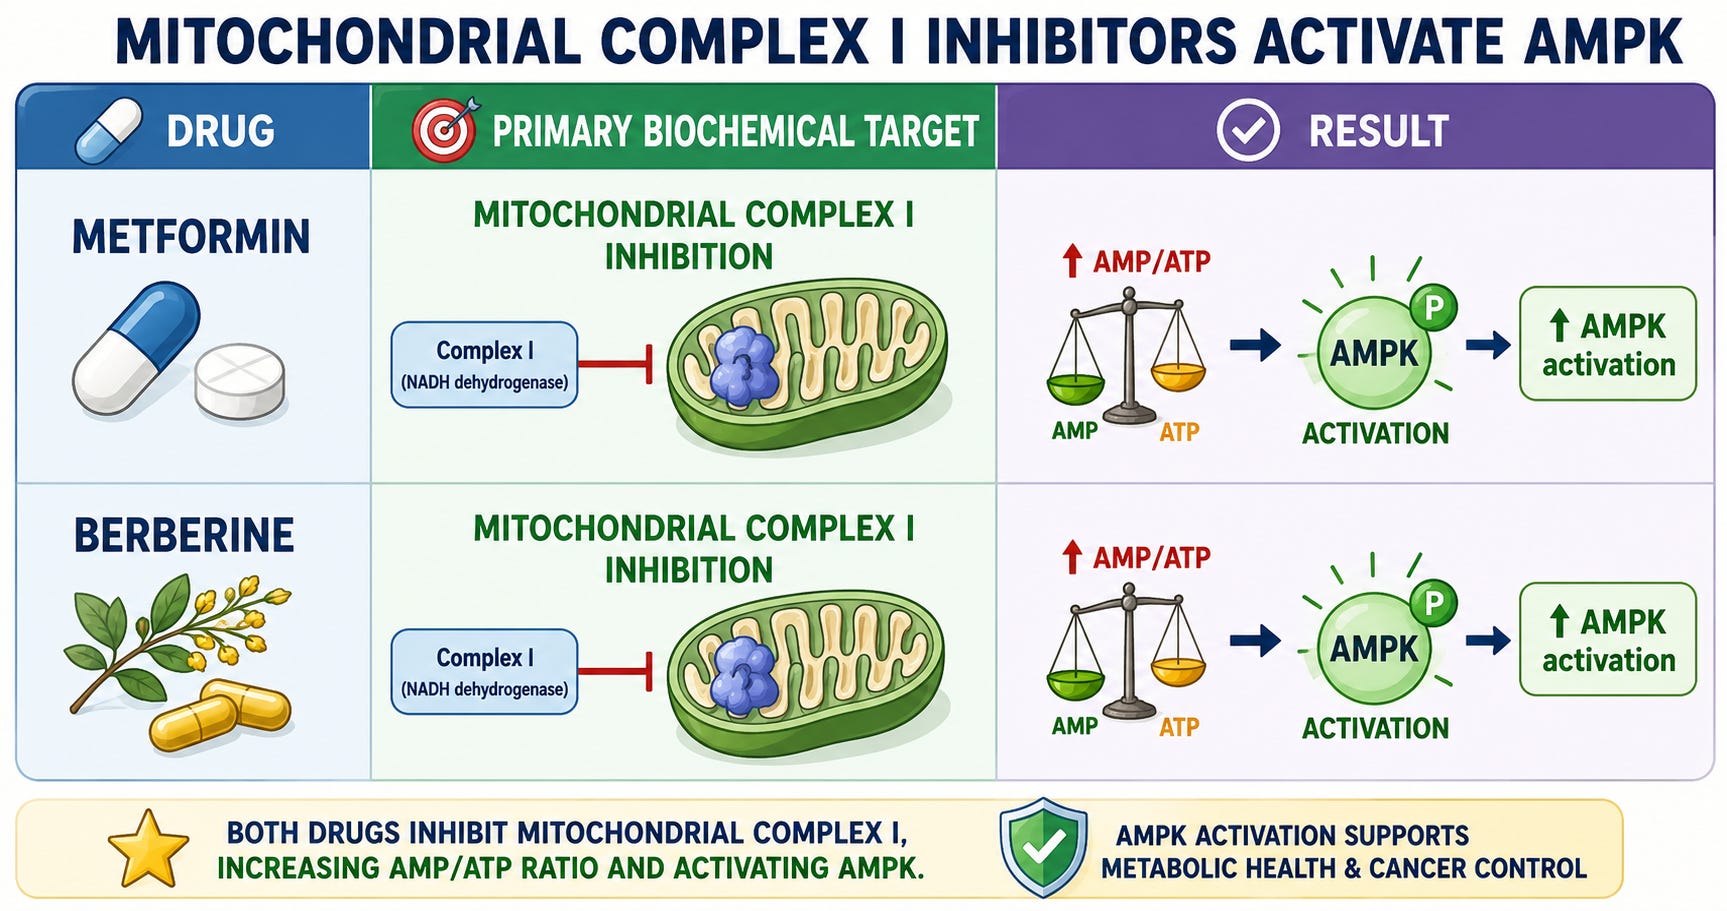
Because they converge on the same metabolic axis, cycling them would not meaningfully change tumor evolutionary pressure.
2. Their Effects Are Synergistic Rather Than Redundant
Although they converge on AMPK, their systemic actions differ:
Metformin
decreases hepatic gluconeogenesis
lowers circulating insulin
reduces IGF-1 signaling
improves insulin sensitivity
Berberine
enhances peripheral glucose uptake
modifies gut microbiome and glucose absorption
suppresses lipogenesis and inflammatory signaling
Together they produce stronger metabolic restriction than either alone.
3. Metabolic Therapies Work Best With Continuous Pressure
Unlike classical chemotherapy resistance (mutations in drug targets), resistance to metabolic therapy usually arises from gradual metabolic adaptation, such as:
increased glycolysis
glutamine dependence
fatty acid oxidation
These adaptations are better countered by persistent energy stress, not intermittent exposure.
Therefore, the goal is chronic AMPK activation and mTOR suppression.
4. Rotation Is More Logical for Drugs With Different Targets
Cycling works best when drugs hit different biological systems, for example:
Switching targets prevent stable resistance.
Cycling two AMPK activators does not provide this benefit.
5. Practical Strategy Used in Many Metabolic Protocols
Continuous backbone
Metformin
Berberine
Vitamin D
Melatonin
Rotating metabolic stressors
Doxycycline
Mebendazole
This maintains stable metabolic suppression while varying tumor stressors.
✅ In summary
Metformin and berberine should generally be taken together continuously because:
both activate the AMPK–mTOR metabolic axis
their systemic metabolic effects are synergistic
metabolic therapy requires constant energetic pressure rather than cycling
Cycling is better reserved for agents targeting different cellular structures (mitochondria, microtubules, signaling pathways).
IV. Should Ivermectin be cycled monthly
In most metabolic oncology strategies, Ivermectin is not usually cycled in strict alternating months the way Doxycycline and Mebendazole often are. Instead, ivermectin is commonly used continuously or in repeated dosing windows alongside the metabolic backbone.
The reason is biochemical.
1. Ivermectin Targets Multiple Cellular Pathways
Unlike doxycycline or mebendazole, which act primarily on one dominant cellular structure, ivermectin affects several tumor signaling systems simultaneously.
Major reported anticancer mechanisms include:
inhibition of Wnt signaling pathway
inhibition of PI3K/AKT/mTOR pathway
suppression of P-glycoprotein drug efflux pumps
induction of mitochondrial oxidative stress
disruption of tumor cell ion homeostasis and membrane potential
Because its activity is multi-targeted, tumors have more difficulty developing a single resistance mechanism.
2. It Does Not Target a Single Adaptive Axis
Rotating drugs is most useful when therapy applies strong pressure to one cellular system, which tumors can adapt to.
Ivermectin, however, simultaneously affects:
mitochondrial stress
Wnt signaling
ion channels
drug efflux pumps
Because the pressure is distributed across multiple systems, cycling to avoid resistance is less critical.
3. Ivermectin Often Acts as a Sensitizer
Another reason it is frequently used continuously is that ivermectin can increase tumor sensitivity to other therapies.
Reported effects include:
increased tumor susceptibility to chemotherapy
enhanced immunogenic cell death
possible potentiation of immune therapies
In this role, maintaining steady exposure may be advantageous.
✅ Summary
Ivermectin generally does not need to be rotated in alternate months because:
it targets multiple cancer pathways simultaneously
resistance mechanisms are less pathway-specific
it often functions as a sensitizing agent within multi-drug metabolic protocols
In contrast, drugs with single dominant targets (like doxycycline or mebendazole) benefit more from rotational scheduling.
V. Should omega-3 fatty acids be added to a multidrug regimen to reduce resistance?
Yes, there is a biochemical rationale for adding omega-3 fatty acids to a multidrug metabolic oncology regimen, primarily because they can reduce several mechanisms of tumor resistance and enhance treatment sensitivity. The effects are modest individually but potentially useful as part of a multi-axis metabolic strategy.
The key mechanisms are outlined below.
1. Membrane Remodeling and Drug Uptake
Omega-3 fatty acids—especially Eicosapentanoic acid (EPA) and Docosahexaenoic acid (DHA)—incorporate into tumor cell membranes.
This alters membrane properties:
↑ membrane fluidity
disruption of lipid rafts
improved drug penetration into cells
This can increase the intracellular concentrations of various anticancer agents.
2. Suppression of Drug Efflux Pumps
One mechanism of chemotherapy resistance is overexpression of P‑glycoprotein (MDR1).
Omega-3 fatty acids can:
decrease expression of drug efflux pumps
alter membrane transport dynamics
This can improve retention of therapeutic agents inside tumor cells.
3. Increased Lipid Peroxidation
Tumor cells enriched with omega-3 fatty acids become more susceptible to oxidative lipid damage. Polyunsaturated lipids such as DHA are particularly prone to peroxidation, which can trigger:
oxidative stress
mitochondrial damage
ferroptosis-like cell death pathways
This effect can increase sensitivity to therapies that generate reactive oxygen species.
4. Anti-Inflammatory Microenvironment
Chronic inflammation promotes tumor growth and therapy resistance.
Omega-3 fatty acids generate specialized pro-resolving mediators such as:
resolvins
protectins
maresins
These compounds reduce:
tumor-promoting inflammation
pro-angiogenic signaling
immune suppression within the tumor microenvironment.
5. Modulation of Oncogenic Signaling
EPA and DHA have been reported to influence several cancer-related signaling pathways, including:
NF‑κB
PI3K/AKT/mTOR pathway
Wnt signaling pathway
These effects may modestly suppress proliferation and survival signaling.
6. Interaction With Metabolic Therapy
Omega-3 fatty acids integrate reasonably well with metabolic oncology strategies involving agents such as:
Metformin
Doxycycline
Mebendazole
Ivermectin
Potential synergistic effects include:
enhanced oxidative stress
mitochondrial vulnerability
disruption of survival signaling pathways.
7. Practical Considerations
Common approaches in metabolic oncology protocols involve:
combined EPA + DHA supplementation
doses roughly 2–4 g/day of total omega-3 fatty acids
Higher doses may increase bleeding risk, particularly in patients taking anticoagulants.
✅ Summary
Omega-3 fatty acids may help reduce therapeutic resistance by:
improving drug uptake
inhibiting drug efflux pumps
increasing oxidative vulnerability
suppressing inflammatory tumor signaling
modulating oncogenic pathways.
Their effects are supportive rather than dominant, but they can contribute to a multi-axis metabolic pressure strategy designed to make tumors metabolically inflexible.
Lipid Peroxidation and Ferroptosis
Many tumors exhibit a specific vulnerability to lipid peroxidation, meaning that when their membranes contain highly unsaturated lipids they become susceptible to a form of cell death called Ferroptosis. This is one of the reasons omega-3 fatty acids can sometimes enhance anti-cancer therapies.
The Lipid Peroxidation Vulnerability of Cancer Cells
1. Cancer Cells Already Live Under High Oxidative Stress
Most tumors generate large amounts of reactive oxygen species (ROS) because of:
rapid proliferation
mitochondrial dysfunction
oncogenic signaling (RAS, MYC, PI3K pathways)
To survive this stress, tumors rely heavily on antioxidant systems such as:
Glutathione
Glutathione peroxidase 4 (GPX4)
These defenses prevent lipid damage from reaching lethal levels.
2. Polyunsaturated Lipids Are Highly Peroxidizable
Omega-3 fatty acids such as Docosahexaenoic acid (DHA) and Eicosapentaenoic acid (EPA) contain multiple double bonds. This makes them extremely vulnerable to oxidative attack.
When these fatty acids are incorporated into tumor membranes:
lipid radicals form easily
chain-reaction lipid peroxidation occurs
membranes become structurally unstable.
3. Ferroptosis: When Lipid Peroxidation Becomes Lethal
If lipid peroxidation exceeds the cell’s antioxidant capacity:
membrane phospholipids undergo catastrophic oxidation → cell death.
This process is called ferroptosis, characterized by:
iron-dependent lipid oxidation
mitochondrial shrinkage
plasma membrane rupture.
Cancer cells that rely heavily on antioxidant defense systems can therefore become selectively vulnerable to ferroptosis.
4. Why Omega-3 Fatty Acids Can Amplify This Process
Supplemental omega-3 fatty acids increase the amount of peroxidizable substrate inside tumor cells.
Conceptually:
More polyunsaturated lipids
+
oxidative stress
+
iron
↓
lipid peroxidation cascade
↓
ferroptotic cell death
This can amplify therapies that generate oxidative stress.
5. Therapies That Can Synergize With Lipid Peroxidation
Several anticancer strategies increase oxidative stress and may interact with omega-3–driven lipid peroxidation: Examples include agents that impair mitochondrial function or antioxidant defenses, such as:
Doxycycline
Ivermectin
Metformin
Some chemotherapies and radiation therapy also increase ROS production.
6. Why Normal Cells Are Often Less Affected
Normal tissues usually tolerate lipid peroxidation better because they have:
stronger antioxidant systems
lower baseline oxidative stress
slower proliferation rates
Tumors often operate close to their oxidative limits, which creates a therapeutic window.
The Concept in One Sentence
Omega-3 fatty acids load tumor membranes with oxidation-prone lipids, so when oxidative stress rises the cancer cell crosses a threshold and dies through ferroptosis.
✅ Key insight
The goal is not that omega-3 fatty acids directly kill cancer cells.
Rather, they increase the fragility of tumor membranes, making cancer cells much more susceptible to oxidative or metabolic therapies.
VI. Should the following phytochemicals be rotated to prevent drug resistance: curcumin, EGCG, sulforaphane, and resveratrol?
In most metabolic oncology frameworks, rotating these phytochemicals is generally not necessary to prevent resistance. Agents such as Curcumin, Epigallocatechin gallate, Sulforaphane, and Resveratrol are usually taken continuously rather than rotated.
These agents are pleiotropic, low-affinity, multitarget modulators, not narrow single-node inhibitors, which likely reduces classic target-specific resistance selection pressure compared with kinase inhibitors or cytotoxics. To date, there are no clinical or robust preclinical data showing that continuous use of curcumin, EGCG, sulforaphane, or resveratrol leads to specific resistant clones that can be avoided by periodically switching among these four.
The biochemical reasons are different from those for classical anticancer drugs.
1. They Are Multi-Targeted Signaling Modulators
Unlike targeted drugs that inhibit a single molecular pathway, these phytochemicals influence dozens of signaling systems simultaneously.
Common pathways affected include:
NF-κB
PI3K/AKT/mTOR pathway
Wnt signaling pathway
Nrf2 pathway
Because these compounds act on broad regulatory networks, tumors have difficulty developing classic single-mutation resistance.
2. Their Role Is Supportive Rather Than Dominant Cytotoxicity
Phytochemicals typically exert modulatory effects rather than strong direct cytotoxicity.
Their main functions include:
reducing inflammatory signaling
modulating oxidative stress
suppressing pro-survival pathways
enhancing apoptosis signaling
improving sensitivity to other therapies
This means their benefit usually comes from persistent signaling pressure, not intermittent high-intensity exposure.
3. They Often Work Synergistically
These compounds influence overlapping but complementary pathways.
Examples:
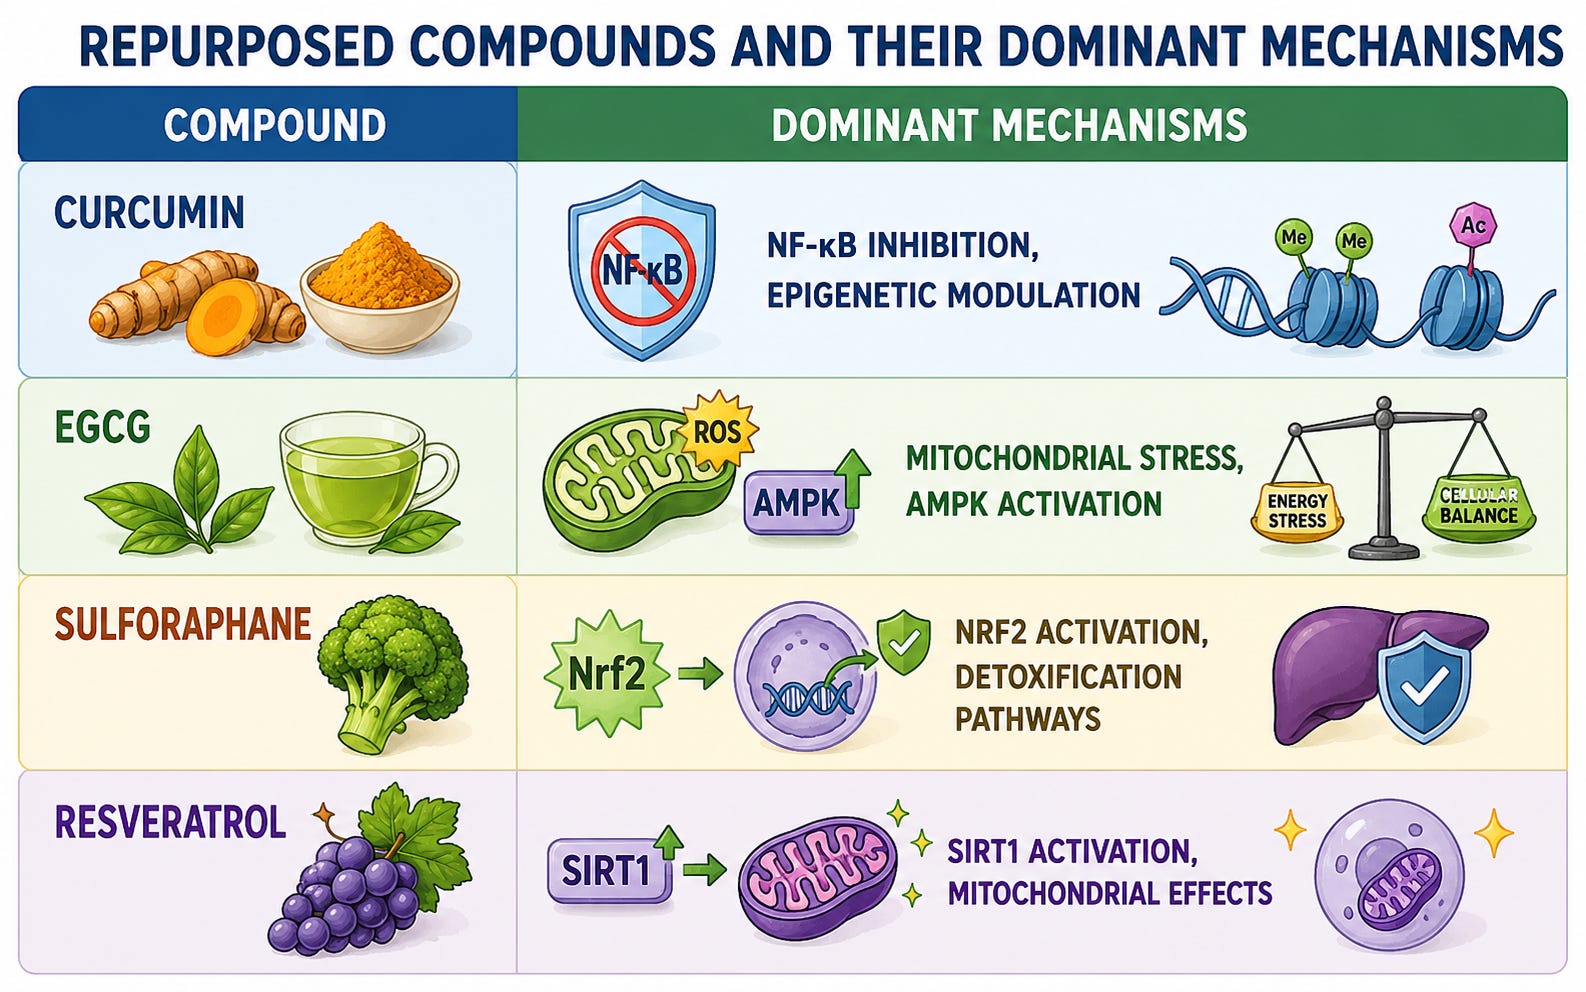
Taken together they create broad suppression of pro-tumor signaling networks.
4. Continuous Exposure Maintains Signaling Suppression
Many of the pathways affected by phytochemicals (such as NF-κB) are dynamic and rapidly reactivated.
If exposure stops:
inflammatory signaling rebounds
survival pathways reactivate
metabolic signaling increases
For this reason, steady exposure may be more effective than cycling.
5. Rotation May Still Be Used for Practical Reasons
Some clinicians rotate phytochemicals for:
gastrointestinal tolerance
simplifying large supplement regimens
theoretical metabolic diversity
However, there is little biochemical evidence that monthly cycling prevents resistance.
Practical Strategy Often Used
Continuous backbone phytochemicals
Curcumin
Epigallocatechin gallate
Sulforaphane
Resveratrol
These are often combined with metabolic drugs such as:
Metformin
Doxycycline
Mebendazole
✅ Summary
These phytochemicals generally do not need to be rotated because:
they affect multiple signaling pathways simultaneously
resistance mechanisms are unlikely to arise from a single mutation
their role is persistent signaling modulation rather than direct cytotoxicity
Thus, they are usually used as continuous background metabolic modulators rather than cyclic therapies.


Thank you, Dr. Marik. I have learned so much. I was dx with Malignant Psoas Syndrome in Mar 2024. It is very rare. The AI which I used found 50 cases worldwide since 1990 when it was named. No survivors past 36 months. In Sept of 2024, I started using what I learned from you. In Jan of 2026, it suddenly doubled and spread. Just in time, I started learning from your Cancer Resistance and The Metabolic Trap. I was able to get everything and titrate doses up by Apr 27. However, a few weeks before that I was doing very poorly. I came very close to signing up for hospice. Then, on Apr 19 I started feeling better and have felt better every day since. Next PET is in July. If the results are not very good, we will use Dr. Pierre Kory’s Leading Edge Clinic. Finally, I will be able to have a medical team that can help me use your research. I think the Lord, then you, should get credit for the fact that I have survived so long and am doing well.
Thank you, Dr. Marik. Here is hoping this works with my family member. This is explained so clearly. I, too, wondered as I went through how one can do it but I believe it is really important for said person. So well explained. The “C” word changes the thought pattern of anyone seeking help outside the box or inside the box with chemotherapy. I watched my brother suffer from cancer and it never went to a vital organ. It was close but never crossed over to the liver which is the primary metastasis from colon cancer. He didn’t have these options. I am so hoping this changes mainstream oncology. Also, thank you for all the time you have given to finding an answer to cancer. Time for a cure that gives back to the patient.