

What Steve Kirsch taught his Cardiologist!
“Don’t let your doctor fool you, coronary artery disease is not caused by cholesterol, it is a metabolic disease” - Paul

For more than half a century, we have told patients a simple story:
Eat less fat. Lower your cholesterol. Prevent heart disease.
It is a story repeated in medical schools, reinforced in guidelines, and echoed in nearly every clinic visit. And yet—despite decades of aggressive cholesterol lowering—coronary artery disease remains the leading cause of death worldwide.
Something doesn’t add up.
Because when you look closely at the data, a different pattern emerges—one that has been hiding in plain sight.
Patients with normal cholesterol still suffer heart attacks.
Patients on statins still progress.
And perhaps most strikingly—patients with insulin resistance, even with “normal” cholesterol levels, carry a dramatically increased risk of cardiovascular events.
This forces an uncomfortable but necessary question:
What if coronary artery disease is not primarily a cholesterol disease at all?
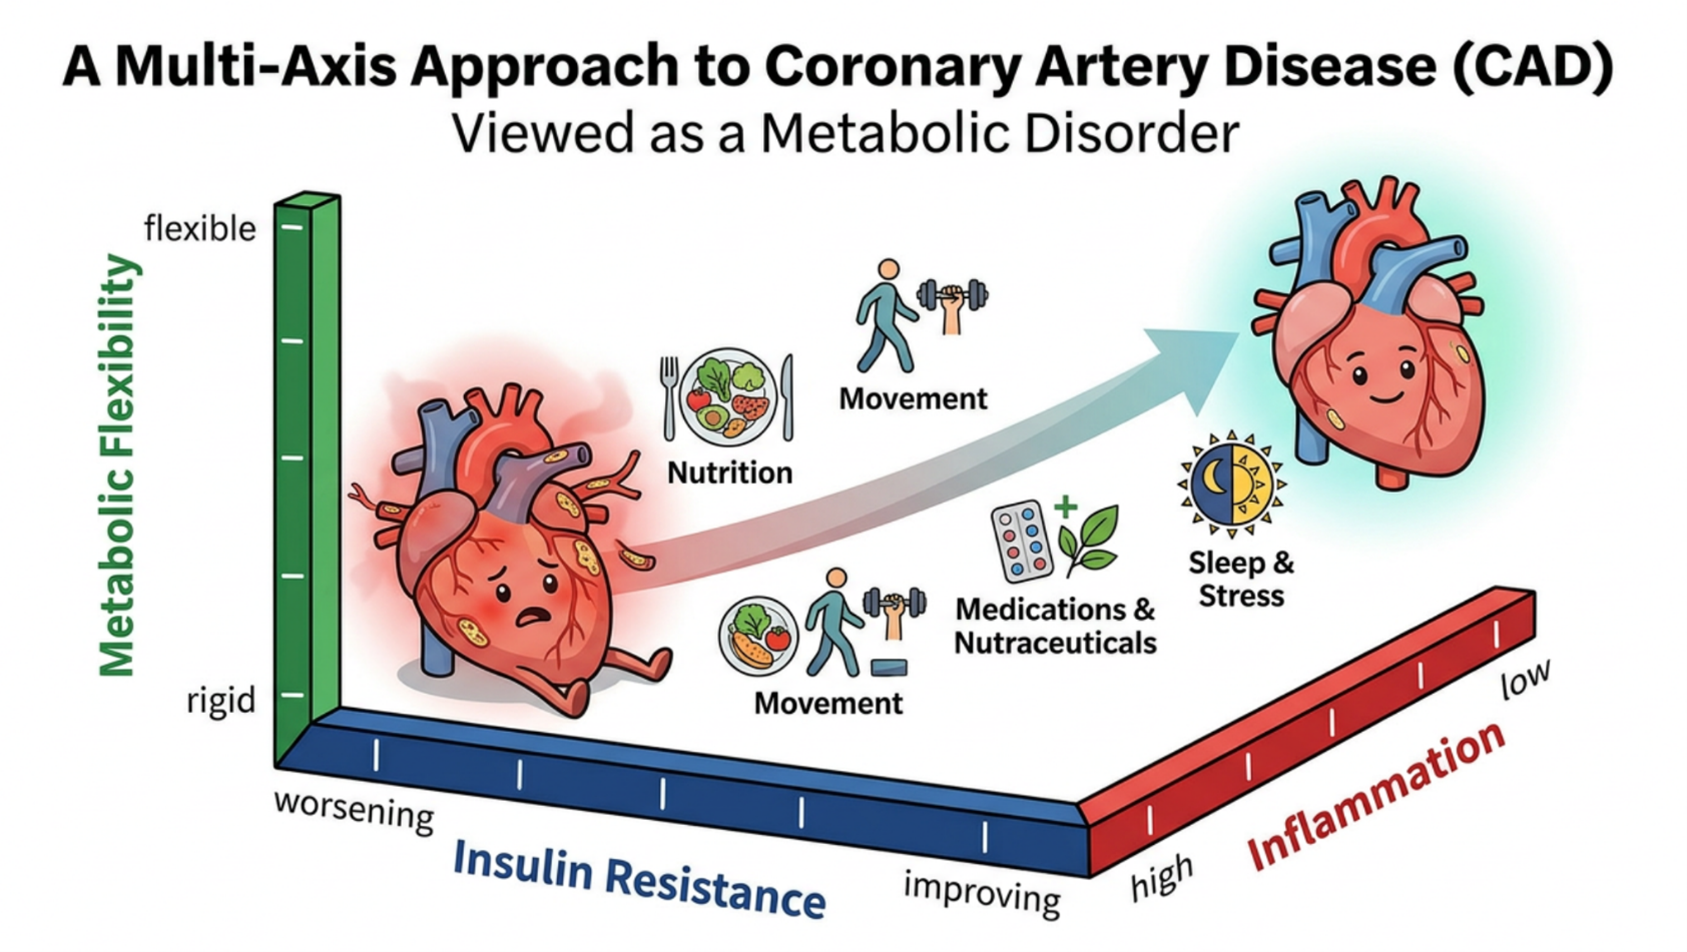
What if it is, instead, a disorder of metabolism—driven by insulin resistance, chronic inflammation, and energy dysregulation at the cellular level?
If that is true—and the evidence increasingly suggests that it is—then our entire framework for prevention and treatment needs to change.
Not slightly. Fundamentally.
Coronary Artery Disease as a Metabolic Disorder
Historical Perspective: The Lipid Hypothesis
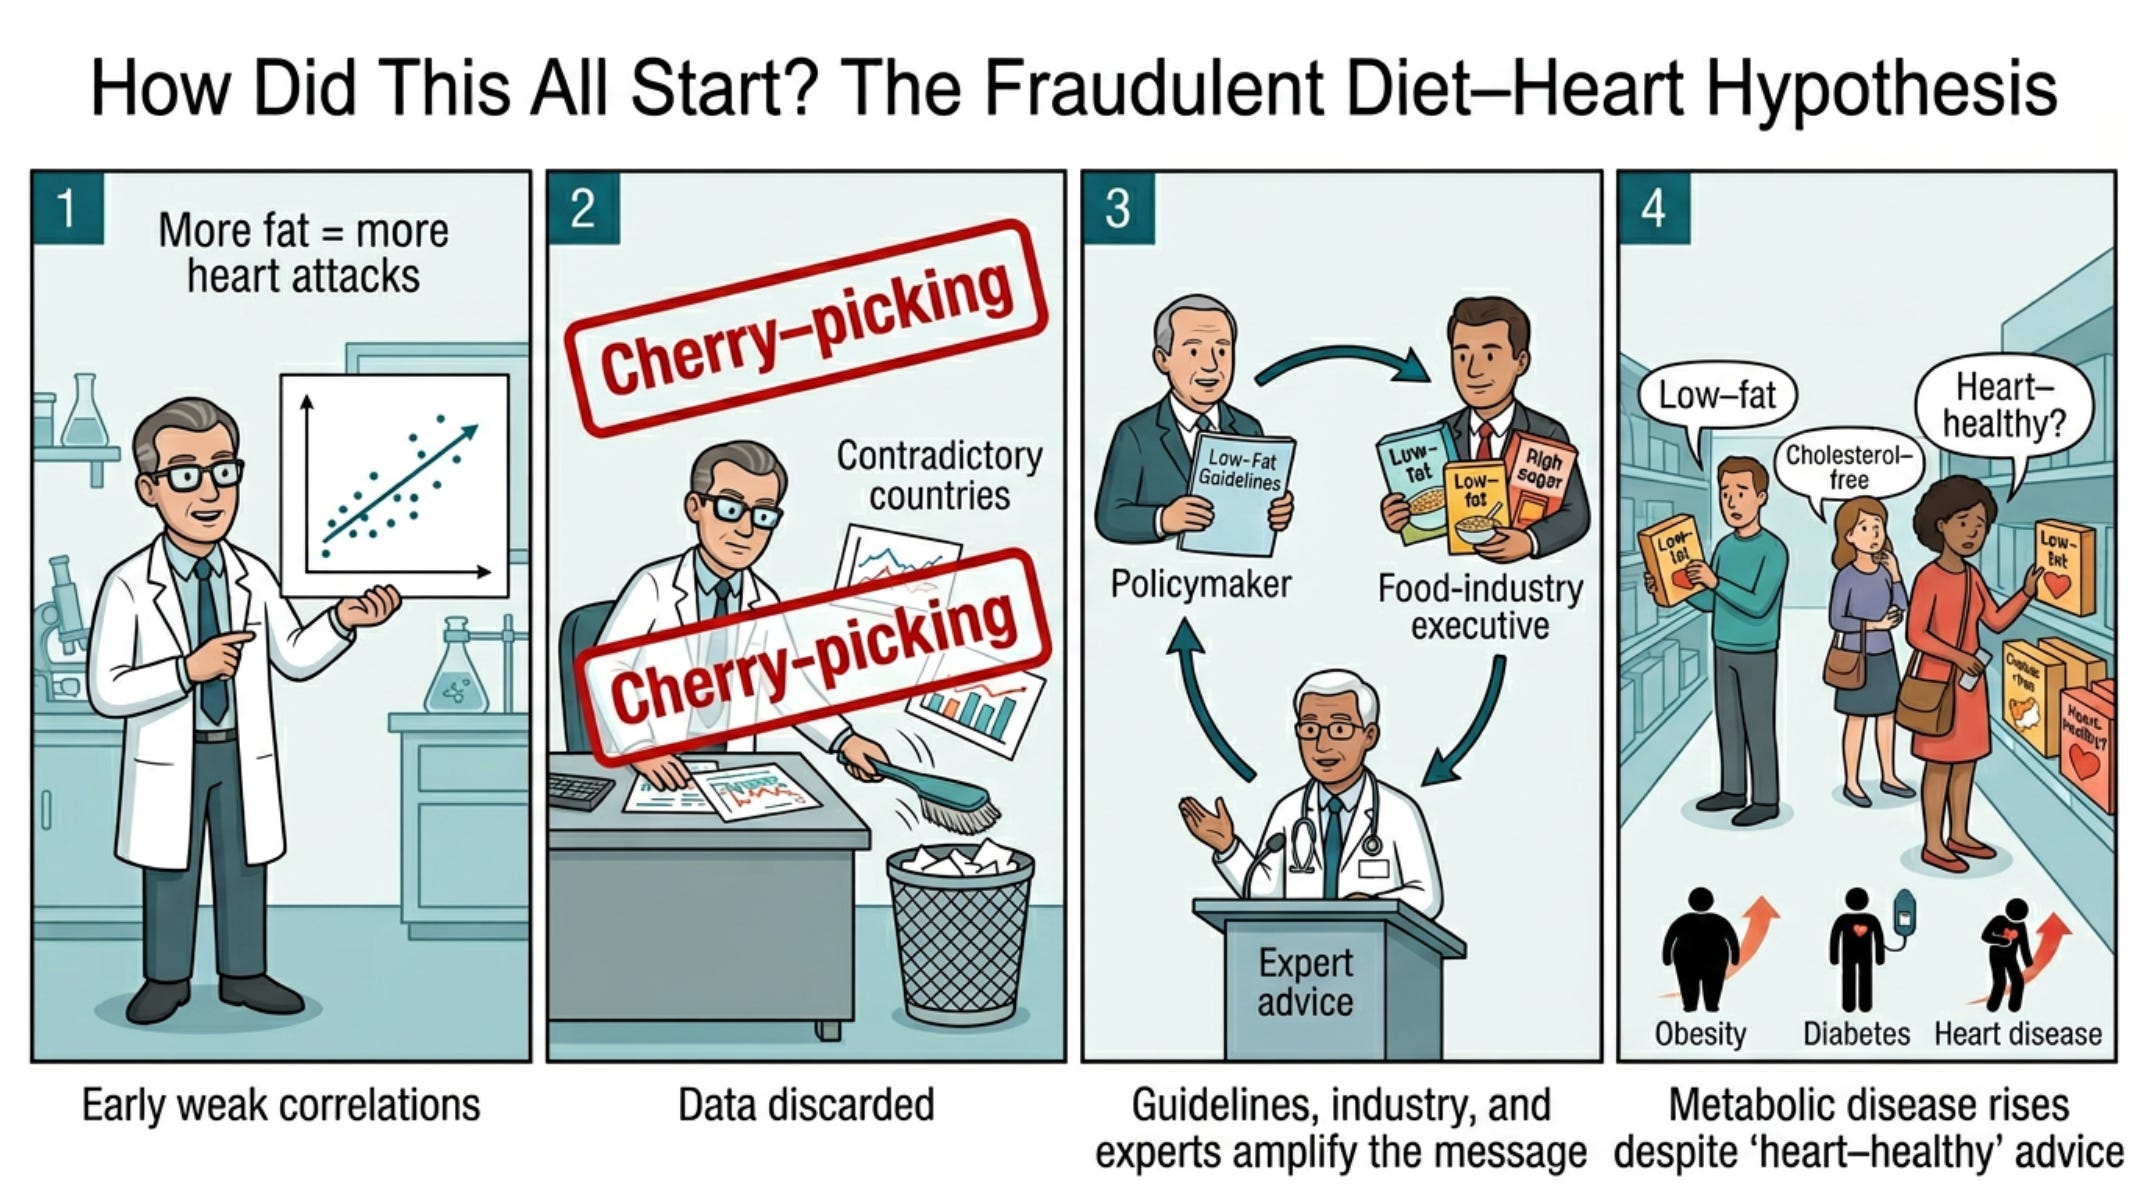
The lipid hypothesis originated with Ancel Keys’ Seven Countries Study in the 1950s, linking dietary saturated fat to elevated serum cholesterol and myocardial infarction. This framework guided decades of dietary and pharmacologic interventions focused on reducing serum LDL. Statins, developed from the 1970s onward, became the cornerstone of CAD prevention, significantly reducing event rates but never fully eliminating residual risk.
Figure 1.
Metabolic Clues and Contradictions
Despite widespread cholesterol control, the prevalence of CAD remained high—especially among individuals with obesity, metabolic syndrome, or type 2 diabetes. Approximately two‑thirds of patients presenting with myocardial infarction have features of insulin resistance, even when LDL levels are not markedly elevated. Moreover, LDL particle quality (small, dense LDL) correlates more strongly with risk than total LDL concentration, hinting at underlying metabolic dysregulation rather than simple lipid overload.
Pathophysiology: Insulin Resistance and Vascular Metabolism
Insulin resistance alters endothelial function, vascular inflammation, and lipid trafficking through several mechanisms:
Endothelial dysfunction: Hyperinsulinemia and hyperglycemia impair nitric oxide signaling, reduce vasodilation, and increase vascular stiffness.
Oxidative stress and inflammation: Excess intracellular glucose and free fatty acids promote mitochondrial dysfunction, generating reactive oxygen species and activating NF‑κB–driven inflammatory cascades.
Altered lipoprotein metabolism: Insulin resistance increases hepatic VLDL production, elevates triglycerides, and fosters the formation of small, dense LDL particles prone to oxidation and arterial retention.
Foam cell formation: The combination of endothelial injury, oxidized LDL, and macrophage dysfunction accelerates the formation of atherosclerotic plaques.
In essence, CAD represents the vascular consequence of systemic insulin resistance and altered energy substrate handling.
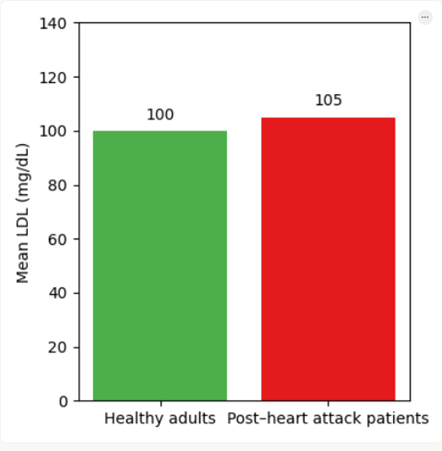
Figure 2. Graph comparing approximate mean LDL levels of U.S. healthy adults and patients with prior heart attack (CAD).(1)
The Real Disease: A Metabolic Storm
When you connect the dots, a clear pattern emerges.
Coronary artery disease clusters with:
Metabolic syndrome
Type 2 diabetes
Obesity
Hypertension
Fatty liver disease
These are not separate conditions.
They are manifestations of the same underlying disorder: Metabolic dysfunction.
Evidence from Clinical and Epidemiologic Studies
Metabolic syndrome and CAD risk: Each component—abdominal obesity, elevated triglycerides, low HDL, hypertension, and hyperglycemia—predicts CAD even after adjusting for LDL cholesterol.
Insulin resistance as a prognostic biomarker: HOMA‑IR, fasting insulin, and postprandial glucose excursions correlate more tightly with coronary events than LDL levels in multiple prospective cohorts.
Interventional evidence: Low‑carbohydrate or ketogenic diets, which reduce insulin secretion, often improve lipid subfractions (lower triglycerides, raise HDL, reduce LDL particle number) and markers of endothelial health. Conversely, diets high in refined carbohydrates elevate small dense LDL and inflammatory markers.
Pharmacologic parallels: Metformin and GLP‑1 receptor agonists, which improve insulin sensitivity, demonstrate cardiovascular protection independent of LDL lowering.
Integrative Mechanistic Model
CAD may best be conceptualized as a metabolic vascular disease initiated by chronic energy surplus and insulin resistance. Hyperinsulinemia drives smooth muscle proliferation, inflammation, and plaque instability. The arterial wall becomes metabolically inflexible, reliant on glucose rather than fatty acid oxidation, fostering local oxidative stress. This model unifies lipid abnormalities, hypertension, inflammation, and thrombosis as downstream effects of a primary metabolic disturbance.
Implications for Prevention and Therapy
Reframed dietary guidance: Emphasis on carbohydrate restriction, whole‑food nutrition, and intermittent fasting to restore insulin sensitivity rather than blanket reduction of dietary fat.
Expanded biomarker panels: Include fasting insulin, triglyceride/HDL ratio, and continuous glucose monitoring for earlier metabolic risk detection.
Pharmacologic integration: Several agents improve metabolic function and may reduce cardiovascular risk. These therapies target the underlying metabolic dysfunction, not just lipid levels:
Metformin – improves insulin sensitivity and reduces hepatic glucose production
GLP-1 receptor agonists – improve glycemic control and promote weight loss
SGLT2 inhibitors – reduce cardiovascular events and heart failure risk
Selective use of statins
Lifestyle as medicine: Regular exercise, circadian alignment, and stress modulation as key modulators of insulin sensitivity.
Reframing coronary artery disease as a metabolic disorder does more than challenge dogma—it shifts medicine toward root‑cause prevention. The arteries, like the rest of the body, are metabolically alive, and when energy metabolism fails, their pathology follows.
The Statin Myth
According to the AHA, ACC etc. (and all those institutions supported by Pharma) humans are genetically deficient in statins and therefore all adult need to be taking a statin. According to integrative clinicians” statins are a hoax” and no humans should ever take a statin. It is likely that the truth lies somewhere between these two extremes. – Paul.

Figure 3.
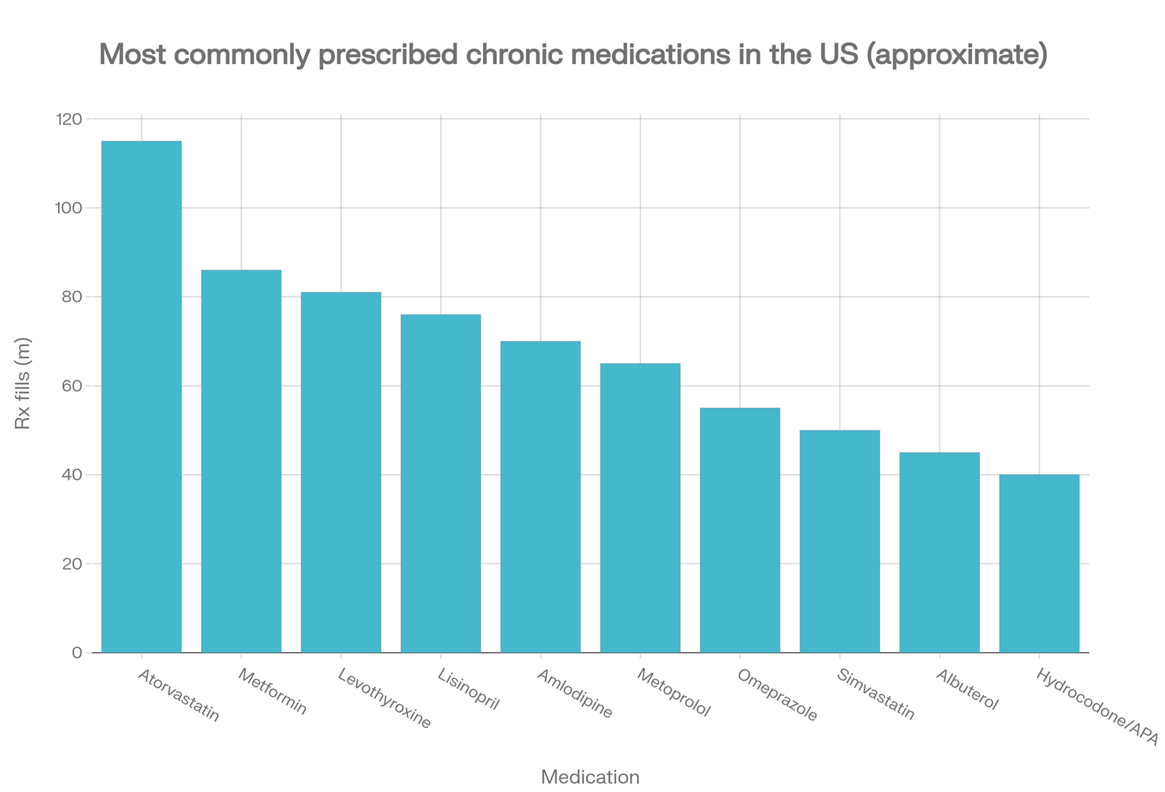
Statins clearly reduce cardiovascular events and mortality in higher‑risk patients with established CAD, but their benefit in low‑risk primary prevention is modest and often overstated; the “statin myth” is not that statins never work, but that they are a universal solution to coronary artery disease.
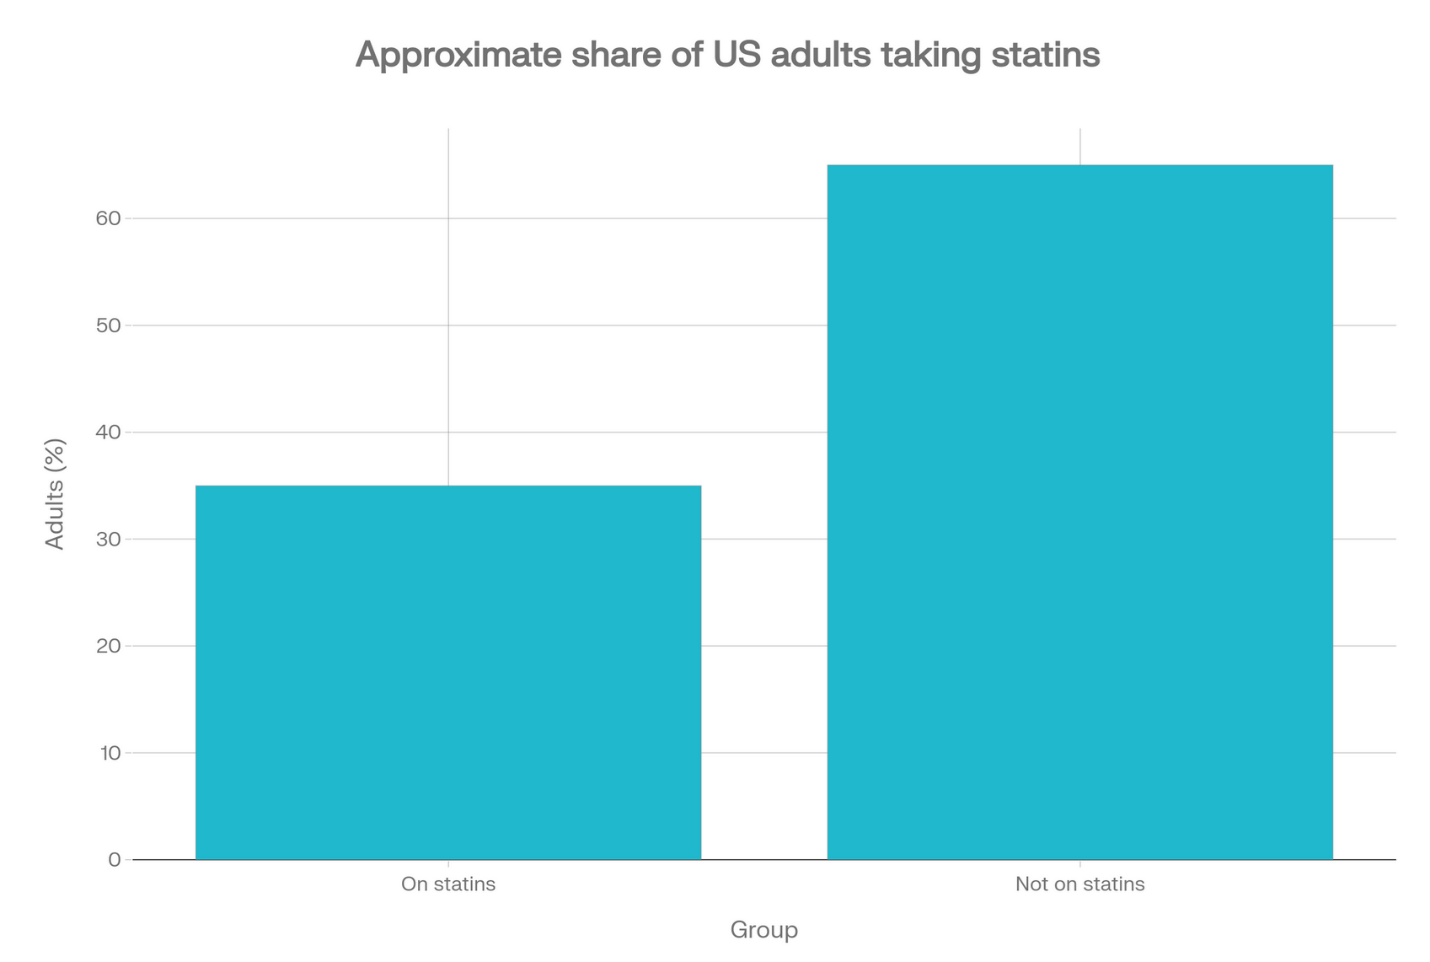
The “statin myth” has two opposing narratives. One claims statins are near‑miraculous drugs that everyone over middle age should take, while the other claims they are ineffective, dangerous, and purely pharma‑driven. A nuanced reading of the evidence shows a more complex reality: statins provide clinically important benefit in secondary prevention and in selected high‑risk primary‑prevention patients, but their absolute benefit in low‑risk populations is small, with non‑trivial side‑effects and significant residual risk that demands attention to metabolic drivers of CAD.
Figure 4.
Do Statins Have a Role in CAD?
Yes, for secondary prevention: In patients with prior MI, angiographically proven CAD, or acute coronary syndrome, statins reduce mortality and recurrent events and act synergistically with antiplatelets, beta‑blockers, ACE inhibitors, and lifestyle measures.(2)
Statins are recommended and beneficial in asymptomatic patients with angiographically proven CAD, because any documented coronary atherosclerosis is treated as chronic coronary disease (secondary prevention) rather than “primary prevention”.
No, for primary prevention. The US Preventive Services Task Force Recommends (USPSTF) statin use for the prevention of CVD events and all-cause mortality in adults aged 40 to 75 years with no history of CVD and who have 1 or more CVD risk factors (ie, dyslipidemia, diabetes, hypertension, or smoking) and an estimated 10-year CVD event risk of 10% or greater. (2) However, a Meta-analysis of 11 Randomized Controlled Trials Involving 65 229 high risk participants which investigated the effect of statins on all-cause mortality contradicts this recommendation.(3) This meta-analysis did not find evidence for the benefit of statin therapy on all-cause mortality in high-risk primary prevention; and therefore challenges the recommendations of the USPSTF.
No, for primary prevention in low‑risk individual. For people with low 10‑year risk, the absolute benefit is very small, and labeling millions as “statin‑deficient” while under‑emphasizing diet, exercise, weight loss, and insulin‑sensitivity‑focused strategies embodies the real “statin myth.”(4)
In high-risk individuals’ primary prevention with a statin should be individualized, however lifestyle changes should always be considered the first treatment approach. A practical approach for a high‑risk primary‑prevention patient (AHA, ACC, UPSTF, etc.) includes:
Calculate 10‑year ASCVD risk and classify (borderline, intermediate, high) using a standard tool based on pooled cohort equations.(5)
For high risk (≥20% or “risk‑equivalent” such as LDL ≥190, diabetes plus additional risk factors), recommend a statin aiming for a significant LDL‑C reduction, reassessing lipids and tolerance in 6–8 weeks.
Discuss absolute risk reduction, potential side effects, pill burden, and alternatives (lifestyle, non‑statin agents if statin‑intolerant) so the patient.
Current evidence suggests the LDL-C does not cause cardiovascular disease. (6) Experimental and clinical data show statins reduce pro‑inflammatory cytokines, oxidative stress, improve endothelial NO bioavailability, stabilize plaque, and have anti‑thrombotic effects independent of cholesterol changes.(7) It is likely that the “pleiotropic” anti-inflammatory effects of statins contribute to plaque stabilization independent of LDL lowering. (8) 7
The Bigger Picture
If coronary artery disease is fundamentally a metabolic disease, as the evidence increasingly suggests—then:
Lowering LDL is helpful, but insufficient
Improving metabolic health is essential
This reframes treatment priorities:
Address insulin resistance
Reduce inflammation
Restore metabolic flexibility
Use statins selectively—not reflexively
Complications of Statins
Common adverse effects include myalgias and small increases in liver enzymes; serious rhabdomyolysis and liver failure are rare in trials and observational data.
Myalgia/SAMS: muscle pain or weakness without major CK elevation, common and a major driver of discontinuation.
Nonspecific symptoms: headache, fatigue, dizziness, GI upset (nausea, constipation, diarrhea, gas), and sleep disturbance; often disappear with use.
Statins slightly increase incident diabetes risk, especially in those with pre‑existing metabolic syndrome.
Some patients report confusion or memory issues, and early observational work suggested reversible memory loss soon after initiation.
Nutraceuticals and CAD
For CAD, the most relevant nutraceuticals are those that improve insulin resistance and endothelial function, used as adjuncts to lifestyle and (when indicated) drugs, not stand‑alone replacements.
Insulin‑resistance–targeted nutraceuticals
Berberine
Activates AMPK, improves insulin receptor expression, and enhances insulin sensitivity, with consistent improvements in HOMA‑IR, fasting glucose, HbA1c, lipids, blood pressure, and inflammatory markers across clinical studies.(9)
Mechanistically relevant to CAD via better glycemic control, reduced oxidative stress, and improved endothelial biomarkers; human CAD‑outcome trials are still lacking, so it is best framed as a metabolic adjunct.
Resveratrol (often combined with berberine)
Activates SIRT1, reduces CRP and oxidative stress, and improves insulin resistance and glycemic control in type 2 diabetes trials.(10)
Combination with berberine shows synergistic lipid‑lowering and LDL receptor upregulation in preclinical models, suggesting potential for dual metabolic and vascular benefits.(11)
Omega‑3 fatty acids (EPA‑focused)
Improve triglycerides and may modestly improve insulin sensitivity and post‑prandial lipemia while providing established secondary‑prevention benefit in high‑risk CVD populations.(12)
Aged garlic extract
Aged garlic extract (AGE) appears to modestly slow coronary atherosclerosis progression and improve vascular biology.
Multiple small randomized, placebo‑controlled trials have found that AGE slows progression of coronary artery calcium (CAC) and CT‑measured plaque volume compared with placebo, including in patients already on statins. (13)
Meta‑analytic data suggest that doses ≥1,200 mg/day have clear blood‑pressure effects, and there are signals toward lower TNF‑α, modest lipid changes, and improved inflammatory profiles.(14)
Conclusion.
For decades, statins have been presented as the solution to heart disease.
They are not.
They are one piece of a much larger puzzle.
And when used in the right context, they can be valuable.
But when used as a substitute for understanding the true nature of the disease…
They risk distracting us from what matters most.
Figure 5.

Medical Disclaimer: The discussion of repurposed medications and nutraceuticals in this article is intended to review the scientific literature and does not constitute a recommendation for self-treatment. Decisions regarding the use of off-label therapies should be made in consultation with a qualified healthcare professional familiar with the patient’s medical history and current treatment plan. Please see the full Medical Disclaimer on the introductory page to Marik’s Cancer & Metabolic Healing Playbook.
References
1. Sachdeva A, Cannon CP, Deedwania PC, Labresh KA, Smith SC, Jr., Dai D, et al. Lipid levels in patients hospitalized with coronary artery disease: an analysis of 136,905 hospitalizations in Get With The Guidelines. Am Heart J. 2009;157(1):111–7.e2.
2. Reid FD, Cook DG, Whincup PH. Use of statins in the secondary prevention of coronary heart disease: is treatment equitable? Heart. 2002;88(1):15–9.
3. Ray KK, Seshasai SR, Erqou S, Sever P, Jukema JW. Statins and all-cause mortality in high-risk primary prevention. A meta-analysis of 11 randomized controlled trials involving 65 229 participants. Arch. Intern. Med. 2010;170:1024–31.
4. Singh BM, Lamichhane HK, Srivatsa SS, Adhikari P, Kshetri BJ, Khatiwada S, et al. Role of Statins in the Primary Prevention of Atherosclerotic Cardiovascular Disease and Mortality in the Population with Mean Cholesterol in the Near-Optimal to Borderline High Range: A Systematic Review and Meta-Analysis. Adv Prev Med. 2020;2020:6617905.
5. Arnett DK, Blumenthal RS, Albert MA, Buroker AB, Goldberger ZD, Hahn EJ, et al. 2019 ACC/AHA Guideline on the Primary Prevention of Cardiovascular Disease: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Circulation. 2019;140(11):e596–e646.
6. Ravnskov U, de Lorgeril M, Diamond DM, Hama R, Hamazaki T, Hammarskjöld B, et al. LDL-C does not cause cardiovascular disease: a comprehensive review of the current literature. Expert Rev Clin Pharmacol. 2018;11(10):959–70.
7. Mahmoudi A, Katsiki N, Vrablik M, Sahebkar A. Pleiotropic Effects of Statins: Focus on Inflammation, Oxidative Stress and Immunomodulation (Part I). Curr Atheroscler Rep. 2026;28(1):8.
8. Oesterle A, Laufs U, Liao JK. Pleiotropic Effects of Statins on the Cardiovascular System. Circ Res. 2017;120(1):229–43.
9. Carrizzo A, Izzo C, Forte M, Sommella E, Di Pietro P, Venturini E, et al. A Novel Promising Frontier for Human Health: The Beneficial Effects of Nutraceuticals in Cardiovascular Diseases. Int J Mol Sci. 2020;21(22).
10. McCubrey JA, Lertpiriyapong K, Steelman LS, Abrams SL, Yang LV, Murata RM, et al. Effects of resveratrol, curcumin, berberine and other nutraceuticals on aging, cancer development, cancer stem cells and microRNAs. Aging (Albany NY). 2017;9(6):1477–536.
11. Zhu X, Yang J, Zhu W, Yin X, Yang B, Wei Y, et al. Combination of Berberine with Resveratrol Improves the Lipid-Lowering Efficacy. Int J Mol Sci. 2018;19(12).
12. Tognola C, Alessandro M, Milani M, Cartella I, Tavecchia G, Grasso E, et al. Nutraceuticals in Chronic Coronary Syndromes: Preclinical Data and Translational Experiences. High Blood Press Cardiovasc Prev. 2021;28(1):13–25.
13. Murali S, Smith ER, Tiong MK, Tan SJ, Toussaint ND. Interventions to Attenuate Cardiovascular Calcification Progression: A Systematic Review of Randomized Clinical Trials. J Am Heart Assoc. 2023;12(23):e031676.
14. Saadh MJ, Kariem M, Shukla M, Ballal S, Kumar A, Chahar M, et al. Effects of aged garlic extract on blood pressure in hypertensive patients: A systematic review and meta-analysis of randomized controlled trials. Prostaglandins Other Lipid Mediat. 2024;175:106914.
Thank you, Dr. Marik, for this clear and easy-to-understand (even for a lay person like myself) piece.
Paul, I support most of this but cannot endorse any use of statins. Attempting to lower cholesterol, which is an absolutely essential substance, by any means is simply misguided. None of the Pharma-sponsored trials will ever convince me otherwise. They are all biased and unreliable. Source data is closely held by the Cholesterol Trialists in Oxford. Why not make it available for independent evaluation? The question answers itself.
I also believe the massively increased consumption of seed oils instead of traditional animal fats such as butter and lard has played a major role in the epidemic of metabolic syndrome and heart disease. Elimination of these from our food will lead to major improvements in health of the population. @Dr. Wojak, M.D. @Dr. Jason Fung