

Introduction
Caution to the reader: This is a complex and evolving topic that depends heavily on an understanding of molecular biology. The material has been distilled to remain accessible while preserving mechanistic accuracy. Please refer to Figures 2, which outlines a simplified and practical approaches to managing resistance. The next post will explain in more practical terms when to rotate and when not to rotate.
Clinicians using a metabolic framework informed by the work of Thomas Seyfried and Paul Marik may combine four to five repurposed prescription agents with four to five nutraceuticals. After approximately two years of this approach, acquired resistance may begin to emerge, and a disease that was previously stable can progress, in some cases rapidly.
This raises critical questions:
How should this strategy be modified?
Should mechanistically similar agents be cycled or alternated more frequently?
Should dosing be intermittent rather than continuous?
What approaches have been developed to prevent resistance to cancer therapy?
Acquired resistance under chronic metabolic therapy is not a failure of targeting but a predictable evolutionary response. The central issue is not whether multi-agent metabolic therapy works initially, but how tumor populations adapt over time under sustained selective pressure.
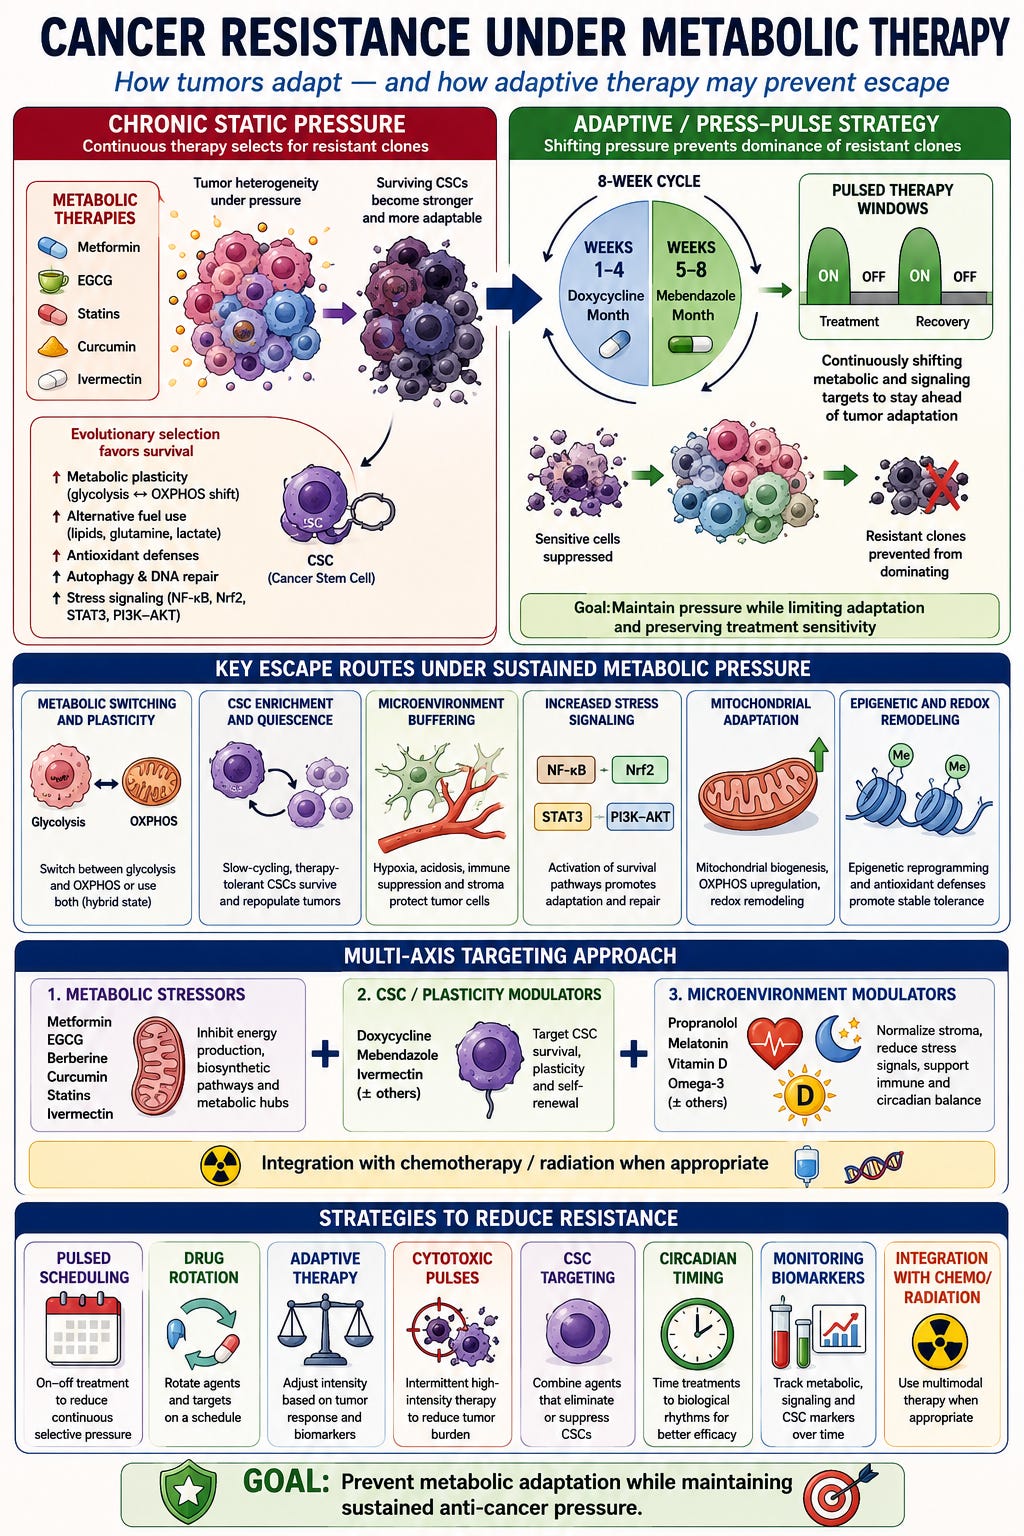
Biological Basis of Metabolic Resistance
Evolutionary dynamics under chronic pressure
This scenario reflects acquired therapeutic resistance under chronic multi-agent metabolic pressure—a well-established phenomenon in oncology, even when regimens fall outside conventional protocols. Cancers develop resistance because metabolically flexible, stress-tolerant subclones—often enriched for cancer stem cell (CSC)-like properties—survive and adapt through layered metabolic, signaling, and microenvironmental rewiring. Preventing resistance requires constraining metabolic plasticity, limiting tolerable stress, and periodically reshaping the selective landscape rather than applying static, continuous pressure.
Under chronic low-to-moderate metabolic stress from repurposed drugs and nutraceuticals such as metformin, statins, EGCG, and curcumin, tumor populations are not simply suppressed; they are evolutionarily trained to survive in a perturbed metabolic niche. This selects subpopulations with enhanced metabolic plasticity, stress-response signaling, and CSC-like traits, which together drive resistance and relapse.(1-3)
Under chronic exposure to repurposed drugs and nutraceuticals, the cells that survive are those capable of rewiring metabolism, repairing damage, and occupying protective niches, thereby enriching tumors with highly adaptable, therapy-tolerant clones over time.(2) These conditions favor slow‑cycling, quasi-dormant, CSC-like populations that can shift between glycolysis and oxidative phosphorylation (OXPHOS), exploit lipids and glutamine, and upregulate stress‑response programs, rendering subsequent therapies less effective.(4)
Metabolic plasticity as a central driver
This adaptive flexibility is rooted in metabolic plasticity. Metabolic plasticity enables cancer cells to toggle between glycolytic and oxidative states or adopt hybrid phenotypes that utilize both pathways while maintaining reactive oxygen species (ROS) at survivable levels, thereby promoting survival under diverse metabolic therapies.(5) Repurposed agents such as metformin and statins typically target specific metabolic nodes (e.g., AMPK–mTOR signaling, complex I, lipogenesis), but chronic partial inhibition can drive a shift toward alternative fuel sources, including fatty acid oxidation, glutamine, and lactate, along with increased mitochondrial biogenesis, ultimately creating a more resilient metabolic network.(6)
Stress signaling, epigenetic adaptation, and redox remodeling
Continuous exposure to polyphenols and metabolic drugs can remodel signaling (e.g., NF‑κB, Nrf2, STAT3, PI3K–AKT) and alter epigenetic markers, facilitating the emergence of a stable, tolerant phenotype rather than outright cell death.(7) Some nutraceuticals, such as EGCG, induce cytoprotective responses, including activation of the Nrf2–HO‑1 axis; combinations such as EGCG plus metformin may enhance tumor cell kill, but if underdosed or poorly timed, they may permit selection of cells with reinforced antioxidant defenses.(8)
Taken together, the following factors are the most common drivers of resistance under sustained metabolic pressure.
Key Drivers of Resistance Under Metabolic Pressure
Metabolic plasticity and switching
Tumors and CSCs switch between glycolysis and OXPHOS in response to metabolic therapies; inhibition of Warburg-type glycolysis may promote an OXPHOS-dominant, more quiescent, stress-resistant state.(3)
Metabolic therapies (including dietary modulation and pharmacologic agents) can induce a glycolysis↔OXPHOS shift that sustains survival despite initial growth inhibition.(9)
Enrichment of CSC-like subpopulations
CSCs exhibit marked metabolic flexibility—glycolytic in some contexts, OXPHOS- or fatty-acid-oxidation–dependent in others—enabling survival under nutrient restriction, hypoxia, and drug-induced stress.(10)
Chronic metabolic stress may increase CSC markers, enhance sphere-forming capacity, and promote quiescence via pathways such as Notch, Wnt/β‑catenin, and JARID1B-associated programs, supporting survival and delayed relapse.
Adaptive stress signaling and transcriptional reprogramming
Targeted inhibition of oncogenic signaling often triggers compensatory activation of survival pathways (e.g., STAT3–IL-6, Notch, stress granule–associated programs), providing early adaptive resistance that precedes stable genetic changes.(11)
Metabolic stress activates the integrated stress response (ISR), unfolded protein response, autophagy, and antioxidant systems, allowing cells to tolerate ROS and energy depletion while maintaining viability.(12)
Microenvironmental and niche-level adaptation
Stromal cells, immune infiltrates, and the extracellular matrix remodel in response to chronic stress, buffering cancer cells metabolically through lactate and amino acid shuttling and exosome-mediated transfer of metabolites and microRNA.(2)
Dietary inputs and nutraceutical exposure may shape CSC metabolic phenotypes and niche signals, affecting the balance between differentiation and stemness under ongoing therapy.(13)
Genetic and epigenetic hardening over time
Repeated or chronic sublethal stress selects for clones with mutations or stable epigenetic programs that further stabilize adaptable phenotypes, such as those driven by chromatin modifiers like JARID1B that support slow-cycling, therapy-tolerant cells.(9)
Drug repurposing targets multiple pathways (AMPK–mTOR, EMT, angiogenesis, inflammation), but incomplete suppression may favor cells that integrate these signals into a more resilient state rather than undergoing apoptosis.
Why Multi-Agent Metabolic Regimens Are Double-Edged
Multi-agent metabolic combinations (e.g., metformin plus statins, beta-blockers, and nutraceuticals such as EGCG and curcumin) aim to exert synergistic pressure across tumor metabolism, angiogenesis, EMT, inflammatory signaling, and CSC pathways. Yet this broad metabolic pressure can be double-edged:
If dosing intensity is kept in a tolerable band, cells experience chronic, nonlethal glycometabolic stress that can enhance metabolic flexibility and CSC-like properties through altered N‑glycosylation and Notch activation.(1)
Incomplete, static pathway blockade can encourage rewiring rather than collapse of network function, so combination regimens that are not optimized for depth of target engagement may inadvertently act as training pressure rather than curative pressure.(11, 14)
Why Chronic, Flat Multi‑Agent Regimens Are Risky
Flat, continuous dosing of multiple repurposed drugs and nutraceuticals at tolerable levels can create a relatively stable, nonlethal environment—strong enough to stress but not eradicate cancer cells—thereby maximizing evolutionary time for adaptation.(5) Because many metabolic agents converge on overlapping pathways (e.g., AMPK activation, mTOR inhibition, glycolysis dampening), chronic multi‑agent use may canalize evolution toward subclones optimized for oxidative metabolism, fatty‑acid utilization, autophagy, and CSC-like traits, enabling improved survival during subsequent therapies.(15, 16)
Role of Press–Pulse and Adaptive Therapy
Press–pulse strategies apply a chronic press (e.g., a calorie-restricted ketogenic diet, low-dose metabolic modulators) to maintain sustained energy stress, while using intermittent pulses (cytotoxic drugs, ablative radiotherapy, higher‑intensity metabolic blocks) to debulk stressed cells.(16) Adaptive therapy and press–pulse regimens deliberately avoid driving the tumor toward a single, maximally resistant state by modulating timing and intensity in response to tumor burden and biomarkers, preserving a population of therapy-sensitive cells to competitively suppress resistant clones.(5, 16)
Practical Design Strategies
When building multi-agent protocols centered on repurposed drugs and nutraceuticals, several design elements can help minimize the emergence of adaptive resistance.(6)
Time‑structured press–pulse scheduling(16)
Use chronic press elements, such as ketogenic or low-glucose diets and a small backbone of well-tolerated agents, rather than deploying the entire arsenal continuously.
Superimpose short pulses in which additional drugs (including cytotoxics or higher-dose metabolic blockers) are layered to produce decisive tumoricidal stress, then de-escalate to allow recovery of normal tissues and reduce selection for hyper-tolerant clones.
Rotating and modular combinations(15)
Rotate subsets of agents that share overlapping targets (e.g., alternating OXPHOS‑heavy, glycolysis‑heavy, or lipogenesis‑heavy modules) so tumors cannot stabilize around a single optimal metabolic configuration.
Periodically withdraw certain agents (drug holidays) while maintaining overall tumor control with others, analogous to adaptive tyrosine kinase inhibitor strategies that preserve drug-sensitive populations and limit resistant expansion.
Explicit CSC and plasticity targeting(17)
Include agents and pulses known to debulk CSC-like cells or collapse hybrid metabolic states (for example, combinations that simultaneously raise ROS and impair antioxidant responses, or pair mitochondrial inhibitors with agents that block glycolytic upshift).
Combine metabolic strategies with microenvironmental interventions (e.g., angiogenesis inhibitors or targeting cancer-associated fibroblasts) in metronomic or adaptive schedules to reduce the protective niche that fosters CSC survival and plasticity.
Dosing intensity and sequence optimization(17)
Aim for clearly cytotoxic or cytostatic pulses rather than chronic near-threshold exposures; subtherapeutic dosing is more likely to train tolerance than to eradicate.
Multi-Agent Protocol: Adaptive Resistance Considerations
The proposed multi-agent protocol combines vitamin D, curcumin, EGCG, melatonin, metformin, ivermectin, mebendazole, sulforaphane, resveratrol, and modified citrus pectin. This protocol targets multiple metabolic and CSC pathways; however, given its breadth and likely chronic use, it may strongly select for highly plastic, slow-cycling, OXPHOS‑ and fatty-acid oxidation (FAO)‑dependent CSC-like clones unless timing, intensity, and escape routes are deliberately managed.
What the protocol is doing
Core elements and dominant pressures:
Metabolic/AMPK–mTOR axis: Metformin, berberine, resveratrol, and EGCG activate AMPK and dampen mTOR signaling, glycolysis, and biosynthetic pathways, exerting Warburg‑antagonistic pressure.(18)
CSC‑targeting phytochemicals (the “Big Five”): Curcumin, EGCG, resveratrol, sulforaphane, and genistein have documented effects on CSC-related pathways (Notch, Wnt/β‑catenin, Hedgehog, PI3K/Akt, NF‑κB) and have reduced CSC markers, sphere formation, and tumor-initiating capacity in preclinical models.(19, 20) The present protocol incorporates four of these compounds (curcumin, EGCG, resveratrol, sulforaphane).
Anti‑CSC repurposed drugs: Ivermectin, mebendazole, and doxycycline each have preclinical data targeting CSC biology (microtubules, Wnt/β‑catenin, mitochondrial translation) and are highlighted in repurposing frameworks as part of foundational CSC‑targeting backbones.(20, 21)
Microenvironment/stress modulation: Propranolol modulates adrenergic signaling, angiogenesis, and immune interactions, whereas melatonin and vitamin D influence circadian regulation, immune function, and differentiation programs.(19-21)
Net effect: Broad suppression of glycolysis, mTOR signaling, proliferation, angiogenesis, stress signaling, and multiple CSC pathways—largely delivered as continuous low‑ to moderate-intensity metabolic pressure rather than short, decisive cytotoxic pulses.
Likely escape routes under chronic use
Even with strong CSC coverage, a static, multi-agent metabolic protocol will tend to select for:
Shift to OXPHOS/FAO‑dominant metabolism: Suppression of glycolysis and mTOR signaling, combined with mitochondrial stress from doxycycline and resveratrol, favors survival of cells with robust mitochondrial biogenesis, FAO, and antioxidant capacity—a recognized CSC phenotype across multiple cancers.(2, 14)
Emergence of slow‑cycling, stress-tolerant CSC-like cells: While natural compounds such as curcumin, EGCG, sulforaphane, and resveratrol may reduce CSC fractions, chronic sublethal exposure can also select for cells with heightened stress-response signaling, autophagy, and DNA repair capacity; CSCs with flexible metabolic programs may adapt rather than be eliminated.(3, 19)
Microenvironmental buffering: Stromal and immune cells may adapt to long-term exposure to propranolol, vitamin D, phytochemicals, and metformin, establishing metabolite shuttles (e.g., lactate, amino acids, lipids) that support resistant clones despite glycolytic suppression.(9, 22)
Pharmacokinetic gaps and variable target engagement: Many nutraceuticals (curcumin, resveratrol, EGCG, sulforaphane) have limited bioavailability and short half-lives, so continuous oral dosing may result in fluctuating subtherapeutic concentrations—conditions more conducive to adaptive training than to the eradication of plastic cells.(13, 19, 20, 23)
Practical Modifications to Reduce Adaptive Resistance
Introduce pulsing and drug rotation
Goal: avoid chronic, tolerable stress by alternating intensified and recovery windows.
Care Oncology–style regimens use a four-drug metabolic backbone (metformin, atorvastatin, doxycycline, mebendazole) and commonly alternate doxycycline and mebendazole month on/month off rather than administering both continuously.(24)
Core Care Oncology metabolic protocol drugs
The standard protocol uses metformin, atorvastatin, mebendazole, and doxycycline as a long-term adjunctive metabolic regimen (“Care Metabolic Protocol,” “COC Protocol™”).(24)
Together, these agents target glycolysis/AMPK–mTOR (metformin), cholesterol synthesis and prenylation pathways (atorvastatin), microtubule dynamics and Wnt/β-catenin signaling (mebendazole), mitochondrial translation/CSC functions, and angiogenesis and inflammation (doxycycline).
How mebendazole and doxycycline are cycled
Patient-facing descriptions indicate that Care Oncology typically rotates doxycycline and mebendazole, administering one month of doxycycline followed by one month of mebendazole (or vice versa), rather than both simultaneously.(24)
This alternation reflects their overlapping anti‑CSC and anti-angiogenic roles and helps limit prolonged antibiotic exposure while maintaining continuous metabolic pressure through metformin and atorvastatin.
Why cycling matters for resistance
Alternating mebendazole and doxycycline applies sequential pressure to distinct CSC and metabolic vulnerabilities (mitochondrial biogenesis/translation versus microtubules and glucose handling) rather than maintaining a static, unchanging assault on the same targets.
This month‑on/month‑off design may also reduce cumulative toxicity and microbiome disruption from chronic doxycycline, preserving longer-term metabolic therapy options without driving antimicrobial resistance or intolerable gastrointestinal effects.
Anchor combinations with cytotoxic or local therapies when possible
This protocol is inherently adjunctive. Whenever feasible, layer pulses of metabolic/CSC-targeting agents onto cytotoxic or local treatments (chemotherapy, radiotherapy, ablative procedures) so stressed, plastic cells are eliminated rather than allowed to remodel; this can include metronomic chemotherapy strategies.
Rebalance CSC versus non-CSC pressure
This protocol is heavily CSC-oriented; refinements may reduce the selection of ultra-resistant niches:
Combine core CSC phytochemicals (curcumin, EGCG, sulforaphane, resveratrol) in intervals—e.g., two to three at a time with periodic rotation—at doses supported by available clinical or translational CSC-related data to ensure adequate exposure.
Synchronize ivermectin plus mebendazole pulses with periods of likely CSC activation (e.g., post‑chemotherapy or post‑radiation) to target cells entering repair or replication phases rather than maintaining unbroken chronic dosing.
Use propranolol and melatonin strategically
Rather than background use only:
Propranolol may be most valuable around surgery, high-stress periods, and during cytotoxic therapy to curb adrenergic pro-angiogenic and pro-metastatic signaling; continuous long-term use may be reasonable but can be titrated around those windows.
Melatonin can act as a chronobiotic and oncostatic agent; nightly use is defensible, and timing of metabolic pulses can be aligned with circadian biology (e.g., dosing AMPK activators earlier in the day, when hepatic and tumor metabolic flux are highest).
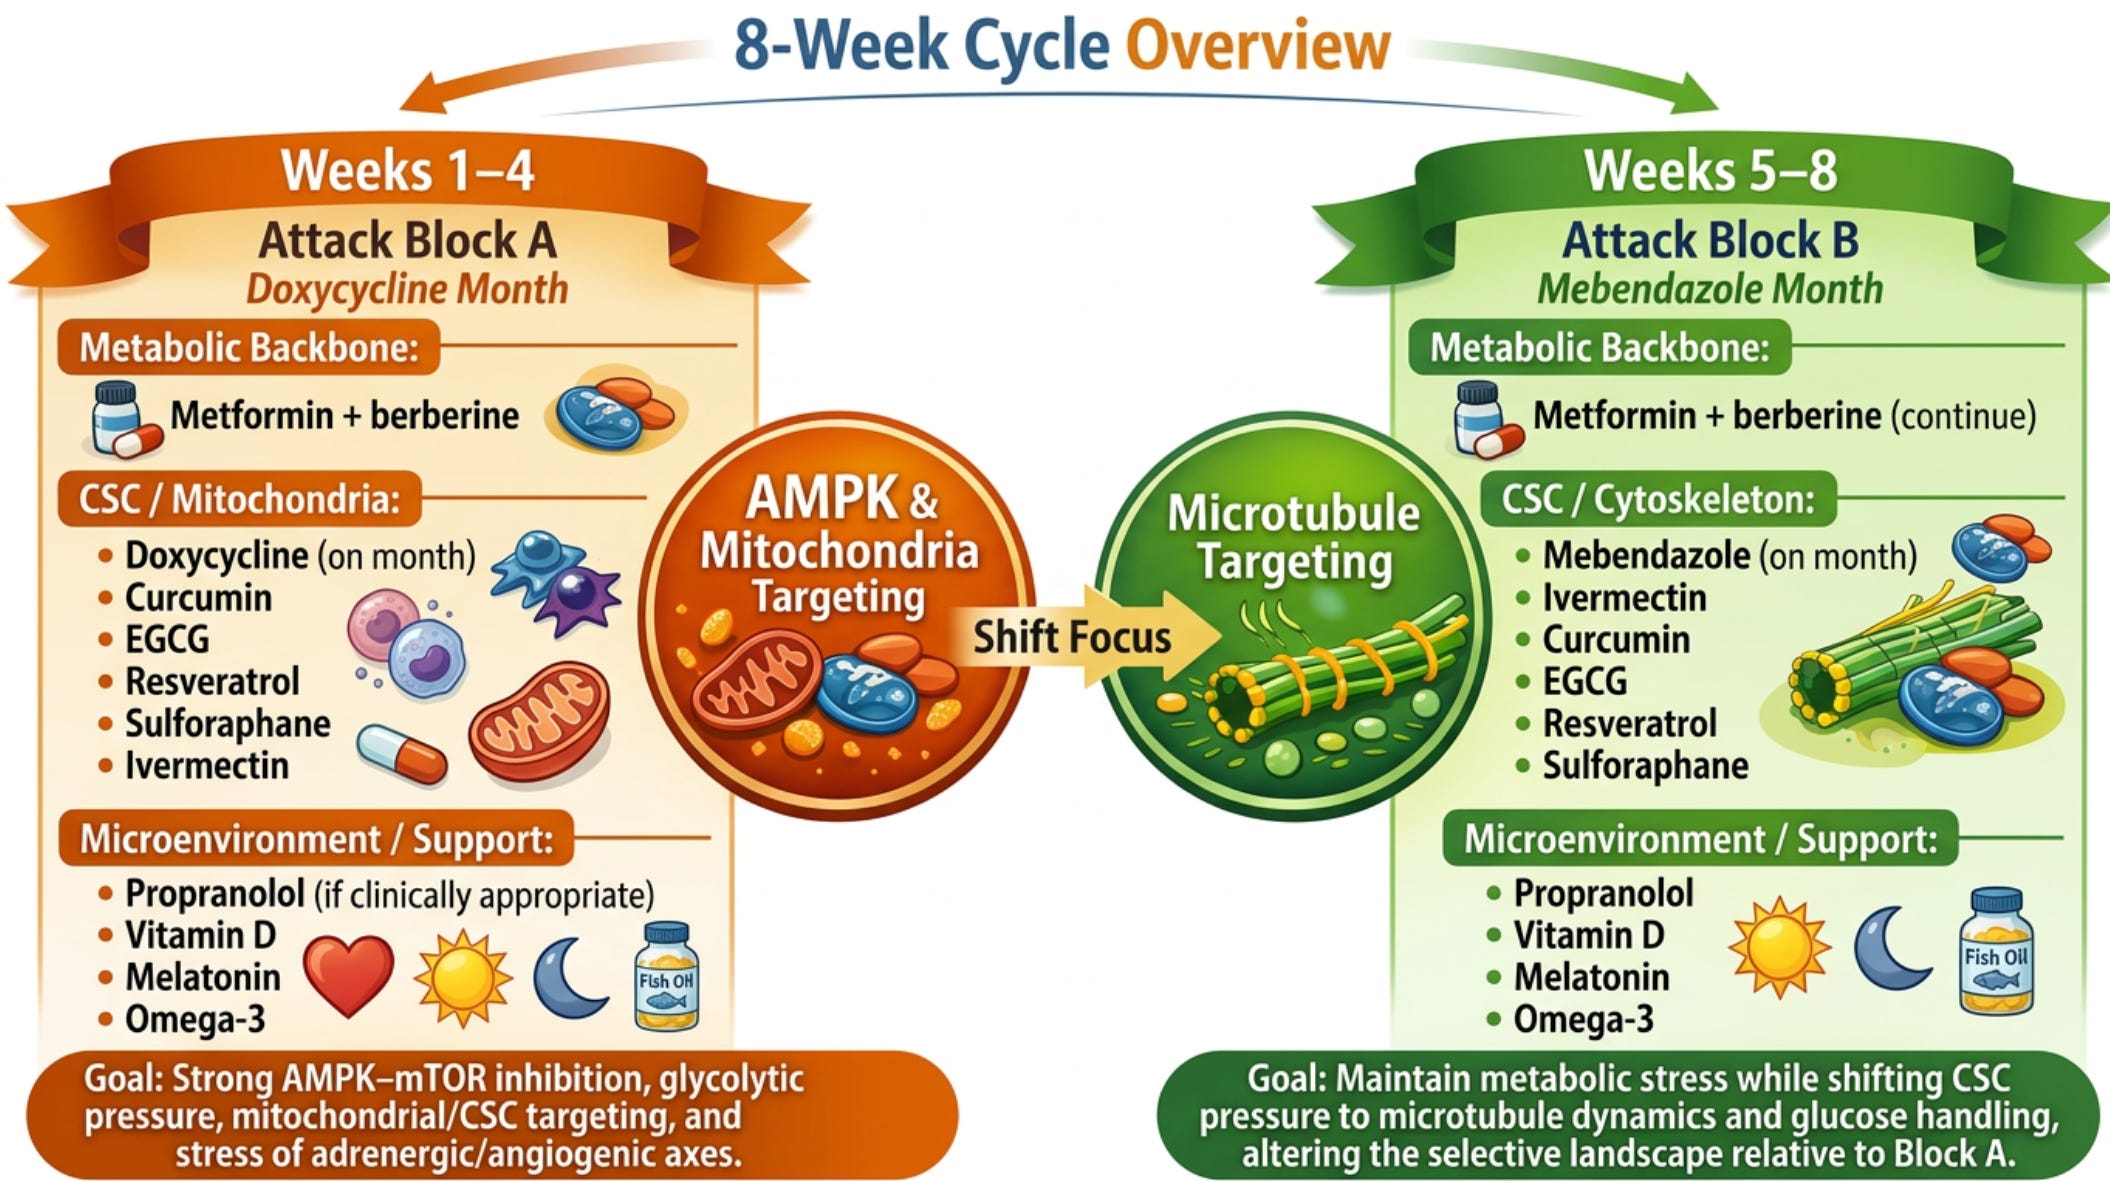
Example of an Adaptive Rotating Schedule (Adjunctive or Stand-alone)
Overall, eight‑week cycle
Weeks 1–4 (Doxycycline month)
Metabolic backbone: Metformin + berberine
CSC/mitochondria: Doxycycline (on month), curcumin, EGCG, resveratrol, sulforaphane, ivermectin
Microenvironment/support: Propranolol (if clinically appropriate), vitamin D, melatonin, omega-3
Goal: Strong AMPK–mTOR inhibition, glycolytic pressure, mitochondrial/CSC targeting, and stress of adrenergic/angiogenic axes
Weeks 5–8 (Mebendazole month)
Metabolic backbone: Metformin + berberine (continue)
CSC/cytoskeleton: Mebendazole (on month), ivermectin, curcumin, EGCG, resveratrol, sulforaphane
Microenvironment/support: Propranolol, vitamin D, melatonin, omega-3
Goal: maintain metabolic stress while shifting CSC pressure to microtubule dynamics and glucose handling, thereby altering the selective landscape relative to Block A
Figure 1. Approach to prevent adaptive resistance in multi-agent metabolic protocols.
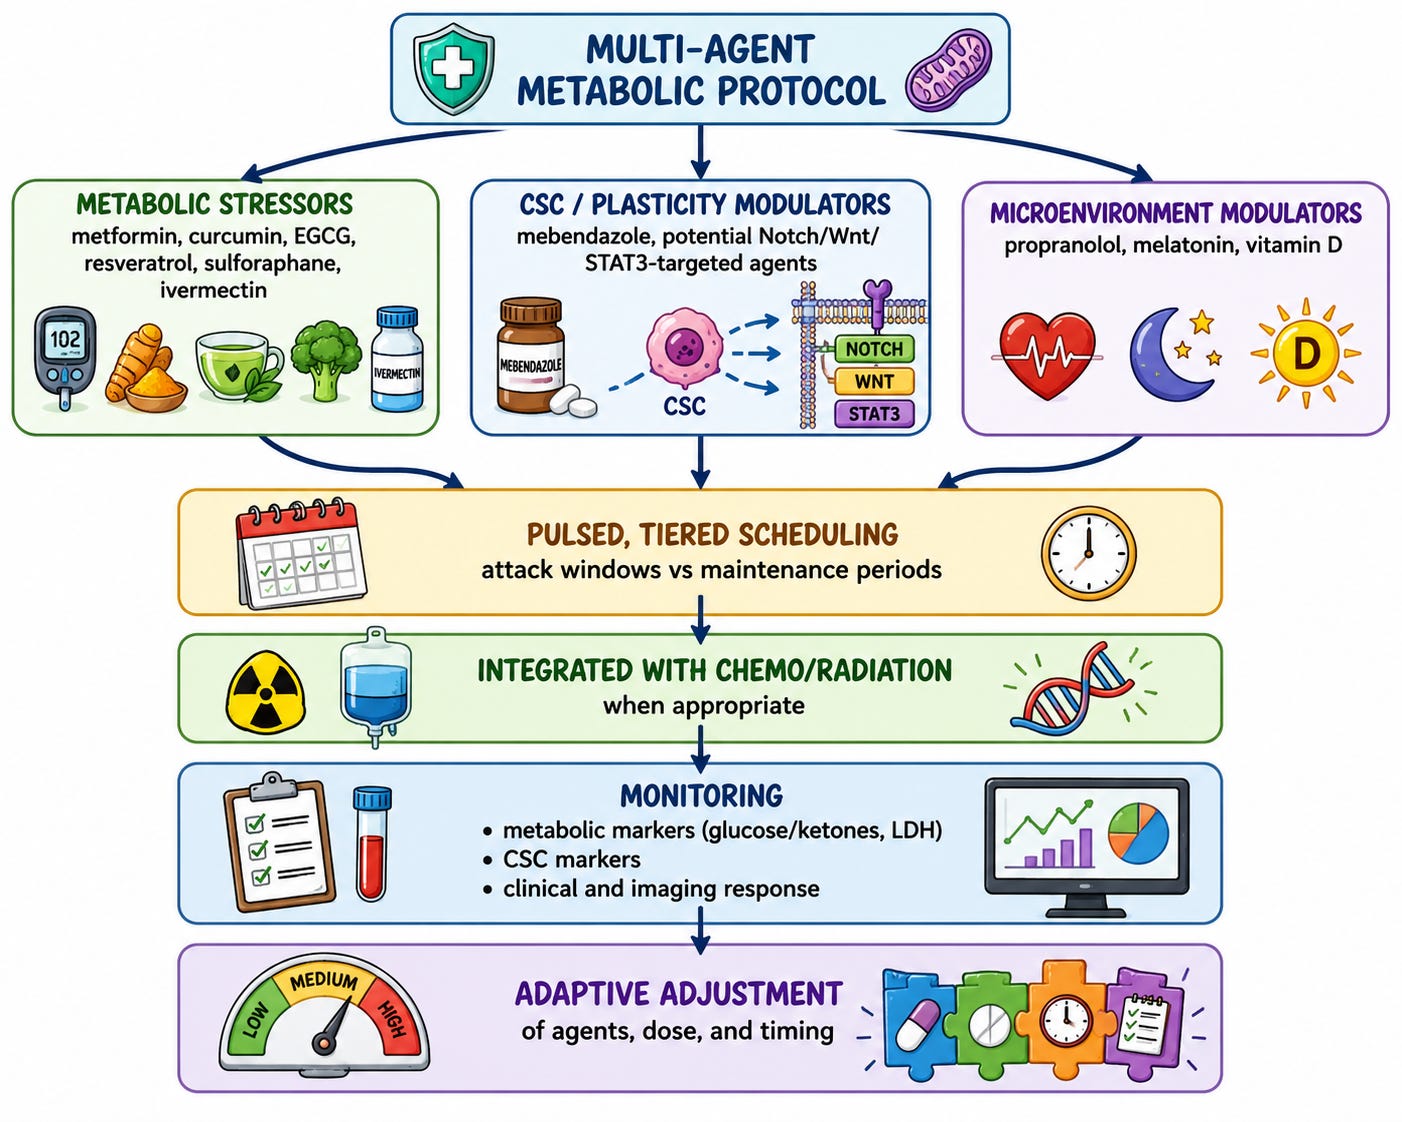
Figure 2. Adaptive metabolic rotation strategy (adjunctive or stand-alone)

References
1. Iwamoto S, Kobayashi T, Hanamatsu H, Yokota I, Teranishi Y, Iwamoto A, et al. Tolerable glycometabolic stress boosts cancer cell resilience through altered N-glycosylation and Notch signaling activation. Cell Death Dis. 2024;15(1):53.
2. Keoh LQ, Chiu CF, Ramasamy TS. Metabolic Plasticity and Cancer Stem Cell Metabolism: Exploring the Glycolysis-OXPHOS Switch as a Mechanism for Resistance and Tumorigenesis. Stem Cell Rev Rep. 2025;21(8):2446–68.
3. Xie Y, Ma S, Tong M. Metabolic Plasticity of Cancer Stem Cells in Response to Microenvironmental Cues. Cancers (Basel). 2022;14(21).
4. Rojas M, Manzi M, Madurga S, García Velásquez FE, Romero MA, Marín S, et al. Metabolic plasticity drives specific mechanisms of chemotherapy and targeted therapy resistance in metastatic colorectal cancer. Explor Target Antitumor Ther. 2025;6:1002337.
5. Goldman A, Khiste S, Freinkman E, Dhawan A, Majumder B, Mondal J, et al. Targeting tumor phenotypic plasticity and metabolic remodeling in adaptive cross-drug tolerance. Sci Signal. 2019;12(595).
6. Zhang Z, Zhou L, Xie N, Nice EC, Zhang T, Cui Y, et al. Overcoming cancer therapeutic bottleneck by drug repurposing. Signal Transduct Target Ther. 2020;5(1):113.
7. Castelli S, Franchini M, Ferraro L, Mangraviti N. The impact of epigenetics on tumor metabolism: friend or foe in drug response? Fronteirs in Epigenetics and Epigenomics. 2026;4:1755829.
8. Talib WH, Awajan D, Alqudah A, Alsawwaf R, Althunibat R, Abu AlRoos M, et al. Targeting Cancer Hallmarks with Epigallocatechin Gallate (EGCG): Mechanistic Basis and Therapeutic Targets. Molecules. 2024;29(6).
9. Lee CJ, Yoon H. Metabolic Adaptation and Cellular Stress Response As Targets for Cancer Therapy. World J Mens Health. 2024;42(1):62–70.
10. Masoudi M, Moti D, Masoudi R, Auwal A, Hossain MM, Pronoy TUH, et al. Metabolic adaptations in cancer stem cells: A key to therapy resistance. Biochim Biophys Acta Mol Basis Dis. 2024;1870(5):167164.
11. Pazarentzos E, Bivona TG. Adaptive stress signaling in targeted cancer therapy resistance. Oncogene. 2015;34(45):5599–606.
12. Jia Y, Jia R, Dai Z, Zhou J, Ruan J, Chng W, et al. Stress granules in cancer: Adaptive dynamics and therapeutic implications. iScience. 2024;27(8):110359.
13. Vernieri C, Casola S, Foiani M, Pietrantonio F, de Braud F, Longo V. Targeting Cancer Metabolism: Dietary and Pharmacologic Interventions. Cancer Discov. 2016;6(12):1315–33.
14. Punnasseril JMJ, Auwal A, Gopalan V, Lam AK, Islam F. Metabolic Reprogramming of Cancer Cells and Therapeutics Targeting Cancer Metabolism. Cancer Med. 2025;14(18):e71244.
15. Fendt SM, Frezza C, Erez A. Targeting Metabolic Plasticity and Flexibility Dynamics for Cancer Therapy. Cancer Discov. 2020;10(12):1797–807.
16. Seyfried TN, Yu G, Maroon JC, D’Agostino DP. Press-pulse: a novel therapeutic strategy for the metabolic management of cancer. Nutr Metab (Lond). 2017;14:19.
17. Desbats MA, Giacomini I, Prayer-Galetti T, Montopoli M. Metabolic Plasticity in Chemotherapy Resistance. Front Oncol. 2020;10:281.
18. Saini N, Yang X. Metformin as an anti-cancer agent: actions and mechanisms targeting cancer stem cells. Acta Biochim Biophys Sin (Shanghai). 2018;50(2):133–43.
19. Naujokat C, McKee DL. The “Big Five” Phytochemicals Targeting Cancer Stem Cells: Curcumin, EGCG, Sulforaphane, Resveratrol and Genistein. Curr Med Chem. 2021;28(22):4321–42.
20. Lo Iacono M, Gaggianesi M, Bianca P, Brancato OR, Muratore G, Modica C, et al. Destroying the Shield of Cancer Stem Cells: Natural Compounds as Promising Players in Cancer Therapy. J Clin Med. 2022;11(23).
21. Al Khzem AH, Gomaa MS, Alturki MS, Tawfeeq N, Sarafroz M, Alonaizi SM, et al. Drug Repurposing for Cancer Treatment: A Comprehensive Review. Int J Mol Sci. 2024;25(22).
22. Halma MT, Marik P. Cancer metabolism as a therapeutic target and review of interventions. Nutrients. 2023.
23. Aggarwal P, Dutta G, Shaurya R, Rajendran V, Thirunavukkarasu P, Charan J, et al. Unlocking the Potential of Nutraceuticals in Cancer Chemotherapy: A Comprehensive Review. Cureus. 2025;17(8):e89328.
24. Agrawal S, Vamadevan P, Mazibuko N, Bannister R, Swery R, Wilson S. A new method for ethical and efficient evidence generation for off-label medication use in oncology (A case study in glioblastoma). Front. Pharmacol. 2019;10:681.
25. Wang H, Zhu C, Ying Y, Luo L, Huang D, Luo Z. Metformin and berberine, two versatile drugs in treatment of common metabolic diseases. Oncotarget. 2018;9(11):10135–46.
26. Zheng F, Wu J, Tang Q, Xiao Q, Wu W, Hann SS. The enhancement of combination of berberine and metformin in inhibition of DNMT1 gene expression through interplay of SP1 and PDPK1. J Cell Mol Med. 2018;22(1):600–12.
27. Jiang L, Wang P, Sun YJ, Wu YJ. Ivermectin reverses the drug resistance in cancer cells through EGFR/ERK/Akt/NF-κB pathway. J Exp Clin Cancer Res. 2019;38(1):265.
28. Juarez M, Schcolnik-Cabrera A, Dueñas-Gonzalez A. The multitargeted drug ivermectin: from an antiparasitic agent to a repositioned cancer drug. Am J Cancer Res. 2018;8(2):317–31.
29. D’Eliseo D, Velotti F. Omega-3 Fatty Acids and Cancer Cell Cytotoxicity: Implications for Multi-Targeted Cancer Therapy. J Clin Med. 2016;5(2).
30. Das UN, Madhavi N, Sravan Kumar G, Padma M, Sangeetha P. Can tumour cell drug resistance be reversed by essential fatty acids and their metabolites? Prostaglandins Leukot Essent Fatty Acids. 1998;58(1):39–54.
31. Gelsomino G, Corsetto PA, Campia I, Montorfano G, Kopecka J, Castella B, et al. Omega 3 fatty acids chemosensitize multidrug resistant colon cancer cells by down-regulating cholesterol synthesis and altering detergent resistant membranes composition. Mol Cancer. 2013;12:137.
32. Wang X, Li Y, Dai Y, Liu Q, Ning S, Liu J, et al. Sulforaphane improves chemotherapy efficacy by targeting cancer stem cell-like properties via the miR-124/IL-6R/STAT3 axis. Sci Rep. 2016;6:36796.
Appreciate the topic. This particular article is just too complicated for me and as a blessed, terminal stage 4 survivor, I like to think I have enhanced terminology. Who is the audience for this work? I'll continue to support you and put the light onto https://turbocancer.org
May you be blessed,
Geoff Wexler
Deuteronomy 1:11
https://WHOtoSTOP.org
Thank you Dr. Marik .