

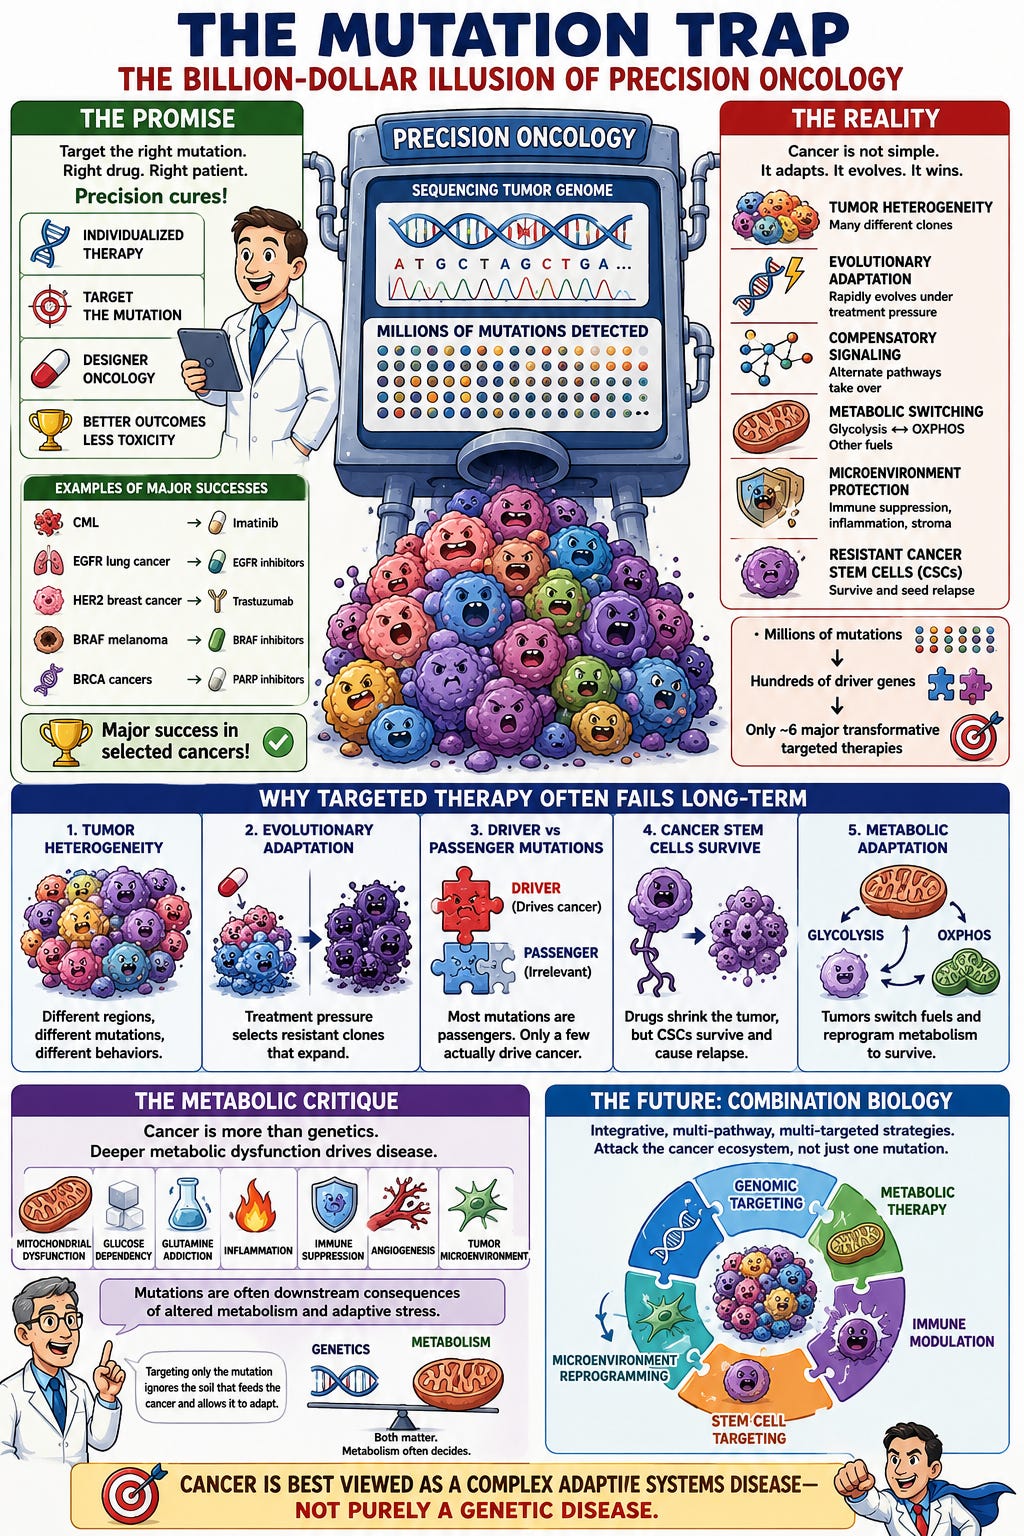
Targeting specific genetic mutations can improve outcomes in selected patients, sometimes dramatically. However, the overall impact across oncology has generally been far more modest than originally hoped, and important limitations have emerged.
The key issue is this:
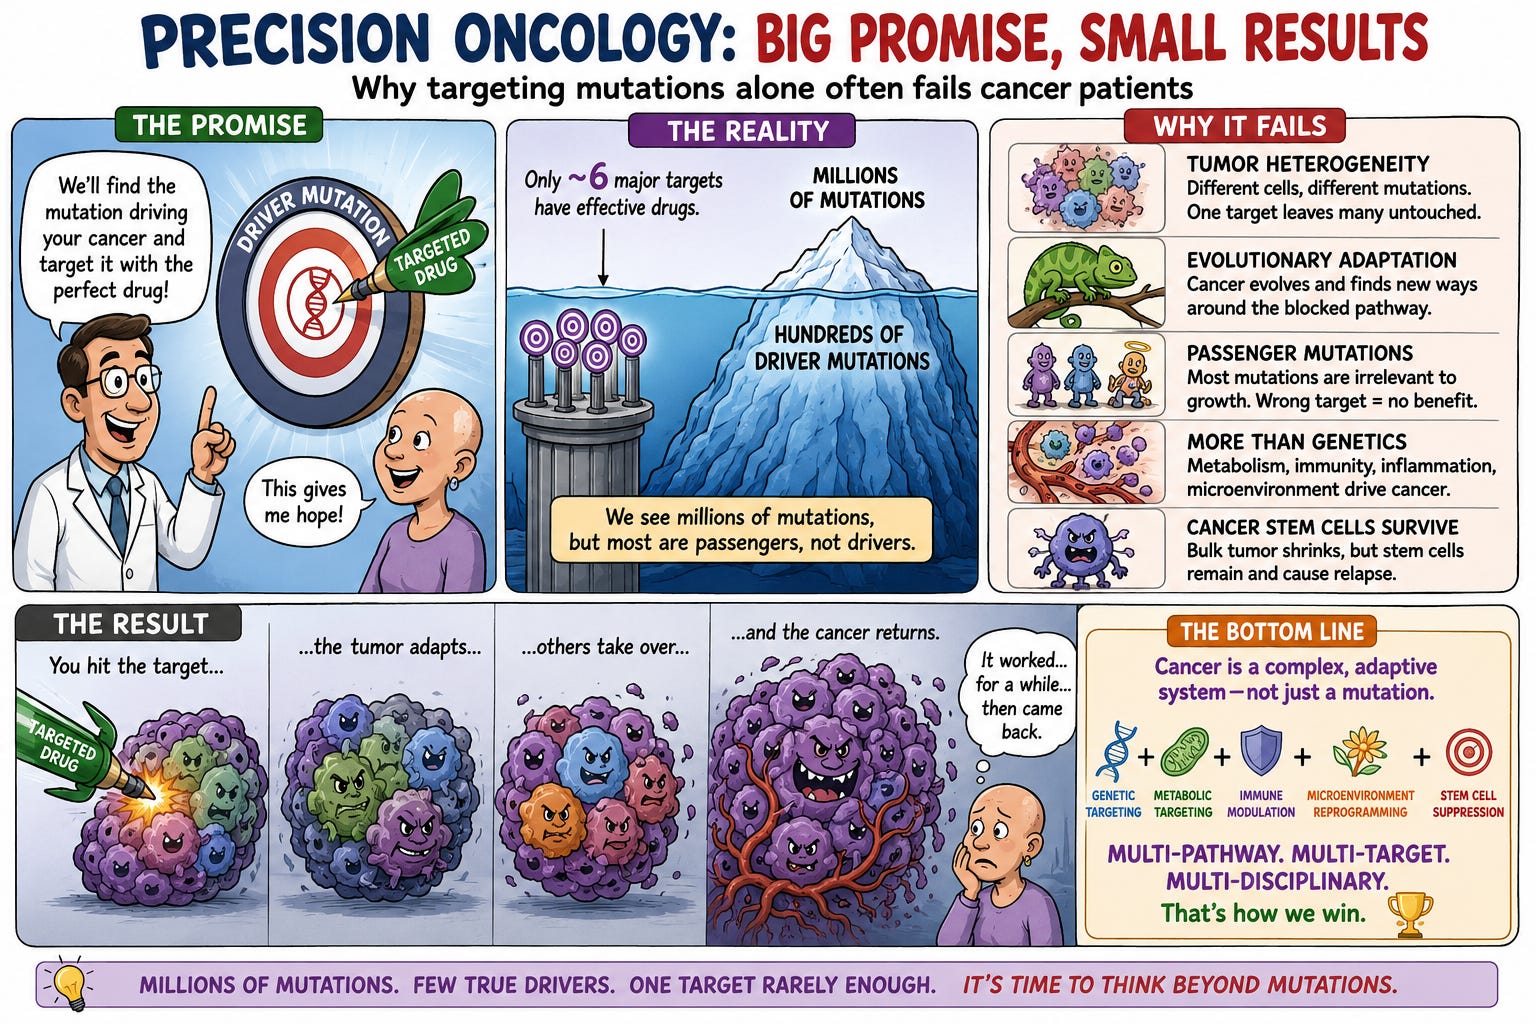
Genetic targeting can be highly effective in some cancers driven by a dominant “driver mutation,” but many cancers are biologically heterogeneous, metabolically adaptive, and rapidly evolve resistance.
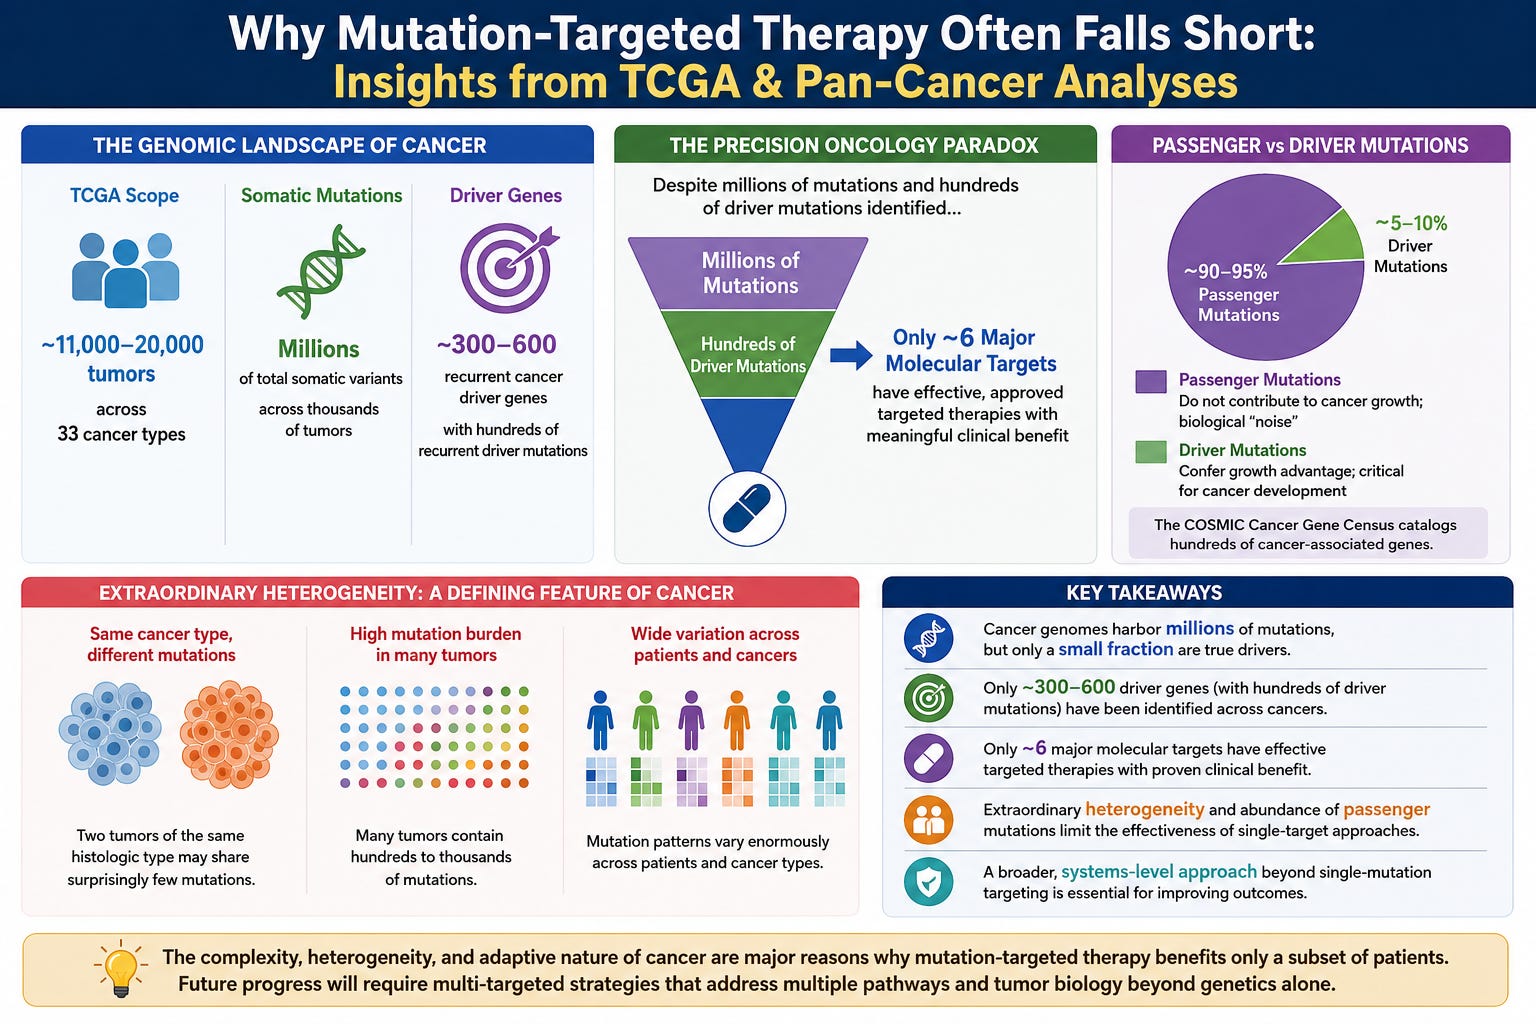
The Cancer Genome Atlas (TCGA) and related Pan-Cancer projects revealed that cancer genomes contain an enormous number of somatic mutations, numbering in the millions overall across all tumors studied.(1, 2) However, only a much smaller subset are believed to be true biologically important “driver” mutations.(1, 2) The TCGA/PanCanAtlas driver-gene analyses estimated approximately ~300–600 recurrent cancer driver genes. One of the most important findings from TCGA was not simply the number of mutations, but the extraordinary heterogeneity:
two tumors of the same histologic type may share surprisingly few mutations,
many tumors contain hundreds to thousands of mutations,
and mutation patterns vary enormously across patients and cancer types.
As discussed further below, these factors largely explain the disappointing performance of mutation-targeted therapy (“precision oncology”) in many patients with cancer. Despite the identification of millions of somatic mutations and hundreds of putative driver mutations, only a small number—approximately six major molecular targets—have resulted in truly effective directly targeted therapies with meaningful clinical benefit.
The Major Successes of Targeted Therapy
There are several unquestionable success stories.
Examples:
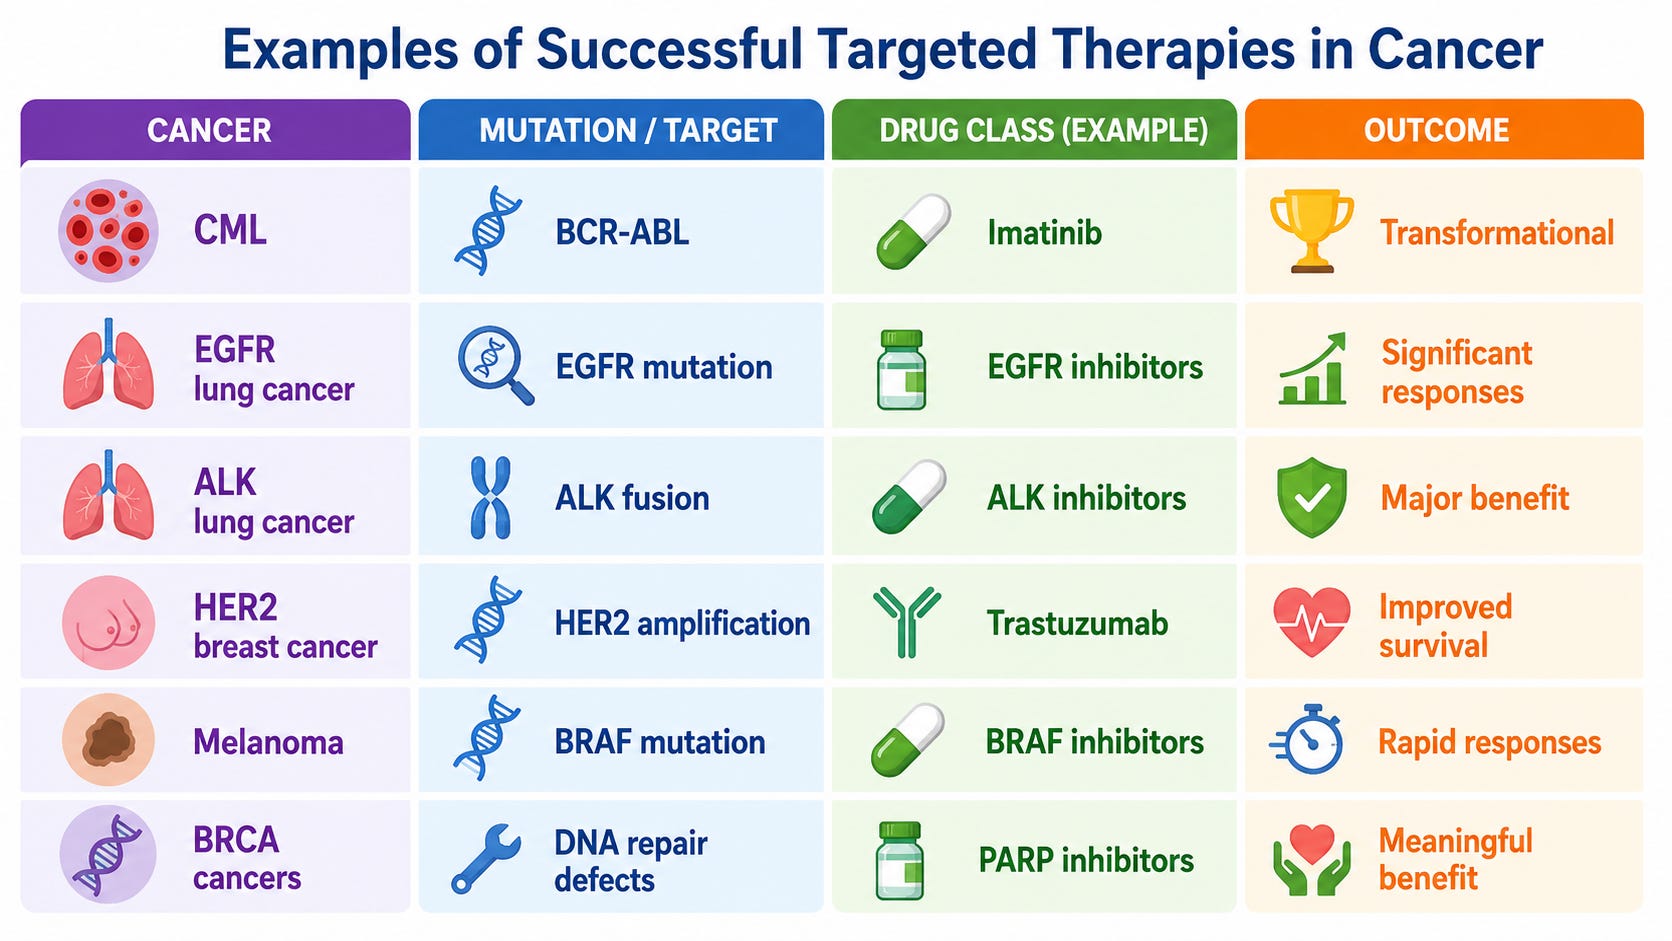
In these diseases:
tumor growth is heavily dependent on a specific pathway,
and inhibition can produce major responses.
Chronic myelogenous leukemia (CML) remains the classic example where targeted therapy fundamentally changed prognosis.
However: The Broader Oncology Reality Is More Complex
Despite major scientific advances:
overall cancer mortality improvements have been relatively modest for many advanced solid tumors,
especially metastatic disease.
A landmark review of oncology RCTs showed that many new cancer drugs improve median overall survival by only:
approximately 2–4 months. (3, 4)
This does not mean targeted therapy “does not work.”
Rather, it means:
responses are often incomplete,
temporary,
or limited to subsets of patients.
Why Genetic Targeting Often Fails Long-Term
1. Tumor Heterogeneity
Most tumors are not genetically uniform.
Different tumor regions may contain:
different mutations,
different metabolic programs,
different resistance pathways.
Targeting one mutation may leave multiple resistant clones untouched.
2. Evolutionary Adaptation
Cancer evolves rapidly under treatment pressure.
Blocking one pathway often causes:
compensatory pathway activation,
metabolic adaptation,
clonal selection,
or phenotypic switching.
For example:
EGFR inhibition → MET amplification,
BRAF inhibition → alternative MAPK activation,
AR blockade → neuroendocrine transformation.
Cancer behaves like an evolving ecosystem.
3. Driver vs Passenger Mutations
Many mutations identified in tumors are:
passenger mutations,
not true biologic drivers.
Sequencing may reveal hundreds of mutations, but only a few may be functionally important.
4. Cancer Is More Than Genetics
Tumor behavior is also shaped by:
metabolism,
mitochondrial function,
immune suppression,
inflammation,
angiogenesis,
stem-cell biology,
and the tumor microenvironment.
Two tumors with identical mutations may behave very differently metabolically.
This is one of the major critiques of purely mutation-centered oncology.
5. Cancer Stem Cells
Many targeted therapies shrink the bulk tumor while:
cancer stem cells survive,
leading to relapse and metastasis.
This is particularly relevant in:
glioblastoma,
pancreatic cancer,
prostate cancer,
and triple-negative breast cancer.
Precision Oncology: Important but Overhyped?
Precision oncology promised:
individualized therapy,
dramatic survival gains,
and highly targeted cures.
The reality has been mixed.
Important Achievements
Better biomarker stratification
Reduced toxicity in some settings
Major responses in selected cancers
Improved understanding of biology
Major Limitations
Resistance emerges rapidly
Benefits often temporary
Very high costs
Many therapies extend life only modestly
Tumor evolution bypasses blockade
The Metabolic Critique
The metabolic oncology perspective argues that:
genetic mutations are often downstream manifestations of deeper metabolic dysfunction,
particularly mitochondrial dysfunction and altered bioenergetics.
From this viewpoint:
targeting mutations alone may not adequately address:
glucose dependency,
glutamine addiction,
inflammatory signaling,
stem-cell metabolism,
or microenvironmental adaptation.
This is why metabolic approaches emphasize:
multi-pathway pressure,
systems biology,
and metabolic flexibility suppression.
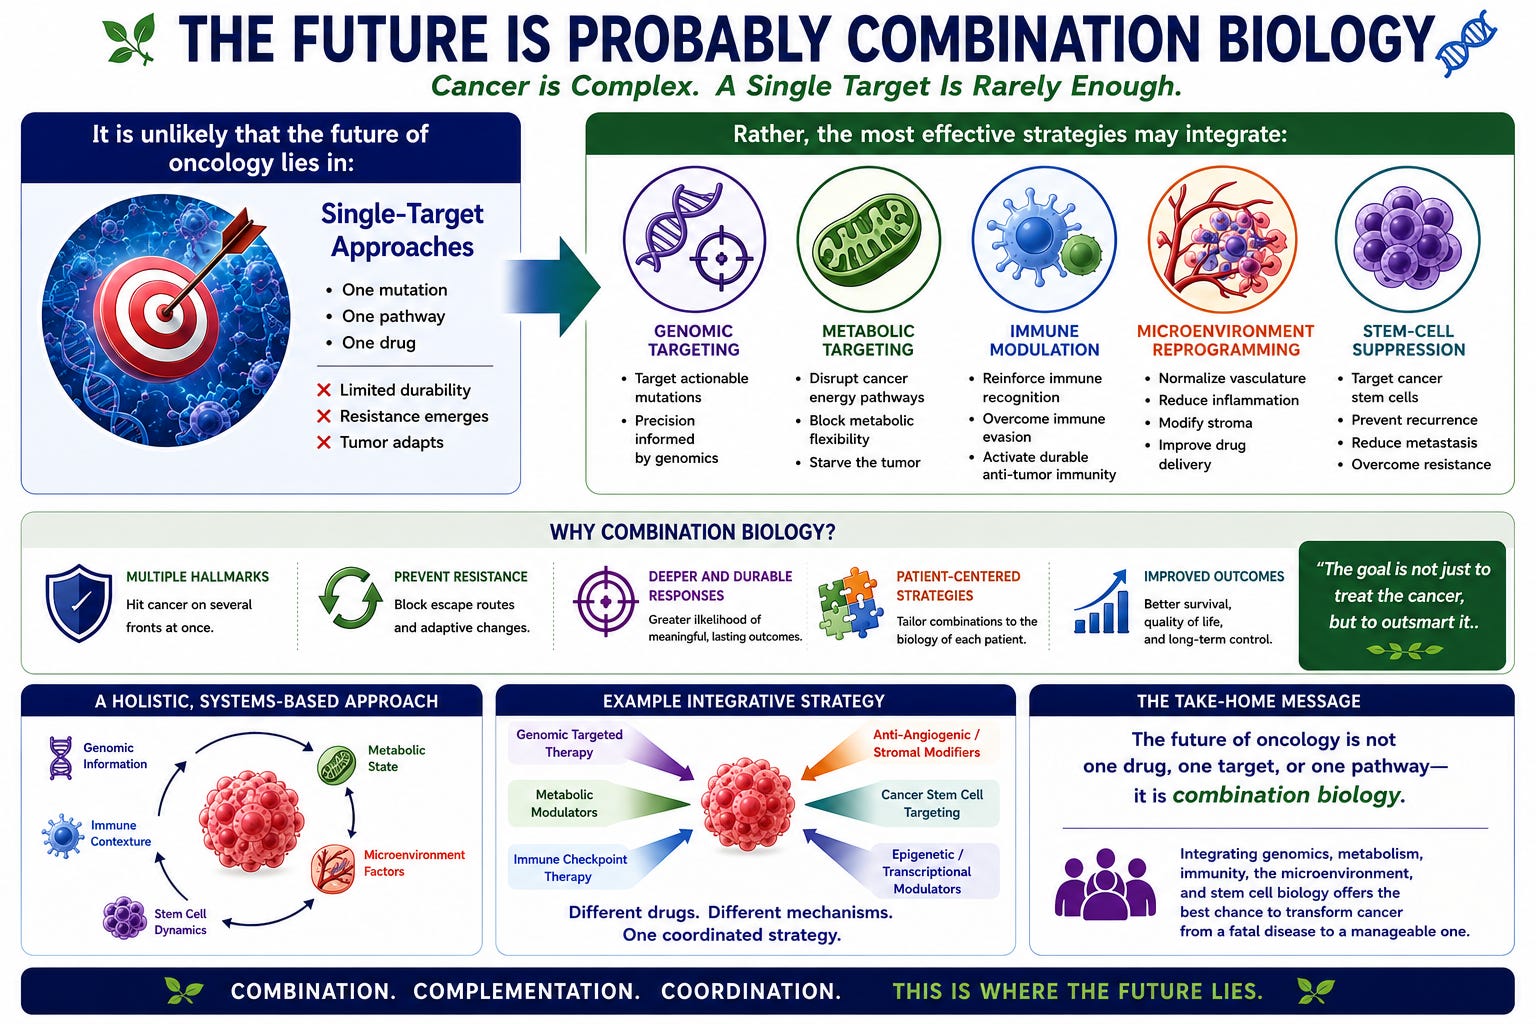
The Future Is Probably Combination Biology
The future of oncology likely lies neither in:
genetics alone,
normetabolism alone.
Rather, the most effective strategies may integrate:
genomic targeting,
metabolic targeting,
immune modulation,
microenvironment reprogramming,
and stem-cell suppression.
In other words:
Cancer is probably best viewed as a complex adaptive systems disease rather than purely a genetic disease.
Bottom Line
Targeting genetic mutations can absolutely improve outcomes in certain cancers and has produced some of the greatest successes in oncology.
However:
many responses are partial or temporary,
resistance commonly develops,
and mutation-centered oncology alone has not fulfilled its original promise of broadly curing advanced cancer.
Cancer biology is increasingly understood to involve:
genetics,
metabolism,
immune signaling,
stem-cell biology,
and evolutionary adaptation simultaneously.
If you’ve found this work valuable, please consider upgrading to a paid subscription. Your support helps me continue independent research and share practical, evolving insights—while giving you access to deeper content and more direct engagement.

References
1. Bailey MH, Tokheim C, Porta-Pardo E, Sengupta S, Bertrand D, Weerasinghe A, et al. Comprehensive Characterization of Cancer Driver Genes and Mutations. Cell. 2018;173(2):371–85.e18.
2. Weinstein JN, Collisson EA, Mills GB, Shaw KR, Ozenberger BA, Ellrott K, et al. The Cancer Genome Atlas Pan-Cancer analysis project. Nat Genet. 2013;45(10):1113–20.
3. Tibau A, Molto C, Borrell M, Del Paggio JC, Barnadas A, Booth CM, et al. Magnitude of Clinical Benefit of Cancer Drugs Approved by the US Food and Drug Administration Based on Single-Arm Trials. JAMA Oncol. 2018;4(11):1610–1.
4. Del Paggio JC, Berry JS, Hopman WM, Eisenhauer EA, Prasad V, Gyawali B, et al. Evolution of the Randomized Clinical Trial in the Era of Precision Oncology. JAMA Oncol. 2021;7(5):728–34.
I have a post on aged garlic extract. Fascinating.
Melanie, thanks for those kind words. Paul