

“After 45 years in medicine, I realized something uncomfortable:
many of the treatments we rely on don’t fail because we use them incorrectly—
they fail because they are built on the wrong model.”
If you’ve found this work valuable, please consider upgrading to a paid subscription. Your support helps me continue independent research and share practical, evolving insights—while giving you access to deeper content and more direct engagement.

Conclusion: The main areas of serotonin research provide no consistent evidence of there being an association between serotonin and depression, and no support for the hypothesis that depression is caused by lowered serotonin activity or concentrations.

The Illusion of Effectiveness: Why Antidepressants Fail
He did everything right.
He saw his doctor.
He took the medication.
He waited.
Weeks passed.
“Give it more time,” he was told.
Months passed.
The dose was increased. Then changed. Then combined with another drug.
Still… nothing.
Not better.
Not worse.
Just… the same.
This is not an unusual story.
It is the typical story.
And yet, it is rarely told honestly.
The Promise
When selective serotonin reuptake inhibitors (SSRIs) were introduced, they came with a powerful narrative:
Depression is caused by a chemical imbalance.
Specifically, a deficiency of serotonin.
Correct the imbalance—and the patient improves.
It was simple.
It was persuasive.
And it was never actually proven.
The Reality
After decades of use and billions of prescriptions, the data tell a very different story.
The landmark STAR*D trial—the largest real-world antidepressant study ever conducted—found:
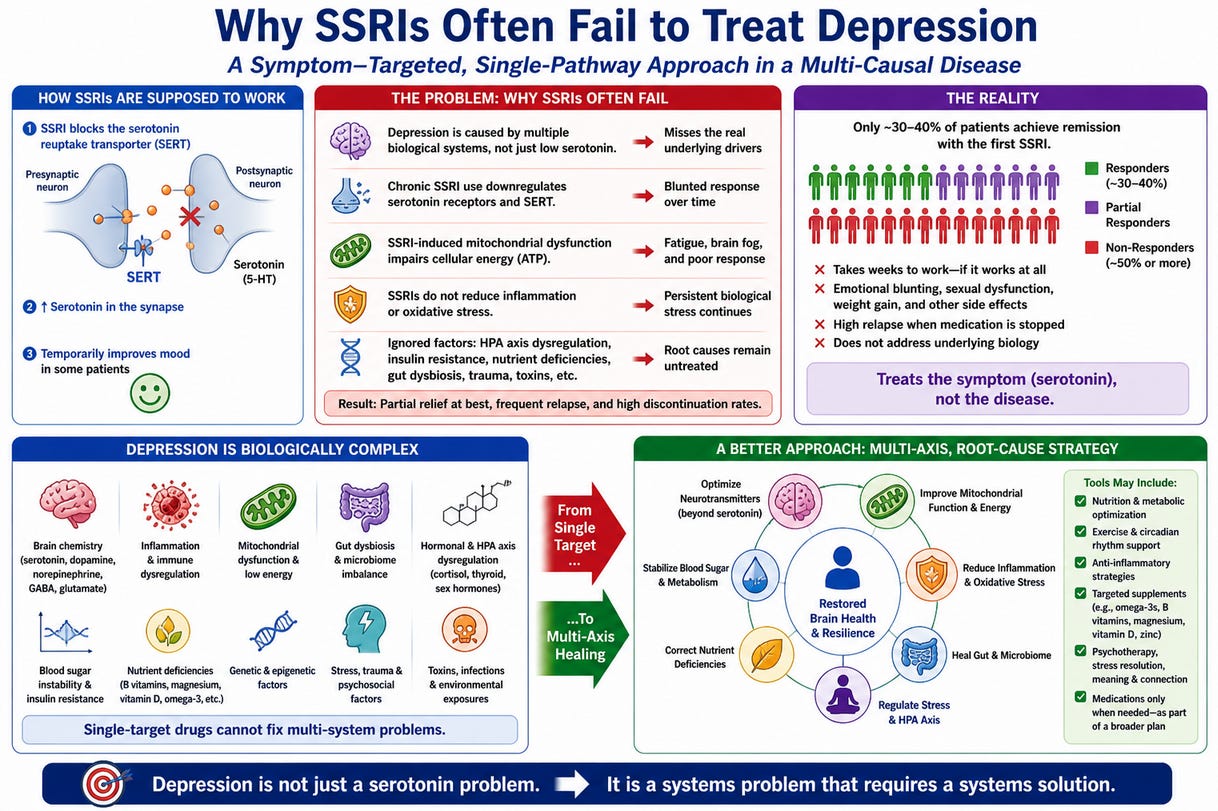
Only ~30% of patients achieved remission with initial treatment (short term)
More than 70% failed to achieve sustained remission
And when you look more closely:
Only ~3% of patients experienced sustained, durable recovery over one year
That is not a breakthrough.
That is a system failure.
The Placebo Problem
Perhaps even more striking is this:
In large FDA analyses:
~50% improve on antidepressants
~40% improve on placebo
A difference of about 10%.
And even that difference may be overstated due to:
Unblinding (patients feel side effects and guess they are on the drug)
Selective reporting
Industry-sponsored bias
In practical terms:
For many patients, antidepressants perform only marginally better than expectation alone.
Severity Doesn’t Save the Model
One might assume that antidepressants work better in severe depression.
But even here, the benefit is modest.
In some analyses:
The drug advantage amounts to only a few days of earlier improvement compared to placebo
Not weeks. Not months.
Days.
The Deeper Problem: They Don’t Fix the Disease
Even when antidepressants “work,” they rarely cure depression.
Relapse is common.
Chronicity is common.
And long-term outcomes are disappointing.
Even Worse: Antidepressants may, in some cases, become depressogenic with long-term use
This is not widely discussed—but it aligns with clinical observation:
Patients cycle through medications
Episodes become more frequent
The illness becomes more entrenched
The Cost of Treatment
If antidepressants were benign, modest benefit might be acceptable.
They are not.
The side effect profile is substantial:
Sexual dysfunction (~60%)
Emotional blunting
Cognitive dulling
Agitation and anxiety
Weight gain
More concerning:
Increased risk of suicidal ideation
Akathisia (a state of severe inner restlessness)
Behavioral dysregulation
In some populations:
Increased mortality has been reported
Increased violent behavior in younger patients has been observed
The Withdrawal Trap
One of the least appreciated aspects of SSRIs is how difficult they are to stop.
~56% experience withdrawal symptoms
Nearly half of these are severe
And here is the critical problem:
Withdrawal is often misinterpreted as relapse.
So the drug is restarted.
And the cycle continues.
Why This Is Happening
The problem is not that SSRIs do nothing.
They do something.
But they target the wrong level of the disease.
Depression is not simply a serotonin disorder.
It involves:
Inflammation
Metabolic dysfunction
Circadian disruption
Neuroplastic impairment
Gut–brain interactions
SSRIs primarily affect one downstream pathway.
And even that effect is modest.
A Mismatch Between Model and Reality
We have been treating depression as if it were:
→ A single neurotransmitter deficiency
But it behaves like:
→ A multi-system disorder
This mismatch explains everything:
Why response rates are low
Why relapse is common
Why treatment resistance is widespread
The Clinical Truth
Most patients do not say:
“The medication cured me.”
They say:
“It helped a little.”
“It took the edge off.”
“I still don’t feel like myself.”
That is not remission.
That is partial suppression of symptoms.
Where Do SSRIs Fit?
Despite these limitations, SSRIs still have a role:
Severe depression
Acute stabilization
Selected patients who respond well
But they should not be:
The default
The only intervention
The foundation of treatment
The Bigger Shift
The failure of SSRIs is not just a pharmacologic issue.
It is a conceptual one.
We asked the wrong question:
“Which drug fixes depression?”
Instead of:
“What biological systems are dysregulated—and how do we restore them?”
Final Thought
The most important lesson is not that SSRIs are ineffective.
It is that:
Depression is far more complex than we were taught.
And until we align our treatments with that complexity…
We will continue to see what we see now:
Patients doing everything right—
and still not getting better.
This was the first of a 3 part series.
The next post explores the epidemiology and clinical features of depression.
In final piece, we will explore what happens when we abandon the reductionist model—and begin treating depression as the whole-body disease it actually is.

Do any doctors ever try to discover the reason for depression?
Childhood trauma was the root cause for me. Drugs just quelled the negative voices in my head that were put there by my critical and abusive parents, they never cured me. In fact, I felt suicidal more often while on SSRi’s.
I am off all meds after 32 years, praise God.
𝗦𝗦𝗥𝗜
𝗦.𝚎𝚟𝚎𝚛𝚎
𝗦.𝚞𝚒𝚌𝚒𝚍𝚊𝚕
𝗥.𝚊𝚐𝚎
𝗜.𝚗𝚍𝚞𝚌𝚎𝚛