

This is PERSONAL. Current data demonstrates that one in two men and one in three women will develop a cancer in their lifetime. The time to take action is NOW. This series of sub-stacks will inform you on understanding cancer and what YOU can to to limit your risk. PAY attention. And Read all the posts.
Thank you for following these posts and your support.
Paul Marik, MD
Cancer remains one of the dominant public health challenges of the modern era, with profound human, economic, and societal consequences. Globally, cancer accounts for approximately 10 million deaths annually, a figure that has continued to rise due to population growth, aging demographics, and increasing exposure to metabolic and environmental risk factors.
In the United States, nearly 2 million new cancer diagnoses occur each year, with over 600,000 deaths annually, making cancer the second leading cause of death, exceeded only by cardiovascular disease.(1, 2) Despite major advances in molecular biology, diagnostics, and therapeutics, overall population-level mortality improvements have been modest when compared with gains seen in cardiovascular medicine. Furthermore, number of new cases of cancer has been steadily increasing over the last 2 decades (see figure 1 & 2).(3, 4)
Cancer in young adults has been rising for several decades, even while cancer rates in older people have plateaued or fallen in many countries. The increase is real but varies by cancer type, sex, and region, and is driven by a mix of lifestyle, environmental, and possibly early‑life biological factors. Globally, cancers diagnosed before age 50 rose by about 79% in incidence and 28% in mortality between 1990 and 2019. In the US, early‑onset cancers (<50) increased substantially from 2010 to 2019, with especially notable rises in breast, colorectal, pancreatic, kidney, and reproductive organ cancers. (3-5)
Figure 1.
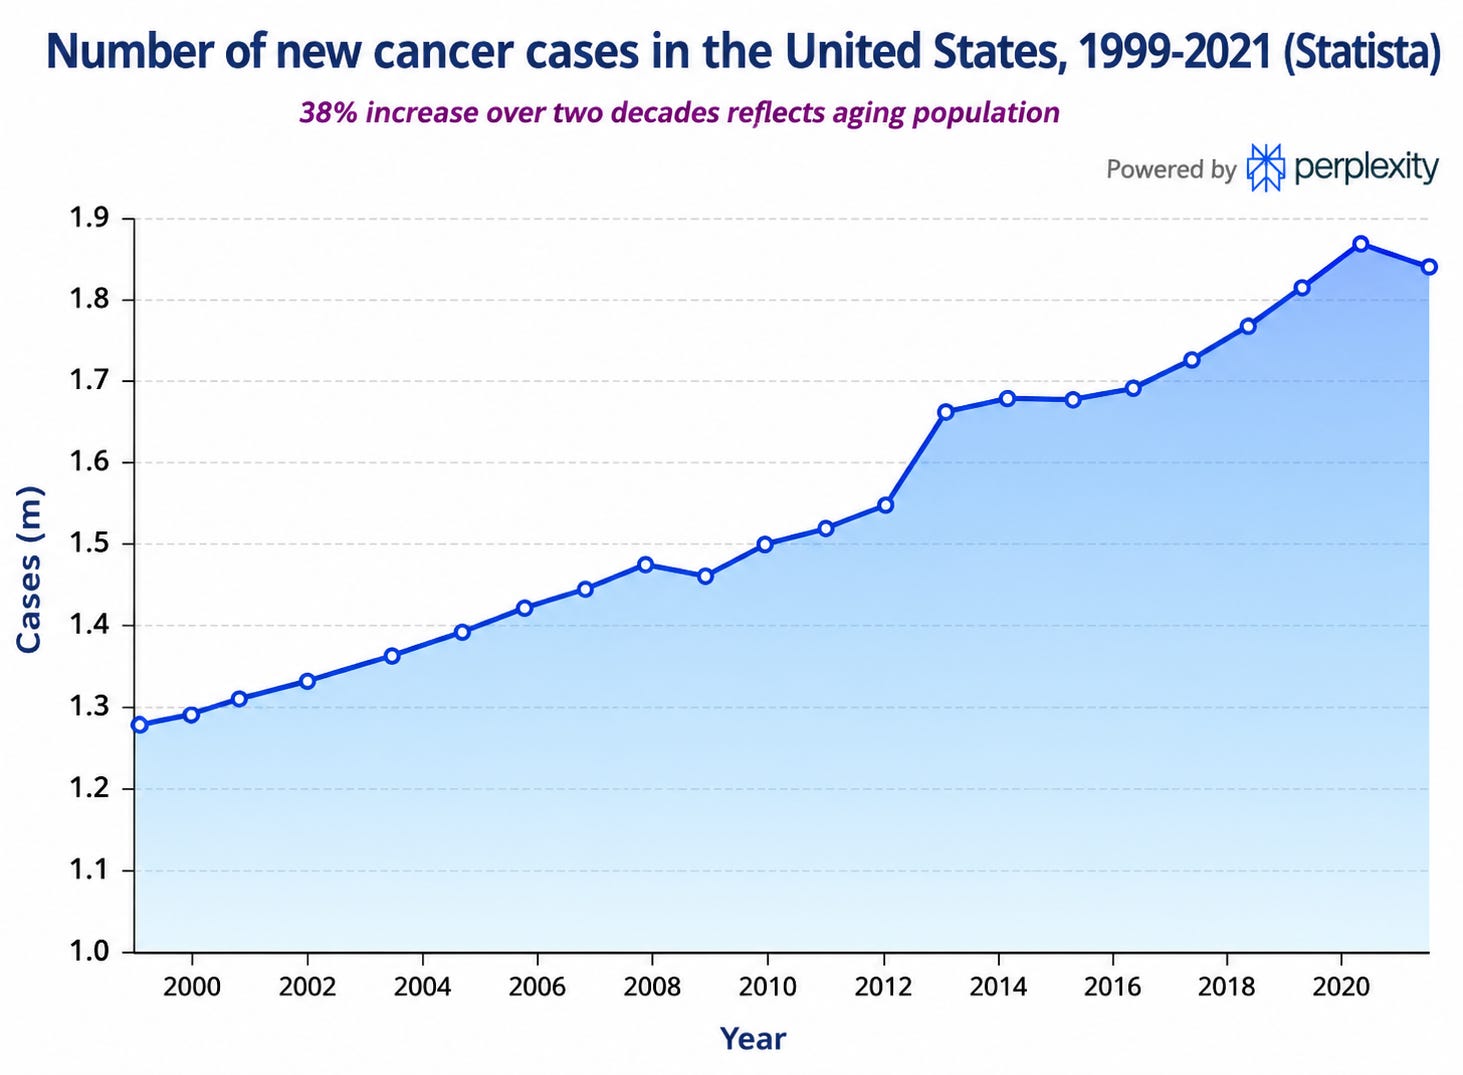
Figure 2. The Cancer Epidemic (data from American Cancer Association).
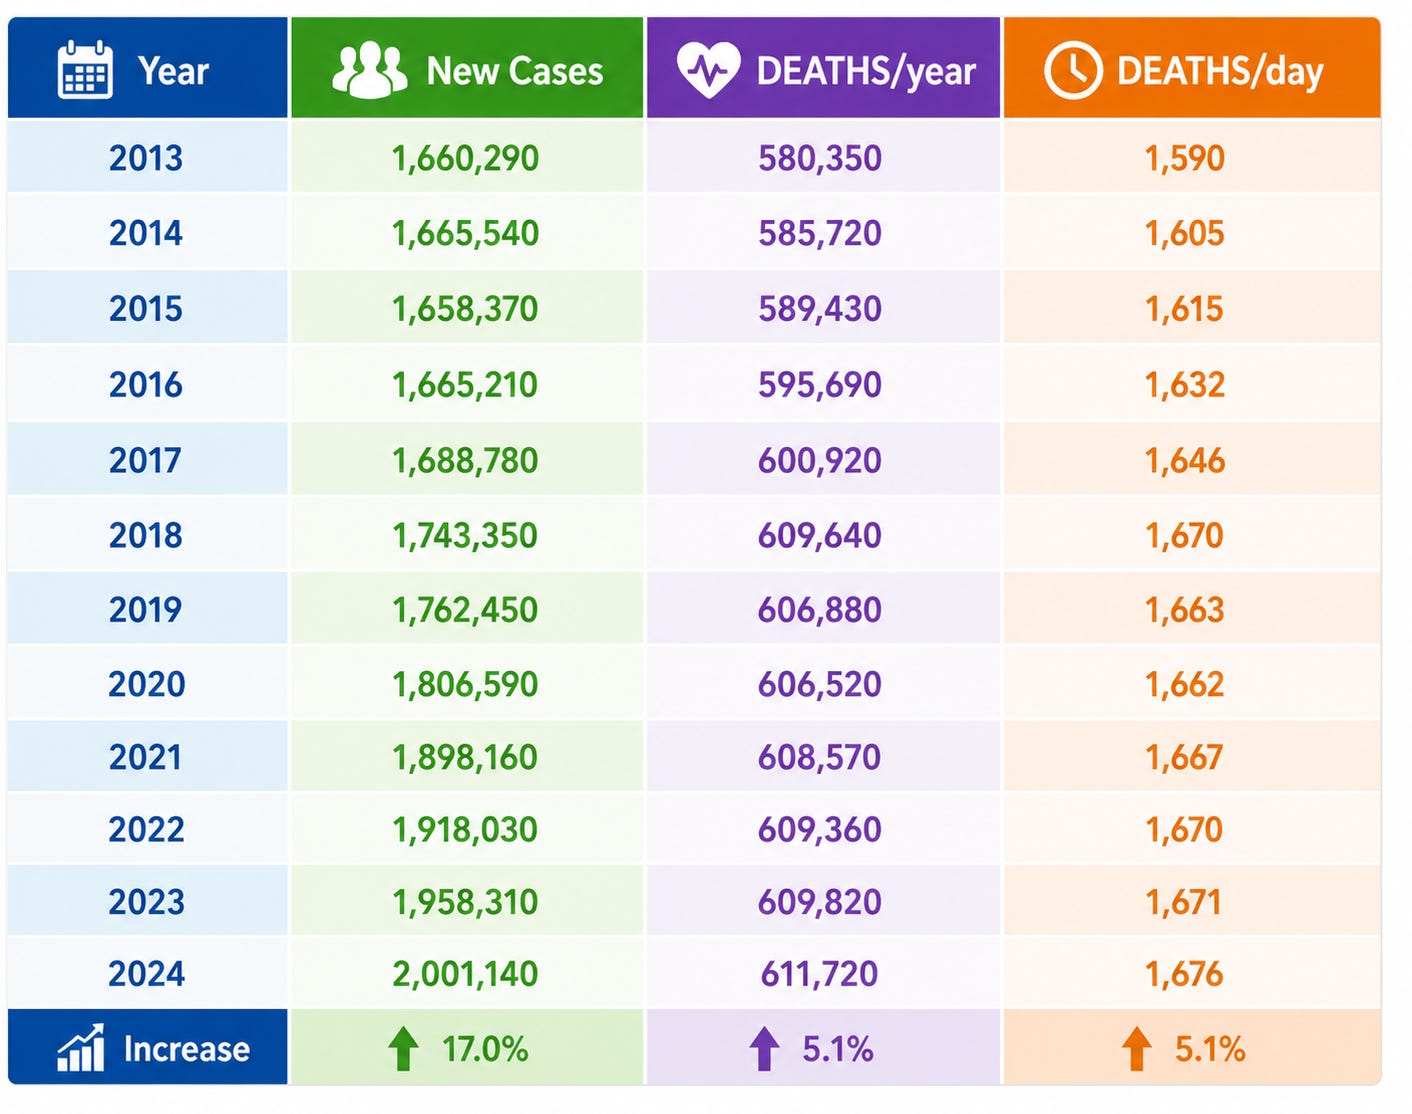
Figure 3. The most common types of cancer in the US
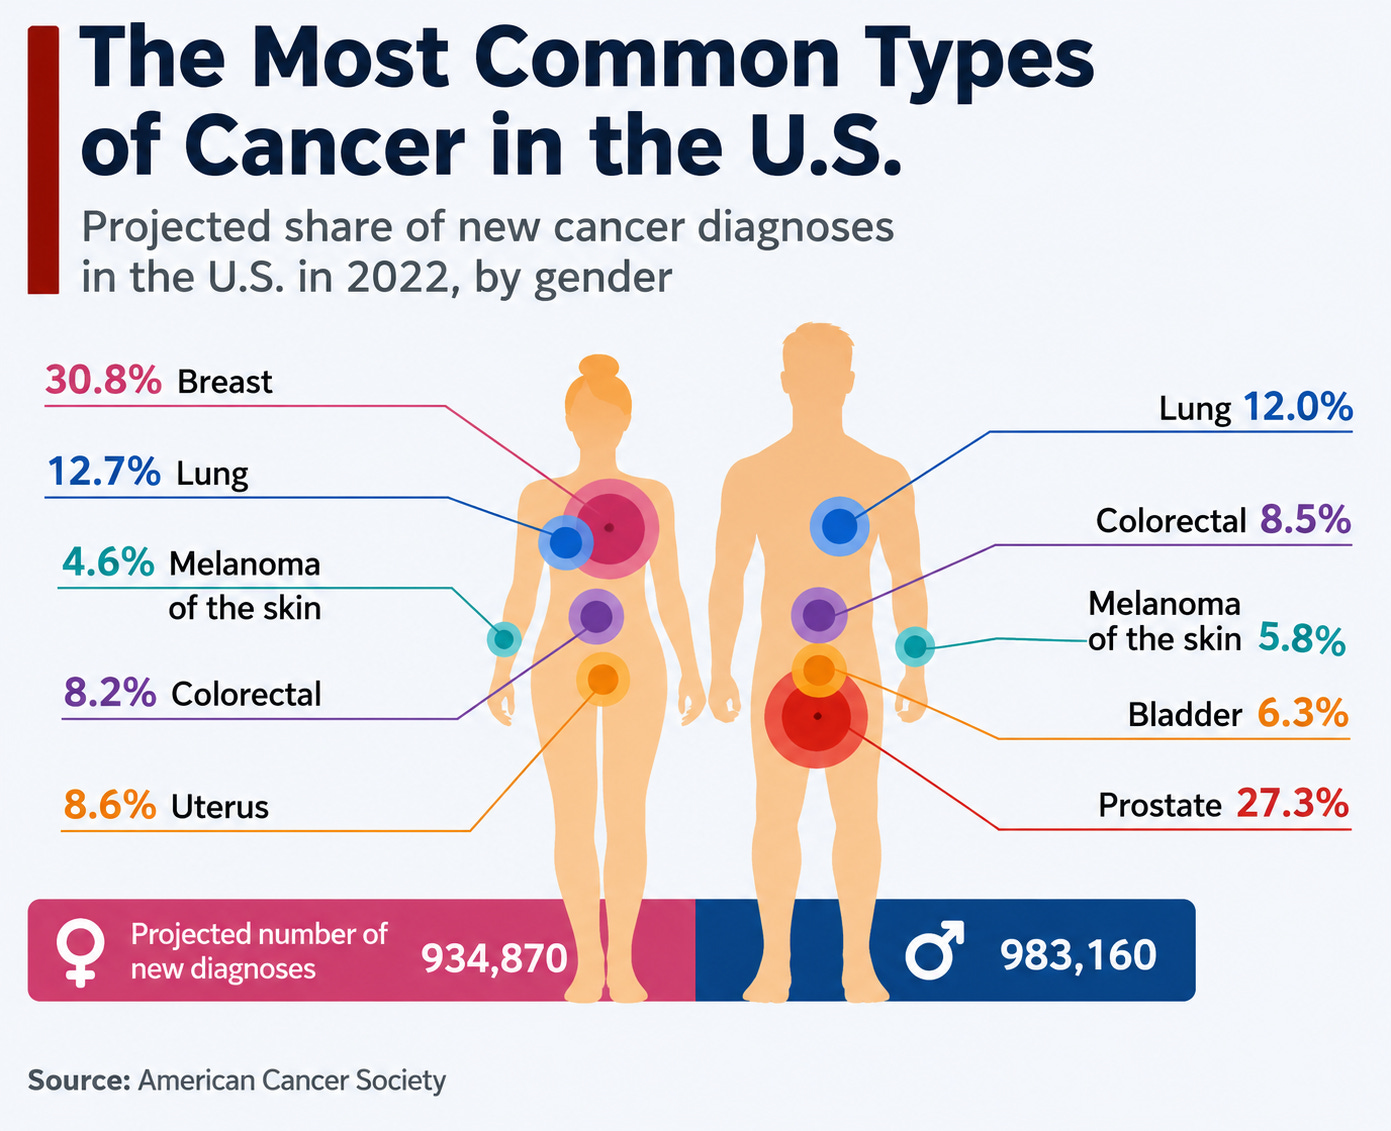
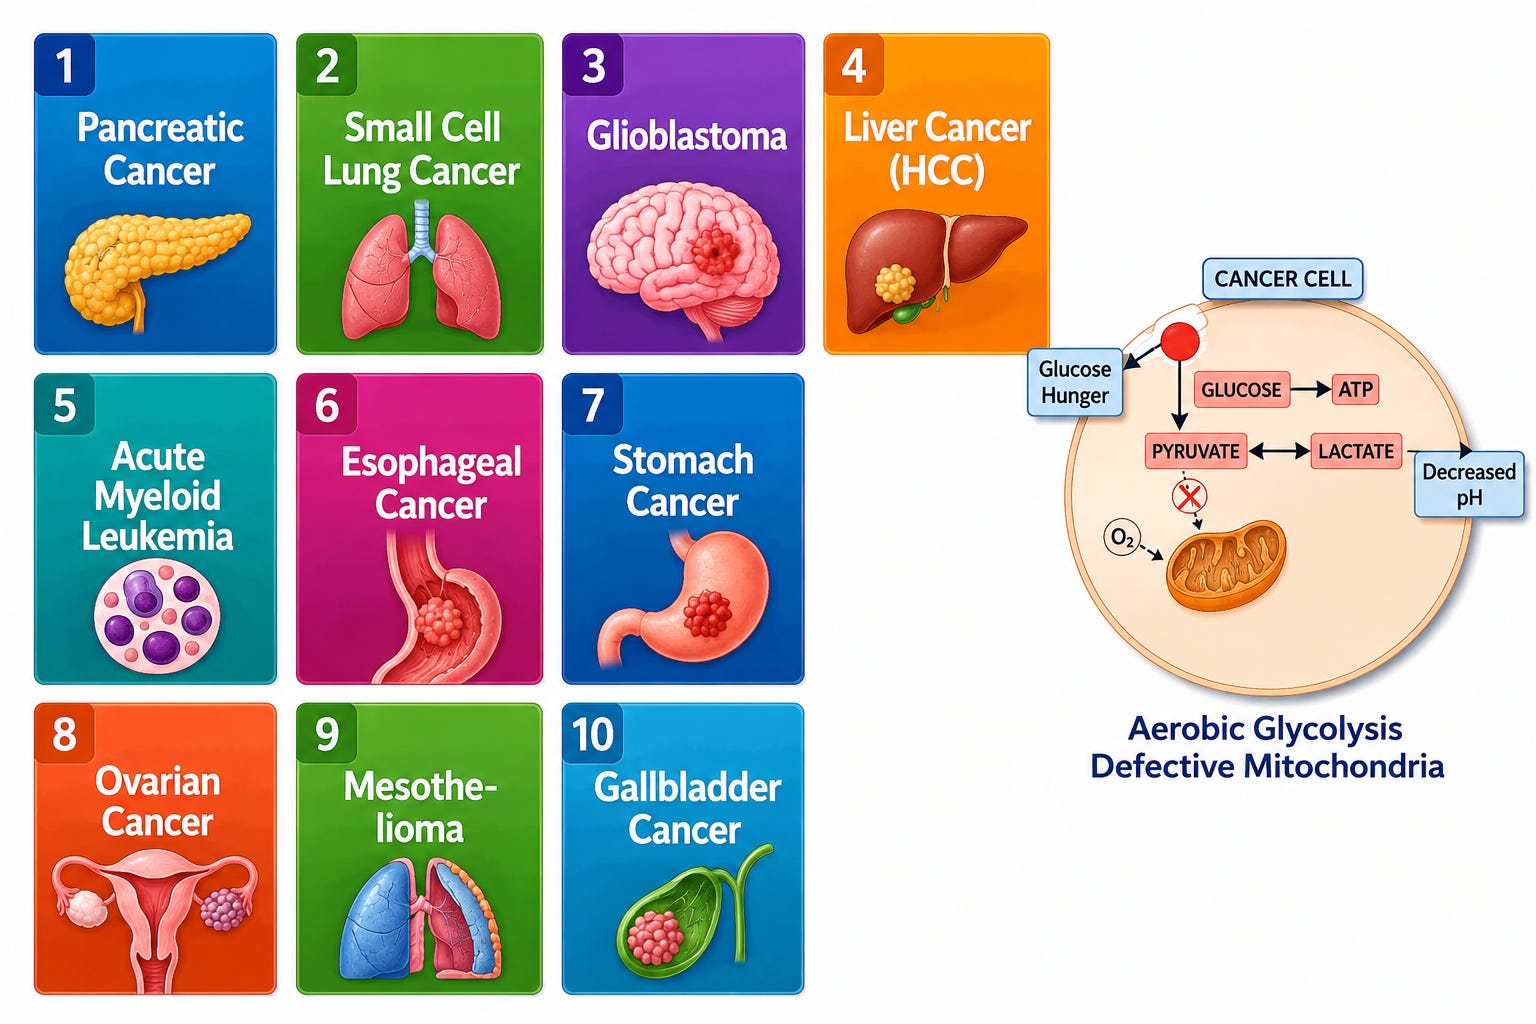
Figure 4. The 10 deadliest Cancer
Preventability and Modifiable Risk Factors
An estimated 40–45% of newly diagnosed cancers in the U.S. are potentially preventable. These are largely driven by modifiable exposures and behaviors, including:
Tobacco use
Insulin resistance and metabolic dysfunction
Poor diet quality and ultra-processed food consumption
Physical inactivity
Excess alcohol intake
Importantly, emerging evidence increasingly implicates metabolic dysfunction—particularly insulin resistance—rather than obesity per se as a central driver of cancer risk. Individuals with insulin resistance, elevated triglyceride-to-HDL ratios, and features of metabolic syndrome face increased risks not only for cardiovascular disease and neurodegeneration, but also for multiple malignancies.
Environmental and Chemical Exposure
Modern societies are characterized by pervasive exposure to industrial chemicals, endocrine disruptors, and environmental carcinogens. While the precise contribution of these exposures is difficult to quantify, the cumulative burden of chronic low-dose exposure is increasingly recognized as a biologically plausible contributor to cancer initiation and progression.
Figure 5. Risk factors for Cancer
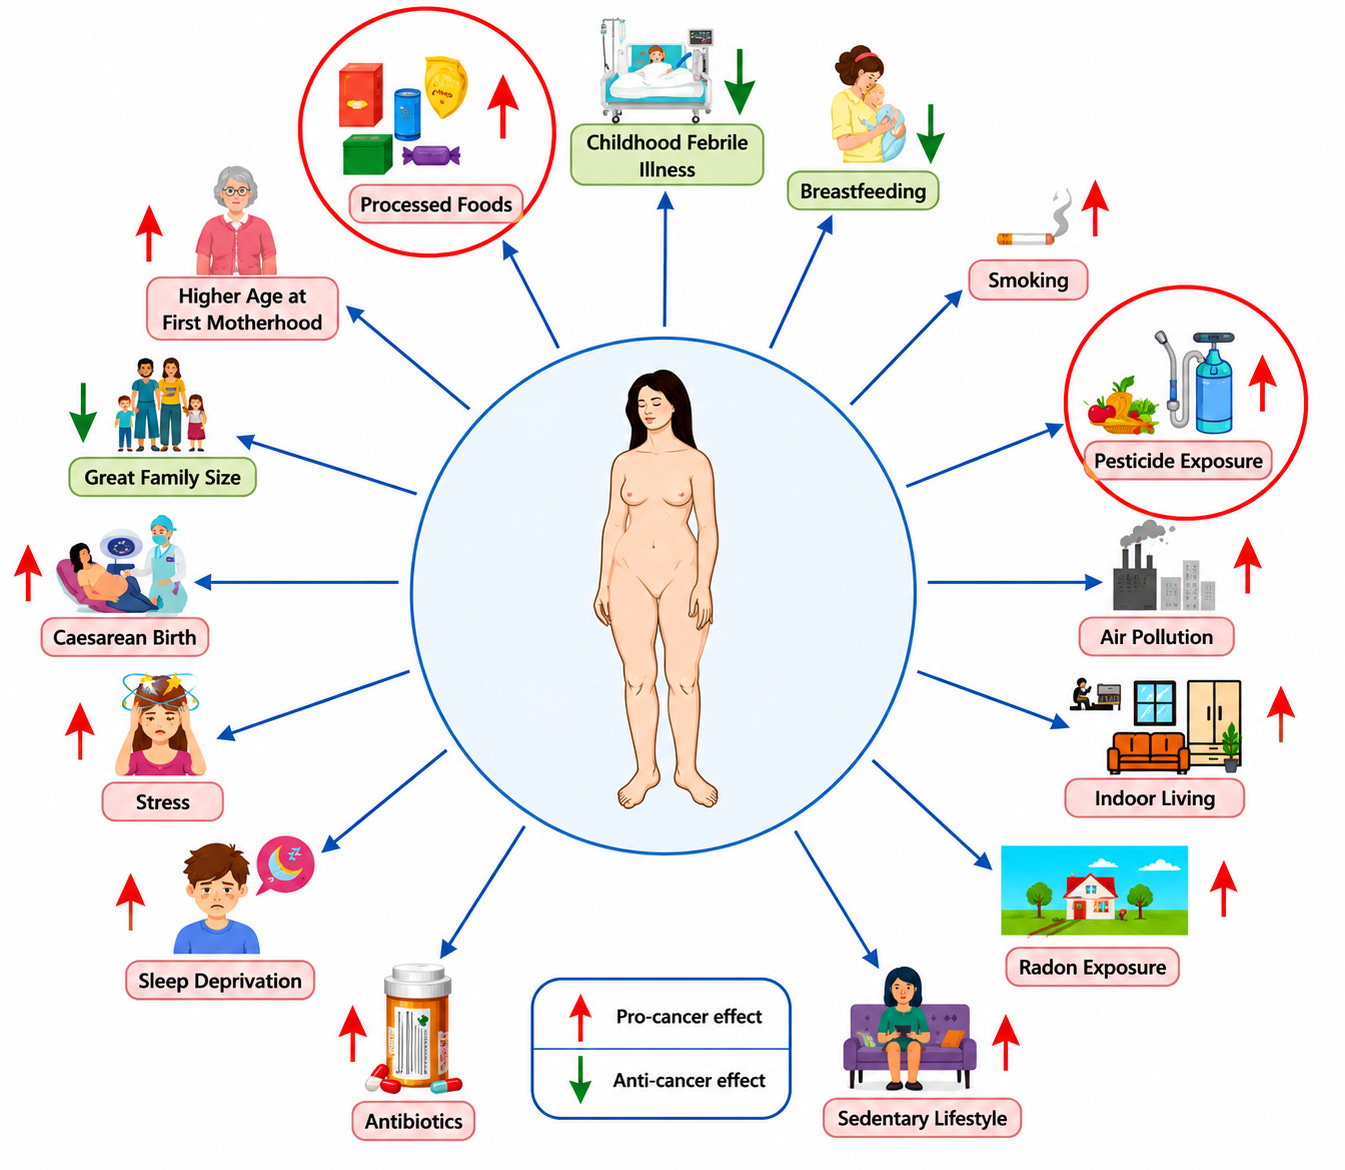
Common Pathways to Malignancy
Clinical observations and epidemiologic data suggest that most cancer patients share at least one dominant risk pathway, including:
Tobacco exposure
Insulin resistance and hyperinsulinemia
Oncogenic viral infections
Inherited genetic syndromes (e.g., BRCA mutations, familial adenomatous polyposis)
These pathways converge on shared mechanisms: chronic inflammation, mitochondrial dysfunction, genomic instability, immune dysregulation, and altered cellular metabolism.
The Cost and Complexity of Modern Oncology
Contemporary cancer care relies on increasingly complex multimodal strategies—surgery, radiation, cytotoxic chemotherapy, targeted agents, and immunotherapies. While technologically sophisticated, many of these interventions offer limited absolute survival benefit, often at the expense of substantial toxicity and diminished quality of life.
Cancer-related healthcare spending in the United States now exceeds $400 billion annually, a figure that continues to rise sharply due to escalating drug prices and prolonged treatment courses (see Figure . The economic burden on patients and families—commonly termed “financial toxicity”—has become a defining feature of modern cancer care, contributing to treatment nonadherence, bankruptcy, and psychological distress.(6)
Figure 6. Cost of Oncology Drugs
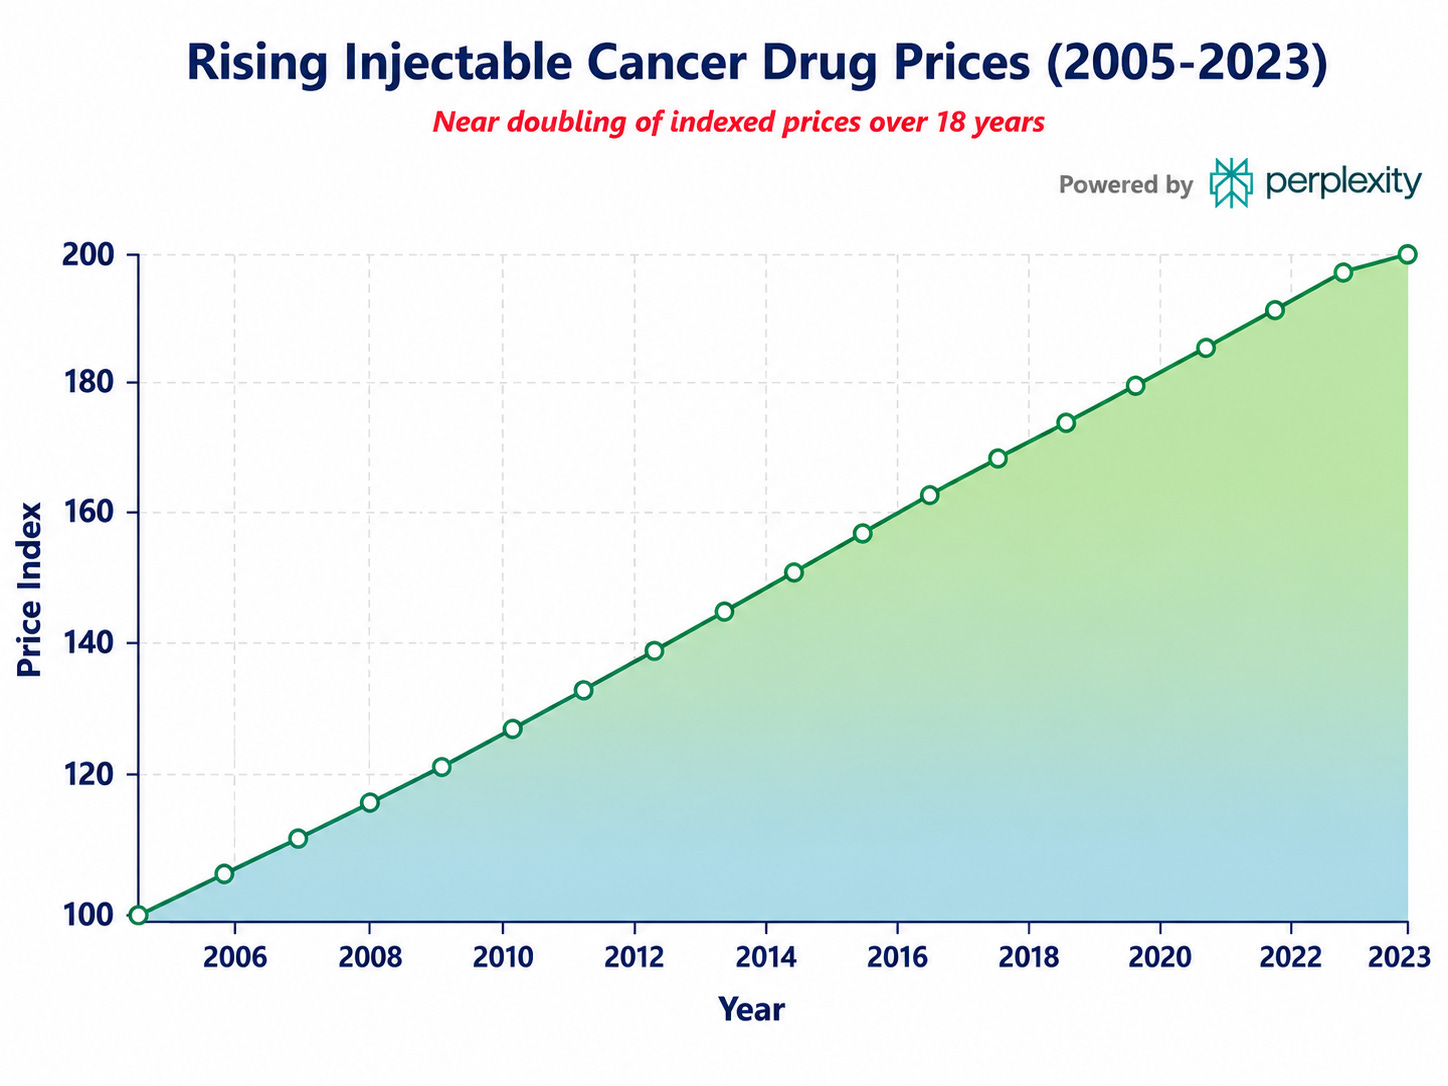
By the early 2010s, oncology had become one of the most lucrative sectors in pharmaceutical medicine, with multiple single agents generating billions of dollars in annual revenue. The commercialization of cancer care has profoundly shaped research priorities, clinical guidelines, and treatment norms.
Outcomes: A Disquieting Reality
Despite extraordinary financial investment, age-adjusted mortality rates for many common cancers—including lung, breast, colorectal, prostate, and pancreatic cancer—have improved only modestly over the past several decades. When viewed against the dramatic reductions in cardiovascular mortality over the same period, progress in oncology appears disproportionately limited.
Seminal analyses have demonstrated that, across common adult malignancies, the contribution of cytotoxic chemotherapy to 5-year survival remains small at the population level. While incremental gains have occurred, overall 5-year survival in the U.S. has increased only modestly over the past 25–30 years.
Implications
These realities suggest that the dominant cancer paradigm—focused primarily on late-stage intervention and high-cost therapeutics—has reached diminishing returns. There is an urgent need for:
Earlier metabolic and lifestyle-based prevention
Less toxic and more affordable treatment strategies
Systems-level approaches that address cancer as a metabolic, immunologic, and environmental disease
Absent a fundamental shift in strategy, cancer will continue to impose escalating human and economic costs while delivering only incremental improvements in long-term outcomes.

References
1. Siegel RL, Giaquinto AN, Jemal A. Cancer Statistics, 2024. CA Cancer J Clin. 2024.
2. Siegel RL, Wagle NS, Cercek A, Smith RA, Jemal A. Colorectal cancer statistics, 2023. CA Cancer J Clin. 2023;73(3):233–54.
3. Patel VR, Adamson AS, Welch HG. The Rise in Early-Onset Cancer in the US Population-More Apparent Than Real. JAMA Intern Med. 2025.
4. Sung H, Jiang C, Bandi P, Minihan A, Fidler-Benaoudia M, Islami F, et al. Differences in cancer rates among adults born between 1920 and 1990 in the USA: an analysis of population-based cancer registry data. Lancet Public Health. 2024;9(8):e583–e93.
5. Ugai T, Sasamoto N, Lee HY, Ando M, Song M, Tamimi RM, et al. Is early-onset cancer an emerging global epidemic? Current evidence and future implications. Nat Rev Clin Oncol. 2022;19(10):656–73.
6. Yabroff KR, Mariotto A, Tangka F, Zhao J, Islami F, Sung H, et al. Annual Report to the Nation on the Status of Cancer, Part 2: Patient Economic Burden Associated With Cancer Care. J Natl Cancer Inst. 2021;113(12):1670–82.
Agree with many of the statements made here, but a few key points are worth clarifying.
First, cancer mortality has not improved only modestly. In the U.S., age-adjusted cancer death rates have declined by roughly 30–35% since the early 1990s. That translates into millions of deaths avoided. The gains are not uniform for all cancers, but they are real, particularly in lung, breast, colorectal cancer, and melanoma.
Second, it is true that cardiovascular mortality has fallen more dramatically over a longer time horizon. But these diseases are fundamentally different. Coronary artery disease has benefited from highly scalable interventions. Cancer is not one disease, and progress tends to occur one subtype at a time.
Third, the often-cited claim that chemotherapy contributes only a small fraction to survival comes from older analyses that looked specifically at cytotoxic chemotherapy and excluded a large portion of treatments including hormonal therapy for breast cancer and prostate cancer. It does not reflect the last 5 or so years of oncology practice, where we have shifted to targeted therapy, immunotherapy, and better adjuvant systemic treatments which have significantly improved outcomes in multiple cancers.
Finally, overall 5-year survival has increased meaningfully over time, from about 50% in the 1970s to close to 70% today in the U.S. That is not a trivial change, even if some cancers still lag behind.
We appreciate this article and sharing it with our community.