


A deeper look at influenza reveals it’s not just a virus—but a multi-system failure we’ve been oversimplifying for decades.
Every winter, millions get the flu.
Most recover. Some don’t.
And the difference isn’t what we’ve been told
Abstract
Influenza remains a major global cause of illness, hospitalization, and death. Traditional treatment has focused primarily on antiviral therapy, particularly the neuraminidase inhibitor oseltamivir (Tamiflu), together with supportive care. However, the clinical benefits of oseltamivir have long been debated, and recent evidence in critically ill patients has raised additional concerns about its effectiveness and potential for harm.
At the same time, our understanding of severe influenza has evolved. Influenza is not simply a problem of viral replication; disease severity reflects a complex interaction between the virus and the host, involving immune dysregulation, inflammation, oxidative and mitochondrial stress, epithelial injury, and impaired mucosal defenses. This broader understanding provides a rationale for looking beyond a single antiviral drug.
This narrative review examines the contemporary evidence for influenza treatment, with particular attention to host-directed and multi-target (“multi-axis”) strategies. Rather than focusing exclusively on suppressing viral replication, this approach considers interventions that simultaneously target the virus, modulate the host immune and inflammatory response, limit cellular injury, support mucosal defenses, and preserve physiological resilience. The central premise is simple: to improve outcomes from influenza, we may need to treat the patient, not just the virus.
It starts the same way every time.
A patient walks in, exhausted, febrile, aching in places they didn’t know could ache. They’ve been told, “It’s just the flu.” Rest. Fluids. Maybe an antiviral—if they’re lucky enough to be seen early.
And yet, some recover quickly… while others spiral.
What we call “influenza” is not a single process. It is a biological cascade—a collision between a virus and a host. And what determines the outcome is not just the virus itself, but the terrain it encounters: the immune system, the mitochondria, the oxidative balance, the inflammatory response.
We’ve spent decades trying to treat influenza as if it were a single-target disease.
It isn’t.
The virus
Influenza is a virus that has evolved to do one thing very efficiently—infect the lining of the human respiratory tract and spread rapidly from person to person.
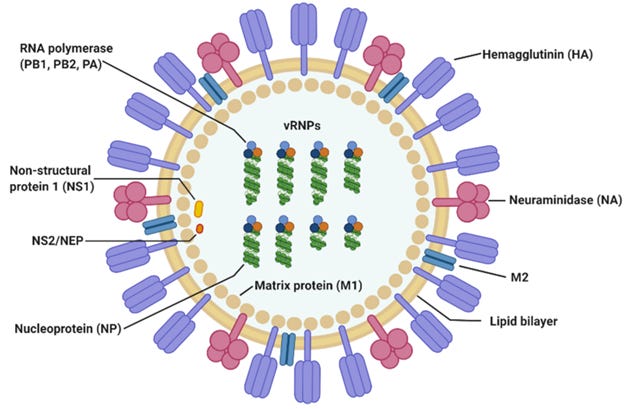
At its core, influenza is a small, enveloped RNA virus. The envelope is a fragile outer coating made from lipids, which is why simple measures like soap and alcohol are so effective at destroying it. Embedded in this outer layer are two critical proteins—hemagglutinin (HA) and neuraminidase (NA)—that determine how the virus behaves.
Hemagglutinin acts like a key. It allows the virus to attach to and enter cells lining the nose, throat, and lungs. Once inside, the virus releases its genetic material—RNA—into the cell. Unlike most RNA viruses, influenza does something unusual: it briefly uses the host cell nucleus to replicate. It then hijacks the cell’s machinery to produce thousands of new viral particles. Neuraminidase then acts like a release mechanism, helping these newly formed viruses escape the infected cell and spread to neighboring cells.
What makes influenza particularly challenging is the structure of its genome. Instead of a single continuous strand, its RNA is divided into multiple segments (eight in influenza A and B). This segmented design gives the virus remarkable flexibility.
Over time, small copying errors occur in the genes that encode HA and NA. These gradual changes—called antigenic drift—are the reason influenza returns each year in slightly altered forms, requiring updated vaccines.
More dramatically, if two different influenza viruses infect the same host (for example, a pig exposed to both avian and human strains), these RNA segments can mix and match. This process, known as antigenic shift, can produce an entirely new virus against which humans have little or no immunity. It is this mechanism that underlies influenza pandemics.
Clinically, the damage caused by influenza is not just from the virus itself, but from the body’s response to it. The virus destroys the epithelial cells that line the respiratory tract, impairing normal defenses. At the same time, it triggers a strong immune response, releasing inflammatory mediators that produce the characteristic symptoms—fever, muscle aches, fatigue, and cough.
This combination—direct tissue injury and an intense inflammatory response—also explains why influenza can predispose patients to secondary bacterial infections, particularly pneumonia.
In simple terms, influenza is a highly adaptable respiratory virus whose success lies in three features: its ability to efficiently enter and exit cells, its segmented genome that allows constant change, and its capacity to provoke a strong host response. These properties make it a persistent and sometimes unpredictable pathogen, responsible for both seasonal outbreaks and, occasionally, global pandemics.
Types of Influenza
There are three main types that infect humans:
Influenza A → most important clinically
Causes seasonal epidemics and pandemics
Found in humans, birds, pigs
Influenza B → milder, seasonal outbreaks only
Influenza C → uncommon, usually mild
Figure 1. Influenzae A virus
Why It Causes Disease
Destroys respiratory epithelial cells
Triggers strong immune response (cytokines)
Leads to symptoms: fever, myalgia, cough, fatigue
Key Clinical Insights
Incubation: ~1–4 days
Transmission: droplets & aerosols
High mutation rate → immunity is incomplete and temporary
Secondary bacterial pneumonia is a major complication
Influenza is often perceived as a self-limited viral illness; however, its most serious consequences arise not from the virus alone, but from secondary bacterial pneumonia, which remains the leading cause of mortality in severe influenza infections. Among these, infection with Staphylococcus aureus is particularly important due to its aggressive clinical course and high fatality rate.
Treatment of Influenzae
The Problem With the Traditional Approach
The standard model of influenza treatment is simple:
Identify the virus (make the diagnosis)
Prescribe an antiviral (usually a neuraminidase inhibitor)
Provide symptomatic relief
But this model has three major limitations:
Neuraminidase inhibitors can be harmful in the sickest patients — the first randomized controlled trial of oseltamivir in critically ill influenza patients (REMAP-CAP) found it highly likely to increase 90-day mortality compared with no antiviral treatment, regardless of a 5- or 10-day course. The trial was stopped early on efficacy grounds after crossing a pre-specified inferiority threshold.(1) (see review at end of post)
Outside the ICU, evidence that neuraminidase inhibitors meaningfully reduce complications — pneumonia, hospitalization, mortality — remains inconsistent and population-dependent.
Ignores host biology — the immune response, not the virus alone, drives severity.
This explains a clinical reality every physician recognizes:
Two patients. Same virus. Completely different outcomes.
What Is a Neuraminidase Inhibitor?
Neuraminidase inhibitors are antiviral drugs designed to limit the spread of influenza A and B viruses within the body. They block neuraminidase, an enzyme on the surface of the influenza virus that helps newly formed viral particles escape from infected cells and infect neighboring cells. By inhibiting this enzyme, these drugs reduce the release and spread of new virus particles.
The best-known neuraminidase inhibitors are oseltamivir (Tamiflu), taken orally, and zanamivir (Relenza), which is inhaled. Their antiviral mechanism is well established; however, demonstrating an antiviral effect is not the same as demonstrating improved clinical outcomes, particularly once influenza has progressed to critical illness.
A Different Way to Think About Influenza
Influenza is best understood not as a viral illness alone, but as a multi-axis biological stressor:
Viral replication in the nasopharynx
Dysregulated immune response
Oxidative and mitochondrial injury
Inflammatory lung damage
This immediately suggests something important:
No single therapy is likely to be sufficient.
Instead, treatment should apply simultaneous pressure across multiple biological systems.
The Multi-Axis Treatment Model of Influenzae
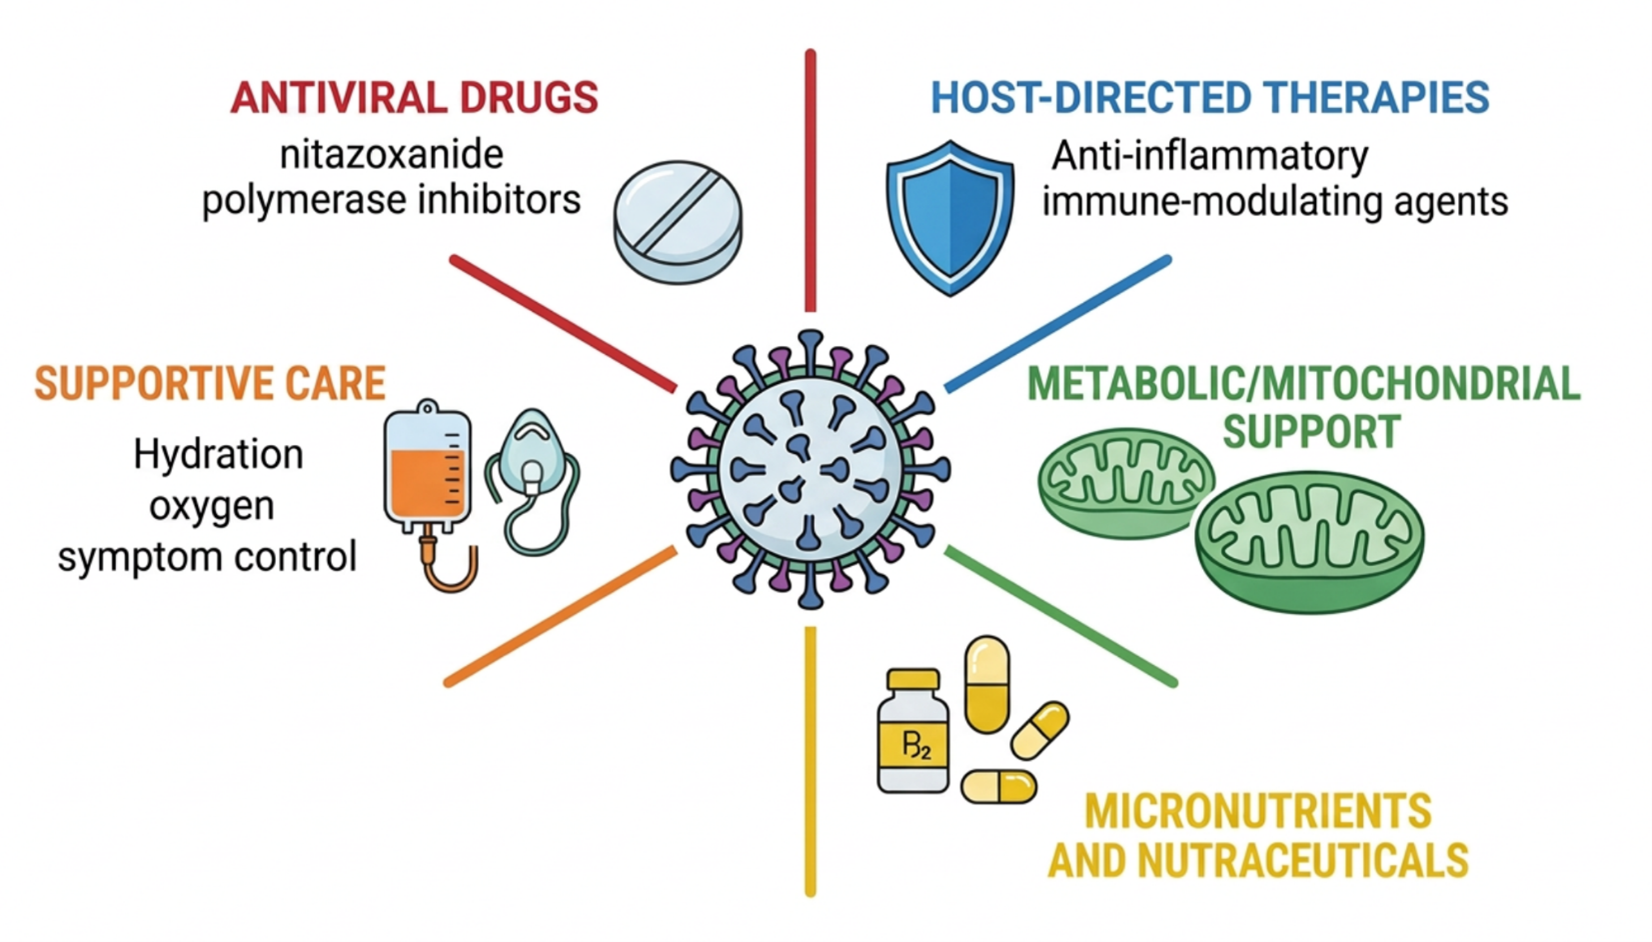
A more effective strategy integrates four key domains:
1. Reduce Viral Load at the Entry Site
Intranasal therapy is an attractive strategy for influenza because the nose and nasopharynx are the primary sites of viral entry and early replication.(2) The concept is biologically sound as it reduces the viral burden in the upper airways. This is clinically beneficial in symptomatic patients (early) as well as in contacts of patients with influenzae. The nasal spray/irrigation should be administered 2-3 times per day. This should be coupled with an anti-septic mouth wash. Patients should have a supply of a nasal spray in their home medicine kit so it is immediately available when required.
Several approaches have been studied, including:(2)
Saline Nasal Irrigation.
Iota-Carrageenan Nasal Spray (3)
Xylitol Nasal Spray
Povidone-Iodine Nasal Sprays
Neutral electrolyzed water and Nitric Oxide (NO) Sprays are similarly likely to be clinically beneficial.
Chlorine dioxide is a powerful broad-spectrum biocidal agent capable of inactivating many bacteria, viruses, fungi, and other microorganisms. Because of its potent antimicrobial activity, a chlorine dioxide nasal formulation might theoretically provide rapid local activity against susceptible pathogens. However, its effectiveness and safety as a nasal spray require appropriate clinical validation.
Clinical insight:
This is one of the simplest and most underutilized interventions—and often one of the most effective early. THIS IS IMPORTANT. Spray the whole family (and contacts). Always have a virucidal nasal spray in your medicine cabinet.
Antiseptic antimicrobial mouthwash
Antiseptic-antimicrobial mouthwashes that include chlorhexidine, povidone-iodine, or cetylpyridinium chloride (e.g., Scope™, Act™, Crest™) or the combination of eucalyptus, menthol, and thymol (Listerine™) have been shown to inhibit the replication of many upper respiratory tract viral pathogens and to reduce viral load. Use of an antimicrobial mouthwash complements that of the nasal spray.
2. Direct Antiviral Pressure
Rather than relying solely on neuraminidase inhibitors (which don’t work):
Nitazoxanide 600 mg twice daily (broad-spectrum antiviral, host-directed) (4,5)
Phytochemicals (e.g., elderberry; gummies, syrup, juice, etc.)(6-15)
These therapies target viral replication and maturation, often through mechanisms less prone to resistance.
Laboratory studies suggest that elderberry contains polyphenols (particularly anthocyanins) that may interfere with viral entry by binding to hemagglutinin and may also enhance cytokine-mediated immune responses.(6-15) Small clinical trials have reported reductions in symptom duration and severity when taken early in the course of illness. Elderberry should be viewed as a supportive adjunct rather than a primary treatment; it does not replace antiviral therapy in high-risk or severe cases of influenza.
3. Control the Host Response
Much of influenza severity is driven by immune dysregulation, not viral burden alone.
Key interventions:
Vitamin C → Vitamin C has important anti-inflammatory, antioxidant, and immune-enhancing properties. The effects of Vitamin C on the course of upper respiratory tract infections have long been recognized. A dose of 500 -1000 mg two or three time daily is suggested.
Zinc → Zinc is essential for innate and adaptive immunity, with zinc deficiency being a major risk factor for influenza and RSV infection. Suggested dose: 20-50 mg/day. Commercial zinc supplements are commonly formulated as zinc oxide or salts with acetate, gluconate, and sulfate.
Melatonin → reduces inflammatory injury and improves immune coordination (5-20 mg at night).
Clinical insight:
Patients rarely deteriorate because of uncontrolled viral replication alone—they deteriorate because of an unbalanced host response.
Addendum:
It is important to recognize that oral vitamin C absorption is saturable. Vitamin C is absorbed from the intestine through specific transport proteins that become progressively saturated as the dose increases. Consequently, taking increasingly large single doses does not produce a proportional increase in systemic vitamin C exposure. Absorption is relatively efficient at lower doses but declines substantially as individual doses increase into the gram range. For this reason, if the goal is to maximize systemic exposure from oral vitamin C, dividing the daily dose is generally more rational than simply increasing the size of a single dose. Rather than taking several grams at once, doses of approximately 500–1,000 mg taken several times throughout the day may provide more sustained exposure while reducing the amount that remains unabsorbed in the gastrointestinal tract. For example, vitamin C might be taken every four to six hours rather than as one very large daily dose.
Vitamin D plays an important role in regulating antiviral immunity, making vitamin D sufficiency particularly important in individuals with severe deficiency (<10 ng/mL). Indeed, an individual-participant meta-analysis of randomized trials found that vitamin D supplementation in people with baseline 25(OH)D levels below 10 ng/mL was associated with an approximately 70% reduction in the odds of developing an acute respiratory tract infection. However, the broader clinical evidence is less consistent. While several randomized trials and meta-analyses suggest that regular vitamin D supplementation may modestly reduce the risk of influenza or other respiratory infections, the most recent large meta-analysis found no statistically significant reduction in acute respiratory infections overall (see Table below). Similarly, a 2025 pediatric review found no significant benefit in infection rates, hospitalization, recovery time, or mortality (see references below).
The evidence for using high-dose vitamin D to treat established influenza is considerably weaker. The most defensible conclusion is therefore that vitamin D should not be regarded as a proven antiviral treatment for influenza. Rather, maintaining adequate vitamin D status, and particularly correcting severe vitamin D deficiency, should be viewed as part of supporting normal host immune function and potentially reducing susceptibility to respiratory infections.
Quercetin is a naturally occurring flavonoid with antiviral, anti-inflammatory, antioxidant, and immunomodulatory properties that make it potentially useful as an adjunct in influenza. Laboratory studies demonstrate activity against several influenza A strains, including H1N1 and H3N2. Quercetin appears to interfere with hemagglutinin-mediated viral entry and membrane fusion and may also inhibit viral replication and other stages of the viral life cycle. Animal studies further suggest that it may reduce influenza-associated oxidative stress and inflammation while supporting host antioxidant defenses. Thus, quercetin is particularly interesting because it may simultaneously target the virus and the host inflammatory response. However, the impressive experimental evidence has not yet been confirmed by robust human clinical trials. There is currently insufficient evidence that quercetin reduces hospitalization, pneumonia, mortality, or other major outcomes in patients with influenza. Poor and variable oral bioavailability may also limit the translation of laboratory findings, although enhanced-bioavailability formulations may partly address this problem. Quercetin should therefore be regarded as a promising adjunct rather than a proven influenza treatment: its mechanistic and preclinical evidence is substantial, but well-designed clinical trials are still needed to establish clinical benefit.
Martineau AR, Jolliffe DA, Hooper RL, et al. Vitamin D supplementation to prevent acute respiratory tract infections: systematic review and meta-analysis of individual participant data. BMJ. 2017;356:i6583
Jolliffe DA, Camargo CA Jr, Sluyter JD, et al. Vitamin D supplementation to prevent acute respiratory infections: systematic review and meta-analysis of stratified aggregate data. Lancet Diabetes Endocrinol. 2025, 13:307-320.
The role of vitamin D in the prevention and treatment of acute respiratory infections in pediatric populations: a systematic review and meta-analysis of randomized controlled trials. BMC Pediatr. 2025;25:985.
Results of the Jolliffe et al study.
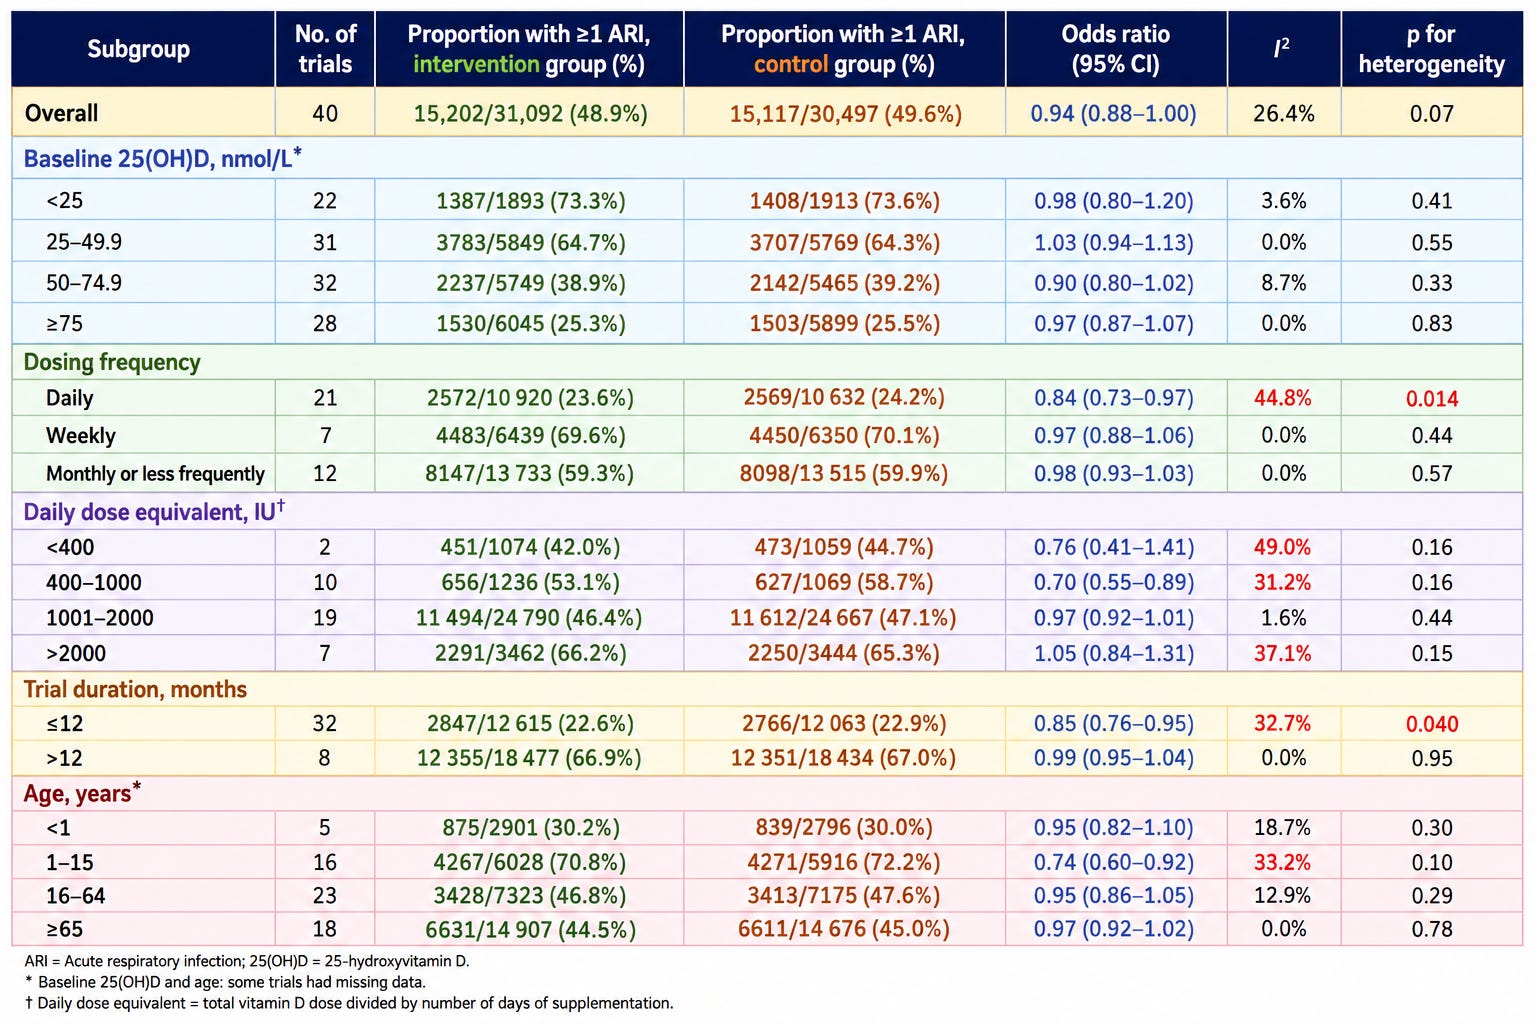
The central limitation of these clinical trials is the low dose of vitamin D they used—possibly by design. For adults, a dose of at least 5,000 IU daily would have been more appropriate. Whether a higher dose would have altered the trials’ outcomes remains unknown. Still, the absence of any signal even among participants in the lowest quartile of vitamin D concentrations is notable.
4. Reduce Oxidative and Mitochondrial Injury
Influenza is, in many ways, a disease of oxidative stress and mitochondrial dysfunction.
Targeted therapies:
N-acetylcysteine (NAC) → restores glutathione
Vitamin C → antioxidant synergy
Photobiomodulation / sunlight → mitochondrial activation
This axis is often overlooked, yet it may play an important role in preventing disease progression. During the 1918 influenza pandemic, open-air treatment, including exposure to fresh air and sunlight, was reported to be associated with substantially lower mortality.
Repurposed Drugs: Where Do They Fit?
A few repurposed agents have been proposed:
Minocycline → anti-inflammatory, possible antiviral effects
Ivermectin → broad in vitro antiviral activity
However, it is important to be precise:
Evidence in influenza remains limited or indirect
These agents should be viewed as adjuncts, not foundational therapies
Ivermectin’s antiviral effects appear to stem from a host-directed mechanism, not a direct virucidal action:
It inhibits the importin α/β nuclear transport system
Many RNA viruses (including influenza) rely on this pathway to shuttle viral proteins into the nucleus
In influenza, viral ribonucleoproteins must enter the nucleus for replication
Blocking this pathway can reduce viral replication in vitro
This mechanism has been demonstrated across multiple RNA viruses (e.g., dengue, Zika, SARS-CoV-2), suggesting a broad but weak antiviral effect
What About Tamiflu? (see below)
Oseltamivir (Tamiflu) remains widely prescribed for influenza, but its clinical benefits appear considerably more modest—and more dependent on the stage of illness—than its widespread use might suggest.
Shortens uncomplicated influenza by approximately one day. Clinical trials generally demonstrate a reduction in symptom duration of about 17–25 hours. This may be related to the drugs antipyretic properties rather than its antiviral effects.
Evidence for preventing serious complications has been controversial. Some analyses report reductions in lower-respiratory complications and hospitalization, while other reviews have questioned the strength and clinical significance of these findings. A reanalysis of the complete investigational data set (see “The Tamiflu Fraud”) showed no significant reduction in the risk of pneumonia, bronchitis, otitis media, sinusitis, serious complications overall, or hospitalization.
The new REMAP-CAP randomized trial raises a major concern in seriously ill patients.(1) In the REMAP-CAP study patients receiving either 5 or 10 days of oseltamivir had higher 90-day mortality than those receiving no antiviral thersapy, with approximately a 98% probability of harm. This finding applies specifically to seriously ill patients requiring organ support and requires further confirmation.
Oseltamivir can cause adverse effects, most commonly nausea and vomiting; other adverse effects have also been reported.
Clinical Takeaway
Oseltamivir has genuine antiviral activity, but antiviral activity should not be confused with meaningful clinical benefit. In uncomplicated influenza, the demonstrated benefit is modest—approximately one day less of symptoms. In critically ill patients, the new REMAP-CAP randomized trial found no survival benefit and instead identified a concerning signal of increased mortality. These findings challenge the routine use of oseltamivir in influenza and deserve urgent independent scrutiny and guideline reassessment.
Putting It All Together: A Practical Framework
A rational, clinically grounded approach to influenza might look like this:
Early Phase (Day 1–3)
Nasal spray + mouthwash
Vitamin C + zinc
NAC
Elderberry
Confirmed or Moderate Disease
Add nitazoxanide (if available)
Continue immune and antioxidant support
Supportive Layer
Melatonin at night
Sunlight or light therapy
Symptomatic medications
Selective Adjuncts
Minocycline or ivermectin (context-specific, not routine)
Broad Spectrum antibiotics
Should only be prescribed in patients with proven complicating bacterial infection (and not prophylactically)
What This Means Clinically
This approach reflects a deeper shift in medicine:
We are moving from “one drug, one target”
to “multi-system modulation.”
And influenza is a perfect example of why this matters.
Because in reality:
The virus is only part of the story
The host response determines the trajectory
And outcomes depend on how many biological systems we support—simultaneously
Final Thought
For decades, we’ve underestimated influenza.
Not because it is rare.
Not because it is benign.
But because we have been treating it too narrowly.
The future of influenza treatment—and infectious disease more broadly—will not be defined by a single breakthrough drug.
It will be defined by integrated, multi-axis strategies that recognize a simple truth:
Disease is rarely one-dimensional.
And treatment shouldn’t be either.
Clinical Takeaways
Influenza severity is driven as much by host response as viral replication
Early reduction of nasopharyngeal viral load is simple and underutilized
Nitazoxanide is one of the most promising broad-spectrum antivirals
Vitamin C, zinc, NAC, and melatonin target key biological pathways
Tamiflu (Oseltamivir phosphate) has minimal/no benefit and should be avoided: ineffective drug with non-trivial toxicity (see below)
Multi-agent, multi-axis strategies are biologically rational—even if difficult to study in large RCTs.
Figure 2. The multi-axis approach to the treatment of Influenzae
The Influenza Vaccine: Imperfect Protection
Each winter, the same quiet question returns to clinic rooms across the country:
“Does the flu shot actually work?”
It is a fair question—and an important one. Unlike many vaccines that provide durable protection, the influenza vaccine lives in a far messier biological reality. The virus evolves rapidly, immunity wanes, and the match between vaccine and circulating strains is never perfect.
The past five influenza seasons in the United States illustrate both the strengths and limitations of this vaccine (CDC data ?? trustworthy).
The 2020–2021 season was essentially an anomaly—public health measures during COVID-19 suppressed influenza circulation so dramatically that meaningful vaccine effectiveness could not even be measured.
Since then, the pattern has been more familiar:
2021–2022: ~36% effectiveness
2022–2023: ~30% effectiveness
2023–2024: ~44% effectiveness
2024–2025 (preliminary): ~56% effectiveness
Mortality: We are told that vaccinated people with influenza have a substantially lower risk of death than unvaccinated people; most large cohort and meta-analytic data show roughly a 20–30% relative reduction in all-cause mortality,
How to translate 20–30% relative reduction
If baseline all‑cause mortality is 0.1%, a 20–30% relative reduction yields vaccinated mortality of 0.08–0.07%, for an absolute risk reduction of 0.02–0.03 percentage points.
The vaccine is not immune from serious side effects which must be weighed against the minute benefit of the vaccine:
Anaphylaxis
Guillain-Barré syndrome (GBS)
Febrile seizures in children
Is the Vaccine Effective?
It is likely that the vaccine is ineffective or more troubling it may be negatively effective (increases risk of influenza).

Conclusion of study: Conclusions: Systematic influenza vaccination in children aged 6 to 59 months has not been shown to be associated with a reduction in influenza cases in primary care or hospitals settings during the early stages of implementation of the new vaccination program.

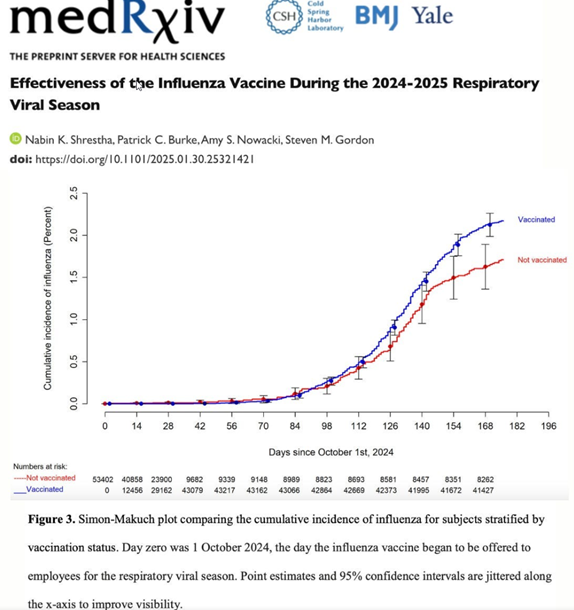
A study completed at the Cleveland Clinic found that flu shots were associated with a 27% higher risk of flu among healthcare workers during the 2024–2025 season (see below).


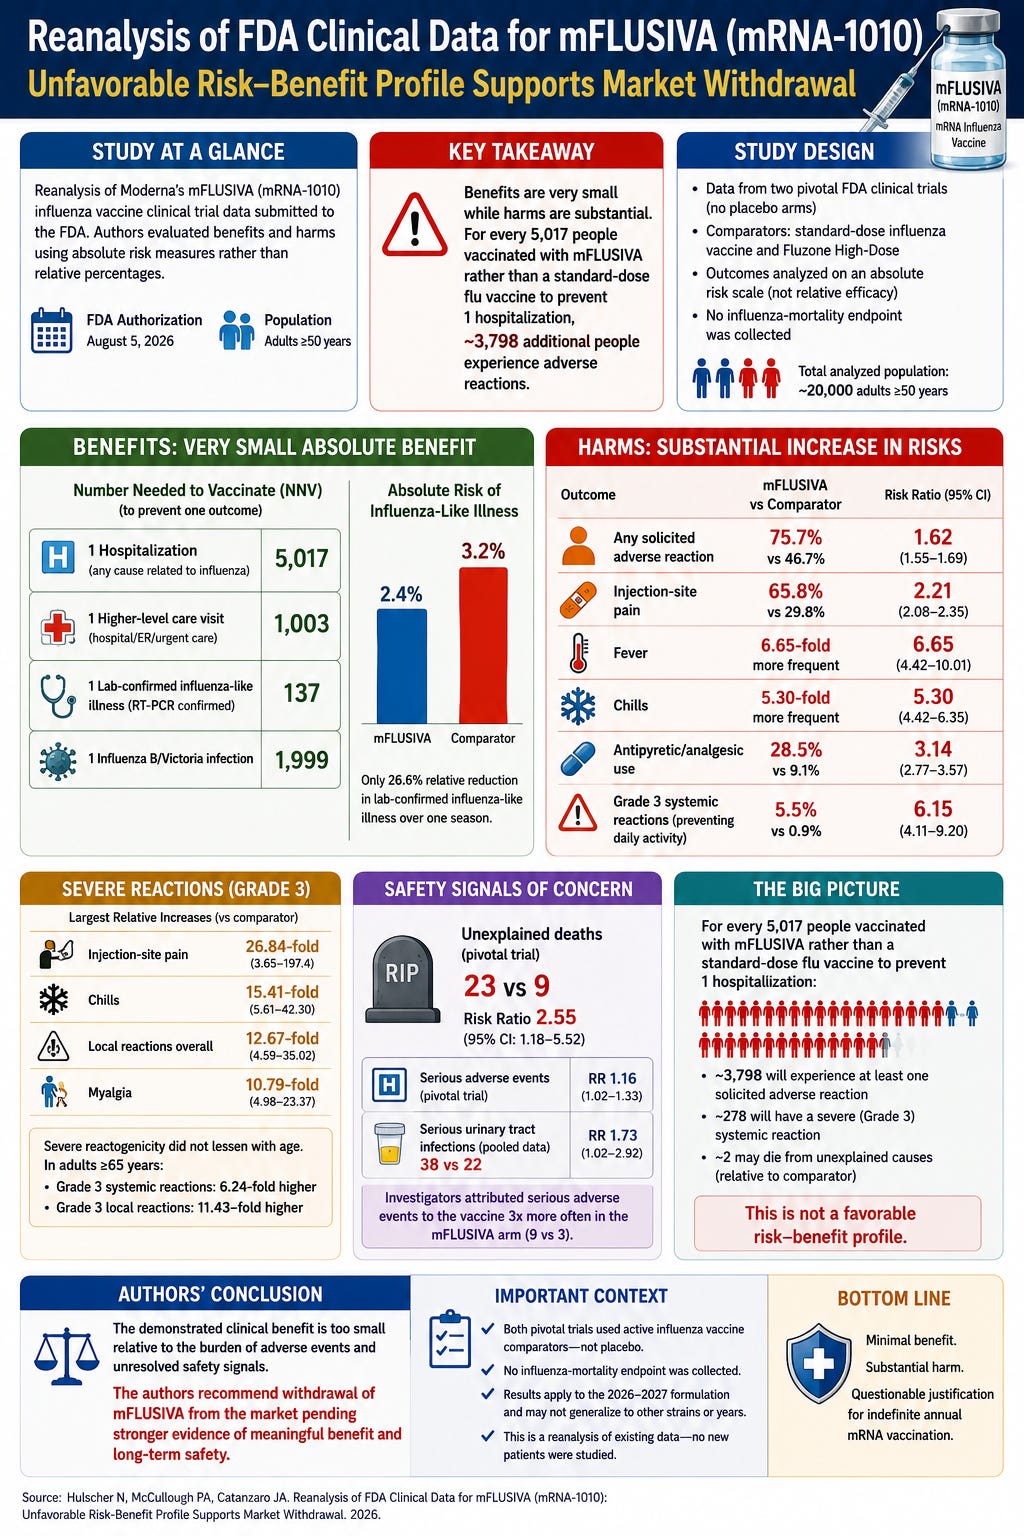
This paper reanalyzes the FDA clinical-trial data for Moderna’s mFLUSIVA (mRNA-1010) influenza vaccine, focusing on absolute benefit versus harm rather than relative efficacy alone. The authors report that, compared with a standard-dose flu vaccine, about 137 people would need to receive mFLUSIVA to prevent one laboratory-confirmed influenza illness, about 1,003 to prevent one higher-level-care visit, and about 5,017 to prevent one hospitalization. They also note that the apparent benefit was smaller in older and higher-risk participants.
The major concern raised by the authors is the frequency of adverse reactions. In the pivotal trial, 75.7% of mFLUSIVA recipients experienced a solicited adverse reaction compared with 46.7% receiving the standard flu vaccine, while serious Grade 3 systemic reactions that interfered with normal daily activity were also substantially more frequent. Using the authors’ calculations, for every hospitalization prevented, there were approximately 1,454 additional adverse reactions and 233 additional severe systemic reactions compared with the standard-dose vaccine.
The paper also highlights a potentially important but unresolved mortality signal. Deaths recorded as being of unspecified cause occurred in 23 mFLUSIVA recipients compared with 9 comparator recipients. The authors appropriately acknowledge that this does not prove the vaccine caused these deaths, but argue that the imbalance deserved much more investigation. They emphasize that influenza mortality itself was never a prespecified clinical endpoint, meaning the trials could not determine whether mFLUSIVA actually reduced deaths from influenza.
Overall, the authors conclude that the demonstrated clinical benefit is too small relative to the adverse-event burden and unresolved safety questions, and they argue that mFLUSIVA should be withdrawn until stronger evidence of meaningful clinical benefit and long-term safety is available. It is important to recognize that this is the authors’ reanalysis and interpretation of existing FDA and trial data, not a new randomized clinical trial; no new patients were studied and no individual patient-level data were available to them.

Tamiflu (oseltamivir) has become a paradigmatic example of how selective data disclosure, industry control of the evidence base, and regulatory inertia can combine to distort both clinical practice and national pandemic policy.
From pandemic scare to global stockpiles
The story begins with the early‑2000s H5N1 avian influenza scare. In anticipation of a catastrophic pandemic, governments across Europe, the United Kingdom, the United States, and elsewhere began stockpiling neuraminidase inhibitors, particularly oseltamivir (Tamiflu) and, to a lesser extent, zanamivir (Relenza). On paper, these agents were framed as key tools to reduce influenza complications and protect health‑care systems under stress. In practice, countries accumulated enough Tamiflu to treat roughly a quarter of their populations, and many European pandemic plans enshrined oseltamivir as a core response pillar. This level of investment and policy commitment rested on a deceptively thin and manufacturer‑controlled evidence base.
The 2003 pooled analysis and the missing trials
The central plank for Tamiflu’s elevation was a 2003 pooled analysis led by Laurent Kaiser, which reported that oseltamivir reduced lower respiratory tract complications and offered clinically meaningful benefit. That analysis drew on ten randomized controlled trials, yet only two had actually been published at the time. The bulk of the data—especially those underpinning claims of reduced serious complications—remained unpublished and inaccessible. When the British Medical Journal and Cochrane reviewers sought to verify the findings, the original authors reported they did not hold the data for the eight unpublished studies. The investigators then approached the manufacturer, Roche, only to be told that access to the full trial data would be conditional on signing a confidentiality agreement containing a secrecy clause. Accepting such terms would have compromised their ability to report findings transparently, so they refused. This refusal marked the beginning of a prolonged public campaign to obtain the data and exposed the extent to which Tamiflu’s purported benefits relied on evidence that had never undergone independent scrutiny.
Regulatory pressure, secrecy, and ghost‑managed science
After years of pressure, including investigative journalism and advocacy from independent researchers, a freedom of information request in 2011 forced the European Medicines Agency to release about 20,000 pages of incomplete oseltamivir data. Later that same year, Roche finally provided 77 full clinical study reports. The contents were revealing. None of the trials had been conducted independently of the manufacturer, and all compared oseltamivir to placebo rather than to standard symptomatic treatments such as acetaminophen. This trial design virtually guaranteed that any modest change in symptom duration could be presented as a meaningful therapeutic victory, while leaving vital comparative effectiveness questions unanswered. Further examination showed that many published articles were ghost‑written, with unclear authorship and opaque attribution of who actually performed the research. In several cases, it was impossible to reconstruct who designed, conducted, and analyzed the trials, reinforcing the impression of a literature carefully curated and managed by the sponsor rather than a transparent body of scientific work.
Reappraisal by Cochrane: benefits evaporate, harms emerge
Armed with the newly released clinical study reports, the Cochrane collaboration undertook a fresh review in 2014. When the full data were examined rather than selectively published fragments, the narrative around Tamiflu shifted dramatically. The updated analysis found no robust evidence that oseltamivir reduced lower respiratory tract complications or meaningfully impeded influenza transmission. There was no significant reduction in the risk of pneumonia, bronchitis, otitis media, sinusitis, serious complications overall, or hospitalization. At the same time, the reviewers identified a clearer and more concerning adverse‑effect profile: in adults, oseltamivir use was associated with increased risks of nausea, vomiting, psychiatric symptoms, and renal events, while in children it was linked to more frequent vomiting. In other words, once the entire evidence base was visible, Tamiflu no longer looked like a drug that averted serious outcomes; it looked like a symptomatic agent with modest effects and non‑trivial toxicity.
Mortality, mechanism, and the antipyretic hypothesis
Additional analyses during the 2009 A/H1N1 influenza pandemic reinforced these doubts. When outcomes such as death were examined, oseltamivir showed no protective effect on mortality among patients with 2009A/H1N1 influenza. This finding undercut one of the main justifications for large‑scale stockpiling: the assumption that Tamiflu would save lives in a severe pandemic. Emerging interpretations suggested that oseltamivir might function more as an antipyretic—dampening fever and improving how patients feel—than as a potent antiviral that significantly suppresses viral replication or prevents complications. If symptom suppression is the primary effect, a perverse consequence is that infected individuals may feel well enough to work, attend school, or travel, all while still shedding virus and transmitting infection. Rather than halting an epidemic, widespread use under these circumstances could plausibly facilitate spread by masking symptoms without addressing underlying infectivity.
Policy inertia and the pharma–government nexus
Perhaps the most striking element of the Tamiflu saga is not just the initial distortion of evidence but the persistence of policy after the distortion was exposed. Despite the Cochrane reappraisal, the revelations of ghost‑writing and withheld data, and the demonstration of limited benefit alongside added harms, national pandemic plans in the UK, US, and other countries have not meaningfully changed. Stockpiles continue to be replenished, and Tamiflu remains entrenched in influenza preparedness strategies much as it was more than a decade ago. This disconnect between the updated evidence base and policy practice illustrates a deeper structural problem: once governments and regulatory agencies have fully embraced a pharmaceutical narrative—backed by substantial financial investments and public commitments—there is strong resistance to revising course, even when independent analysis undermines the foundational claims. The Tamiflu case thus stands as a vivid example of how industry influence, selective data disclosure, and regulatory alignment can produce a durable “fraud by omission,” in which a drug is elevated to essential status on incomplete or biased evidence, and subsequent corrective information struggles to dislodge entrenched policies.
It gets Worse:
A Recent study demonstrates that Tamiflu increases mortality is patients with severe respiratory infection
Summary: Oseltamivir for Critically Ill Patients with Influenza: A Randomised Trial (1)
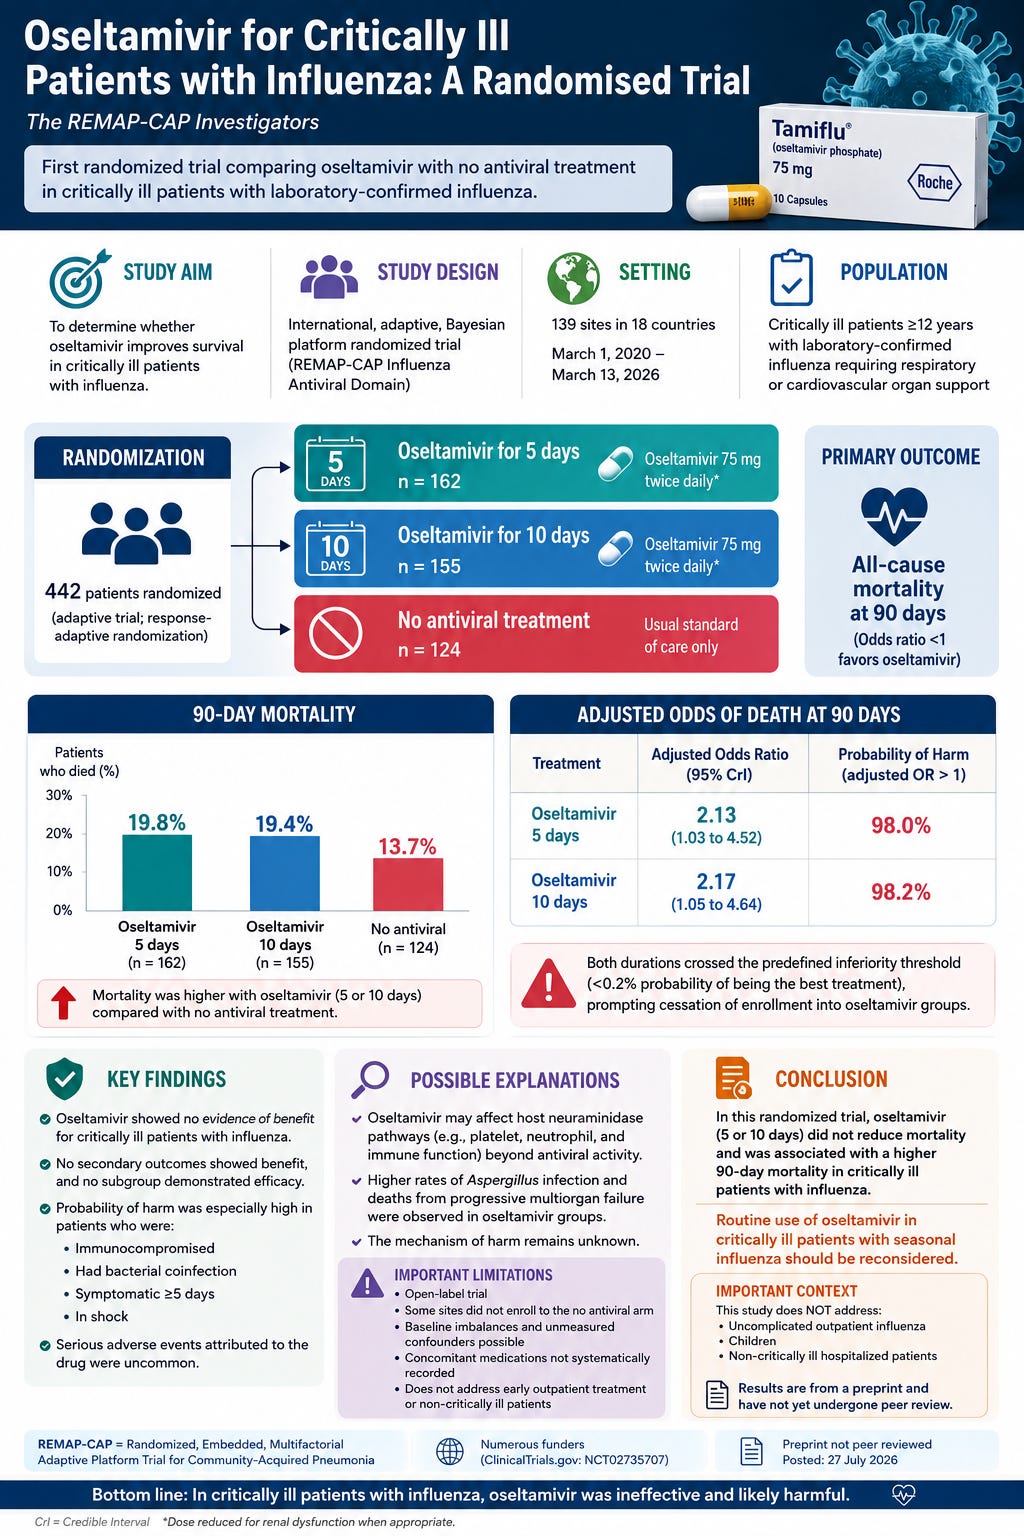
Oseltamivir (Tamiflu) has been widely used for decades in hospitalized and critically ill patients with influenza and is recommended in international guidelines. However, much of the evidence supporting its use in severely ill patients has come from observational studies rather than randomized controlled trials. The REMAP-CAP investigators therefore conducted an international randomized trial to determine whether oseltamivir actually improves survival in critically ill patients with laboratory-confirmed influenza. The study is particularly important because, according to the authors, this was the first randomized trial comparing oseltamivir with no antiviral treatment in this critically ill population.
The trial enrolled 442 critically ill patients aged 12 years or older at 139 sites in 18 countries. Patients required respiratory or cardiovascular organ support and were randomized to oseltamivir for 5 days, oseltamivir for 10 days, or no antiviral treatment. The recommended oseltamivir dose was 75 mg twice daily, adjusted when necessary for renal dysfunction. The primary outcome was death from any cause at 90 days, a clinically meaningful endpoint in critically ill patients.
The results were striking. By 90 days, 17 of 124 patients (13.7%) receiving no antiviral had died, compared with 32 of 162 (19.8%) receiving 5 days of oseltamivir and 30 of 155 (19.4%) receiving 10 days. After statistical adjustment, the odds of death were approximately twice as high with oseltamivir: OR 2.13 for the 5-day course and OR 2.17 for the 10-day course. Using the trial’s Bayesian analysis, there was a 98.0% probability of harm with 5 days of treatment and a 98.2% probability of harm with 10 days. The predefined inferiority threshold was reached, prompting the independent safety board to recommend stopping enrollment into the oseltamivir groups.
Importantly, the findings were not confined to the primary analysis. Sensitivity analyses produced results consistent with the main findings, and none of the secondary outcomes showed evidence that oseltamivir was beneficial. Likewise, none of the prespecified subgroups demonstrated a signal of efficacy. The probability of harm appeared particularly high among patients who were immunocompromised, had bacterial coinfection, had been symptomatic for five days or longer, or were already in shock. Interestingly, serious adverse events formally attributed to the drug were uncommon, suggesting that the mortality signal was not simply explained by conventional recognized drug toxicity.
The authors discuss several possible explanations for the unexpected mortality signal. Oseltamivir may affect not only viral neuraminidase but also host neuraminidase pathways, potentially altering platelet biology, neutrophil function, and immune responses to secondary infections. Patients receiving oseltamivir had more Aspergillus infection and a higher proportion of deaths attributed to progressive multiorgan failure, although these observations do not establish the mechanism of harm. The study also has important limitations: it was open-label, some sites would not randomize patients to no antiviral treatment, there were modest baseline imbalances, concomitant medications were not systematically recorded, and the effect of oseltamivir given earlier—before patients became critically ill—remains unknown.
The bottom line is provocative: in this randomized trial, oseltamivir provided no evidence of benefit in critically ill patients with seasonal influenza and was associated with a substantial signal toward increased 90-day mortality. The authors conclude that routine oseltamivir treatment in this specific population should be reconsidered and that guidelines should incorporate these randomized findings.
References
1. Oseltamivir for Critically Ill Patients with Influenza: A Randomised Trial. Lancet Preprint. 2026.
2. Stathis C, Victoria N, Loomis K, Nguyen SA, Eggers M, Septimus E, et al. Review of the use of nasal and oral antiseptics during a global pandemic. Future Microbiol. 2021;16(2):119–30.
3. Hemilä H, Chalker E. Carrageenan nasal spray may double the rate of recovery from coronavirus and influenza virus infections: Re-analysis of randomized trial data. Pharmacol Res Perspect. 2021;9(4):e00810.
4. Rossignol JF, La Frazia S, Chiappa L, Ciucci A, Santoro MG. Thiazolides, a new class of anti-influenza molecules targeting viral hemagglutinin at the post-translational level. The Journal of Biological Chemistry. 2009;284:29798–808.
5. Haffizulla J, Hartman A, Hoppers M, Resnick H, Samudrala S. Effect of nitazoxanide in adults and adolescents with acute uncomplicated influenza: a double-blind, randomised, placebo-controlled, phase 2b/3 trial. Lancet Infect. Dis. 2014;14:609–18.
6. Zakay-Rones Z, Varsano N, Zlotnik M. Inhibition of several strains on influenza virus in vitro and reduction of symptoms by an an elderberry extract (Sambucus nigra L) during an outbreak of infleunza B Panama. The Journal of Alternative and Complementary Medicine. 1995;1:361–9.
7. Zakay-Rones Z, Thom E, Wollan T, Wadstein J. Randomized study of the efficacy and safety of oral elderberry extract in the treatment of Influenza A and B virus infections. The Journal of International Medical Research. 2004;32:132–40.
8. Wieland LS, Piechotta V, Feinberg T, Ludeman E, Hutton B, Kanji S, et al. Elderberry for prevention and treatment of viral respiratory illnesses: a systematic review. BMC Complementary Medicine and Therapies. 2021;21:112.
9. Torabian G, Valtchev P, Adil Q, Dehghani F. Anti-influenza activity of elderberry (Sambucus nigra). Journal of Functional Foods. 2019;54:353–60.
10. Swaminathan K, Dyason JC, Maggioni A, von Itzstein M, Downard KM. Binding of a natural anthocyanin inhibitor to influenza neuraminidase by mass spectrometry. Analytical and Bioanalytical Chemistry. 2013;405:6563–72.
11. Roschek B, Fink RC, McMichael MD, Li D, Alberte RS. Elderberry flavonoids bind to and prevent H1N1 infection in vitro. Phytochemistry. 2009;70:1255–61.
12. Mocanu ML, Amariei S. Elderberries - A source of bioactive compounds with antiviral action. Plants. 2022;11:740.
13. Macknin M, Wolski K, Negrey J, Mace S. Elderberry extract outpatient influenza treatment for emergency room patients ages 5 and above: a randomized, double-blind, placebo-controlled trial. J. Gen. Intern. Med. 2020;35:3271–7.
14. Kinoshita E, Hayashi K, Katayama H, Hayashi T, Obata A. Anti-influenza virus effects of elderberry juice and its functions. Biosci. Biotechnol. Biochem. 2012;76:120112.
15. Hawkins J, Baker C, Cherry L, Dunne E. Black elderberry (Sambucus nigra) supplementation effectively treats respiratory symptoms: a meta-analysis of randomized, controlled clinical trials. Complementary Therapies in Medicine. 2019;42:361–5.
In 2001, I was prescribed oseltamivir within 12 hours of my initial symptoms. I ended up in the ER several weeks later. It didn’t do anything for me. I had never gotten a flu shot before but started the next year (A doctor lived next door so he would just come over).
I stopped the flue shots when I got the flu again despite the shots. I am now an anti-vaxxer.
This post is so helpful,,,Thank you very much Dr. Marik