

If you’ve found this work valuable, please consider upgrading to a paid subscription. Your support helps me continue independent research and share practical, evolving insights—while giving you access to deeper content and more direct engagement.

If depression is not a single chemical imbalance…
Then it cannot be treated with a single intervention.
It must be approached as what it truly is:
A disorder of interconnected biological systems.
A more effective framework begins with a simple shift in thinking:
Not “Which drug treats depression?”
But:
“Which systems are out of balance—and how do we restore them?”
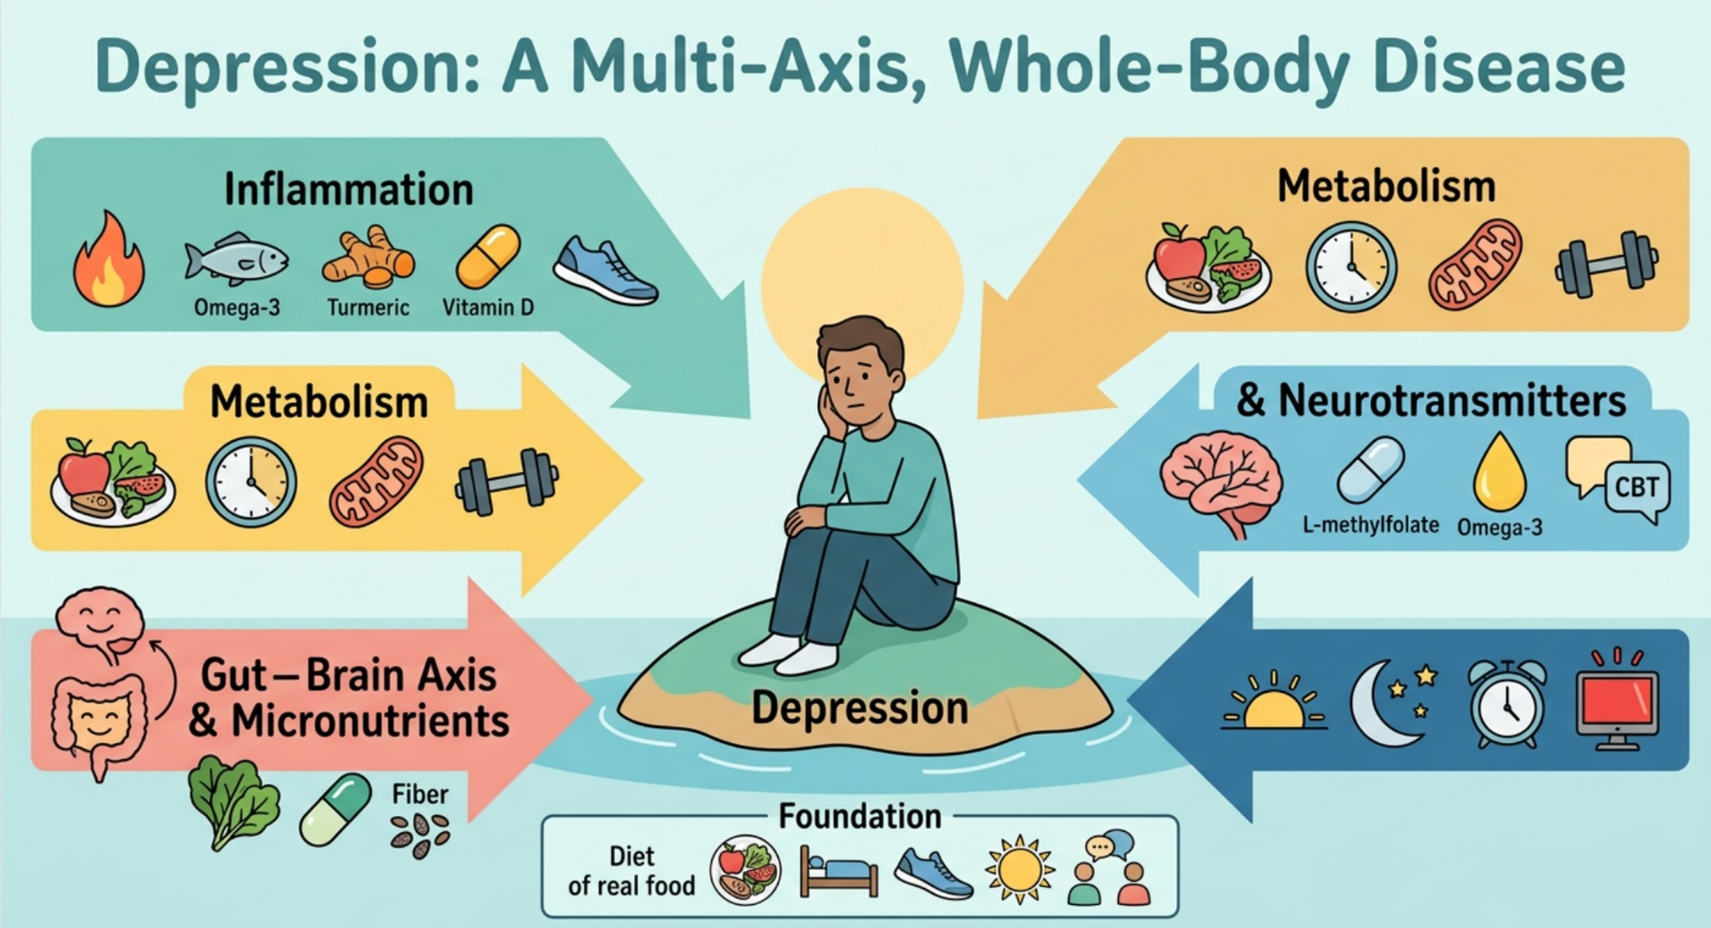
The Five Axes of Depression
Depression can be understood across five key biological domains:
Inflammation
Metabolism
Neurotransmission & neuroplasticity
Circadian rhythm
Gut–brain axis & micronutrients
Each contributes to the illness.
Each must be addressed.
1. Inflammation: Quiet Fire in the Brain
Many patients with depression have elevated inflammatory markers.
Inflammation alters neurotransmission, impairs neuroplasticity, and disrupts mood regulation.
Key interventions:
Omega-3 fatty acids (EPA-dominant)
Curcumin
Vitamin D
Exercise
These are not “alternative therapies.”
They are biological treatments targeting upstream disease mechanisms.
2. Metabolism: Fueling the Brain
The brain is an energy-intensive organ.
When metabolic function is impaired, mood suffers.
Depression is strongly linked to:
Insulin resistance
Obesity
Mitochondrial dysfunction
Key interventions:
Low-insulinemic / whole-food diet
Intermittent fasting
Weight optimization
Physical activity
Magnesium supplementation (magnesium Threonate)
Restoring metabolic health often leads to meaningful improvements in mood.
3. Neuroplasticity: Rewiring the Brain
The problem in depression is not simply low serotonin.
It is impaired brain adaptability.
Reduced neuroplasticity means the brain becomes “stuck.”
Key interventions:
L-methylfolate
Omega-3 fatty acids
Zinc and magnesium
Psychotherapy (especially CBT)
Medications may help—but they are only one piece of a larger puzzle.
4. Circadian Rhythm: Resetting Time
Sleep disturbance is not a symptom of depression.
It is often a driver.
Modern life has profoundly disrupted our biological clock.
Key interventions:
Consistent sleep–wake timing
Morning light exposure
Evening light restriction (red lights)
Melatonin (carefully titrated)
For some patients, restoring circadian rhythm produces rapid improvement.
5. The Gut–Brain Axis: Feeding the System
The brain depends on the gut for:
Nutrient supply
Immune regulation
Neurotransmitter precursors
Dysbiosis and micronutrient deficiencies can perpetuate depression.
Key interventions:
Nutrient-dense diet - Real food diet
L-methylfolate
Magnesium and zinc
Fiber, pre/probiotics, glucomannan, chia seeds
Gut-directed therapies (when indicated)
A Practical Treatment Hierarchy
Rather than a drug-first model, consider a layered approach:
Foundation (for all patients)
Diet
Sleep
Exercise
Sunlight
Social connection and social support
Biological support
Vitamin D
Omega-3
Magnesium
L-methylfolate
Targeted adjuncts
Curcumin
Ashwagandha
Zinc
Melatonin
Lithium orotate
Saffron
The treatment of Gut Dysbiosis
Fiber, pre/probiotics, glucomannan, chia seeds
Pharmacologic therapy (selective use)
SSRIs/SNRIs
Used thoughtfully, not reflexively
Avoid polypharmacy
Used sort-term then weaned off
See chapter on failure of SSRI
Why This Matters
This model explains what clinicians see every day:
Why many patients do not respond to a single drug
Why relapse is common
Why depression looks different in different people
And it explains something else:
Why some patients improve dramatically when multiple systems are addressed simultaneously.
The Bigger Picture
Depression is not a failure of will.
It is not a simple chemical imbalance.
It is a biological signal—that something, somewhere in the system, is out of balance.
When we begin to treat the system…
We begin to see different outcomes.
The future of depression treatment will not come from a single breakthrough drug.
It will come from a better understanding of the organism as a whole.
The future of depression care will not be defined by a new drug.
It will be defined by a better model of the disease—one that recognizes the complexity of the human organism.
And once that shift occurs, something remarkable happens:
Patients who once seemed refractory begin to recover.
Not because we found a better pill—
But because we finally understood the problem.
Figure 1. Treating Depression as a whole-body disease
Summary of Suggested Interventions
1. Vitamin D3 (dosage adjusted based on vitamin D3 blood levels, but 10,000 IU/day is recommended; take with Vitamin K2 100 mcg/day and Magnesium 200-500 mg/day if taking more than 8,000 IU/day of Vitamin D3)
2. L-Methylfolate (7.5-15 mg/day)
3. Lithium Orotate 5-15 mg/day
4. Ashwagandha (300-600 mg/twice daily)
5. Omega-3 fatty acids (1,000 mg/day)
6. Magnesium Threonate/orotate (100-200 mg/day starting dose)
7. Zinc (20-30 mg/day)
8. Melatonin (1 mg/night to start, up to 5-10 mg/night)
9. Curcumin (500-1,000 mg/day)
10. St. John’s wort (600-1,800 mg/day)
11. Saffron (50 mg/twice day)
12. Low insulinemic diet- whole food-Mediterranean diet
13. Treatment of gut dysbiosis (e.g., pre/probiotics, glucomannan, chia seeds)
14. Cognitive behavioral therapy and social support
15. Exercise (20 minutes/day, 5 days/week)
16. Sunshine (30 minutes/day)
17. Photobiomodulation
The Drug That Works in Hours (When Nothing Else Does)
He had tried everything.
Four antidepressants.
Two psychiatrists.
Months of therapy.
Nothing worked.
Sleep was broken.
Energy was gone.
Hope had quietly disappeared.
He wasn’t dramatic about it.
He just said:
“I feel… stuck.”
This is the reality of depression that most people never see.
Not sadness.
Not grief.
But immobility of the mind.
A kind of biological rigidity where thoughts loop, energy fades, and the future collapses into something small and unreachable.
Now consider this:
What if a single intervention could begin to reverse that state—not in weeks, but in hours?
That is what has made ketamine one of the most important—and controversial—developments in modern psychiatry.
A Different Kind of Antidepressant
Most antidepressants work—if they work at all—slowly.
Weeks pass.
Sometimes months.
Ketamine is different.
In many patients, it produces:
Noticeable improvement within hours
Reduction in suicidal thoughts within a day
A sense of mental “release” that patients often struggle to describe
This is not subtle.
And it challenges everything we thought we knew about depression.
What Patients Actually Experience
Patients rarely describe ketamine in biochemical terms.
They describe it like this:
“It’s like my thoughts loosened.”
“I could see things differently.”
“The weight lifted… just enough to breathe again.”
Some experience a brief, dream-like state.
Others feel emotionally distanced from their suffering for the first time in years.
And in that space—something important happens:
The brain becomes flexible again.
This Is Not About Serotonin
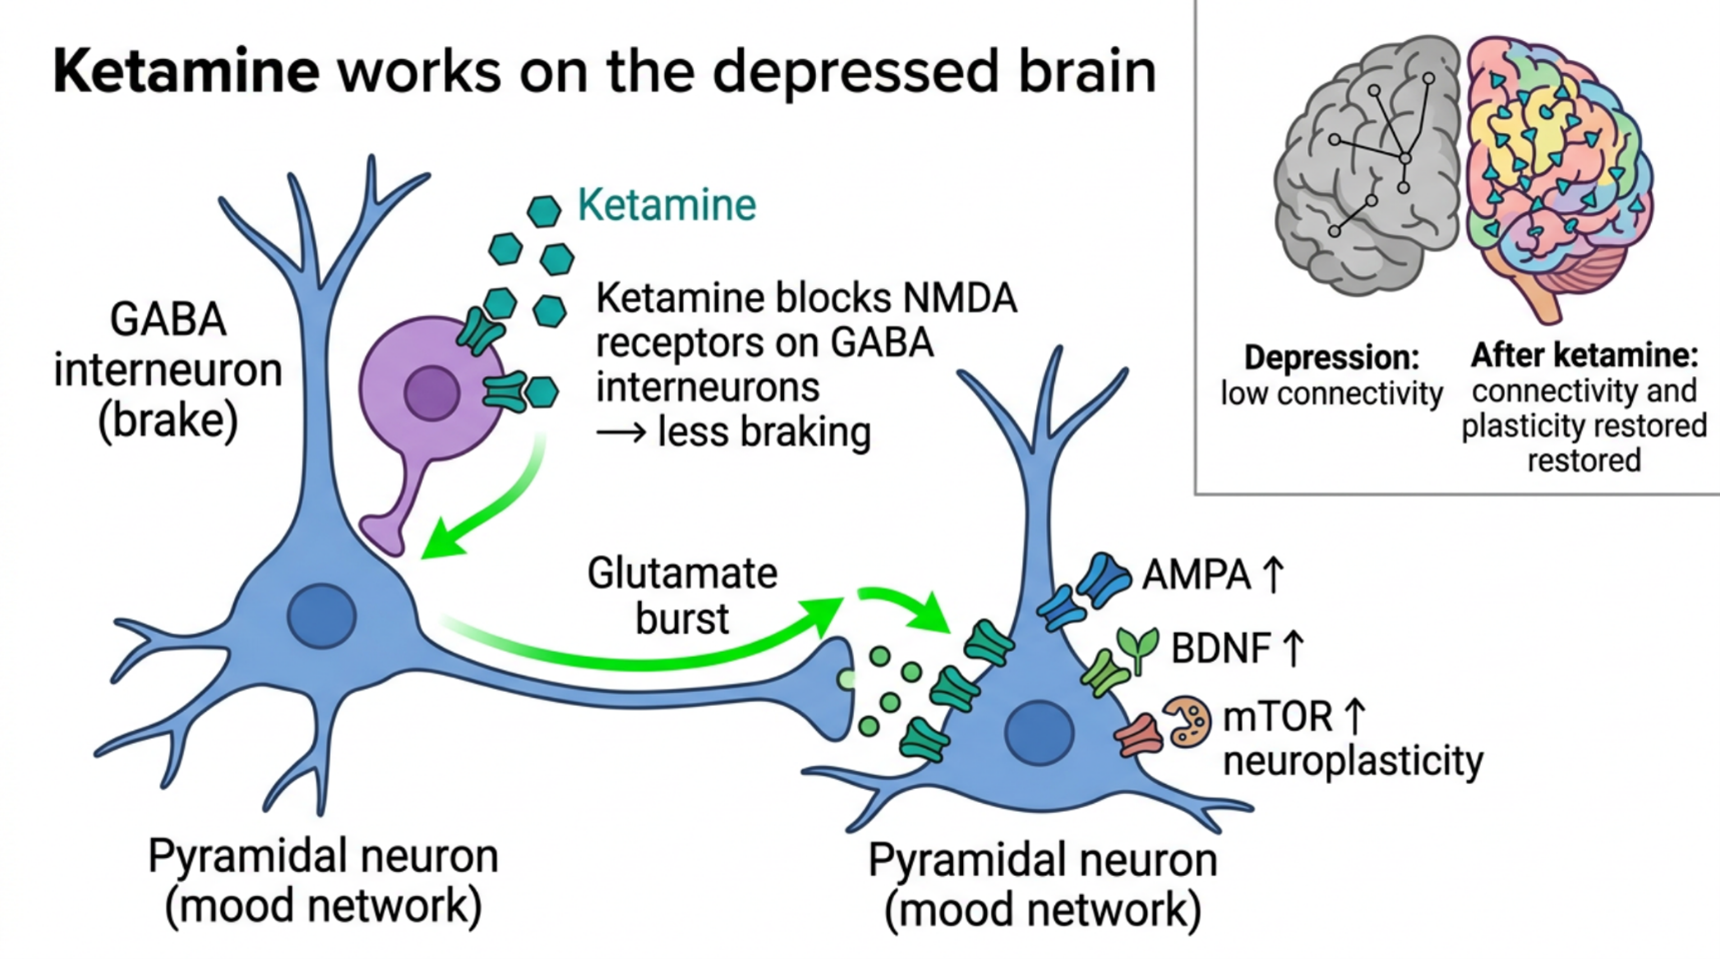
Ketamine does not work by increasing serotonin.
It works by doing something far more fundamental:
It restores neuroplasticity.
In depression, the brain becomes rigid:
Connections weaken
Circuits become fixed
Negative patterns reinforce themselves
Ketamine appears to reverse this—rapidly.
Not by forcing a signal…
But by reopening the system.
Why Sublingual Ketamine Matters
Most early studies used intravenous ketamine.
Effective—but impractical.
Then came intranasal esketamine—a step forward, but still limited by cost and access.
Sublingual ketamine changes the equation.
A small lozenge placed under the tongue/ or a small aliquot of liquid ketamine.
No IV.
No clinic infusion chair.
Just absorption through the oral mucosa.
Slower. Gentler. More accessible.
And for many patients—good enough.
What the Data Suggest
While less studied than IV ketamine, real-world data show:
~50–70% of patients respond
Many have failed multiple prior treatments
Some experience improvement after years of illness
But the most striking effect is this:
Suicidal thoughts can diminish within hours
There is no other widely available psychiatric treatment that does this reliably.
The Critical Insight
Ketamine does not “fix” depression.
It does something more subtle—and more powerful.
It creates a window.
A period of increased neuroplasticity where:
Thought patterns can shift
Therapy becomes more effective
Behavior can change more easily
Without that window, many patients remain stuck.
With it, change becomes possible.
But There Is a Catch
Ketamine is not a complete treatment.
If nothing else changes, the effect often fades.
This is where many clinicians—and patients—go wrong.
They see ketamine as the answer.
It isn’t.
It is an entry point.
The Right Way to Think About It
Depression is a whole-body disorder:
Inflammation
Metabolic dysfunction
Sleep disruption
Circadian misalignment
Nutrient deficiencies
Ketamine primarily targets one axis:
→ Neuroplasticity
That is why it can feel dramatic.
But it is also why it is not enough on its own.
When It Works Best
Ketamine is most effective when it is part of a broader strategy:
Sleep is stabilized
Diet is improved
Inflammation is reduced
Nutrients are optimized
Therapy is integrated
In this context:
Ketamine opens the door—and everything else helps the patient walk through it.
Who Should Consider It?
Sublingual ketamine may be appropriate for:
Treatment-resistant depression
Severe depression with suicidal ideation
Patients who feel cognitively “stuck”
It is less appropriate for:
Mild, situational depression
Patients with uncontrolled hypertension
Active psychosis
Figure 2. Ketamine and the depressed brain.
If you’ve found this work valuable, please consider upgrading to a paid subscription. Your support helps me continue independent research and share practical, evolving insights—while giving you access to deeper content and more direct engagement. Please I need your help.

In the last few years I have come to realize that everything in our body is tied together and it’s the total system that matters.
Just like in a car, if one or more parts in the engine, drivetrain or suspension are not working properly the cars not going anywhere and neither are you !!!
Thanks for helping us understand how we really work as a total body system.
I don’t know about others, but learning can be fun.
a person is not “just a body”
a person is a body-soul-spirit
the whole person needs to be observed
to find the root cause