

An Interruption to Our Usual Programming
Today’s post is a little different.
For more than thirty years, I practiced medicine within the American healthcare system. Like many physicians, I believed that despite its imperfections, it remained fundamentally committed to the well-being of patients. Only after stepping away from the system did I begin to appreciate how profoundly dysfunctional it had become.
What we now call “healthcare” has increasingly evolved into a financially driven sick-care system, where administrative metrics, reimbursement, and protocol compliance often take precedence over thoughtful, individualized patient care.
Today’s young physicians are being trained in an environment that increasingly rewards adherence to protocols, checklists, and electronic prompts rather than independent clinical reasoning. As a result, many become highly proficient at following algorithms but have fewer opportunities to develop the critical thinking, physiological understanding, and bedside judgment that distinguish truly exceptional clinicians.
At the same time, hospitals—while indispensable for many life-threatening conditions—have become places where patients face significant risks from preventable medical harm, hospital-acquired infections, medication errors, unnecessary procedures, and fragmented care. My advice is simple: do everything you reasonably can to stay healthy enough to avoid hospitalization whenever possible.
This essay explores how we arrived at this point, why thoughtful physicians are increasingly being replaced by protocol-driven “automatons,” and what must change if we are to restore medicine to its original purpose: caring for individual human beings rather than simply managing diseases and meeting performance metrics.
Medicine has always been both a science and an art. Scientific knowledge provides the foundation for diagnosis and treatment, but it is clinical judgment that transforms that knowledge into effective patient care. For more than a century, physicians were trained not simply to memorize facts or follow algorithms, but to observe carefully, think critically, challenge assumptions, and continually reassess their patients. Sir William Osler famously remarked that “Medicine is a science of uncertainty and an art of probability.” Every patient presents a unique biological problem, and no two illnesses unfold in exactly the same way.
Over the past several decades, however, medicine has undergone a profound cultural transformation. Increasingly, physicians are expected to practice according to standardized guidelines, protocols, checklists, quality metrics, and electronic decision-support systems. These tools were introduced with good intentions—to reduce unwarranted variation, improve safety, and ensure that evidence-based treatments are consistently applied. In many circumstances they have undoubtedly improved care. Standardization has reduced medication errors, improved surgical safety, and facilitated the rapid implementation of proven therapies.
The problem arises when protocols evolve from guides for clinical practice into substitutes for clinical thinking.
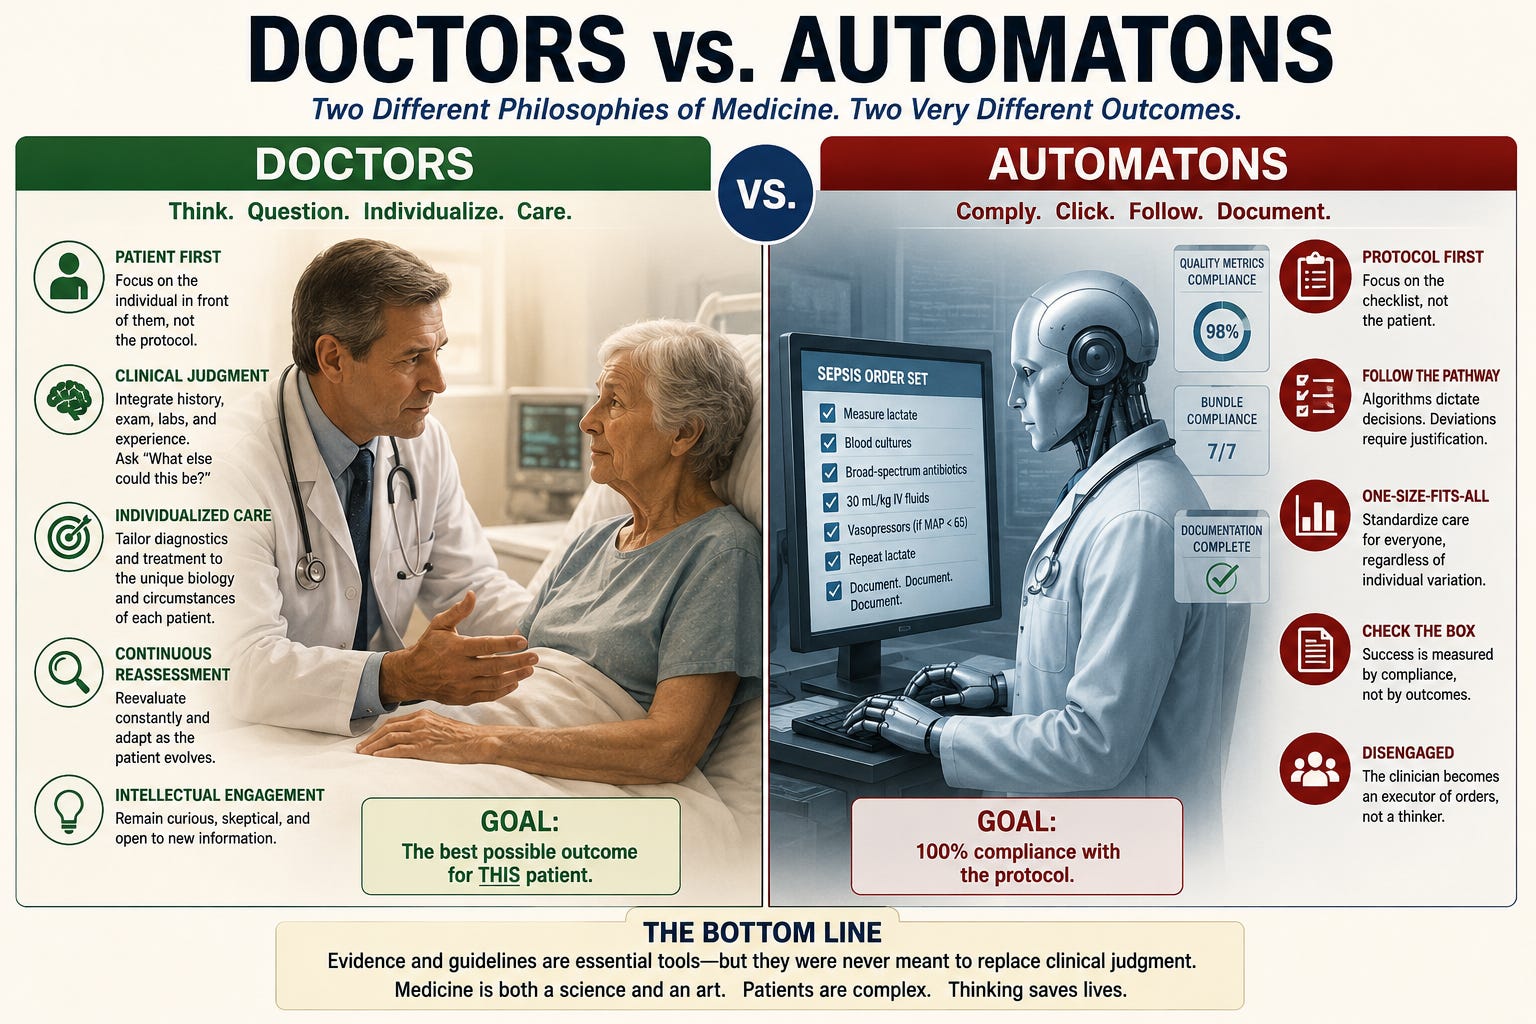
The left side of the graphic represents what many physicians believe medicine should strive to preserve. The physician carefully evaluates the patient, integrates laboratory findings with bedside observations, considers competing diagnoses, anticipates complications, and modifies treatment as new information becomes available. Clinical decisions are individualized rather than formulaic. Evidence informs the decision-making process, but it does not replace it. The physician remains intellectually engaged throughout the patient’s illness, continually asking, “Does this patient fit the guideline—or is this patient telling me something different?”
The right side illustrates the opposite extreme—the physician transformed into an automaton. Here, success is measured less by thoughtful decision-making than by compliance with predetermined protocols. Clinical encounters become exercises in checklist completion. Computers generate treatment recommendations, performance dashboards monitor adherence, and deviations from established pathways often require justification. In this environment, the clinician’s role shifts from independent thinker to protocol executor.
Several forces have contributed to this transformation. Electronic medical records increasingly guide clinicians through structured workflows. Regulatory agencies evaluate hospitals using quality metrics tied to protocol compliance. Insurance companies often reimburse care based on standardized performance measures. Fear of litigation encourages physicians to follow published guidelines even when they believe a different approach may better serve an individual patient. Hospital administrators understandably seek consistency and measurable outcomes, while younger physicians are frequently trained in environments where adherence to protocols is emphasized over independent reasoning.
Perhaps nowhere is this tension more apparent than in the management of sepsis. Sepsis is among the most biologically heterogeneous syndromes encountered in medicine. The infecting organism may be bacterial, viral, or fungal. Patients differ enormously in age, immune function, genetic susceptibility, comorbid illness, source of infection, duration of illness before presentation, and the nature of their inflammatory response. Some patients are profoundly hyperinflammatory, while others exhibit immune paralysis. Some require aggressive fluid resuscitation; others develop worsening pulmonary edema if excessive fluids are administered. Some respond dramatically to vasopressors; others require entirely different physiological strategies. It is therefore difficult to argue that a single protocol can optimally treat every patient.
Clinical guidelines acknowledge this heterogeneity. Most guidelines explicitly state that they are intended to support—not replace—clinical judgment. Yet in many healthcare systems, guidelines have become performance measures. Physicians are evaluated on how closely they follow protocols rather than how effectively they care for individual patients. A clinician who thoughtfully departs from a protocol for sound physiological reasons may nevertheless be criticized for noncompliance.
This creates a subtle but important shift in priorities. The focus moves from asking “What does this patient need?” to asking “What does the protocol require?” Compliance becomes the goal rather than improved patient outcomes.
History reminds us that many major advances in medicine arose because physicians questioned accepted dogma. Handwashing to prevent puerperal fever, Helicobacter pylori as the cause of peptic ulcer disease, thrombolysis for myocardial infarction, low tidal volume ventilation in ARDS, and early mobilization in the ICU all challenged prevailing beliefs. If medicine had consisted solely of following existing protocols, many of these breakthroughs would have been delayed for years or decades.
This is not an argument against evidence-based medicine. On the contrary, evidence should remain the cornerstone of modern practice. However, evidence-based medicine was originally conceived as the integration of three equally important components:
The best available scientific evidence.
The clinician’s expertise and experience.
The patient’s individual values, preferences, and biological characteristics.
Over time, the second and third components have too often become overshadowed by the first. Evidence has increasingly been equated with guidelines, while clinical expertise has been undervalued. Yet evidence itself evolves. Guidelines change as new studies emerge. What is considered best practice today may be abandoned tomorrow. Clinical judgment remains essential precisely because medicine is never static.
Patients do not read textbooks, nor do they present according to protocol. They frequently have multiple interacting diseases, atypical presentations, and physiological responses that cannot be captured by an algorithm. Experienced clinicians recognize patterns that no artificial intelligence or checklist currently can. They appreciate subtle changes in appearance, behavior, breathing, and hemodynamics that often precede objective deterioration. They know when to accelerate treatment, when to withhold therapy, and when to reconsider the diagnosis entirely.
The greatest physicians are therefore not those who memorize the most guidelines, but those who know when guidelines apply—and when they do not.
The goal should never be to eliminate protocols. Well-designed protocols remain invaluable tools that improve consistency, reduce preventable errors, and ensure that proven therapies are not overlooked. But protocols should serve physicians—not replace them. They should provide a framework for decision-making rather than a substitute for it.
Ultimately, the future of medicine depends not on producing clinicians who simply follow algorithms, but on cultivating physicians who remain curious, skeptical, compassionate, and intellectually engaged—professionals who use evidence wisely while never losing sight of the unique individual before them.
Medicine is fundamentally a profession of judgment rather than manufacturing. Patients are not identical products moving along an assembly line. They are individuals with unique biology, values, and clinical circumstances. The best outcomes arise when evidence, experience, and patient-specific factors are integrated thoughtfully by a skilled clinician.
The central message is therefore not that protocols are inherently harmful, but that protocols should assist physicians—not replace them. Modern medicine requires both scientific evidence and human judgment. When clinicians are reduced to automatons whose primary role is protocol compliance, patient-centered care is diminished. Our goal should be to cultivate physicians who think critically, question continuously, personalize treatment, and place the individual patient—not the algorithm—at the center of every clinical decision
Medicine advances when doctors think. Patients benefit when physicians are empowered to exercise judgment. The challenge for modern healthcare is not choosing between evidence and experience, but restoring the balance between them.

Amen Dr. 'M'. Thank you for your analytical gifts, and sound mind.
Many Blessings
You’re absolutely correct with the “adherence to protocols, checklists, and electronic prompts rather than independent clinical reasoning.”
Even back in the 90s I remember one class I was teaching. I asked the students if, instead of a lecture, they’d like to go over to the hospital and observe some real clinical stuff. All I got was confused looks and “uh, is it on the exam?”
Learning to check the right boxes is what’s passing for “medicine” these days. 🤦